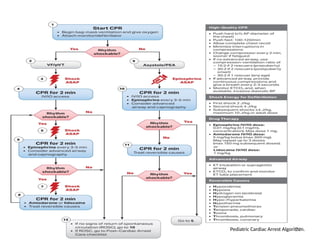
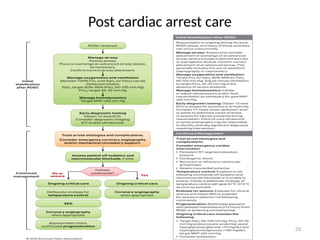
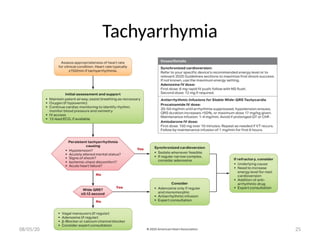
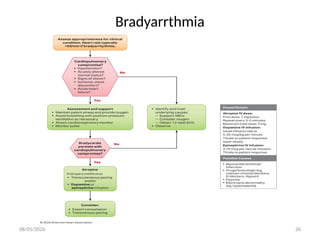
Comprehensive Guide to Basic and Advanced Cardiac Life Support with 2025 AHA Updates
Detailed overview of BLS and ACLS protocols, pediatric and adult resuscitation algorithms, 2025 AHA guideline updates, team dynamics, and post-cardiac arrest care for healthcare professionals.
08/05/2026 10
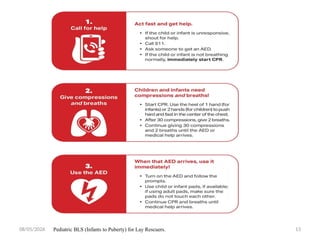
Pediatric BLS
•Respiratory conditions remain the major cause of cardiac
arrest in infants and children
• For out-of-hospital cardiac arrest (OHCA) in infants and
children, providing breaths in addition to chest compressions
improves survival
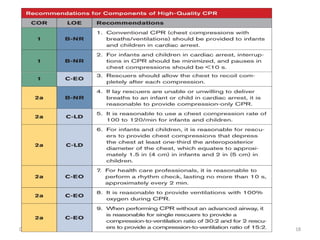
• A respiratory rate of 20 to 30 breaths per minute
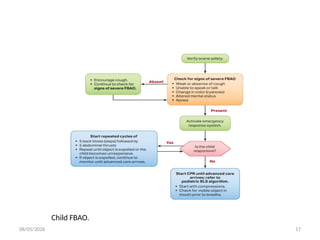
• For infants with severe foreign-body airway obstruction
(FBAO), repeated cycles of 5 back blows alternating with 5
chest thrusts is recommended.
11.
08/05/2026 11
Pediatric BLS
•Abdominal thrusts are not recommended in infants.
• For children with severe FBAO, repeated cycles of 5 back
blows alternating with 5 abdominal thrusts is recommended.
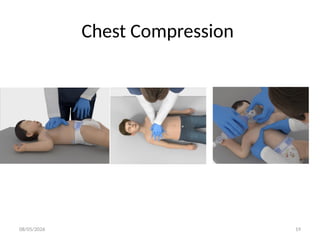
• For infants, the recommended compression techniques
include using either the 1-hand technique or the 2 thumb–
encircling hands technique.
• If the rescuer cannot physically encircle the chest, it is
recommended to compress the chest with the heel-of-1-hand
technique.
• The use of 2 fingers along the sternum was eliminated due to
ineffectiveness in achieving proper depth.
12.
08/05/2026 12
Pediatric BLS
•An automated external defibrillator (AED) should be attached
as soon as possible using a pediatric attenuator and pediatric
pads if available.
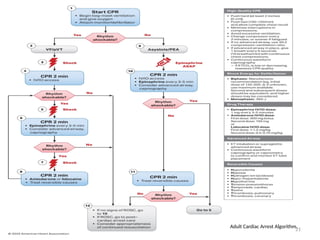
• Prompt defibrillation for ventricular fibrillation (VF) and
pulseless ventricular tachycardia (pVT) is critical, with
minimization of peri-shock pauses.
08/05/2026 15
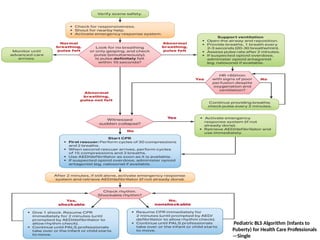
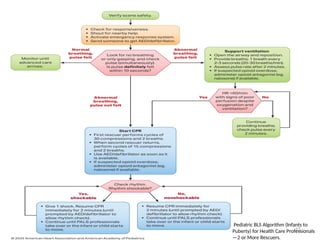
Pediatric BLSAlgorithm (Infants to
Puberty) for Health Care Professionals
—2 or More Rescuers.
16.
08/05/2026 16
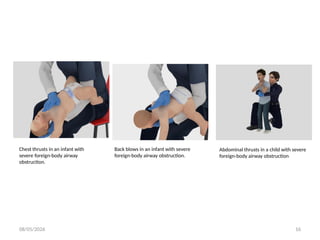
Chest thrustsin an infant with
severe foreign-body airway
obstruction.
Back blows in an infant with severe
foreign-body airway obstruction.
Abdominal thrusts in a child with severe
foreign-body airway obstruction
08/05/2026 27
2025 AHAupdates
Chain of survival Universal chain
Choking 5 back blows + 5 thrusts
Infant CPR Two-finger method removed
Naloxone Increased emphasis
IV vs IO IV preferred first
Temperature control ≥36 hours
Cognitive aids Recommended
28.
08/05/2026 28
High performanceteam dynamics
• Clear roles and responsibilities
• Knowing your limitation
• Constructive intervention
• Closed loop communication
• Clear message
• Mutual respect
• Debriefing
29.
08/05/2026 29
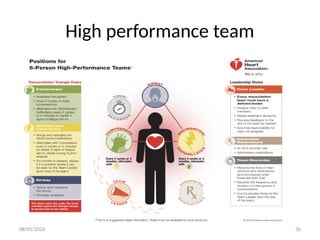
High performanceteam
• Team leader
• Compressor
• Airway manager
• Defibrillator operator
• Medication nurse
• Recorder
08/05/2026 32
Neurologic Prognostication
•Unconcious patient, M≤3 at 72 hours without confounder
• At least two of the foolowing is associated with poor outcome
no pupillary and corneal reflex at ≥72 hours
Bilaterally absent N20 SSEP wave
Highly malignant EEG at > 24 hours
NSE > 60 ug/l at 48 and or 72 hours
Status myoclonus ≤ 72 hours
Diffuse and extensive anoxic injury on brain CT/MRI
33.
08/05/2026 33
Key Messages
•Early recognition
• High-quality CPR
• Early defibrillation
• Effective team dynamics
• Adherence to ACLS algorithms
• Treat reversible causes
• Optimize post-arrest care