WHO Partograph 1994 vs WHO Labour
Care Guide 2020 – Complete Comparison
Dr Muhammad M Al Hennawy
Senior Consultant of Obestetrics ,
gynecology, and Infertility
https://mmhennawy.github.io
https://www.youtube.com/c/mmhennawy
https://www.slideshare.net/
muhammadelhennawy5
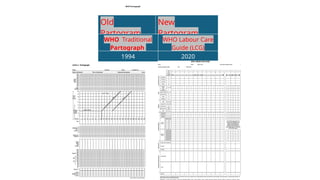
Old Partogram New Partogram
WHO Traditional
Partograph
WHO Labour Care Guide
(LCG)
1994 2020
Partograph
• A partograph is a graphical
record of the observations
made of a women in labour
• For progress of labour and
salient conditions of the
mother and fetus
• It was developed and
extensively tested by the
world health organization
WHO
History Of Partogram
• Friedman's partogram devised in 1954 was
based on observations of cervical dilatation
and foetal station against time elapsed in
hours from onset of labour. The time onset
of labour was based on the patient's
subjective perception of her contractility.
Plotting cervical dilatation against time
yielded the typical sigmoid or 'S' shaped
curve and station against time gave rise to
the hyperbolic curve. Limits of normal were
defined
Philpott and Castle
• in 1972 introduced the concept of "ALERT" and "ACTION"
lines. The aim of this study was to fulfill the needs of
paramedical personnel practising obstetrics in
Rhodesian African primigravidae.
• The alert line represented the mean rate of progress of
the slowest 10% of patients in the African population
whom they served. Alert line was drawn at a slope of 1
centimetre/hr for nulliparous women starting at zero
time i.e. time of admission .
• Action line drawn four hours to the right of the alert line
showing that if the patient has crossed the alert line
active management should be instituted within 4 hours,
enabling the transfer of the patient to a specialised
tertiary care centre.
• The action line was subsequently drawn two hours to the
right of the alert line
Studd's labour stencils
• It were introduced in 1972. These
stencils predicted the expected
pattern of progression of labour
based on the extent of dilataton
achieved by the time the patient is
admitted (zero time). Curves showing
the average course of cervical
dilatation were constructed for various
dilatation on admission. Five separate
patterns representing normal labour
progression were constructed. The
curves were transcribed onto acrylic
stencils On admission in labour, the
cervical dilatation was assessed and a
stencil was used to draw the relevant
pencil line of expected progress on the
patient's cervicograph which was then
completed. Those crossing the
nomogram line were found to have a
three fold increase in instrumental
delivery.
Evolution of Labour Monitoring
• 1954 – Friedman
• Introduced the classic sigmoid labour curve.
• Assumed a relatively constant cervical dilatation rate.
• 1972 – Philpott
• Developed the first practical Partograph.
• Introduced:
• Alert Line
• Action Line
• 1994 – WHO Partograph
• Standardized worldwide.
• Active labour started at 4 cm.
• Action line = 4 hours after alert line.
• 2010–2018
• Large observational studies (including Zhang et al.) showed labour progresses more slowly and variably
than previously thought.
• 2020 – WHO Labour Care Guide
• Active labour begins at 5 cm.
• Alert Line removed.
• Action Line removed.
• Evidence-based time limits introduced.
• Woman-centered care integrated.
WHO Partograph
*Old 1994 and New 2020*
WHO Partograph
Old
Partogram
New
Partogram
WHO Traditional
Partograph
WHO Labour Care
Guide (LCG)
1994 2020
Overview
• The partograph can be used by health workers with
adequate training in midwifery who are able to :
- observe and conduct normal labour and delivery.
- Perform vaginal examination in labour and assess cervical
diltation accurately
- plot cervical diltation accurately on a graph against time
• There is no place for partograph in deliveries at home
conducted by attendants other than those trained in
midwifery
• Whether used in health centers or in hospitals , the
partograph must be accompanied by a program of training
in its use and by appropriate supervision and follow up
Objectives
• early detection of abnormal progress of a labour
• prevention of prolonged labour
• recognize cephalopelvic disproportion long before
obstructed labour
• assist in early decision on transfer , augmentation , or
terminjation of labour
• increase the quality and regularity of all observations of
mother and fetus
• early recognition of maternal or fetal problems
• the partograph can be highly effective in reducing
complications from prolonged labor for the mother
(postpartum hemorrhage, sepsis, uterine rupture and its
sequelae) and for the newborn (death, anoxia, infections,
etc.).
Why Did WHO Change?
• Labour is highly variable
• 1 cm/hour is not universal
• Active labour begins at 5 cm
• Reduce unnecessary interventions
• Promote woman-centred care
Advantages of the LCG
• Evidence-based
• Individualized care
• Better documentation
• Respectful maternity care
• Appropriate interventions
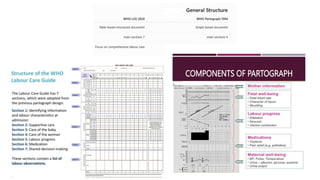
1 identifying informarions and labour
characters at admission
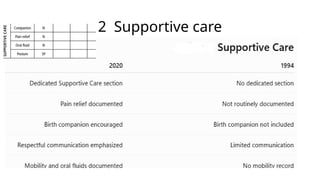
2 Supportive care
Record Supportive Care (New in LCG)
• Birth companion
• Pain score
• Pain relief
• Oral fluids
• Mobility
• Position
• Emotional support
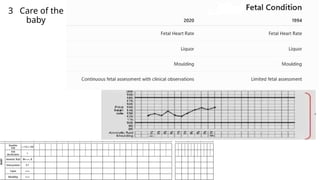
3 Care of the
baby
Fetal heart rate
Basal fetal heart rate?
• < 160 beats/mi =tachycardia
• > 120 beats/min = bradycardia
• >100 beats/min = severe bradycardia
Decelerations? yes/no
Relation to contractions?
n Early
n Variable
n Late – -----Auscultation - return to baseline
> 30 sec  contraction
----- Electronic monitoring
peak and trough (nadir)
 > 30 sec
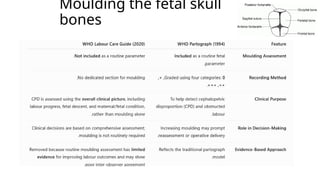
Membranes and liquor
Moulding the fetal skull
bones
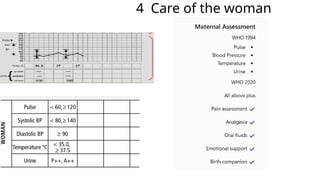
4 Care of the woman
Maternal condition
Name / DOB /Gestation
Medical / Obstetrical issues
Assess maternal condition regularly by monitoring :
• drugs , IV fluids , and oxytocin , if labour is augmented
• pulse every 30 minutes , blood pressure every 4 hour
• Temperature every 2 hour
• Urine volume , analysis for protein and acetone
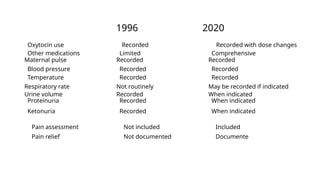
1996 2020
Oxytocin use Recorded Recorded with dose changes
Other medications Limited Comprehensive
Maternal pulse Recorded Recorded
Blood pressure Recorded Recorded
Temperature Recorded Recorded
Respiratory rate Not routinely May be recorded if indicated
Urine volume Recorded When indicated
Proteinuria Recorded When indicated
Ketonuria Recorded When indicated
Pain assessment Not included Included
Pain relief Not documented Documente
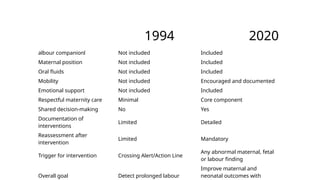
1994 2020
albour companionl Not included Included
Maternal position Not included Included
Oral fluids Not included Included
Mobility Not included Encouraged and documented
Emotional support Not included Included
Respectful maternity care Minimal Core component
Shared decision-making No Yes
Documentation of
interventions
Limited Detailed
Reassessment after
intervention
Limited Mandatory
Trigger for intervention Crossing Alert/Action Line
Any abnormal maternal, fetal
or labour finding
Overall goal Detect prolonged labour
Improve maternal and
neonatal outcomes with
5 Labour
progress
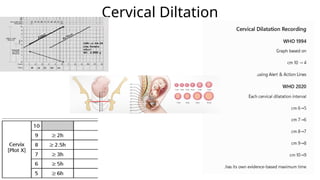
•Cervical dilatation
•Descent of the fetal
head
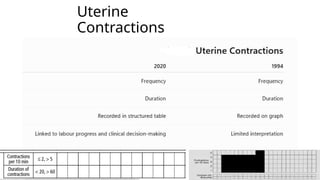
•Uterine contractions
•Frequency
•Duration
Uterine
Contractions
Recording of uterine contraction
latent phase
Second Stage
Cervical Diltation
Descent of the fetal
head
• It should be assessed
• by abdominal examination
• immediately before doing a
vaginal examination, using the
rule of fifth to assess engagement
• The rule of fifth means the
palpable fifth of the fetal head are
felt by abdominal examination to
be above the level of symphysis
pubis
• When 2/5 or less of fetal head is
felt above the level of symphysis
pubis , this means that the head is
engage , and by vaginal
examination , the lowest part of
vertex has passed or is at the level
Assessing descent of the fetal head by vaginal
examination;
0 station is at the level of the ischial spine (Sp).
Occiput transverse
positions
Occiput anterior positions
Fetal position
6 medication
7 Shared Decision making
Decisions Should Be Based on the Whole Clinical Picture
• Management should depend on:
• Maternal condition
• Fetal condition
• Uterine activity
• Labour progress
• Clinical judgement
• —not solely on cervical dilatation.
Make an Individualized Decision
• Continue observation
• ARM
• Oxytocin augmentation
• Referral
• Operative vaginal delivery
• Caesarean section
Approach to labour problems
Management to labour
problems
• The Labour Care Guide (LCG) follows the principle:
• Observe Assess Decide Document
→ → →
• NOT:
• Observe Cross the Alert/Action Line Intervene
→ →
• Golden Rule
• LCG = Reassess Think Decide
→ →
• NOT:
• Delay = Intervention
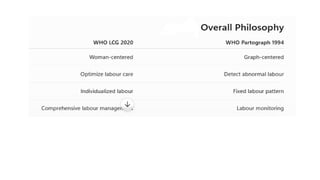
•Partograph 1994 Depends on Lines (Alert & Action).
•Labour Care Guide 2020 Depends on Evidence-based thresholds + Clinical judgment +
Woman-centered car
The Key Message of This Slide
Major Changes in 2020 (Key Messages)
1.Active labour starts at 5 cm, not 4 cm.
2.Alert Line and Action Line have been eliminated.
3.The 1 cm/hour rule is no longer recommended.
4.Labour progress is assessed using evidence-based time
limits for each centimetre of cervical dilatation.
5.Continuous documentation of supportive and respectful
maternity care.
6.Shared decision-making with the woman is encouraged.
7.Dedicated monitoring of the second stage of labour.
8.Clinical actions are triggered by any abnormal maternal,
fetal, or labour finding, not only slow cervical dilatation.
Thank You
From Monitoring Labour…
To Caring for Women
"The greatest advance in modern obstetrics is not performing more interventions—
it is knowing when intervention is truly needed."