Stroke: A Clinical Overview
Exploring Types, Prevalence, and
Pathophysiology
Shubham B. Kendre (MPT Neuro)
What is Stroke?
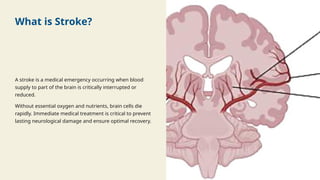
A stroke is a medical emergency occurring when blood
supply to part of the brain is critically interrupted or
reduced.
Without essential oxygen and nutrients, brain cells die
rapidly. Immediate medical treatment is critical to prevent
lasting neurological damage and ensure optimal recovery.
Spot a Stroke (F.A.S.T.)
Face & Arm
Look for one side of the face
drooping or numbness. Check
if one arm drifts downward
when raised simultaneously.
Speech
Listen for slurred speech. Ask
the person to repeat a simple
sentence to check for
comprehension issues or
confusion.
Time
Time is brain. If these
symptoms are observed, call
emergency services
immediately to minimize long-
term damage.
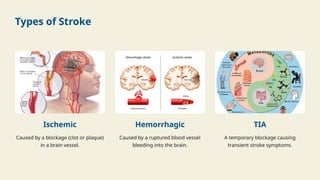
Types of Stroke
Ischemic
Caused by a blockage (clot or plaque)
in a brain vessel.
Hemorrhagic
Caused by a ruptured blood vessel
bleeding into the brain.
TIA
A temporary blockage causing
transient stroke symptoms.
Ischemic vs Hemorrhagic
Ischemic (87% of Cases)
Results from thrombosis or embolism severely
reducing blood flow. Rapid reperfusion therapy
(like tPA or thrombectomy) is the primary time-
sensitive treatment designed to salvage the
ischemic penumbra before irreversible infarction
occurs.
Hemorrhagic (13% of Cases)
Results from intracerebral or subarachnoid
bleeding, often due to uncontrolled hypertension
or vascular anomalies like aneurysms. It presents
with a higher acute mortality rate and requires
immediate pressure management and
occasionally surgical intervention.
Prevalence in Maharashtra
388
per 100,000 Population
High Burden in Rural Regions
A comprehensive study in rural Gadchiroli, Maharashtra
revealed a staggering crude stroke prevalence of 388 per
100,000 individuals, significantly higher than previous rural
estimates globally.
This rising burden highlights a critical need for localized
healthcare interventions and risk factor screening.
Pathophysiology of stroke
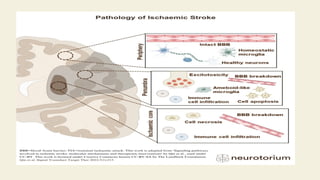
An ischemic stroke occurs when a blood vessel supplying the brain is obstructed, usually by a
thrombus (blood clot formed locally) or an embolus (a clot that traveled from elsewhere, often
the heart).
When blood flow drops below a critical threshold, a destructive biochemical cascade begins:
Energy Failure: Without oxygen and glucose, the brain cannot produce ATP (cellular energy).
Ion Pump Failure & Depolarization: The lack of ATP causes the sodium-potassium pumps
on cell membranes to fail. Sodium and water rush into the cells, causing them to swell
(cytotoxic edema).
Excitotoxicity: The depolarized neurons release massive amounts of glutamate, an excitatory
neurotransmitter.This overstimulates neighboring receptors, causing a lethal influx of calcium
into the cells.
Oxidative Stress & Cell Death: The calcium overload activates destructive enzymes
(proteases, lipases) and generates reactive oxygen species (free radicals).This shreds the cell's
structural proteins and DNA, leading to rapid cell death (necrosis).
The Ischemic Cascade
1. Hypoperfusion
Blood flow drops below critical
thresholds, starving neurons of
oxygen and glucose.
2. Energy Failure
Depletion of ATP leads to the
failure of energy-dependent
cellular ion pumps.
3. Excitotoxicity
Depolarization triggers massive
glutamate release, causing toxic
intracellular calcium influx.
4. Cell Death
Free radical production and
enzymatic cascades lead to
irreversible necrosis and
apoptosis.
Pathophysiology of stroke
A hemorrhagic stroke occurs when a weakened blood vessel ruptures and bleeds into the surrounding brain.This is most
commonly caused by chronic high blood pressure, aneurysms, or vascular malformations. It is subdivided into
Intracerebral Hemorrhage (ICH) (bleeding directly into brain tissue) and Subarachnoid Hemorrhage (SAH)
(bleeding into the fluid-filled space surrounding the brain).
The pathophysiology here involves a two-stage mechanism of injury:
Primary Injury (Mechanical)
Mass Effect: As blood pools, it creates a rapidly expanding hematoma. Because the skull is a rigid box, this adds physical
volume, dramatically increasing intracranial pressure (ICP).
TissueTearing: The sheer force of the high-pressure arterial bleed mechanically tears and compresses adjacent brain
tissue and neurons.
Secondary Injury (Chemical)
BloodToxicity: Blood is highly toxic when it comes into direct contact with brain parenchyma.
Iron andThrombin: As the pooled red blood cells break down, they release hemoglobin, which degrades into free iron.
The clotting process also produces thrombin. Both iron and thrombin trigger severe inflammation, generate free radicals,
and cause a breakdown of the blood-brain barrier.
Vasospasm: In subarachnoid hemorrhages, the irritating presence of blood on the outside of blood vessels can cause them
to violently spasm and constrict days later, leading to delayed ischemic strokes.
Hemorrhagic Pathophysiology
Primary Injury
The initial vessel rupture causes blood to rapidly
accumulate, forming a space-occupying
hematoma. This mass physically compresses
adjacent brain tissue and dramatically increases
Intracranial Pressure (ICP).
Secondary Injury
Blood breakdown products induce local
inflammation and edema. Critically, elevated ICP
directly reduces Cerebral Perfusion Pressure
(CPP), leading to secondary global brain ischemia.
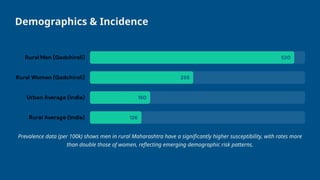
Demographics & Incidence
Prevalence data (per 100k) shows men in rural Maharashtra have a significantly higher susceptibility, with rates more
than double those of women, reflecting emerging demographic risk patterns.
Non-Modifiable Risk Factors
Age: The risk of stroke doubles every decade after the age of 55, making age the strongest independent risk factor.
Gender: Men generally have a higher incidence of stroke at younger ages compared to women, although women
have higher lifetime risks due to longevity.
Genetics & Family History: A familial history of stroke or genetic disorders (like sickle cell disease) significantly
elevates risk.
Prior Events: Individuals with a history of a previous stroke or Transient Ischemic Attack (TIA) are highly vulnerable to
recurrence.
Modifiable Risk Factors
Hypertension is the single most important
modifiable risk factor, directly damaging blood
vessels.
Diabetes Mellitus exacerbates vascular damage and
increases ischemic risk.
Smoking and Hyperlipidemia heavily accelerate the
progression of atherosclerosis.
Sedentary Lifestyle and Obesity increase systemic
risk and compounding comorbidities.
Questions?
Effective stroke management relies on rapid action, prevention, and sustained
rehabilitation.
Shubham B. Kendre (MPT Neuro)
Image Sources
https://www.frontiersin.org/files/Articles/1622630/xml-images/fneur-16-1622630-g001.webp
Source: www.frontiersin.org
https://www.mayoclinic.org/-/media/kcms/gbs/patient-consumer/images/2013/11/15/17/44/ds00150_ds01030_my00077_im00074_r7_ischemicstrokethu_jpg.jpg
Source: www.mayoclinic.org
https://media.istockphoto.com/id/2156333386/vector/hemorrhagic-and-ischemic-strokes.jpg?s=612x612&w=0&k=20&c=x9tzUQHE6YUsqkmkQ7Z6zuzvKRvhBMMwi-Hi-
VvIhuQ=
Source: www.istockphoto.com
https://www.ijbs.com/v19/p2974/toc.jpg
Source: www.ijbs.com
https://media.easy-peasy.ai/bd11b4c7-d320-42db-bb33-e3f9ee4f6c3b/d4db8a4d-19a5-4d94-9e2b-35cd66edd868_medium.webp
Source: easy-peasy.ai