Comprehensive Clinical Insights into Managing Borderline Personality Disorder
1.
THE CLINICAL CHALLENGEOF
MANAGING BORDERLINE
PSYCHOPATHOLOGY
PRESENTERS- DR. SIMRANJIT SINGH, DR. CHIRAG SINGH
COORDINATOR- DR. ADWITIYA RAY
CHAIRPERSON- DR. PRITI SINGH
2.
FLOW OF SEMINAR
•Introduction
• Comparative nosology
• Etiology
• Stigma and perception associated with the diagnosis of borderline
personality disorder
• Challenges in the clinical assessment
• Challenges in treatment and clinical management
• Challenges in managing suicidal crises
• Conclusion
PERSONALITY
“Personality is thedynamic organization within the individual of
those psychophysical systems that determine his characteristic
behavior and thought”
[Allport; 1961]
5.
PERSONALITY DISORDER
A personalitydisorder is an enduring pattern of inner experience and
behavior that deviates markedly from the norms and expectations of
the individual’s culture, is pervasive and inflexible, has an onset in
adolescence or early adulthood, is stable over time, and leads to
distress or impairment.
[DSM-5-TR]
6.
Borderline personality disorder(BPD) is a chronic psychiatric
disorder characterized by pervasive patterns of affective instability,
self-image disturbances, instability of interpersonal relationships,
marked impulsivity, and suicidal behavior (suicidal ideation and
attempt) causing significant impairment and distress in an
individual’s life.
[Kulacaoglu F.; 2018]
7.
• Patients withBPD suffer considerable morbidity which complicates
medical care compared to other individuals.
• BPD has been identified as the most common personality disorder
in clinical populations, and it is associated with significant
individual and societal costs.
• Since BPD is associated with receiving clinical attention and causes
psychosocial impairments, it is more widely studied than other
personality disorders.
[Porter C. et al; 2020]
8.
ORIGINS AND EVOLUTIONOF THE BORDERLINE
DIAGNOSIS
• Stern (1938) introduced the term “Borderline” to describe what he
understood as, “on the cusp” of both psychotic and neurotic.
• The term “borderline” entered the psychological lexicon as a word
that described a group of mental health out-patients who did not
seem to fit comfortably with a diagnosis of psychotic or neurotic
[Ahluwalia CA. et al; 2019]
9.
• Kernberg (1967)made an effort to define their intrapsychic
features.
• Kernberg described borderline personality organization (BPO) as an
intermediary level of internal personality organization, framed on
one side by more severe psychotic personality organization and on
the other by less severe neurotic organization.
10.
• The BPOconstruct encompassed all serious forms of personality
disorder and was characterized by three intrapsychic characteristics:
1) Identity diffusion;
2) Primitive defenses (e.g., splitting, denial, projection, action, and
projective identification)
3) Reality testing that was generally intact, but vulnerable to
alterations and failures.
• BPO is not synonymous with BPD but formed the foundation for
the integration of BPD into the DSM-III.
[Skodol AE. et al; 2002]
11.
PREVALANCE
• BPD isrelatively common in the general population, with a point
prevalence of around 1%.
• The prevalence of BPD is substantially higher in clinical settings,
around 12% in the outpatient psychiatric population and 22% among
inpatients.
[Ellison WD. et al; 2018]
12.
• The ratioof females to males with the disorder is also greater in the
clinical population.
• In contrast to the clinical setting ratio, in two epidemiologic surveys
of United States general population, the lifetime prevalence of BPD
was found to be similar in males and females.
• This result can be interpreted as women with BPD are more likely to
seek treatment than men. About 80% of patients who receive
treatment for BPD were reported to be women.
[Kulacaoglu F.; 2018]
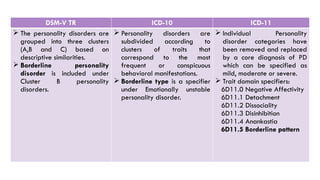
DSM-V TR ICD-10ICD-11
The personality disorders are
grouped into three clusters
(A,B and C) based on
descriptive similarities.
Borderline personality
disorder is included under
Cluster B personality
disorders.
Personality disorders are
subdivided according to
clusters of traits that
correspond to the most
frequent or conspicuous
behavioral manifestations.
Borderline type is a specifier
under Emotionally unstable
personality disorder.
Individual Personality
disorder categories have
been removed and replaced
by a core diagnosis of PD
which can be specified as
mild, moderate or severe.
Trait domain specifiers:
6D11.0 Negative Affectivity
6D11.1 Detachment
6D11.2 Dissociality
6D11.3 Disinhibition
6D11.4 Anankastia
6D11.5 Borderline pattern
1. Psychosocial factors:
•Childhood physical, sexual, or emotional abuse or neglect.
2. Genetic factors:
• Candidate gene study- Association between a haplotype containing
the short allele in the serotonin transporter gene (the serotonin
transporter-linked promoter region [5-HTTLPR] in SLC6A4) and the
development of borderline personality disorder.
[Leichsenring F. et al; 2011]
17.
• Gene–gene interactionsstudies- An interaction between the Met
allele of the catecholamine-O methyltransferase gene (COMT) and
the short allele of 5-HTTLPR was reported in patients with
borderline personality disorder.
• Polymorphisms in 5-HTTLPR, tryptophan hydroxylase gene (TPH-
2), variable number tandem repeat of the high-activity monoamine
oxidase A gene promoter allele.
18.
3. Neurobiology:
Anatomical MRIfindings
• Reduced volume in the amygdala.
• Reduction in grey matter volume in the anterior cingulate gyrus,
posterior cingulate gyrus, or hippocampus, and a reduced size of the right
parietal cortex.
• Reduced grey matter volumes in the dorsolateral cortex and in the left
orbitofrontal cortex were reported in an early stage of borderline
personality disorder.
[Ding JB.; 2021]
19.
PET Findings
• Fronto-limbicdysfunction: Changes in frontal glucose
metabolism (a hypometabolism was more often reported than a
hypermetabolism).
• Abnormality in prefrontal brain regions associated with emotional
control function in borderline personality disorder.
• More activation of the orbital cortex.
[Karas KH. et al; 2021]
20.
FUNCTIONAL MRI FINDINGS
•The fMRI analysis showed significant reduced functional
connectivity in the BPD group compared to healthy controls
between the amygdala (right and left) and the frontal pole.
• Decreased connectivity was also found between amygdala (left)
and precuneus and between amygdala (left) and temporal pole.
[Mitolo M. et al; 2024]
21.
• Increased amygdalaactivation compared with control individuals
when viewing aversive emotion-inducing slides or when viewing
pictures of human emotional facial expressions.
• Activation of the prefrontal cortex was reported for patients with
borderline personality disorder after inducing negative emotions,
possibly indicating an attempt to control intensive emotions.
[Wrege JS. et al; 2021]
22.
• When askedto use a cognitive strategy to control their responses to
unpleasant pictures by distancing themselves from the image, those
with borderline personality disorder had less blood-oxygen-level
dependent (BOLD) signal changes in the anterior cingulate and had
greater activation in the superior temporal sulcus and superior frontal
gyrus than did controls.
• Thus, patients with borderline personality disorder do not seem to
engage the cognitive control regions to the extent that healthy
individuals do, which might contribute to the affective instability of
this disorder.
23.
• These reportslend support to the assumption of a dysfunctional
fronto-limbic network in borderline personality disorder.
• This network seems to involve the anterior cingular cortex, the
orbitofrontal cortex, the dorsolateral prefrontal cortex, the
hippocampus, and the amygdala.
• The phenomenonof stigma and negative attitudes surrounding the
diagnosis of BPD has been widely researched.
• Attitudes held by health professionals including emergency staff,
mental health nurse, and the multidisciplinary team have been
explored extensively and indicate that long-standing stigma remains
attached to this disorder.
[Aguirre B.; 2016]
26.
• Further, manyhealth professionals do not consider BPD to be a
genuine diagnosis and believe the diagnosis to be self-induced or
chosen.
• Subsequently, it has been found that people with BPD either are not
informed about their condition or are told they have a differing
diagnosis, such as bipolar affective disorder, compromising the
principle of veracity.
27.
HEALTH PROFESSIONALS’
PERCEPTIONS OFINDIVIDUALS WITH
BORDERLINE PERSONALITY DISORDER
• A considerable body of research has explored health professionals’
attitudes and approaches towards people with BPD, highlighting the
stigma associated with the diagnosis.
• Findings indicated that health professionals were less validating of
the subjective experiences of individuals with BPD in comparison to
those who have other mental health diagnoses.
[Lester R. et al; 2020]
28.
• These perceptionsappeared to elicit more negative attitudes and
significantly less empathetic responses towards these individuals.
• The characteristic ways that individuals with BPD may behave
during interpersonal transactions with healthcare professionals have
been described as –
Emotionally blackmailing.
Threatening.
Rule-breaking.
Evoking heightened emotional reactions.
29.
• A literaturereview of mental health nurses’ attitudes towards BPD
individuals in acute mental health settings identified that mental
health nurses tended to distance themselves from individuals with
BPD, again contributing to the stigma surrounding the diagnosis.
• A recent study suggested that differing staff perceptions of recovery
in BPD can pose risks for consistent teamwork due to the relational
difficulties associated with the diagnosis.
[Lester R. et al; 2020]
30.
CARERS AND FAMILIES’PERCEPTIONS AND
LIVED EXPERIENCES OF INDIVIDUALS WITH
BORDERLINE PERSONALITY DISORDER
• Some studies highlighted that carers can experience feelings of
being overwhelmed and powerless to help the person because of
their repeated self-harm or suicide attempts.
• Bailey and Grenyer found that burden and grief were significantly
higher for carers of individuals diagnosed with BPD than reported by
carers of those with other mental health diagnoses.
[Lester R. et al; 2020]
31.
• Similar findingswere noted by Kirtley et al. who reported higher
levels of carer burden, stigma, expressed emotion, emotional
overinvolvement, criticism, and perceived threat of strong
emotions in carers of individuals with BPD compared to carers of
individuals with other types of mental health difficulty.
• Giffin discovered that the broader family, as reported by parents
of individuals with BPD, tended to have less tolerance for
behaviors associated with the diagnosis and seemed readier to
express their expectations that they should take more
responsibility for their actions.
IMPULSIVITY
• It isseen in behaviors such as substance misuse, unsafe sexual
activity, disordered eating, and impulsive self-harm.
• It is generally assumed that impulsive behaviors are the product of
being an impulsive individual. High-trait impulsivity is frequently
found in BPD patients and has been defined as a tendency for rapid
and unplanned behaviors.
• There is a tendency to act on urges without regard for the possible
consequences.
[Barker V.; 2015]
35.
• In thestudy of Brodsky et al. impulsivity was the only
characteristic of BPD found to be associated with a higher number
of suicide attempts controlling for diagnoses such as depression
and substance abuse.
• Self-destructive impulsivity probably represents the clinically
most challenging part of the borderline syndrome and, as
suggested by Brodsky et al., monitoring impulsivity in patients in
the course of treatment might be a useful guide to therapeutic
response.
36.
PSYCHIATRIC COMORBIDITY
• Othermental disorders are common in patients with BPD, as
evidenced by the high comorbidity rates reported in numerous
cross-sectional and longitudinal studies.
• The findings of an epidemiological study in the USA suggested that
BPD is rarely diagnosed alone, with high lifetime prevalence rates
in these patients for anxiety disorders (84.8%), mood disorders
(82.7%), substance use disorders (78.2%), and eating disorders
(33.7%).
[Pascual JC.; 2023]
37.
• Similarly, severalother mental disorders also present high rates of
comorbidity with BPD, including posttraumatic stress disorder
(PTSD), attention deficit hyperactivity disorder (ADHD), and
bipolar disorder.
• However, it is important to consider that the symptoms of BPD
frequently overlap with several disorders that share the same
features. For example, while impulsivity with drug abuse or binge
eating is a key marker of BPD, it is also a common symptom in
other disorders.
38.
• Patients withBPD, and co-occurring psychiatric disorders are
often chronic, and may be associated with severely impaired social
and occupational functioning that requires social support;
moreover, they are often difficult to treat.
1. Comorbid Mood Disorders:
Mood disorders are one of the most common disorders in
individuals with BPD.
Up to 80% of patients with BPD present one or more episodes of
major depressive disorder (MDD) in their lifetime and 10–30% of
patients with MDD have co-occurring BPD.
[Pascual JC.; 2023]
39.
2. Comorbid AnxietyDisorders
Lifetime comorbidity between BPD and anxiety disorders is high
(84.8%) and patients with BPD are 14 times more likely to present an
anxiety disorder (especially panic disorder with agoraphobia,
generalized anxiety disorder, and PTSD).
3. Comorbid Eating Disorders
Eating disorders also present high rates of comorbidity with BPD.
In a meta-analysis that examined the prevalence of personality
disorders among individuals with eating disorders, BPD was present in
28% of patients with bulimia nervosa (BN), 25% of those with
anorexia nervosa.
40.
4. Comorbid SubstanceUse Disorders
BPD is generally characterized by greater impulsivity and a
preference for short-term rewards.
This inability to focus on the long term predisposes patients to
develop SUD. The overall lifetime prevalence of SUD in patients
with BPD is approximately 78%.
41.
• The prevalenceof these comorbid disorders tends to decrease
gradually over time in parallel with the clinical improvement of the
typical symptoms that characterize BPD.
• No drugs have yet been approved specifically for the treatment of
BPD.
• The therapeuticrelationship
• What treatment works for BPD patients?
• To hospitalize or not to hospitalize
• Suicidal crises
44.
THE THERAPEUTIC RELATIONSHIP
•An important aspect of BPD individuals’ problems is their
difficulty with regulating their relation to other people and to
maintain nurturing close interpersonal relations over time.
• This extends to the clinical setting where BPD patients all too often
very soon feel disappointed over, rejected or invalidated by their
therapists.
[Campbell K. et al; 2020]
45.
• Many patientsbring with them from their past experiences of
abuse, trauma, neglect, and rejection from families, friends, and
previous healthcare providers.
• Building a trusting relationship with the patient can therefore
prove quite a difficult challenge, but is nevertheless indispensable if
we are going to succeed in the treatment.
46.
• Despite thelack of empirical evidence, a strong therapeutic
alliance is a good candidate among potential suicide preventive
aspects of treatments.
• One of the factors that seem to strengthen a therapeutic alliance is
for the patient early in the treatment to notice progress and
increased coping, however small this improvement may be.
• However, setting too ambitious targets early in the treatment may
work in the opposite direction.
47.
WHAT TREATMENT WORKSFOR BPD PATIENTS?
• About 40 randomized (RCT) and nonrandomized controlled
studies on psychosocial treatments of BPD patients have been
published covering dialectical behaviour therapy, various forms of
cognitive behaviour therapy, problem solving therapy,
psychodynamically oriented psychotherapy and combinations.
[Unruh BT. et al; 2016]
48.
• Nearly 30RCTs on pharmacological treatments have been
published. All of these studies have recently been reviewed by the
NICE in UK.
• According to recommendations from NICE, BPD patients should
be offered psychosocial treatments in the form of a structured care
based on an explicit and integrated theoretical approach used by
both the treatment team and the therapist.
49.
• Lengthy, intensive,and expensive treatment models may have
their limitations in many settings and require high motivation, good
funding, and long-term commitment in order to succeed.
• To be realistic, we should admit that there is a need to develop
shorter and less resource-demanding alternatives for those patients
and those clinical settings who are unable or not motivated to
embark on long-term treatment programs.
50.
HOSPITALIZE OR NOTTO HOSPITALIZE
• BPD patients are high users of inpatient treatment. There is,
however, no evidence that long-term hospitalization is effective in
the treatment of BPD.
• Most experts suggest that if hospital admission is needed, it should
be brief and focus on crisis management.
• Clinicians often find the question of hospitalization one of the most
problematic decisions to make in the management of suicidal crises
in BPD patients.
[Campbell K. et al; 2020]
51.
• This decisioncarries risks in several ways. There is the real risk
that the patient – if not protected by the hospital environment – may
actually commit suicide.
• If hospitalized, on the other hand, the problems may actually
become worse, through negative interplay with staff or fellow
patients – leading to escalating suicide threats, self-mutilating or
suicidal behavior.
52.
• This maylead to extended admissions or premature discharge.
Some patients will rapidly adapt their problem-solving strategies,
once hospital treatment has been introduced to them as an option.
• Having experienced that the hospital staff in general will respond
to their suicidal behavior with the provision of increased support
and attention, there is a danger that they will become shaped to use
suicidal behavior as a strategy for obtaining psychological support.
53.
• Hence, thereare reasons to seek to avoid hospital admission.
• If the need for protection makes hospitalization unavoidable, this
intervention should be brief and it is recommendable to set a fixed
date of discharge (‘next morning’ or ‘over the weekend’) and
clearly inform the patient and her family about this.
[Campbell K. et al; 2020]
54.
SUICIDE IN BORDERLINEPERSONALITY
DISORDER
• The incidence of completed suicide in borderline personality
disorder (BPD) has been unknown until recently.
• In two long-term follow-up studies of borderline patients treated in
residential settings, McGlashan and Stone et al. found that 3% and
9%, respectively, of borderline go on to complete suicide.
[Mehlum L.; 2009]
55.
• Patients withBPD represent 9.33% of all suicides. Mehlum et al.
pointed out that a lack of control of high intensity affects such as
depression, anxiety or anger may increase the tendency towards
suicidal behavior. Thus the notion of BPD as ‘‘the suicidal
personality disorder’’ may be justified.
• On the other hand, the self-destructive tendency in subjects with
BPD may not primarily be due to the personality disorder (PD)
syndrome itself but rather be caused by some secondary or
coexisting mental disorder.
56.
CHALLENGES IN MANAGINGSUICIDAL CRISES
• When managing suicidal crises clinicians are generally faced with
three challenges:
To protect the patient against repetition of attempted suicide and suicide or
irreversible injury.
To reduce the patient’s profound feeling of hopelessness.
To elevate the patient’s subjective experience of quality of life.
[Mehlum L; 2009]
57.
ADDITIONAL CHALLENGES INMANAGING
SUICIDAL CRISES WITH BPD PATIENTS
• For clinicians facing this type of situation with BPD patients,
there are additional challenges:
To help the patient as quickly as possible to return emotionally to a more
acceptable level of arousal and mental functioning.
To manage the crisis in the short term perspective in a way that does not
increase the risk of suicidal behaviors in the long term perspective.
[Mehlum L.; 2009]
58.
MANAGEMENT OF SUICIDALCRISES
• One key to this is to distinguish between suicide attempts on the
one hand and non-suicidal intentional self-harm on the other, even
though the line between these two cannot be sharply drawn.
• Patients can learn how to monitor their urges to self-harm and
suicidal behavior and to distinguish between these.
• When crises emerge this may become very useful with respect to
what intervention approach to adopt.
[Mehlum L.; 2009]
59.
• Another strategythat may facilitate crisis management is for the
patient and therapist early in the treatment to work out a safety
plan describing which high-risk situations or emotional states the
patient needs to be aware of.
60.
DISTINGUISHING SUICIDAL FROMNON-
SUICIDAL DELIBERATE SELF-HARM EVENTS
• Within BPD populations, DSH is a common, though maladaptive,
and often dangerous coping strategy used by individuals who
experience extreme distress and who have not been able to utilize
a more constructive approach to managing their distress.
[Maddock GR.; 2010]
61.
• Changes inattitude toward DSH by clinicians may improve the
treatment experience of those who self-harm and therefore make
treatment compliance a more attractive option for the patient.
• Patients with BPD and DSH may engage in both NS-DSH and S-
DSH events at different times, are motivated by a range of reasons,
may or may not seek treatment, and are also at increased risk of
subsequent suicide.
62.
• SPECIFIC COUNTERTRANSFERENCEREACTIONS
Guilt Feelings
Rescue Fantasies
Transgressions of Professional Boundaries
Rage and Hatred
Helplessness and Worthlessness
Anxiety and Terror
• Countertransference in the psychotherapy of borderline patients
must be viewed as a source of valuable diagnostic and therapeutic
information and not simply as interference with the therapeutic
process.
[Gabbard GO.; 1997]
OTHER CHALLENGE
63.
THE ROLE OFPROJECTIVE IDENTIFICATION
• Ogden has defined it as a three-step procedure in which the following
events occur:
1 An aspect of the self is projectively disavowed by unconsciously placing
it in someone else.
2. The projector exerts interpersonal pressure that coerces the other person
to experience or unconsciously identify with what has been projected.
3. The recipient of the projection (in the therapeutic situation) processes
and contains the projected contents leading to a reintrojection of them by
the patient in modified form.
64.
PHARMACOLOGICAL CHALLENGES
• Comorbiditywith other mental disorders is common in individuals
with BPD.
• The prevalence of these comorbid disorders tends to decrease
gradually over time in parallel with the clinical improvement of the
typical symptoms that characterize BPD.
• No drugs have yet been approved specifically for the treatment of
BPD.
[Pascual JC. et al; 2023]
65.
• Nonetheless, variousmedications are routinely prescribed of label
for this condition despite the lack of agreement among clinical
guidelines.
• Comorbidity between BPD and other psychiatric disorders is
considered to be the main factor associated with both
pharmacological treatment and polypharmacy in these patients.
• In conclusion,managing Borderline Psychopathology presents
unique clinical challenges due to the complex and often
unpredictable nature of the disorder.
• It requires a comprehensive and individualized approach that
incorporates psychotherapy, medication management, and support
from a multidisciplinary team.
• Despite the difficulties, with proper treatment and support,
individuals with Borderline Psychopathology can experience
significant improvements in their symptoms and quality of life.
68.
• Continued researchand collaboration among mental health
professionals are essential to further enhance our understanding
and management of this challenging disorder.
• It is crucial for clinicians to stay updated on the latest evidence-
based practices and to adapt their treatment strategies to meet the
specific needs of each patient.
• By providing a holistic and personalized approach to care, we can
help individuals with Borderline Psychopathology navigate their
symptoms and work towards improved mental health and well-
being.
#14 The borderline pattern specifier has been included to enhance the clinical utility of the classification of personality disorder.
Specifically, use of this specifier may facilitate the identification of individuals who may respond to certain psychotherapeutic treatments.
A complete description of a particular case of personality disorder includes the rating of the severity level and the assignment of the applicable trait domain specifiers (e.g. mild personality disorder with negative affectivity and anankastia.
#26 Accurate diagnosis is imperative for two reasons:
To ensure people receive the correct treatment
To ensure a more accurate prevalence of the condition to facilitate funding for specialist services.
#46 It is important that the therapist actively seeks to motivate and engage the patient in the treatment through using commitment strategies to counteract early drop-out. For the therapist to be consistent and reliable at the same time as she observes her own limits will usually strengthen the therapeutic alliance with the patient.
#58 (and then use the safety plan), what the patient can do herself to manage the situation (e.g. problem solving skills), from whom in the environment the patient can seek help and what professional helpers (with telephone numbers) are available.