Comprehensive Biomedical Waste Management in Healthcare Settings
Overview of biomedical waste types, management rules, segregation, disposal methods, and legislative framework in Indian healthcare facilities to ensure safety and environmental protection.
INTRODUCTION
The lastcentury witnessed the rapid mushrooming of
hospitals dictated by the need of the expanding
population, and the advent and acceptance of
“disposable” has made the generation of hospital
waste a significant factor in biomedical waste
management.
Safe disposal of waste is very difficult
The need of proper hospital waste management
system is of prime importance and is an essential
component of quality assurance.
3.
Waste characteristics
About 10-15%of health care waste is
infected waste.
Mixing of infected waste with household waste should
not be allowed.
Waste quantity
Depends on type of health care setting & services
offered.
Estimated waste generated in Indian hospitals
is 1.59-2.2 kg/bed/day.
4.
DEFINITION
Biomedical wastemeans any waste which is
generated during the diagnosis, treatment or
immunization of human beings or animals or
in research activities pertaining there to or in
the production or testing of biologicals.
(Biomedical Waste Management and Handling Rules1998, India)
Biomedical waste management is sorting of medical
waste in hospital.
5.
PURPOSES OF WASTE
MANAGEMENTSYSTEM
To reduce hazardous nature of waste
To reduce volume of waste
To prevent misuse or abuse of waste
To ensure occupational safety and health
To consider aesthetics
To reuse items that can be of repeat utility
6.
PURPOSES CONTD…
Torecycle waste where possible for another
utility item
Maintain order and cleanliness in hospital
Maintain healthy environment
Prevent spread of infectious diseases
Project good impression of management
Attract more clientele
7.
SOURCES-HEALTH CARE WASTE
Government and Private hospitals
Nursing homes
Physician’s office/clinics
Dispensaries
Primary Health Centres
Medical research and training establishments
Mortuaries
📘 Schedule I– Waste categories and disposal methods
📘 Schedule II – Standards for treatment and disposal
📘 Schedule III – Labeling and color-coding norms
📘 Schedule IV – Bar-coding of bags and containers
📘 Schedule V – Liquid waste treatment standards
📘 Schedule VI – Incinerator standards
📘 Schedule VII – Duties of occupier, operator & authorities
📘 Schedule VIII – Accident reporting & record maintenance formats
SCHEDULE OF BIOMEDICAL WASTE
MANAGEMENT
11.
2.General Waste
Generalwaste consists of all the waste other than
bio-medical waste and which has not been in
contact with any hazardous or infectious, chemical
or biological secretions and does not includes any
waste sharps.
12.
GENERAL WASTE INCLUDES-
News paper, paper and card boxes (dry
waste)
Plastic water bottles (dry waste)
Aluminum cans of soft drinks (dry waste)
Packaging materials (dry waste)
Food Containers after emptying residual food
(dry waste)
Organic / Bio-degradable waste - mostly food
waste (wet waste)
13.
3. OTHER WASTES
Used electronic wastes
Used batteries
Radio-active wastes which are not covered under
biomedical wastes
14.
CLASSIFICATION OF
BIOMEDICAL WASTE
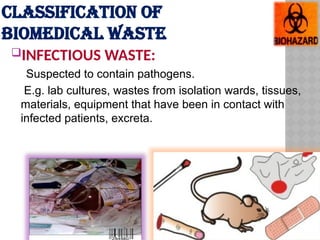
INFECTIOUSWASTE:
Suspected to contain pathogens.
E.g. lab cultures, wastes from isolation wards, tissues,
materials, equipment that have been in contact with
infected patients, excreta.
WASTES WITH HIGHCONTENT OF
SOLVENTS:
Batteries, broken thermometers, BP
gauges, etc.
21.
RADIOACTIVE WASTE CONTAINING
RADIOACTIVESUBSTANCES :
Unused liquids from radiotherapy Lab, research
contaminated glassware, packages and
absorbent paper, patients tested or treated.
22.
LEGISLATIVE FRAMEWORK
Basic principles
Segregationof waste at the health facility level.
Processing and storage for terminal disposal.
Bio-medical waste shall not be mixed with other
wastes.
Bio-medical waste shall be segregated into
containers/ bags at the point of generation in
accordance with BMW Rules 1998 prior to its storage,
transportation, treatment and disposal.
23.
BASIC PRINCIPLES
Colorcoding to support segregation at source
Untreated bio-medical waste not to be stored beyond a period of
48 hours.
Transport waste safely to pick up site.
Identify destination for each type of waste and ensure safe
disposal.
Every authorised person shall maintain records related to any
form of handling of biomedical waste.
24.
INDIAN LEGISLATIONS
TheEnvironment Protection Act 1986
The biomedical waste(management and handling) rules in 20th
July
1998, subsequently revised in 2000, 2003, and 2011.
Now Ministry of Environment, Forest and Climate change in March 2016
have amended the BMWM rules
The "the biomedical waste management rules 2016" are an attestation to
the commitment of the Govt of India.
Further the BMW rules amended in 16th
march 2018.
BMWM RULES 2nd
amendement on 19th
February 2019,
25.
BMW MANAGEMENT RULE
These new rules have increased the coverage, simplified the categorization and
authorization while improving the segregation, transportation and disposal
methods to decrease environmental pollution.
According to Bio-medical Waste Management Rules, 2016, the Central
Pollution Control Board and the State Pollution Control Committees have the
authority to cancel the consent to operate and the authorization of healthcare
institutions, for non-compliant hospitals. Indeed, there have been such
instances in India.
26.
Application of BMWmanagement
rule
Bio-medical Waste Management rules are applicable
to all persons who generate, segregate, collect,
receive, store, treat, transport, dispose, or handle
bio medical waste in any form.
27.
RESEARCH INPUT
Knowledge, attitude,and practices of Bio-medical Waste Management
rules, 2016 , 2018 among health-care workers in a tertiary care setup
Annapurna et .al
Result - Only 68% of the participants knew that the most important step in
waste management is waste segregation. Eighty-two percent of the HCWs
working in this setup knew of the different color-coded bins used for
segregation so that researcher concludes that Training aspects of health-
care waste management should be strengthened so that the current,
existing, and future regulations are practiced diligently and uniformly.
28.
MAJOR SALIENT FEATURESOF BMW MANAGEMENT RULES,
2016 ALONG WITH BIOMEDICAL WASTE MANAGEMENT
(AMENDMENT) RULES, 2018
29.
FEATURES OF BMWRULE,2016 ALONG
WITH BMWM (AMENDMENT) RULES,2018
Scope of the rules has been expanded to include vaccination
camps, blood donation camps, surgical camps or any other
healthcare activity.
Phase-out the use of chlorinated plastic bags, gloves and blood
bags within two years.
Pre-treatment of the laboratory waste, microbiological waste,
blood samples and blood bags through disinfection, sterilization
on-site in the manner as prescribed by WHO or NACO.
30.
FEATURES OF BMWRULE,2016 ALONG
WITH BMWM (AMENDMENT) RULES,2018
Provide training to all its health care workers and immunize
all health workers regularly against diseases like tetanus and
Hepatitis B.
Establish a Bar-Code System for bags or containers
containing biomedical waste for disposal
Report major accidents like needle stick injuries, accidents
caused by fire, blasts during handling of biomedical waste
31.
FEATURES OF BMWRULE,2016 ALONG
WITH BMWM (AMENDMENT) RULES,2018
Procedure to get authorization is simplified.
New rules prescribe more stringent standards for
incinerator to reduce the emission of pollutants in
environment.
Before – the acceptable SPM emission - 150 mg/Nm3
Now – the acceptable SPM emission – 50 mg /Nm3
32.
FEATURES OF BMWRULE,2016 ALONG
WITH BMWM (AMENDMENT) RULES,2018
No hospital/ healthcare facility (occupier) shall establish
on-site treatment and disposal facility, if a service of
“common bio-medical waste treatment facility’’
(CBMWTF) is available at seventy-five kilometres.
Operator of a common bio-medical waste treatment and
disposal facility to ensure the timely collection of bio-medical
waste from the healthcare facility and assist the healthcare
facility in conducting training.
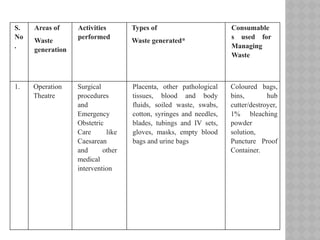
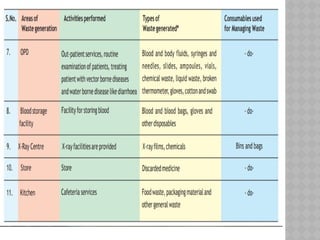
S.
No
.
Areas of
Waste
generation
Activities
performed
Types of
Wastegenerated*
Consumable
s used for
Managing
Waste
1. Operation
Theatre
Surgical
procedures
and
Emergency
Obstetric
Care like
Caesarean
and other
medical
intervention
Placenta, other pathological
tissues, blood and body
fluids, soiled waste, swabs,
cotton, syringes and needles,
blades, tubings and IV sets,
gloves, masks, empty blood
bags and urine bags
Coloured bags,
bins, hub
cutter/destroyer,
1% bleaching
powder
solution,
Puncture Proof
Container.
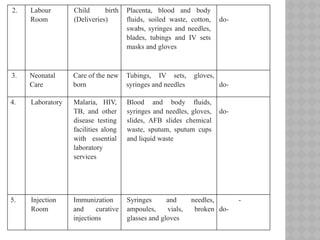
38.
2. Labour
Room
Child birth
(Deliveries)
Placenta,blood and body
fluids, soiled waste, cotton,
swabs, syringes and needles,
blades, tubings and IV sets
masks and gloves
do-
3. Neonatal
Care
Care of the new
born
Tubings, IV sets, gloves,
syringes and needles do-
4. Laboratory Malaria, HIV,
TB, and other
disease testing
facilities along
with essential
laboratory
services
Blood and body fluids,
syringes and needles, gloves,
slides, AFB slides chemical
waste, sputum, sputum cups
and liquid waste
do-
5. Injection
Room
Immunization
and curative
injections
Syringes and needles,
ampoules, vials, broken
glasses and gloves
-
do-
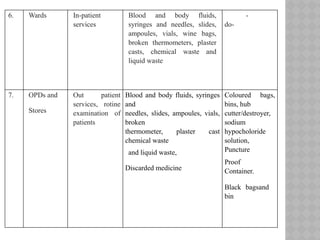
39.
6. Wards In-patient
services
Bloodand body fluids,
syringes and needles, slides,
ampoules, vials, wine bags,
broken thermometers, plaster
casts, chemical waste and
liquid waste
-
do-
7. OPDs and
Stores
Out patient
services, rotine
examination of
patients
Blood and body fluids, syringes
and
needles, slides, ampoules, vials,
broken
thermometer, plaster cast
chemical waste
and liquid waste,
Discarded medicine
Coloured bags,
bins, hub
cutter/destroyer,
sodium
hypocholoride
solution,
Puncture
Proof
Container.
Black bagsand
bin
HEALTH HAZARDS
HEALTHHAZARDS ASSOCIATED WITH POOR BMWM
Hospital acquired infections(HAI)/ Nosocomial infections
Blood borne diseases like Hep.B, Hep.C, HIV.
Epidemics
Cancer
Physical injury
44.
HEALTH HAZARDS CONTD…
Injury from sharps to staff and waste handlers
associated with the health care establishment.
Risk of infection outside the hospital for waste
handlers/scavengers and eventually general public.
Occupational risk associated with hazardous chemicals,
drugs etc.
Unauthorised repackaging and sale of disposable items
and unused / date expired drugs
46.
HEALTH HAZARDS
Main riskgroups:
Medical doctors
Nurses
Health care auxiliaries & hospital
maintenance personnel
Patients & Visitors
Workers coming in contact with bio-medical
waste
47.
MOHFW RECOMMENDATIONS ON
BMWMANAGEMENT
The Ministry of Health and Family Welfare (MoHFW) of
India has provided recommendations and guidelines on
Biomedical Waste Management (BMW) to ensure the safe and
proper disposal of waste generated from healthcare activities.
These guidelines are in line with the Biomedical Waste
Management Rules, 2016, issued by the Ministry of
Environment, Forest, and Climate Change (MoEFCC). Here
are key points from the MoHFW recommendations:
48.
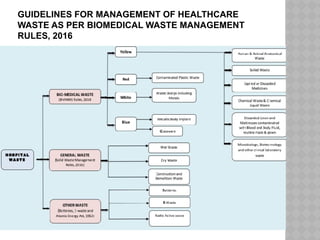
1. Categorization ofWaste: Biomedical waste is categorized into different
groups based on its nature and hazard potential:
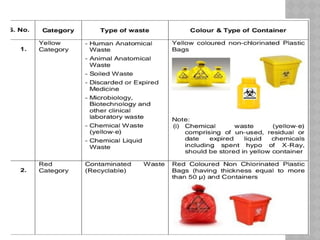
Yellow Category: Human anatomical waste, animal anatomical waste, soiled
waste (dressings, cotton, etc.), expired medicines, chemical waste, and
discarded linen.
Red Category: Contaminated waste like tubes, catheters, IV sets, gloves, etc.,
that can be recycled.
White (Translucent) Category: Waste sharps such as needles, syringes,
scalpels, etc.
Blue Category: Glassware like broken or discarded bottles and metallic body
implants.
49.
2. Segregation atSource:All biomedical waste must be segregated at the point of
generation into the specified color-coded bins.Segregation is crucial to prevent the
mixing of hazardous and non-hazardous waste, and to facilitate effective treatment
and disposal.
3. Handling and Storage:Waste should be collected in properly labeled
containers/bags based on the categorization.Waste must not be stored for more than
48 hours before it is treated or disposed of.
4. Transportation:Biomedical waste should be transported in dedicated vehicles
that prevent spillage and are designed as per prescribed safety standards.Vehicles
should carry proper labeling and follow specific routes to avoid public exposure
50.
5. Treatment andDisposal:Incineration or plasma pyrolysis is recommended
for yellow category waste, especially human and animal anatomical
waste.Autoclaving or microwaving is suggested for infectious waste in the
red category to make it safe for recycling.Sharp waste must be shredded after
disinfection.Liquid biomedical waste should be properly treated before being
discharged into sewers or water bodies.
6. Record Keeping and Monitoring:Healthcare facilities are required to
maintain records of the generation, collection, treatment, and disposal of
biomedical waste.Periodic audits and inspections are essential to ensure
compliance with the rules.Institutions generating biomedical waste must
obtain authorization from the State Pollution Control Board
51.
7. Training andAwareness: Regular training for healthcare workers, waste
handlers, and support staff on safe handling, segregation, and disposal of
biomedical waste.Awareness programs must emphasize the importance of
proper waste management to prevent health hazards
8. COVID-19 Specific Guidelines:The MoHFW has provided special
guidelines for handling waste generated from COVID-19 treatment
facilities, including quarantine centers, isolation wards, and
laboratories.Separate color-coded bins for COVID-19 waste, ensuring
proper disinfection and containment.PPE waste is to be treated and disposed
of under the yellow category with incineration or deep burial options
These guidelines are designed to prevent infection, reduce the
environmental impact, and ensure the safe disposal of hazardous biomedical
waste. Regular compliance with these recommendations is crucial for public
health and environmental safety.
52.
WHAT IS BIOSAFETY?
Biosafety is essentially a preventive concept and
consists of wide variety of safety precautions that are
to be undertaken, either singly or in combination,
depending on the type of hazard by all medical, nursing
& paramedical workers as well as by patients,
attendants, ancillary staff & administrators in a
hospital.
Waste assessment strategy
Main objectives:
Assessing type & amount of waste
Planning disposal strategies
Gather information by:
A walk through the hospital
Interviewing workers
Examining records
56.
Waste recycling strategy
Mainobjectives:
Prolonging life of material
Helping in cost saving & waste volume
reduction
Ensuring that reusables are properly sterilized
57.
Hospital waste disposal
Mainobjectives:
Disposing waste in most hygienic & cost
effective manner.
Using methods that minimize risk to environment.
58.
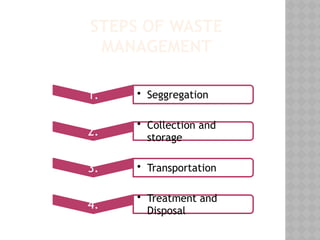
STEPS OF WASTE
MANAGEMENT
1.• Seggregation
2.
• Collection and
storage
3. • Transportation
4.
• Treatment and
Disposal
Don’ts
Never mixinfectious and non-infectious
waste either at :
Source of generation
During waste collection
Waste storage
Waste transportation
During final disposal of waste
61.
COLLECTION AND STORAGE
Do’s
1. Always collect the waste in covered bins
2. Fill the bins upto the 3/4th level
3. Clean the bins regularly with soap and
water/disinfect the bins regularly
Don’ts
1. Never overfill the bins
2. Never mix infectious and non-infectious
waste in the same bin
3. Never store waste beyond 48 hrs
63.
TRANSPORTATION
Do’s
1.Always carry/transport the waste in closed
containers
2. Use dedicated waste collection
bins/trolleys/wheel barrows for transporting
waste
3. Transport waste through a pre-defined route
within the health care facility
Don’ts
1. Never transport the waste in open containers
or bags, it may spill and lead to spread of
infections
2. Never transport waste through crowded areas
64.
TREATMENT AND DISPOSAL
Do’s
Always remember to disinfect and mutilate the waste
before its final disposal
Remember the following while treating the waste streams
a. Anatomical waste to be deep buried
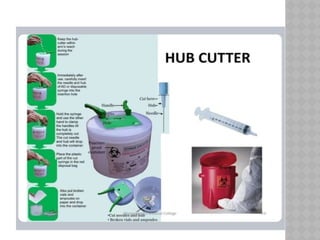
b. Syringes to be cut (with hub cutters) and
chemically disinfected with 1% bleaching powder
solution at source of generation before final disposal
into sharps pit
65.
ELEMENTS OF BIOMEDICAL
WASTEMANAGEMENT
1) Waste management team
2) Waste management plan
3) Training on biomedical waste management
4) Waste segregation
5) Waste collection
6) Waste storage
7) Transportation
8) Treatment
9) Disposal
66.
WASTE MANAGEMENT TEAM
Head of hospital
forms
Waste management team
develop
Waste management plan(WMP)
67.
WASTE MANAGEMENT TEAM
The staff typically involves:
Head of hospital(Chairperson)
Heads of hospital departments
Infection control officer/nurse
Chief pharmacist
Matron or senior nursing officer
Hospital manager/administrator
Hospital engineer/technician
68.
WASTE MANAGEMENT TEAM
A Waste management officer(WMO) is
also appointed
WMO,s responsibilities:
Waste management plan formulation
Subsequent day-to-day operation
Monitoring of waste disposal system
Produces a draft
69.
WASTE MANAGEMENT TEAM
The draft address following issues:
Present situation regarding waste management
Quantities of waste generated, the points of generation, the type of waste at
each point
Possibilities for waste minimization, reuse &recycling
Waste segregation, on-site handling, transport &
storage practices
Identification & evaluation of waste treatment/disposal options
Training
Estimation of costs relating to BMWM
Strategy for implementation of plan
70.
WASTE MANAGEMENT
PLAN (WMP)
Comprises of the complete outline of waste
management process
WMP is reviewed annually
Periodic auditing & evaluation of waste
management methods is performed
71.
TRAINING ON BIOMEDICAL
WASTEMANAGEMENT
Overall aim of training:
To develop awareness of health, safety and
environmental issues relating to health care
waste.
Roles & responsibilities of health care
personnel in overall management program
should be highlighted.
72.
TRAINING ON BIOMEDICAL
WASTEMANAGEMENT
Four main categories for which separate
training activities are designed:
1. Hospital managers & administrative staff
2. Medical doctors
3. Nurses & assistant nurses
4. Cleaners, porters, auxiliary
staff &waste handlers
73.
TRAINING ON BIOMEDICAL
WASTEMANAGEMENT
Staff education programs
Information given on:
All aspects of health care waste policy
Role & responsibilities of each hospital staff
member.
Relevant technical instructions
Adequate education & training of
health personnel about handling waste
74.
WASTE SEGREGATION
Done atthe source of waste generation
Responsibility of generator of waste.
segregation as per categories
applicable.
75.
COLOR CODING &TYPE OF CONTAINER/ BAGS TO
BE USED FOR WASTE SEGREGATION & COLLECTION
80.
WASTE COLLECTION
Doneby sanitary worker daily
Collected on daily basis at a fixed interval of time
Sharp items collected together safely in
puncture-proof plastic container and tightly sealed
81.
WASTE COLLECTION CONTD..
To discourage abuse, containers should be tamper-proof
(difficult to open or break)and needles and syringes
should be rendered unusable.
Where plastic or metal containers are unavailable or too
costly, containers made of dense cardboard are
recommended (WHO, 1997);
82.
COLLECTION TIMINGS
Wards- Every morning
Operation theatre (OT)- Each operation /
surgical procedure
OPD, ICU, Emergency, Laboratories - Each shift
Pharmacy - Once a day
Administrative unit and central store- Once a
day
Surrounding premises and garden-Once a day
Dialysis unit-Each procedure
Radiation unit- Each procedure
83.
BIOMEDICAL WASTE
PACKAGING
Bio-medicalwaste bags and sharps containers should be filled to no
more than three quarters full.
Plastic bags should never be stapled instead use tie and tapes
Replacement bags or containers should be available at each waste-
collection location.
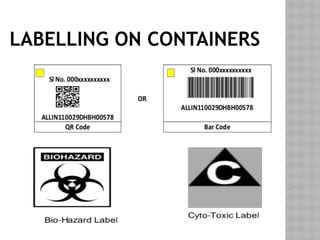
Colour coded waste bags and containers should be printed with the bio-
hazard symbol, labelled with details such as date, type of waste,
waste quantity, senders name and receivers’ details as well as bar coded
label to allow them to be tracked till final disposal.
WASTE STORAGE
Storagefacility should be located within
hospital premises.
It should have sufficient capacity.
Radioactive waste must be stored separately.
Untreated biomedical waste not to be kept beyond 48 hrs.
Permission required for more than 48 hrs.
Take measures for protecting human health &
environment.
87.
WASTE TRANSPORTATION
Points tobe remembered:
Before taking the bags it should be tied and labelled.
Waste handlers should not touch any other articles.
A covered cart with a biohazard symbol to carry the
waste to the central area of collection.
88.
SAFETY MEASURESFOR CLEANING AND
TRANSPORTATION STAFF:
Display of illustrated notices.
Issuance of protective gears.
Provision of hand washing articles
Provision of wash area.
Sterilisation of all equipment and issue of only properly sterilised equipment
and tool to the medical personnel.
Regular medical check-up.
Provision of disinfectant of the right quality.
WASTE TREATMENT AND
DISPOSAL
Biological Method
Plasma torch Technology
Deep burial
Land filling
Open dumps
Sanitary land fill
Worm composting
91.
WASTE TREATMENT ANDDISPOSAL
Chemical Technology
It uses chemicals to destroy pathogenic organisms from any
inanimate objects
Mostly suitable for liquids- blood, urine etc.
Solid- microbiological cultures, sharps.
92.
Thermal Technology
Autoclaving
Operate at high temp. and pressure to generate
steam(biocidal)
temperatures of 121°C & has cycle time of approx.
60-90 minutes.
93.
Hydroclave
Steam sterilizationtechnology.
Steam is used as indirect heating source
allowing total dehydration of waste material.
Holding time for waste is 15 minutes at 132°C
or 30 minutes at 121°C.
Performs sterilization faster , greater heat
penetrance.
94.
Incinerator
High heat,dry oxidation process of
burning combustible solids at very high
temperature in a furnace.
Reduces waste volume and weight
Not for pressurized containers, reactive
chemicals, silver mercury cadmium
waste
95.
Microwave
Lowheat system.
Uses microwaves to heat up the waste material from
inside.
Electromagnetic waves that lie between 300 to 300,000
MHz range in the electromagnetic radiation spectrum.
The heat produced at
95 - 100°C for a holding
period of 25 minutes.
Efficacy checked by
bacteriological, virological test
96.
Screw feedtechnology
Waste shredded & heated in a rotary auger.
Waste reduced by 80% in volume & by 20-35% in weight.
Used for treatment of infectious waste & sharps.
Not suitable for:
Pathological waste
Cytotoxic waste
Radioactive waste
97.
Mechanical Technology
Compaction
Compactingis carried out by a hydraulic ram against
a hard surface.
Grinding / Shredding
Waste material is broken down into smaller
particles under negative pressure to avoid any
spillage outside the chamber.
COMPACTION SHREDDING
98.
Pulverization
Waste ismixed with large volume of water
and bleach solution.
1. Waste is torn to shreds
2. Fed to an ultra high speed hammer
mill with large spin blades.
3.Pulverize the matter into small, safe particles
99.
Inertization
Processof mixing waste with other substance like
cement, lime & water.
Risk of toxic substances migrating into surface
water or ground water is minimum.
Proportion of mixture:-
Pharmaceutical waste - 65%
Lime - 15%
Cement - 15%
Water - 5%
Homogenous mass formed into cubes or pellets.
100.
Irradiation Technology
Wastesexposed to ultraviolet or ionizing radiation in an enclosed
chamber.
Require post shredding to render the waste unrecognizable.
Biological Processes
Use biological enzymes for treating medical waste.
Not only decontaminate the waste but also cause the destruction
of all the organic constituents.
Editor's Notes
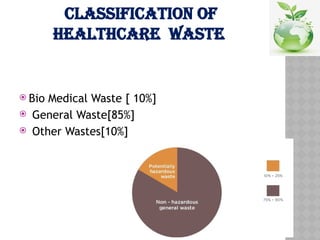
#2 Nowadays, because hospitals and disposable items have increased, a lot of medical waste is produced. Safe disposal of this waste is very tough. So, proper biomedical waste management is very important for hospital quality and safety.” “This pie chart shows the different types of waste produced in hospitals.
The majority of waste is general waste, which is about 69% — this includes things like paper, food waste, and packaging.
Next, 18% of the waste is recycled materials like plastic or cardboard.
About 12% is biomedical waste, which comes from patient care — such as syringes, bandages, and gloves.
And only 1% is chemical waste, which includes things like disinfectants and lab chemicals.
So, most of the hospital waste is general waste, but even the small part of biomedical and chemical waste needs proper management because it can be harmful.”
#5 Objectives of Biomedical Waste Management (Easy Explanation):
To reduce hazardous nature of waste:
Matlab — waste me jo harmful ya infectious part hai, usko kam karna.
So that it doesn’t spread infection or harm people and the environment.
👉 Example: Infectious waste ko disinfect karna ya treat karna before disposal.
To reduce volume of waste:
Matlab — total kachre ki quantity kam karna.
Jab waste kam hoga to uska treatment aur disposal dono easy aur safe ho jata hai.
👉 Example: Reuse or recycle karne se waste ka volume kam hota hai.
To prevent misuse or abuse of waste:
Matlab — koi bhi used medical item (jaise syringe, needle, or medicine bottle) ko galat tarike se dobara use na kare.
Isse infection aur illegal use dono roke ja sakte hain.
To ensure occupational safety and health:
Matlab — hospital staff, waste handlers, aur cleaners ki safety ensure karna.
Unhe proper gloves, masks aur training milni chahiye taaki unhe infection na lage.
To consider aesthetics:
Matlab — hospital environment clean aur pleasant dikhna chahiye.
Waste idhar-udhar pada rahe to hospital ka environment kharab lagta hai aur smell bhi hoti hai.
To reuse items that can be of repeat utility:
Matlab — jo items safely reuse ho sakte hain (jaise some plastic or metal instruments after sterilization), unhe phir se use karke cost aur waste dono kam karna.
#8 Also known as health care waste or hospital waste it is given by central pollotion and controll board
#31 Procedure to get authorization is simplified:
Pehle hospitals aur clinics ko biomedical waste manage karne ke liye permission lene ki process bahut lambi aur complicated thi.
Ab government ne ye process simple aur fast kar di hai, taaki har healthcare center easily permission le sake aur rules follow kare.
New rules prescribe more stringent standards for incinerator:
“Stringent” ka matlab hota hai strict.
Matlab ab incinerators (jo machines waste ko jalate hain) ke liye aur zyaada strict rules banaye gaye hain — taaki pollution kam ho aur environment safe rahe.
Change in SPM emission limit:
SPM means Suspended Particulate Matter — yaani hawa me chhote harmful particles.
Pehle acceptable limit thi 150 mg per cubic meter (mg/Nm³)
Ab new rule ke hisaab se ye limit sirf 50 mg/Nm³ kar di gayi hai.
👉 Matlab ab incinerators ko aur clean way me kaam karna hoga, taaki kam smoke aur pollutants nikle aur environment safe rahe.
🔹 Short version (for speaking in seminar):
“Earlier, getting authorization for biomedical waste management was difficult, but now the procedure is simplified.
Also, new rules have made the standards for incinerators stricter to control pollution.
Previously, the acceptable SPM emission was 150 mg per cubic meter, but now it has been reduced to 50 mg — which means less air pollution and a cleaner environment.”
SPM means Suspended Particulate Matter — these are tiny dust or smoke particles released into the air during burning. They can cause air pollution and affect health, so the new rules have reduced their limit from 150 to 50 mg/Nm³.”
#90 andfilling = large, engineered, municipal-level disposal.
Deep burial = small, local, rural-level burial method for biomedical waste.
Deep burial is permitted only in rural and remote areas without access to a Common Biomedical Waste Treatment Facility (CBMWTF) and must be done as per CPCB guidelines.central pollution and controll board
#123 Source of Mercury
Hospitals use mercury in thermometers, sphygmomanometers (BP instruments), and some lab chemicals.
When these instruments break or are disposed of improperly, mercury leaks into the environment — often through drains or biomedical waste.
2. Mercury reaches Water
The spilled mercury flows with wastewater and reaches rivers, ponds, or the sea.
There, mercury doesn’t stay in its original (elemental) form for long.
3. Conversion into Methyl Mercury
Microorganisms (bacteria) in water convert the mercury into a toxic compound called Methyl Mercury.
Methyl mercury is highly poisonous and easily enters living organisms.
4. Biomagnification (Food Chain effect)
Seaweeds and small aquatic plants absorb methyl mercury.
Small fish eat those plants → mercury enters their body.
Bigger fish (like tuna, shark) eat many small fish → mercury amount increases each step.
This is called biomagnification — meaning the concentration of mercury increases as we go up the food chain.
5. Effect on Humans
When humans eat large fish like tuna or swordfish, they also take in high amounts of methyl mercury.
This leads to mercury poisoning, which can cause:
Brain and nerve damage
Memory loss
Tremors (shaking hands)
In pregnant women → can harm baby’s brain development
#127 CN Position:
ICN ke according, sabhi nurses ka duty hai ki wo medical waste ke negative effects ko kam karein aur environment ko protect karein.
Nurses healthcare system ka important part hain, isliye unka role bahut crucial hai.
🔹 ICN supports these initiatives:
Decisions favoring recycled products:
Matlab — jab possible ho, nurses aur hospitals ko recycled ya reusable products use karne chahiye, jaise metal trays instead of disposable plastic — taaki waste kam ho.
Proper waste segregation:
Matlab — different types of waste alag-alag bins me dalna (red, yellow, blue, black) taaki unka correct treatment aur disposal ho sake.
Ye infection control ke liye bhi zaruri hai.
Waste treatment choices minimizing toxic disinfectants and sterilants:
Matlab — waste treat karte time kam toxic chemicals use karne chahiye, taaki environment aur staff dono safe rahein.
(For example: safer disinfectants instead of harsh chemical ones.)
Waste disposal choices reducing incineration to maximum:
Matlab — waste ko kam se kam jalana chahiye (incineration), kyunki jalane se smoke aur toxic gases nikalti hain.
Uske badle safer methods jaise autoclaving or chemical treatment use karne chahiye.
Patient education:
Matlab — nurses ko patients aur unke families ko bhi waste segregation aur cleanliness ke importance ke baare me educate karna chahiye.
Ye community level par bhi awareness badhata hai.
🗣️ Short version for seminar speaking:
“The ICN says that every nurse has a responsibility to reduce the negative impact of medical waste.
ICN supports actions like using recycled products, doing proper segregation, choosing less toxic disinfectants, minimizing incineration, and educating patients about safe waste practices.”