Clinical approach to Coagulation
Disorders
 Disorders of blood coagulation

 Disorders of vessels and platelets
 Good history
 Drug history
 Clinical examination
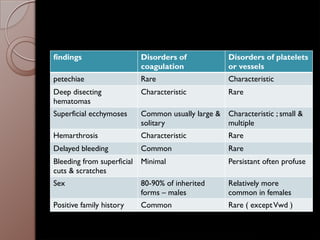
findings Disorders of
coagulation
Disorders of platelets
or vessels
petechiae Rare Characteristic
Deep disecting
hematomas
Characteristic Rare
Superficial ecchymoses Common usually large &
solitary
Characteristic ; small &
multiple
Hemarthrosis Characteristic Rare
Delayed bleeding Common Rare
Bleeding from superficial
cuts & scratches
Minimal Persistant often profuse
Sex 80-90% of inherited
forms – males
Relatively more
common in females
Positive family history Common Rare ( exceptVwd )
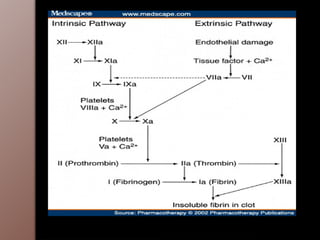
CLOTTING FACTORS
 Fibrinogen
 Prothrombin
 Tissue factor
 Calcium
 FactorV
 FactorVII
 FactorVIII
 Factor IX
 Factor X
 Factor XI
 Factor XII
 Factor XIII
 Prekallikrein
 Hmwk
 platelets
 Factor I
 Factor II
 Factor III ,Tissue thromboplastin
 Factor IV
 Proaccelerin, labile factor
 Proconvertin, stable factor
 Antihemophilic factor
 Christmas factor
 Stuart factor; stuart-prower
 Plasma thromboplastin antecedent
 Hageman factor
 Fibrin stabilizing factor
 Fletchet factor
 Fitzgerald factor
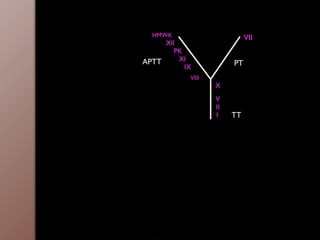
PT
APTT
HMWK
XII
PK
XI
IX
VIII
VII
X
V
II
I TT
LABORATORY
METHODS
 Tests ofVascular & Platelet Phases
 Tests of Coagulation Phase
Tests ofVascular & Platelet Phases
 Bleeding time
 Platelet enumeration
 Platelet volume measurement
 Release reaction & markers of platelet
activation
 Tests of platelet factor 3 activity
 Clot retraction
Bleeding time
 Depends on rate at which stable platelet plug
is formed.
 Provides a measure of efficiency of vascular
and platelet phases
 But does not discriminate b/w vascular defects,
thrombocytopenia & platelet dysfunction.
 Normal : 3-9 min
 Valuable in platelet disorders ( qualitative
platelet disorders & vonWillebrand’s disease
Bleeding time
 Screen patient for inherited platelet
disorders
 An abnormal bleeding time in a patient
with personel and family history of
excessive mucocutaneous bleeding would
justify further hemostatic testing for
platelet dysfunction
Aspirin tolerance test
 To assess the effect of standard dose of
aspirin on bleeding time
 Mild disorders of platelet function might
have normal bleeding time
 Aspirin administration – prolongs BT
 Slightly – normal individuals
 Substantially prolonged / precipitate
clinical bleeding –Vwd / Qualitative
platelet disorders
Platelet Enumeration
 Hemacytometer / direct methods
 Semiautomated methods
 Fully automated electronic methods
 Normal –
 Phase microscopy : 140- 440,000 /ul
 Automated : 150-450,000 /ul
Artifacts in automated platelet counting :
 Falsely low platelet counts :
 Platelet cold agglutinins
 Paraproteinemias
 Previous contact of platelet with foreign
surfaces such as dialysis membranes
 Giant platelets
 Lipemia
 EDTA-induced platelet clumping
Artifacts
 Falsely high platelet counts-
 Presence of microspherocytes
 Fragments of leukemic cells
PlateletVolume Measurements
 Increased in disorders with accelerated
platelet turnover as the result of large
numbers of megathrombocytes or in
patients with Bernard-Soulier syndrome
 Normal / Decreased in disorders with
deficient platelet production, sepsis & big
spleen syndromes
 Some say increased MPV – as evidence of
Accelerated Platelet Production
Tests of specific platelet function
 Most widely used & reliable – Platelet
Aggregation
 Historical interest – Platelet adhesiveness
& Platelet retention
Ristocetin induced platelet aggregation
 Ristocetin induces platelet agglutination in
presence of vWF
 In von Willebrand’s disease &
Bernard-Soulier’s disease –
abnormal ristocetin response
Kaolin-induced PF-3
 Indirect measures of platelet aggregation
Clot Retraction
 Incubate a tube of clotted blood, clot
retraction normally apparent within 2
hours
Usually deficient when –
 platelet count is below 50,000/ul
 Glanzmann Thrombasthenia
Tests of Coagulation Phase
 Partial thromboplastin time
 Plasma prothrombin time
 Whole blood clotting time
 Thromboplastin generation test
 Assay of plasma fibrinogen
 Thrombin time
 Tests for fibrin – fibrin degradation products
 Bioassay for coagulation factors
 Tests for inhibitors of coagulation
 Tests for physiological inhibitors of coagulation
 Automated coagulation methods
 Chromogenic & flurometric techniques
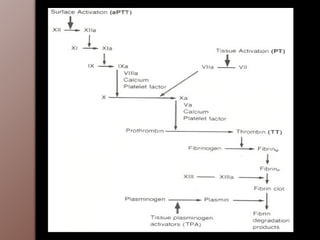
Partial Thromboplastin Time
 Simple test of intrinsic & common
pathways of coagulation
 More sensitive to deficiencies of
factorsVIII and IX than to deficiencies of
factors XI and XII or factors involved in
common pathway
 Test is abnormal when essential factors
are below 15 to 30 % of normal value.
Activated partial thromboplastin time
 Using activators – Celite or Kaolin
 Assay used to evaluate intrinsic
coagulation
 Normal : 25 – 36 sec
 Abnormal – deficiencies prekallikrein,
HMW Kininogen, factors XII,XI,IX,VIII,X
&V; Prothrombin /Fibrinogen.
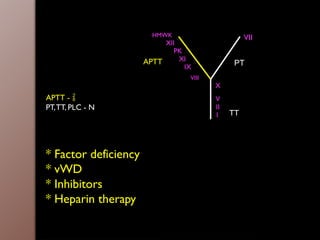
APTT - 
PT,TT, PLC - N
* Factor deficiency
* vWD
* Inhibitors
* Heparin therapy
PT
TT
APTT
HMWK
XII
PK
XI
IX
VIII
VII
X
V
II
I
Plasma Prothrombin Time
 The production of fibrin by means of
Extrinsic and Common Pathway requires
tissue thromboplastin and FactorVII ,
inaddition to factors X,V, Prothrombin
and Fibrinogen.These pathways are
measured by plasma prothrombin time.
Plasma Prothrombin Time
 FactorsV,VII,X,Prothrombin & Fibrinogen
 Vitamin K dependent – prothrombin
factorVII & X
Are depressed by Coumarin like drugs
 PT – widely used for controlling
oral anticoagulant therapy
Plasma Prothrombin Time
 PT is more sensitive to deficiencies of
factorVII & X than to prothrombin &
fibrinogen.
 Normal : 15 – 18 sec
PT
TT
APTT
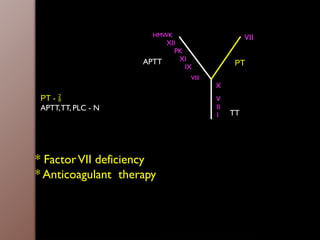
PT - 
APTT,TT, PLC - N
HMWK
XII
PK
XI
IX
VIII
VII
X
V
II
I
* FactorVII deficiency
* Anticoagulant therapy
Stypven time
 Venom of Russel’s viper contains enzyme
that initiates coagulation by direct
activation of factor X and does not
require factorVII.
 One stage Prothrombin time performed
with this venom ( stypven time ) –
distinguishes b/w deficiency of FactorVII
and Factor X .
Whole blood clotting time
 Measures only the time required for the
formation of the first traces of thrombin
sufficient to produce visible clot.
 Prolonged only in severe deficiencies of
various coagulation factors involved in
intrinsic and common pathways.
 Test result not affected by factorVII
 Coagualation time is significant only if it is
significantly prolonged.
Whole blood clotting time
 It is a poor screening test
 Prolonged by heparin
 But aPTT – monitor heparin
anticoagulation
Thromboplastin generation time
 2 stage test
 Measures the amount and rate of
prothrombinase formation by way of
intrinsic pathway
 Supplanted by specific factor assays
Assay for plasma fibrinogen
 Aid in identifying inherited
dysfibrinogenemias
Thrombin time
 thrombin is added to plasma, time
required for the clot formation is the
measure of the rate at which fibrin forms
 Abnormal – when fibrinogen is below
70-100 mg /dL, by Heparin
 Prolonged : abnormal fibrinogen, elevated
fibrin-FDPs, paraproteinemias,
hyperfibrinogenemia
 Normal :13-17 sec
Tests for fibrin – fibrin degradation
products
 Increased in DIC, Fibrinogenolysis
 Cannot distinguish b/w fibrin degradation
products and fibrinogen degradation
products.
- Measurement of fibrinopeptides,
specific FDP ( DD dimer, DDE trimer )
are useful indices of DIC
Tests for fibrinolysis
 Whole blood clot lysis
 But may be normal in hypofibrinogenemia
 Specific assays of fibrinolytic components
supplanted whole blood clot lysis test
Tests for inhibitors of coagulation
 Abnormalities of any test in coagulation, if
caused by deficiency of essential factor,
are corrected by addition of small
amounts of normal plasma .
 If inhibitors are present : addition of small
amounts of patient’s plasma impair
coagulation in normal plasma.
Tests for physiological inhibitors of
coagulation
 Assays of physiological inhibitors of
coagulation – antithrombin III,
heparin cofactor II
protein C
protein S
PRIMARY SCREENING
TESTS
 aPPT – BEST SINGLE SCREENING TEST
 PT , Prothrombin time
 Followed by confirmatory tests
 PT : increased
 aPPT : normal
 Platelet count : normal
 Common : acquired factorVII deficiency
( early liver disease, early vit K deficiency,
early warfarin therapy )
 Rare : FactorVII inhibitior,
dysfibrinogenemia,DIC,
inherited factorVII deficiency
 PT : normal
 aPTT : increased
 Platelet count : normal
 Common : deficiency or inhibitor of
factorsVIII, IX, XI,
von Willebrand’s disease,
heparin
 Rare : lupus inhibitor
 PT : increased
 aPTT : increased
 Platelet count : normal
 Common : vitamin K deficiency,
liver disease, warfaarin, heparin
 Rare : deficiency / inhibitor of factor X,V
prothrombin, fibrinogen,
DIC
 PT : increased
 aPTT : increased
 Platelet count : decreased
 Common : DIC, Liver diseasee
 Rare : heparin therapy with associated
thrombocytopenia
 PT : normal
 a PPT : normal
 Platelet count : decreased
 Common : increased platelet destruction,
decreased platelet production,
hypersplenism
 Rare : bernard-soulier syndrome
 PT : normal
 aPPT : normal
 Platelet count : increased
--- myeloproliferative disorder
 PT : normal
 aPTT : normal
 Platelet count: normal
 Common : mildVwd, uremia
 Rare : inherited qualitative platelet
disorders
CONFIRMATORYTESTS
Thrombocytopenia
 Most common acquired bleeding disorder
 Bleeding time : prolonged
 Clot retraction : deficient
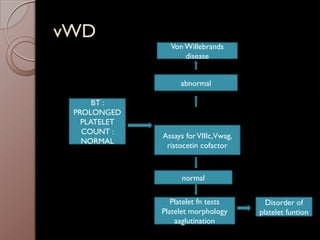
vWD
BT :
PROLONGED
PLATELET
COUNT :
NORMAL
Assays forVIIIc,Vwag,
ristocetin cofactor
abnormal
Von Willebrands
disease
normal
Platelet fn tests
Platelet morphology
aaglutination
Disorder of
platelet funtion
Qualitative platelet disorders
 Deficient clot retraction is seen in
glanzmann thrombasthenia
 Strikingly large platelets – Bernard Soulier
syndrome
 Elevated platelet count –
myeloproliferative disorder
 Absence of platelet aggregation by ADP,
collagen, epinephrine – Glanzmann
thrombasthenia
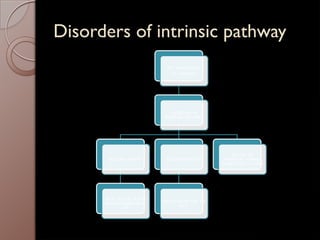
Disorders of intrinsic pathway
PPT :PROLONGED
PT : NORMAL
DISORDERS OF
INTRINSIC PATHWAY
BLEEDING ABSENT
ASSAY FOR FACTORXII,
PREKALLIKREIN,HMWK
DEF
BLEEDING PRESENT
ASSAY FOR FACTOR VIII,
IX, X
FACTORVIII
INHIBITORS, HEPARIN,
INHIBITIORS OF LUPUS
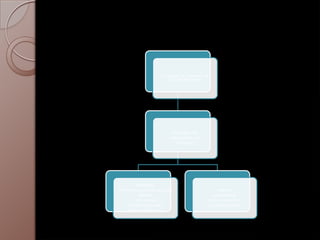
Disorders of common pathway
PTT : PROLONGED
PT : PROLONGED
DISORDERS OF
COMMON
PATHWAY
ASSAY FOR
FACTORS
X,V,PROTHROMBIN,
FIBRINOGEN,FDP
DISORDERS OF COMMON OR
MULTIPLE PATHWAYS
THROMBINTIME
FIBRINOGEN LEVEL
FDP LEVELS
ABNORMAL
INTRAVASCULAR COAGULATION
HEPARIN
LIVER DISEASE
DYSFIBRINOGENEMIA
PRIMARY FIBRINOLYSIS
NORMAL
LIVER DISEASE
VITAMIN K DEFICIENCY
COUMARIN DRUGS
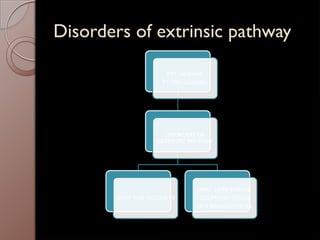
Disorders of extrinsic pathway
PTT: NORMAL
PT : PROLONGED
DISORDERS OF
EXTRINSIC PATHWAY
ASSAY FOR FACTORVII
EARLY LIVER DISEASE
COUMARIN DRUGS
DYSFIBRINOGENEMIA
Disorders of extrinsic pathway
 Coagulation and stypven time are normal
Bleeding disorders with normal primary
screening tests
 vonWillebrand’s disease
 Mild inherited coagulation disorders : factor XI deficiency
 Heterozygous carriers for inherited coagulation disorders
 Factor XIII ( Fibrin stabilizing factor ) deficiency
 Some forms of dysfibrinogenemia
 Disordered platelet function- deficient release reaction
 Hereditary hemorrhagic telangiectasia
 Allergic and other vascular purpura
 Alpha2 plasmin inhibitor deficiency
 Elevated levels of plasminogen activator
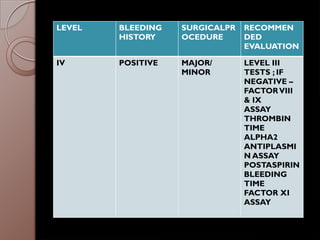
Preoperative hemostasis evaluation
level Bleeding
history
Surgical
procedure
Recommended
evaluation
I NEGATIVE MINOR NONE
II NEGATIVE MAJOR PLATELET
COUNT,APTT
III EQUIVOCAL MAJOR PT,APTT,PLATELE
T COUNT,
BLEEDING TIME,
FACTOR XIII
ASSAY,ECLT
LEVEL BLEEDING
HISTORY
SURGICALPR
OCEDURE
RECOMMEN
DED
EVALUATION
IV POSITIVE MAJOR/
MINOR
LEVEL III
TESTS ; IF
NEGATIVE –
FACTORVIII
& IX
ASSAY
THROMBIN
TIME
ALPHA2
ANTIPLASMI
N ASSAY
POSTASPIRIN
BLEEDING
TIME
FACTOR XI
ASSAY
THANKYOU