This presentation provides an overview of COPD,it's causes and risk factors, pathophysiology, clinical signs and symptoms, diagnosis,complication, manegement.
INTRODUCTION:
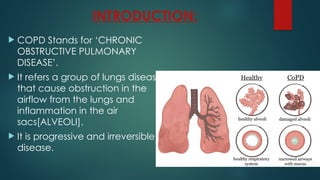
COPD Standsfor ‘CHRONIC
OBSTRUCTIVE PULMONARY
DISEASE’.
It refers a group of lungs disease
that cause obstruction in the
airflow from the lungs and
inflammation in the air
sacs[ALVEOLI].
It is progressive and irreversible
disease.
3.
TYPES OF COPD
1.Emphysema:Emphysema is a long – term progressive lung
disease where the air sacs in the lungs become damaged, and
leading to difficulty in breathing.
This damage cause the air sacs to lose their elasticity making
it harder for them to expand and contract property.
2.Chronic Bronchitis: It is defined as long term inflammation of
bronchial tubes.
Cough is mainly caused by oversecretion of mucus.
People with bronchitis breath less air and O2 into the lungs.
2. OXYGEN THERAPY:
O2 therapy for COPD gives
you extra O2 to you to
breathe easier.
Its usually give through a
mask or small tubes in your
nose.
This extra O2 helps your
body get the O2 it needs
when your lungs are not
working well.
9.
3. MEDICATION TREATMENT:
[A]BRONCHODILATORS:
Bronchodilators are the medications that relax and open the
airway to help breathing easier.
These drugs relax the smooth muscle of the airway allowing for
improved airflow.
TYPES:
1. B2 Agonist: Salbutamol, Terbutaline
2. Anticholinergics: Ipratropium, Tiotropium
3. Methylxanthine: Theophylline, Aminophylline, Doxophylline.
10.
1.BETA 2 AGONIST:
MOA: These are beta 2 adrenergic receptor on airway smooth
muscles.
Activation of these receptors stimulates adenylate cyclase,
raising cAMP level in smooth muscle cells.
Lower Ca2+ level relax the airway smooth muscle.
SALBUTAMOL
It is a short acting beta2 adrenergic receptor agonist used for
the relief of bronchospasm in condition such as COPD.
MOA: It stimulates the beta2 receptor leads to rise in cAMP
level causing smooth muscle relaxation.
11.
FORMOTEROL
Formoterol isa potent, rapid-onset, and long-acting
beta2 adrenergic receptor agonist used as
bronchodilator to treat COPD.
It work within 2-3 minutes and last over 12 hours.
MOA: Formoterol binds with high affinity to bera2
adrenoceptors on the bronchial smooth muscle
cells.
Stimulation of these receptor activates the enzyme
adenylate cyclase.
Increasing cAMP level leads to bronchodilation.
12.
2.ANTI-CHOLINERGIC AGENTS:
MOA:Anticholinergic agents block muscarinic receptor inn lungs.
This reduces bronchoconstriction by inhibiting acetylcholine action.
Leads to relaxed airway and improved airway flow in asthma.
IPRATROPIUM BROMIDE
It is an anticholinergic agent which is chemically related to atropin.
MOA: It blocks muscarinic cholinergic receptors, resulting in a decrease
in the formation of cGMP.
This results in decreased contractility of smooth muscle.
13.
3.METHYLXANTHINE:
MOA: Theyinhibits phosphodiesterase enzyme, increasing
cAMP level.
Elevated cAMP levels reduces airway smooth muscle, leading
to bronchodilation.
THEOPHYLLINE
Theophylline, known as dimethylxanthine drug used in COPD.
MOA: It causes bronchodilation by inhibiting
phosphodiesterase, leading to increased cAMP level and
relaxation of bronchial smooth muscle.
14.
[B] ANTI-INFLAMMATORY AGENTS:
Anti- Inflammatory medications in COPD reduce
swelling and irritation in the airway to help improve
breathing.
TYPES:
1. CORTICOSTEROIDS
2. LEUKOTRIENE MODIFIER
3. PDE4 [PHOSPHODISTEREASES] INHIBITORS
15.
1. CORTICOSTEROIDS:
InCOPD, they are used as like pills and inhalers.
Pills wax faster, and help during flare-ups.
Pharmacokinetics:
1. Absorption: Corticosteroids are absorbed through the lungs,
digestive system or skin , depending on the form.
2. Distribution: The circulate in the bloodstream and reach target
tissues, including the lungs.
3. Metabolism: They are broken down mainly in the liver.
4. Excretion : Metabolite's are excreted mainly through urine.
16.
MODE OF ACTION:
They block substance that causing inflammation in airway
Decrease activity of immune cells that increase inflammation
Reduce mucus production
Improve airflow
Therapeutic Uses: Inflammation, COPD
Adverse Effects: Osteoporosis, Hypertension, Diabetes
Example: Hydrocortisone, Prednisolone, Fluticasone
17.
BUDESONIDE
It isused in COPD and asthma to reduce airway
inflammation.
It prevents sypmtoms like- wheezing, breathlessness.
It is not for immediate relief having long – term
control.
MOA: Budesonide enters airway cells and binds to
glucocorticoid receptors.
This activates anti- inflammatory proteins and blocks
inflammatory genes.
Result in decrease inflammation, cytokines
production.
18.
2.LUEKOTRIENE MODIFIER:
Leukotrienemodifier are medications that blocks chemical called
leukotrienes, which cause inflammation and narrowing of the airway
They are used to prevent mild to moderate asthma and can bean
alternative to inhaled steroids.
EXAMPLES: Montelukast, Zafirlukast & Zileuton
Pharmacokinetics:
1. Absorption: They are absorbed through digestive system.
2. Distribution: They are carried in the bloodstream to targrt organs in
lungs.
3. Metabolism: Mostly metabolised in liver.
4. Excretion: Excreted mainly through urine and feces.
19.
MODE OF ACTION:
They block leukotriene receptors
Decrease swelling is airways
Relax airway
Decrease mucus production
Improve airflow and easy to breathing
Therapeutic Uses: Asthma, COPD, Allergies
Adverse Effects: Headache, Nausea,
Fatigue ,Diarrhoea
Example: Montelukast, Zafirlukast
20.
MONTELUKAST
Montelukast isa leukotriene receptor antagonist
used in the management of COPD.
Montelukast is taken orally and helps in long-term
control of symptoms, but it is not a first-line drug for
COPD.
MOA: It works by blocking the leukotriene receptors,
so leukotriene cannot produce their harmful effects.
As a result, airway inflammation is reduced, mucus
secretion decrease, and breathing becomes easier.
21.
3.PDE4 [PHOSPHODISTEREASE]INHIBITOR:
Theyare medications that act by blocking the enzyme
called PDE4 and reduce inflammation in the lungs and help
to relax the airway, making it easier to breathe, especially in
condition like: COPD.
Pharmacokinetics:
1. Absorption: They are absorbed through the digestive
system.
2. Distribution: They are distributed in the bloodstream to
the lungs and other tissues.
3. Metabolism: Primarily metabolized in the liver.
4. Excretion : Excreted mainly through urine and feces.
22.
MODE OF ACTION:
Blocks PDE4 enzyme, which cause inflammation in lungs
Decrease swelling and irritant in airway
Thus, open airway and reduce mucus prodution
Easy to breathe
Therapeutic Uses: COPD, Chronic Bronchitis
Adverse Effect: Nausea, Diarrhoea
Example: Roflumilast
23.
ROFLUMILAST
It isan oral anti- inflammatory drug used in severe
COPD, especially in patients with chronic bronhitis.
It is mainly used to reduce COPD exacerbations, not
for immediate relief.
MOA: Roflumilast inhibits PDE4 enzyme, normally
PDE4 breaks down cAMP.
Inhibition of PDE4 increases cAMP level leads to
reduce inflammatory cell activity.
 Most read








 Most read













