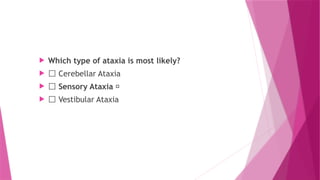Cerebellar Ataxia vs Sensory Ataxia
Clinical Features, Assessment, Differential Diagnosis &
Physiotherapy Management
Dr. Etika Rana, (PT)
PhD Scholar (Physiotherapy)
Department of Physiotherapy
Learning Objectives
By the end of this presentation, you will be able to:
 Define ataxia and understand its neurological basis.
 Differentiate cerebellar ataxia from sensory ataxia.
 Explain the underlying neuroanatomy and pathophysiology.
 Recognize key clinical features and examination findings.
 Perform evidence-based physiotherapy assessment.
 Plan individualized rehabilitation programs for both
conditions.
What is Ataxia ?
Ataxia is a neurological sign characterized by impaired coordination of voluntary
movement that cannot be explained by muscle weakness, abnormal muscle tone,
or involuntary movements. It results from dysfunction of the cerebellum,
proprioceptive pathways, vestibular system, or their interconnections.
 Common Manifestations
 Unsteady gait
 Impaired balance
 Poor limb coordination
 Difficulty performing precise movements
 Dysmetria
 Intention tremor
 Impaired postural control
Neuroanatomy of Motor Coordination
 How is Coordinated Movement Produced?
Normal voluntary movement requires continuous interaction between multiple neural
systems.
Components of the Motor Control System
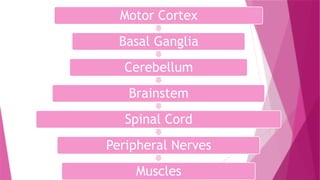
Motor Cortex
 Plans and initiates voluntary movement.
 Sends motor commands via the corticospinal tract.
⬇️
Basal Ganglia
 Selects appropriate motor programs.
 Suppresses unwanted movements.
 Regulates movement initiation and amplitude.
⬇️
Cerebellum
 Compares intended movement with actual performance.
 Corrects movement errors in real time.
 Maintains balance, posture, and motor learning.
Brainstem & Spinal Cord
 Relay motor commands.
 Integrate postural reflexes.
 Coordinate muscle activation.
⬇️
Muscles
 Execute smooth, coordinated movement.
Smooth movement depends on accurate sensory input, intact cerebellar processing,
and appropriate motor output. Dysfunction at any level can produce ataxia.
Motor Cortex
Basal Ganglia
Cerebellum
Brainstem
Spinal Cord
Peripheral Nerves
Muscles
Role of the Cerebellum in Motor Control
The cerebellum does not initiate movement. Instead, it ensures that movements are accurate, coordinated, and
efficient.
Major Functions
Movement Coordination
 Synchronizes muscle activity.
 Produces smooth and precise voluntary movement.
Balance & Postural Control
 Maintains equilibrium during static and dynamic activities.
 Integrates vestibular, visual, and somatosensory information.
Gait Control
 Regulates timing, rhythm, and symmetry of walking.
 Adjusts step length and trunk stability.
Motor Learning
 Facilitates acquisition and refinement of motor skills through error-based learning.
Eye Movement Control
 Coordinates smooth pursuit, saccades, and vestibulo-ocular reflexes.
 Lesions may result in nystagmus or ocular dysmetria.
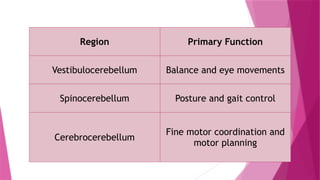
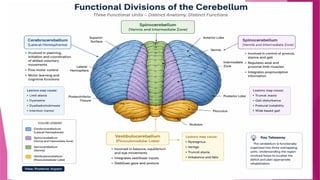
Region Primary Function
Vestibulocerebellum Balance and eye movements
Spinocerebellum Posture and gait control
Cerebrocerebellum
Fine motor coordination and
motor planning
Clinical Correlation
Damage to different cerebellar regions results in distinct clinical
presentations:
 Vestibulocerebellum truncal ataxia, nystagmus
→
 Spinocerebellum gait and postural instability
→
 Cerebrocerebellum limb ataxia, dysmetria, dysdiadochokinesia
→
Dorsal Column–Medial Lemniscus (DCML) Pathway
The Proprioceptive Pathway for Coordinated Movement
The Dorsal Column–Medial Lemniscus (DCML) pathway transmits conscious proprioceptive and
discriminative sensory information from the body to the cerebral cortex. Accurate proprioceptive input
enables the central nervous system to determine limb position and movement without visual guidance.
Loss of DCML function results in sensory ataxia, where patients rely heavily on visual feedback to
maintain balance and coordinate movement.
Functions of the DCML Pathway
 Joint position sense (Proprioception)
 Vibration sense
 Fine/discriminative touch
 Two-point discrimination
 Stereognosis
 Graphesthesia
Peripheral Receptors
Dorsal Root Ganglion
Dorsal Columns
(Fasciculus Gracilis & Fasciculus Cuneatus)
Medulla
(Gracile & Cuneate Nuclei)
Internal Arcuate Fibers
Medial Lemniscus
Thalamus (VPL)
Primary Somatosensory Cortex
(Postcentral Gyrus)
Clinical Correlation
 Lesions affecting the DCML pathway can occur in:
 Peripheral neuropathy
 Vitamin B12 deficiency
 Posterior column lesions
 Cervical spondylotic myelopathy
 Multiple sclerosis
 Tabes dorsalis
Patients with sensory ataxia can often compensate using vision. Balance typically worsens markedly
when visual input is removed (e.g., eyes closed), leading to a positive Romberg test.
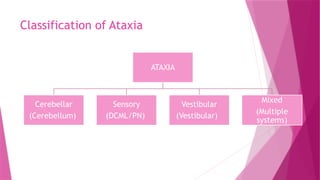
Classification of Ataxia
ATAXIA
Cerebellar
(Cerebellum)
Sensory
(DCML/PN)
Vestibular
(Vestibular)
Mixed
(Multiple
systems)
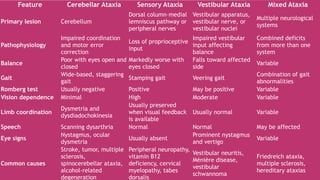
Feature Cerebellar Ataxia Sensory Ataxia Vestibular Ataxia Mixed Ataxia
Primary lesion Cerebellum
Dorsal column–medial
lemniscus pathway or
peripheral nerves
Vestibular apparatus,
vestibular nerve, or
vestibular nuclei
Multiple neurological
systems
Pathophysiology
Impaired coordination
and motor error
correction
Loss of proprioceptive
input
Impaired vestibular
input affecting
balance
Combined deficits
from more than one
system
Balance
Poor with eyes open and
closed
Markedly worse with
eyes closed
Falls toward affected
side
Variable
Gait
Wide-based, staggering
gait
Stamping gait Veering gait
Combination of gait
abnormalities
Romberg test Usually negative Positive May be positive Variable
Vision dependence Minimal High Moderate Variable
Limb coordination
Dysmetria and
dysdiadochokinesia
Usually preserved
when visual feedback
is available
Usually normal Variable
Speech Scanning dysarthria Normal Normal May be affected
Eye signs
Nystagmus, ocular
dysmetria
Usually absent
Prominent nystagmus
and vertigo
Variable
Common causes
Stroke, tumor, multiple
sclerosis,
spinocerebellar ataxia,
alcohol-related
degeneration
Peripheral neuropathy,
vitamin B12
deficiency, cervical
myelopathy, tabes
dorsalis
Vestibular neuritis,
Ménière disease,
vestibular
schwannoma
Friedreich ataxia,
multiple sclerosis,
hereditary ataxias
Cerebellar Ataxia
 Cerebellar ataxia is a neurological syndrome characterized by impaired coordination of
voluntary movements resulting from dysfunction of the cerebellum or its afferent and
efferent pathways. It affects the timing, precision, force, and coordination of movement
while muscle strength is often preserved.
Key Characteristics
 Impaired coordination of voluntary movements
 Wide-based, unsteady gait
 Dysmetria (overshooting or undershooting a target)
 Dysdiadochokinesia (impaired rapid alternating movements)
 Intention tremor
 Impaired balance and postural control
 Ocular motor abnormalities (e.g., nystagmus)
 Scanning (ataxic) speech
 The hallmark of cerebellar ataxia is impaired coordination despite normal muscle strength.
Patients know what movement they want to make but cannot execute it smoothly or
accurately.
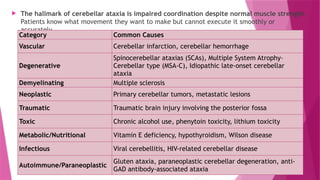
Category Common Causes
Vascular Cerebellar infarction, cerebellar hemorrhage
Degenerative
Spinocerebellar ataxias (SCAs), Multiple System Atrophy–
Cerebellar type (MSA-C), Idiopathic late-onset cerebellar
ataxia
Demyelinating Multiple sclerosis
Neoplastic Primary cerebellar tumors, metastatic lesions
Traumatic Traumatic brain injury involving the posterior fossa
Toxic Chronic alcohol use, phenytoin toxicity, lithium toxicity
Metabolic/Nutritional Vitamin E deficiency, hypothyroidism, Wilson disease
Infectious Viral cerebellitis, HIV-related cerebellar disease
Autoimmune/Paraneoplastic
Gluten ataxia, paraneoplastic cerebellar degeneration, anti-
GAD antibody-associated ataxia
Pathophysiology of Cerebellar Ataxia
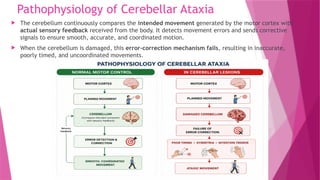
 The cerebellum continuously compares the intended movement generated by the motor cortex with
actual sensory feedback received from the body. It detects movement errors and sends corrective
signals to ensure smooth, accurate, and coordinated motion.
 When the cerebellum is damaged, this error-correction mechanism fails, resulting in inaccurate,
poorly timed, and uncoordinated movements.
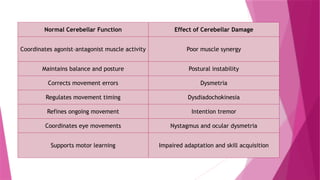
Normal Cerebellar Function Effect of Cerebellar Damage
Coordinates agonist–antagonist muscle activity Poor muscle synergy
Maintains balance and posture Postural instability
Corrects movement errors Dysmetria
Regulates movement timing Dysdiadochokinesia
Refines ongoing movement Intention tremor
Coordinates eye movements Nystagmus and ocular dysmetria
Supports motor learning Impaired adaptation and skill acquisition
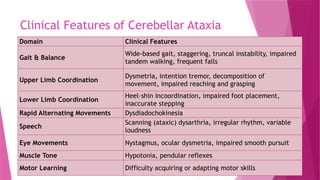
Clinical Features of Cerebellar Ataxia
Domain Clinical Features
Gait & Balance
Wide-based gait, staggering, truncal instability, impaired
tandem walking, frequent falls
Upper Limb Coordination
Dysmetria, intention tremor, decomposition of
movement, impaired reaching and grasping
Lower Limb Coordination
Heel–shin incoordination, impaired foot placement,
inaccurate stepping
Rapid Alternating Movements Dysdiadochokinesia
Speech
Scanning (ataxic) dysarthria, irregular rhythm, variable
loudness
Eye Movements Nystagmus, ocular dysmetria, impaired smooth pursuit
Muscle Tone Hypotonia, pendular reflexes
Motor Learning Difficulty acquiring or adapting motor skills
 Clinical Presentation
 Patients commonly report:
 Difficulty walking on uneven surfaces
 Frequent loss of balance
 Clumsiness while reaching or writing
 Tremor during goal-directed activities
 Slurred or scanning speech
 Oscillopsia or visual instability (in some patients)
 Increased risk of falls
Symptoms are typically more pronounced during voluntary, goal-directed
movements and are not due to muscle weakness or sensory loss.
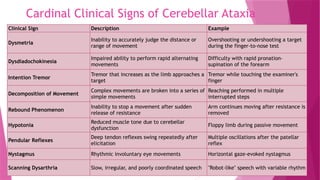
Cardinal Clinical Signs of Cerebellar Ataxia
Clinical Sign Description Example
Dysmetria
Inability to accurately judge the distance or
range of movement
Overshooting or undershooting a target
during the finger-to-nose test
Dysdiadochokinesia
Impaired ability to perform rapid alternating
movements
Difficulty with rapid pronation–
supination of the forearm
Intention Tremor
Tremor that increases as the limb approaches a
target
Tremor while touching the examiner's
finger
Decomposition of Movement
Complex movements are broken into a series of
simple movements
Reaching performed in multiple
interrupted steps
Rebound Phenomenon
Inability to stop a movement after sudden
release of resistance
Arm continues moving after resistance is
removed
Hypotonia
Reduced muscle tone due to cerebellar
dysfunction
Floppy limb during passive movement
Pendular Reflexes
Deep tendon reflexes swing repeatedly after
elicitation
Multiple oscillations after the patellar
reflex
Nystagmus Rhythmic involuntary eye movements Horizontal gaze-evoked nystagmus
Scanning Dysarthria Slow, irregular, and poorly coordinated speech "Robot-like" speech with variable rhythm
Gait Characteristics in Cerebellar Ataxia
 Damage to the cerebellum impairs the coordination of trunk and lower-limb muscles,
resulting in an unstable, inefficient, and highly variable gait pattern.
Feature Clinical Presentation
Base of Support Wide-based stance to improve stability
Step Pattern Irregular step length and timing
Trunk Control Excessive side-to-side sway
Walking Direction
Deviates unpredictably; may veer toward the
lesion
Turning Slow, unsteady, requires multiple corrective steps
Tandem Walking Markedly impaired or impossible
Speed Reduced walking velocity with poor rhythm
Falls
Frequent, especially during turning or dual-task
activities
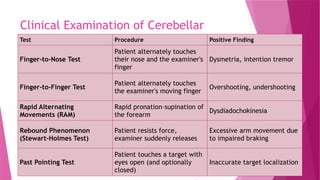
Clinical Examination of Cerebellar
Ataxia
Test Procedure Positive Finding
Finger-to-Nose Test
Patient alternately touches
their nose and the examiner's
finger
Dysmetria, intention tremor
Finger-to-Finger Test
Patient alternately touches
the examiner's moving finger
Overshooting, undershooting
Rapid Alternating
Movements (RAM)
Rapid pronation–supination of
the forearm
Dysdiadochokinesia
Rebound Phenomenon
(Stewart–Holmes Test)
Patient resists force,
examiner suddenly releases
Excessive arm movement due
to impaired braking
Past Pointing Test
Patient touches a target with
eyes open (and optionally
closed)
Inaccurate target localization
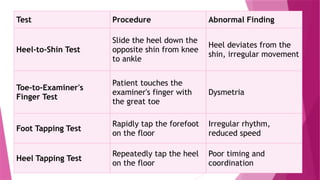
Test Procedure Abnormal Finding
Heel-to-Shin Test
Slide the heel down the
opposite shin from knee
to ankle
Heel deviates from the
shin, irregular movement
Toe-to-Examiner's
Finger Test
Patient touches the
examiner's finger with
the great toe
Dysmetria
Foot Tapping Test
Rapidly tap the forefoot
on the floor
Irregular rhythm,
reduced speed
Heel Tapping Test
Repeatedly tap the heel
on the floor
Poor timing and
coordination
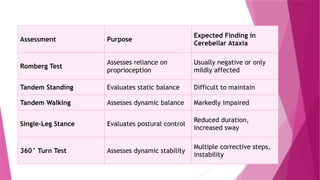
Assessment Purpose
Expected Finding in
Cerebellar Ataxia
Romberg Test
Assesses reliance on
proprioception
Usually negative or only
mildly affected
Tandem Standing Evaluates static balance Difficult to maintain
Tandem Walking Assesses dynamic balance Markedly impaired
Single-Leg Stance Evaluates postural control
Reduced duration,
increased sway
360° Turn Test Assesses dynamic stability
Multiple corrective steps,
instability
Sensory Ataxia
Sensory ataxia is a disorder of movement coordination caused by impaired proprioceptive input resulting
from lesions affecting the peripheral nerves, dorsal root ganglia, posterior (dorsal) columns of the spinal
cord, or the dorsal column–medial lemniscus (DCML) pathway. Although muscle strength and cerebellar
function may be preserved, patients are unable to accurately perceive the position and movement of their
limbs, leading to impaired balance and coordination.
Key Characteristics
 Loss of joint position sense (proprioception)
 Loss of vibration sense
 Unsteady gait that worsens in darkness or with eyes closed
 Positive Romberg sign
 Heavy dependence on visual feedback for movement
 Stamping gait
 Frequent falls, especially on uneven surfaces
The hallmark of sensory ataxia is impaired proprioception with preserved cerebellar function. Patients
compensate by watching their feet while walking.
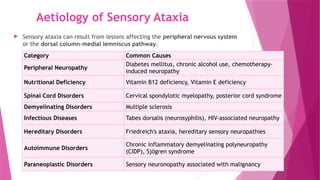
Aetiology of Sensory Ataxia
 Sensory ataxia can result from lesions affecting the peripheral nervous system
or the dorsal column–medial lemniscus pathway.
Category Common Causes
Peripheral Neuropathy
Diabetes mellitus, chronic alcohol use, chemotherapy-
induced neuropathy
Nutritional Deficiency Vitamin B12 deficiency, Vitamin E deficiency
Spinal Cord Disorders Cervical spondylotic myelopathy, posterior cord syndrome
Demyelinating Disorders Multiple sclerosis
Infectious Diseases Tabes dorsalis (neurosyphilis), HIV-associated neuropathy
Hereditary Disorders Friedreich's ataxia, hereditary sensory neuropathies
Autoimmune Disorders
Chronic inflammatory demyelinating polyneuropathy
(CIDP), Sjögren syndrome
Paraneoplastic Disorders Sensory neuronopathy associated with malignancy
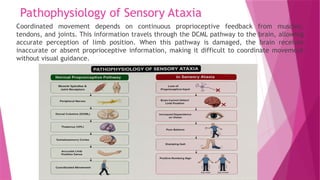
Pathophysiology of Sensory Ataxia
Coordinated movement depends on continuous proprioceptive feedback from muscles,
tendons, and joints. This information travels through the DCML pathway to the brain, allowing
accurate perception of limb position. When this pathway is damaged, the brain receives
inaccurate or absent proprioceptive information, making it difficult to coordinate movement
without visual guidance.
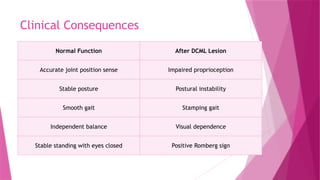
Clinical Consequences
Normal Function After DCML Lesion
Accurate joint position sense Impaired proprioception
Stable posture Postural instability
Smooth gait Stamping gait
Independent balance Visual dependence
Stable standing with eyes closed Positive Romberg sign
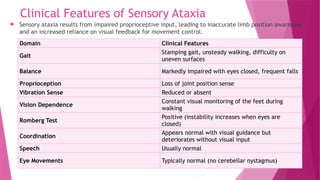
Clinical Features of Sensory Ataxia
 Sensory ataxia results from impaired proprioceptive input, leading to inaccurate limb position awareness
and an increased reliance on visual feedback for movement control.
Domain Clinical Features
Gait
Stamping gait, unsteady walking, difficulty on
uneven surfaces
Balance Markedly impaired with eyes closed, frequent falls
Proprioception Loss of joint position sense
Vibration Sense Reduced or absent
Vision Dependence
Constant visual monitoring of the feet during
walking
Romberg Test
Positive (instability increases when eyes are
closed)
Coordination
Appears normal with visual guidance but
deteriorates without visual input
Speech Usually normal
Eye Movements Typically normal (no cerebellar nystagmus)
Common Patient Complaints
 "I lose my balance in the dark."
 "I have to look at my feet while walking."
 "I feel like I'm walking on cotton."
 "I stumble more on uneven ground."
 "I can't tell where my feet are without looking."
A patient with sensory ataxia often compensates remarkably well in well-lit
environments but becomes significantly unstable when visual input is
removed.
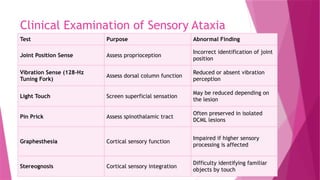
Clinical Examination of Sensory Ataxia
Test Purpose Abnormal Finding
Joint Position Sense Assess proprioception
Incorrect identification of joint
position
Vibration Sense (128-Hz
Tuning Fork)
Assess dorsal column function
Reduced or absent vibration
perception
Light Touch Screen superficial sensation
May be reduced depending on
the lesion
Pin Prick Assess spinothalamic tract
Often preserved in isolated
DCML lesions
Graphesthesia Cortical sensory function
Impaired if higher sensory
processing is affected
Stereognosis Cortical sensory integration
Difficulty identifying familiar
objects by touch
Functional Examination
 Observe the patient during:
 Standing with eyes open and closed
 Walking forward and backward
 Tandem walking
 Walking on uneven surfaces (if safe)
 Turning
 Stair negotiation
Always compare both sides and correlate sensory deficits with the patient's
functional limitations.
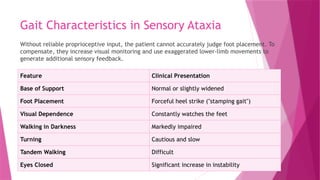
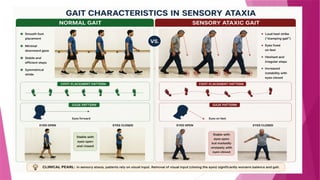
Gait Characteristics in Sensory Ataxia
Without reliable proprioceptive input, the patient cannot accurately judge foot placement. To
compensate, they increase visual monitoring and use exaggerated lower-limb movements to
generate additional sensory feedback.
Feature Clinical Presentation
Base of Support Normal or slightly widened
Foot Placement Forceful heel strike ("stamping gait")
Visual Dependence Constantly watches the feet
Walking in Darkness Markedly impaired
Turning Cautious and slow
Tandem Walking Difficult
Eyes Closed Significant increase in instability
Clinical Observation
Look for:
 Loud heel strike
 High-stepping or stamping gait
 Frequent downward gaze
 Hesitation on uneven terrain
 Increased sway when standing with eyes closed
The stamping gait is a compensatory strategy. Forcefully striking the ground increases sensory
feedback from the feet, partially compensating for impaired proprioception.
Cerebellar Ataxia vs Sensory Ataxia
Feature Cerebellar Ataxia Sensory Ataxia
Primary Site of Lesion Cerebellum or cerebellar pathways
Peripheral nerves, dorsal columns, or
DCML pathway
Primary Deficit Impaired coordination and motor error correction Loss of proprioceptive input
Muscle Strength Usually preserved
Usually preserved (unless associated
neuropathy)
Muscle Tone Hypotonia common Usually normal
Proprioception Normal Decreased or absent
Vibration Sense Normal Reduced or absent
Gait Pattern Wide-based, staggering gait Stamping gait with forceful heel strike
Base of Support Wide Normal or slightly widened
Visual Dependence Minimal Marked dependence on visual input
Romberg Test Usually negative Positive
Tandem Walking Severely impaired Impaired, especially with eyes closed
Limb Coordination Dysmetria, dysdiadochokinesia, intention tremor Improves with visual feedback
Speech Scanning (ataxic) dysarthria Normal
Eye Movements Nystagmus, ocular dysmetria Usually normal
Falls Any direction
More common in darkness or with eyes
closed
Representative Causes
Stroke, spinocerebellar ataxia, tumor, alcohol-
related degeneration
Peripheral neuropathy, vitamin B12
deficiency, cervical myelopathy, tabes
dorsalis
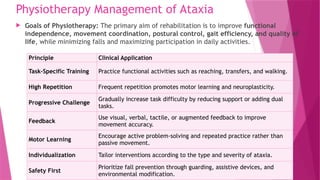
Physiotherapy Management of Ataxia
 Goals of Physiotherapy: The primary aim of rehabilitation is to improve functional
independence, movement coordination, postural control, gait efficiency, and quality of
life, while minimizing falls and maximizing participation in daily activities.
Principle Clinical Application
Task-Specific Training Practice functional activities such as reaching, transfers, and walking.
High Repetition Frequent repetition promotes motor learning and neuroplasticity.
Progressive Challenge
Gradually increase task difficulty by reducing support or adding dual
tasks.
Feedback
Use visual, verbal, tactile, or augmented feedback to improve
movement accuracy.
Motor Learning
Encourage active problem-solving and repeated practice rather than
passive movement.
Individualization Tailor interventions according to the type and severity of ataxia.
Safety First
Prioritize fall prevention through guarding, assistive devices, and
environmental modification.
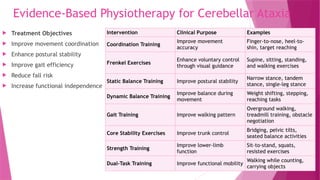
Evidence-Based Physiotherapy for Cerebellar Ataxia
 Treatment Objectives
 Improve movement coordination
 Enhance postural stability
 Improve gait efficiency
 Reduce fall risk
 Increase functional independence
Intervention Clinical Purpose Examples
Coordination Training
Improve movement
accuracy
Finger-to-nose, heel-to-
shin, target reaching
Frenkel Exercises
Enhance voluntary control
through visual guidance
Supine, sitting, standing,
and walking exercises
Static Balance Training Improve postural stability
Narrow stance, tandem
stance, single-leg stance
Dynamic Balance Training
Improve balance during
movement
Weight shifting, stepping,
reaching tasks
Gait Training Improve walking pattern
Overground walking,
treadmill training, obstacle
negotiation
Core Stability Exercises Improve trunk control
Bridging, pelvic tilts,
seated balance activities
Strength Training
Improve lower-limb
function
Sit-to-stand, squats,
resisted exercises
Dual-Task Training Improve functional mobility
Walking while counting,
carrying objects
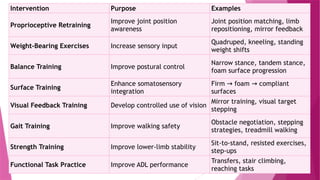
Evidence-Based Physiotherapy Management of
Sensory Ataxia
 Treatment Objectives
 Improve proprioceptive awareness
 Enhance postural stability
 Improve gait safety and efficiency
 Reduce visual dependence
 Prevent falls
 Improve functional independence
Intervention Purpose Examples
Proprioceptive Retraining
Improve joint position
awareness
Joint position matching, limb
repositioning, mirror feedback
Weight-Bearing Exercises Increase sensory input
Quadruped, kneeling, standing
weight shifts
Balance Training Improve postural control
Narrow stance, tandem stance,
foam surface progression
Surface Training
Enhance somatosensory
integration
Firm foam compliant
→ →
surfaces
Visual Feedback Training Develop controlled use of vision
Mirror training, visual target
stepping
Gait Training Improve walking safety
Obstacle negotiation, stepping
strategies, treadmill walking
Strength Training Improve lower-limb stability
Sit-to-stand, resisted exercises,
step-ups
Functional Task Practice Improve ADL performance
Transfers, stair climbing,
reaching tasks
Balance Training in Ataxia
 Progressive Balance Training: Balance exercises should progress from stable
to unstable, simple to complex, and static to dynamic tasks.
Level Exercise Examples
Level 1 Sitting balance, reaching in sitting
Level 2 Standing with wide base
Level 3 Narrow stance, semi-tandem, tandem stance
Level 4 Weight shifting, multidirectional reaching
Level 5 Stepping strategies, obstacle negotiation
Level 6 Dual-task balance, perturbation training
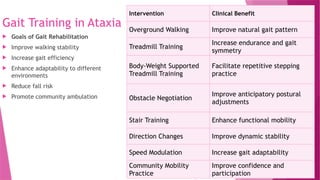
Gait Training in Ataxia
 Goals of Gait Rehabilitation
 Improve walking stability
 Increase gait efficiency
 Enhance adaptability to different
environments
 Reduce fall risk
 Promote community ambulation
Intervention Clinical Benefit
Overground Walking Improve natural gait pattern
Treadmill Training
Increase endurance and gait
symmetry
Body-Weight Supported
Treadmill Training
Facilitate repetitive stepping
practice
Obstacle Negotiation
Improve anticipatory postural
adjustments
Stair Training Enhance functional mobility
Direction Changes Improve dynamic stability
Speed Modulation Increase gait adaptability
Community Mobility
Practice
Improve confidence and
participation
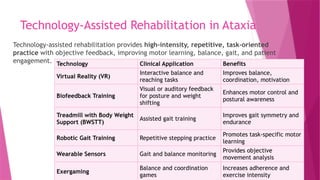
Technology-Assisted Rehabilitation in Ataxia
Technology-assisted rehabilitation provides high-intensity, repetitive, task-oriented
practice with objective feedback, improving motor learning, balance, gait, and patient
engagement. Technology Clinical Application Benefits
Virtual Reality (VR)
Interactive balance and
reaching tasks
Improves balance,
coordination, motivation
Biofeedback Training
Visual or auditory feedback
for posture and weight
shifting
Enhances motor control and
postural awareness
Treadmill with Body Weight
Support (BWSTT)
Assisted gait training
Improves gait symmetry and
endurance
Robotic Gait Training Repetitive stepping practice
Promotes task-specific motor
learning
Wearable Sensors Gait and balance monitoring
Provides objective
movement analysis
Exergaming
Balance and coordination
games
Increases adherence and
exercise intensity
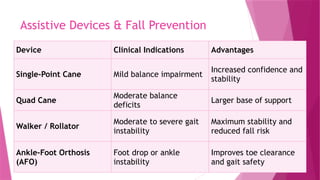
Assistive Devices & Fall Prevention
Device Clinical Indications Advantages
Single-Point Cane Mild balance impairment
Increased confidence and
stability
Quad Cane

Moderate balance
deficits
Larger base of support
Walker / Rollator
Moderate to severe gait
instability
Maximum stability and
reduced fall risk
Ankle-Foot Orthosis
(AFO)
Foot drop or ankle
instability
Improves toe clearance
and gait safety
Fall Prevention Strategies
Patient Education
 Wear appropriate footwear.
 Avoid slippery surfaces.
 Ensure adequate lighting at home.
 Remove loose rugs and obstacles.
 Use handrails on stairs.
Physiotherapy Strategies
 Balance training
 Strengthening exercises
 Reactive stepping practice
 Safe transfer training
 Home hazard assessment
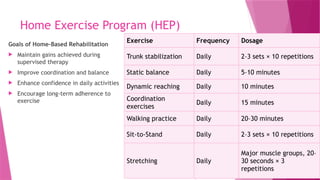
Home Exercise Program (HEP)
Goals of Home-Based Rehabilitation
 Maintain gains achieved during
supervised therapy
 Improve coordination and balance
 Enhance confidence in daily activities
 Encourage long-term adherence to
exercise
Exercise Frequency Dosage
Trunk stabilization Daily 2–3 sets × 10 repetitions
Static balance Daily 5–10 minutes
Dynamic reaching Daily 10 minutes
Coordination
exercises
Daily 15 minutes
Walking practice Daily 20–30 minutes
Sit-to-Stand Daily 2–3 sets × 10 repetitions
Stretching Daily
Major muscle groups, 20–
30 seconds × 3
repetitions
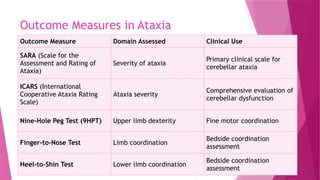
Outcome Measures in Ataxia
Outcome Measure Domain Assessed Clinical Use
SARA (Scale for the
Assessment and Rating of
Ataxia)
Severity of ataxia
Primary clinical scale for
cerebellar ataxia
ICARS (International
Cooperative Ataxia Rating
Scale)
Ataxia severity
Comprehensive evaluation of
cerebellar dysfunction
Nine-Hole Peg Test (9HPT) Upper limb dexterity Fine motor coordination
Finger-to-Nose Test Limb coordination
Bedside coordination
assessment
Heel-to-Shin Test Lower limb coordination
Bedside coordination
assessment
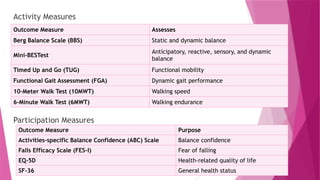
Activity Measures
Participation Measures
Outcome Measure Assesses
Berg Balance Scale (BBS) Static and dynamic balance
Mini-BESTest
Anticipatory, reactive, sensory, and dynamic
balance
Timed Up and Go (TUG) Functional mobility
Functional Gait Assessment (FGA) Dynamic gait performance
10-Meter Walk Test (10MWT) Walking speed
6-Minute Walk Test (6MWT) Walking endurance
Outcome Measure Purpose
Activities-specific Balance Confidence (ABC) Scale Balance confidence
Falls Efficacy Scale (FES-I) Fear of falling
EQ-5D Health-related quality of life
SF-36 General health status
Key Take-Home Messages
 Ataxia is a clinical sign, not a disease.
 Cerebellar ataxia results from impaired motor coordination, whereas sensory ataxia results
from impaired proprioception.
 A positive Romberg test strongly suggests sensory ataxia.
 Dysmetria, dysdiadochokinesia, intention tremor, and nystagmus are characteristic of
cerebellar ataxia.
 Stamping gait and visual dependence are hallmarks of sensory ataxia.
 Early physiotherapy improves balance, gait, coordination, and functional independence.
 Task-specific, repetitive, and progressive practice promotes motor learning and
neuroplasticity.
 Rehabilitation should be individualized using the ICF framework.
 Standardized outcome measures should guide clinical decision-making and monitor progress.
 Effective rehabilitation combines clinical expertise, patient-centered goals, and evidence-
based practice.
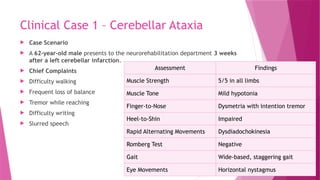
Clinical Case 1 – Cerebellar Ataxia
 Case Scenario
 A 62-year-old male presents to the neurorehabilitation department 3 weeks
after a left cerebellar infarction.
 Chief Complaints
 Difficulty walking
 Frequent loss of balance
 Tremor while reaching
 Difficulty writing
 Slurred speech
Assessment Findings
Muscle Strength 5/5 in all limbs
Muscle Tone Mild hypotonia
Finger-to-Nose Dysmetria with intention tremor
Heel-to-Shin Impaired
Rapid Alternating Movements Dysdiadochokinesia
Romberg Test Negative
Gait Wide-based, staggering gait
Eye Movements Horizontal nystagmus
References
 Bastian AJ. Mechanisms of ataxia. Physical Therapy. 1997.
 Ilg W, Synofzik M, Brötz D, et al. Intensive coordinative training improves motor performance
in degenerative cerebellar disease. Neurology. 2009.
 Marquer A, Barbieri G, Pérennou D. The assessment and treatment of postural disorders in
cerebellar ataxia: A systematic review. Annals of Physical and Rehabilitation Medicine. 2014.
 Winser SJ, Smith C, Hale LA, et al. Motor rehabilitation in people with hereditary
degenerative cerebellar ataxia: A systematic review. Clinical Rehabilitation. 2020.
 Miyai I, Ito M, Hattori N, et al. Cerebellar ataxia rehabilitation trial. Neurorehabilitation and
Neural Repair.
 American Physical Therapy Association (APTA). Neurologic Physical Therapy Practice
Resources.
 European Academy of Neurology (EAN). Guidelines for the diagnosis and management of
cerebellar disorders.
 World Health Organization. International Classification of Functioning, Disability and Health
(ICF). Geneva: WHO; 2001.
Which type of ataxia is most likely?
 ⬜ Sensory Ataxia
 ⬜ Vestibular Ataxia
 ⬜ Cerebellar Ataxia ✅
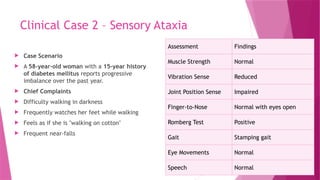
Clinical Case 2 – Sensory Ataxia
 Case Scenario
 A 58-year-old woman with a 15-year history
of diabetes mellitus reports progressive
imbalance over the past year.
 Chief Complaints
 Difficulty walking in darkness
 Frequently watches her feet while walking
 Feels as if she is "walking on cotton"
 Frequent near-falls
Assessment Findings
Muscle Strength Normal
Vibration Sense Reduced
Joint Position Sense Impaired
Finger-to-Nose Normal with eyes open
Romberg Test Positive
Gait Stamping gait
Eye Movements Normal
Speech Normal
 Which type of ataxia is most likely?
 ⬜ Cerebellar Ataxia
 ⬜ Sensory Ataxia ✅
 ⬜ Vestibular Ataxia
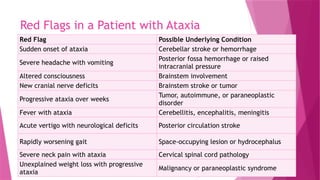
Red Flags in a Patient with Ataxia
Red Flag Possible Underlying Condition
Sudden onset of ataxia Cerebellar stroke or hemorrhage
Severe headache with vomiting
Posterior fossa hemorrhage or raised
intracranial pressure
Altered consciousness Brainstem involvement
New cranial nerve deficits Brainstem stroke or tumor
Progressive ataxia over weeks
Tumor, autoimmune, or paraneoplastic
disorder
Fever with ataxia Cerebellitis, encephalitis, meningitis
Acute vertigo with neurological deficits Posterior circulation stroke
Rapidly worsening gait Space-occupying lesion or hydrocephalus
Severe neck pain with ataxia Cervical spinal cord pathology
Unexplained weight loss with progressive
ataxia
Malignancy or paraneoplastic syndrome
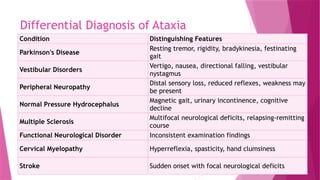
Differential Diagnosis of Ataxia
Condition Distinguishing Features
Parkinson's Disease
Resting tremor, rigidity, bradykinesia, festinating
gait
Vestibular Disorders
Vertigo, nausea, directional falling, vestibular
nystagmus
Peripheral Neuropathy
Distal sensory loss, reduced reflexes, weakness may
be present
Normal Pressure Hydrocephalus
Magnetic gait, urinary incontinence, cognitive
decline
Multiple Sclerosis
Multifocal neurological deficits, relapsing-remitting
course
Functional Neurological Disorder Inconsistent examination findings
Cervical Myelopathy Hyperreflexia, spasticity, hand clumsiness
Stroke Sudden onset with focal neurological deficits
Thank You