



















































Cardiac Care Unit (CCU) Excellence Manual Dr J L Meena
Cardiac Care Unit (CCU) Excellence Manual – Dr J L Meena | Page 1
CARDIAC CARE UNIT (CCU)
EXCELLENCE MANUAL
Global Standards for Cardiac Critical Care Excellence, Patient Safety, and Quality
Healthcare
A Comprehensive Reference for
THE MULTIDISCIPLINARY CARDIAC CRITICAL CARE TEAM
Cardiologists • CCU Nurses • Cardiac Catheterization Teams • Cardiac Rehabilitation & Allied Cardiac Care
Professionals
“Every Heartbeat on the Monitor Is a Question the CCU Team Must Answer Before It Becomes
Silence.”
Dr J L Meena
Cardiac Care Unit (CCU) Excellence Manual Dr J L Meena
Cardiac Care Unit (CCU) Excellence Manual – Dr J L Meena | Page 2
DEDICATION
This book is dedicated to all those who are committed to advancing healthcare through the unblinking vigilance
a heart in crisis demands, and the decisive action only minutes can reward.
To Every Patient in the CCU
For whom every minute shaved from door-to-balloon time, every arrhythmia caught on the monitor before it
became cardiac arrest, and every anticoagulant dose calculated with exacting precision represents heart
muscle preserved, and a life continued rather than cut short.
To Every Family in the Waiting Room
For whom the CCU is the place where a single moment — a chest pain, a collapse, a diagnosis — changes
everything, and who deserve a team that treats their fear and their hope with the same rigour it applies to
every clinical decision.
To My Family
For their unwavering love, patience, and encouragement, which have been the foundation of this journey.
To My Mentors & Teachers
For inspiring my passion, guiding my path, and instilling in me the understanding that in cardiac care, time is
muscle, and muscle, once lost, does not return.
To My Colleagues & Friends
For their support, collaboration, and shared dedication to a unit where every rhythm on every monitor is
watched as though it were the only one that mattered.
To Every Member of the CCU Team
Cardiologists, CCU nurses, catheterization laboratory teams, and every professional who has read a rhythm
strip correctly in the seconds that mattered most — the guardians of the heart's most fragile hours.
Your vigilance, your precision, and your decisive readiness for the heart that can fail without warning are
the silent pillars of a healthcare system that gives every cardiac patient the fullest possible chance at
survival and recovery. This book is for you, and because of you. Thank you to everyone who has been a part
of this journey.
Dr J L Meena
Cardiac Care Unit (CCU) Excellence Manual Dr J L Meena
Cardiac Care Unit (CCU) Excellence Manual – Dr J L Meena | Page 3
FOREWORD
There is a phrase that defines the entire discipline of cardiac critical care more precisely than any other: time
is muscle. Every minute that passes between the onset of a heart attack and the restoration of blood flow costs
heart muscle that will never regenerate, never contract again, never pump blood to a body that depends on it
for the rest of a life that continues long after this single crisis has passed. A cardiac arrhythmia detected on a
monitor and treated within seconds is a recovery; the same arrhythmia missed for even a few minutes can be
a cardiac arrest. The Cardiac Care Unit exists because the heart, when it fails, does not fail gradually and gently
— it fails suddenly, and the team watching over it must be positioned to act before the failure becomes
irreversible.
The “Cardiac Care Unit (CCU) Excellence Manual: Global Standards for Cardiac Critical Care Excellence, Patient
Safety, and Quality Healthcare” has been developed to provide a comprehensive professional framework for
the multidisciplinary CCU team — cardiologists, CCU nurses, cardiac catheterization teams, and allied cardiac
critical care professionals — working together to protect patients whose survival is frequently measured in
minutes rather than hours.
This manual brings together internationally recognized principles of acute coronary syndrome and STEMI
management, door-to-balloon and door-to-needle time optimization, continuous cardiac rhythm monitoring
and arrhythmia management, cardiogenic shock and mechanical circulatory support, high-alert cardiac
medication safety (anticoagulants, thrombolytics, antiarrhythmics), post-catheterization and post-cardiac-
surgery care, cardiac rehabilitation initiation, and continuous quality improvement specific to cardiac critical
care. It is built around globally accepted accreditation frameworks — WHO cardiovascular disease guidelines,
NABH, JCI, American Heart Association/American College of Cardiology (AHA/ACC) and European Society of
Cardiology (ESC) standards — to provide a rigorous, regulation-compliant framework for CCU excellence.
The chapters of this manual guide the CCU team through every dimension of the role — from admission and
continuous rhythm monitoring, through acute coronary syndrome and heart failure management, arrhythmia
recognition and defibrillation readiness, anticoagulation and bleeding risk management, to cardiac
rehabilitation, discharge planning, and the professional conduct that defines excellence across every category
of cardiac emergency: the STEMI requiring immediate reperfusion, the cardiogenic shock requiring mechanical
support, and every patient whose heart's next few minutes will determine the years that follow.
The CCU is not simply a general intensive care unit for patients who happen to have heart disease — it is a
distinct discipline built on the understanding that cardiac time-sensitivity is unlike almost any other area of
critical care, that a rhythm strip must be read correctly within seconds, and that the medications used to treat
the heart — anticoagulants, thrombolytics, antiarrhythmics — carry among the narrowest safety margins in all
of pharmacology. Their work is defined by a vigilance that must never lapse, because a heart's rhythm can
change from stable to fatal in the time it takes to look away from the monitor.
It is hoped that this manual will serve as an indispensable resource for Cardiologists, CCU Nurses, Cardiac
Catheterization Teams, Cardiac Rehabilitation Specialists, hospital administrators, quality heads, and all those
Cardiac Care Unit (CCU) Excellence Manual Dr J L Meena
Cardiac Care Unit (CCU) Excellence Manual – Dr J L Meena | Page 4
committed to building a healthcare system where cardiac critical care is delivered with the speed, precision,
vigilance, and compassion that the heart's most vulnerable hours demand.
“Every Heartbeat on the Monitor Is a Question the CCU Team Must Answer Before It Becomes Silence.”
With Best Wishes, Dr J L Meena
Cardiac Care Unit (CCU) Excellence Manual Dr J L Meena
Cardiac Care Unit (CCU) Excellence Manual – Dr J L Meena | Page 5
TABLE OF CONTENTS
FOREWORD............................................................................................................................................3
LIST OF ABBREVIATIONS........................................................................................................................7
MANUAL MOTTO...................................................................................................................................9
CHAPTER 1: Introduction.....................................................................................................................10
Purpose...........................................................................................................................................................10
Objectives .......................................................................................................................................................11
Vision & Mission .............................................................................................................................................13
CHAPTER 2: Role of the CCU Team in Quality Healthcare..................................................................14
Admission & Continuous Rhythm Monitoring................................................................................................14
Acute Coronary Syndrome & STEMI Management.........................................................................................14
Arrhythmia Recognition & Defibrillation Readiness .......................................................................................15
Cardiogenic Shock & Mechanical Circulatory Support....................................................................................15
High-Alert Cardiac Medication Safety.............................................................................................................16
Post-Catheterization & Post-Cardiac-Surgery Care.........................................................................................16
Heart Failure Management.............................................................................................................................16
Cardiac Rehabilitation & Discharge Planning..................................................................................................17
CHAPTER 3: Professional Standards for the CCU Team......................................................................17
Professional Appearance & Behaviour ...........................................................................................................17
Communication Standards .............................................................................................................................18
Confidentiality & Information Security...........................................................................................................19
Ethical Standards ............................................................................................................................................19
Time Management, Teamwork & Continuous Learning.................................................................................20
CHAPTER 4: Patient- and Family-Centered Communication in the CCU ............................................21
The A-T-C-R-C Communication Model............................................................................................................21
Communicating Risk, Prognosis & Sudden Cardiac Events.............................................................................22
CHAPTER 5: Patient Safety and Cardiac Critical Care Standards ........................................................24
The R-T-A-C-A Framework ..............................................................................................................................24
Daily Quality Standards Checklist ...................................................................................................................26
CHAPTER 6: Confidentiality, Privacy, and Information Security ........................................................27
Privacy in the Continuous Monitoring Environment ......................................................................................27
Cybersecurity of Cardiac Information Systems...............................................................................................28
CHAPTER 7: Standard Operating Procedures (SOPs)..........................................................................29
SOP 1: CCU Admission and Continuous Monitoring Setup.............................................................................29
SOP 2: STEMI Protocol and Door-to-Balloon Time .........................................................................................29
Cardiac Care Unit (CCU) Excellence Manual Dr J L Meena
Cardiac Care Unit (CCU) Excellence Manual – Dr J L Meena | Page 6
SOP 3: Thrombolysis and Door-to-Needle Time .............................................................................................30
SOP 4: Malignant Arrhythmia Recognition and Response..............................................................................30
SOP 5: Defibrillation and Synchronized Cardioversion ...................................................................................31
SOP 6: Anticoagulation and Bleeding Risk Management................................................................................31
SOP 7: Cardiogenic Shock and Mechanical Circulatory Support.....................................................................32
SOP 8: Post-Catheterization Access Site Monitoring......................................................................................32
SOP 9: Heart Failure Decompensation Management.....................................................................................33
SOP 10: Cardiac Rehabilitation Initiation and Discharge Planning .................................................................33
CHAPTER 8: Communication with Special Groups..............................................................................34
CHAPTER 9: Handling Difficult Situations ...........................................................................................36
CHAPTER 10: Emergency Response — Critical Cardiac Presentations ...............................................39
CHAPTER 11: Digital Competency for the CCU Team..........................................................................42
CHAPTER 12: Daily CCU Checklist........................................................................................................44
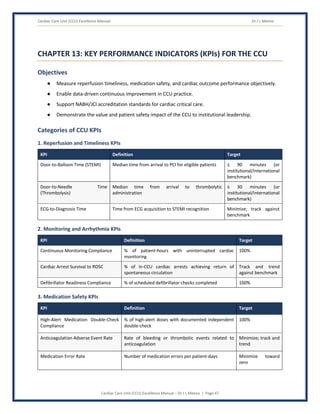
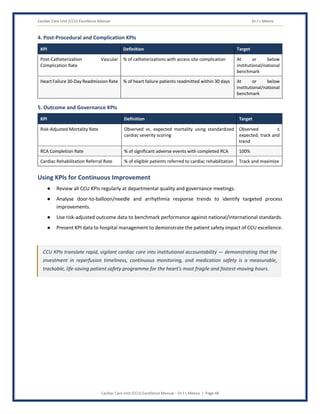
CHAPTER 13: Key Performance Indicators (KPIs)................................................................................46
CHAPTER 14: Top 20 Do's & Top 20 Don'ts.........................................................................................48
CHAPTER 15: CCU Professional Pledge................................................................................................51
CONCLUSION........................................................................................................................................54
REFERENCES.........................................................................................................................................56
Cardiac Care Unit (CCU) Excellence Manual Dr J L Meena
Cardiac Care Unit (CCU) Excellence Manual – Dr J L Meena | Page 7
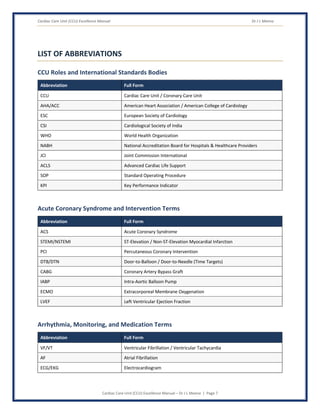
LIST OF ABBREVIATIONS
CCU Roles and International Standards Bodies
Abbreviation Full Form
CCU Cardiac Care Unit / Coronary Care Unit
AHA/ACC American Heart Association / American College of Cardiology
ESC European Society of Cardiology
CSI Cardiological Society of India
WHO World Health Organization
NABH National Accreditation Board for Hospitals & Healthcare Providers
JCI Joint Commission International
ACLS Advanced Cardiac Life Support
SOP Standard Operating Procedure
KPI Key Performance Indicator
Acute Coronary Syndrome and Intervention Terms
Abbreviation Full Form
ACS Acute Coronary Syndrome
STEMI/NSTEMI ST-Elevation / Non-ST-Elevation Myocardial Infarction
PCI Percutaneous Coronary Intervention
DTB/DTN Door-to-Balloon / Door-to-Needle (Time Targets)
CABG Coronary Artery Bypass Graft
IABP Intra-Aortic Balloon Pump
ECMO Extracorporeal Membrane Oxygenation
LVEF Left Ventricular Ejection Fraction
Arrhythmia, Monitoring, and Medication Terms
Abbreviation Full Form
VF/VT Ventricular Fibrillation / Ventricular Tachycardia
AF Atrial Fibrillation
ECG/EKG Electrocardiogram
Cardiac Care Unit (CCU) Excellence Manual Dr J L Meena
Cardiac Care Unit (CCU) Excellence Manual – Dr J L Meena | Page 8
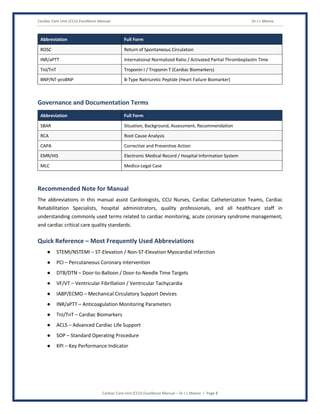
Abbreviation Full Form
ROSC Return of Spontaneous Circulation
INR/aPTT International Normalized Ratio / Activated Partial Thromboplastin Time
TnI/TnT Troponin I / Troponin T (Cardiac Biomarkers)
BNP/NT-proBNP B-Type Natriuretic Peptide (Heart Failure Biomarker)
Governance and Documentation Terms
Abbreviation Full Form
SBAR Situation, Background, Assessment, Recommendation
RCA Root Cause Analysis
CAPA Corrective and Preventive Action
EMR/HIS Electronic Medical Record / Hospital Information System
MLC Medico-Legal Case
Recommended Note for Manual
The abbreviations in this manual assist Cardiologists, CCU Nurses, Cardiac Catheterization Teams, Cardiac
Rehabilitation Specialists, hospital administrators, quality professionals, and all healthcare staff in
understanding commonly used terms related to cardiac monitoring, acute coronary syndrome management,
and cardiac critical care quality standards.
Quick Reference – Most Frequently Used Abbreviations
● STEMI/NSTEMI – ST-Elevation / Non-ST-Elevation Myocardial Infarction
● PCI – Percutaneous Coronary Intervention
● DTB/DTN – Door-to-Balloon / Door-to-Needle Time Targets
● VF/VT – Ventricular Fibrillation / Ventricular Tachycardia
● IABP/ECMO – Mechanical Circulatory Support Devices
● INR/aPTT – Anticoagulation Monitoring Parameters
● TnI/TnT – Cardiac Biomarkers
● ACLS – Advanced Cardiac Life Support
● SOP – Standard Operating Procedure
● KPI – Key Performance Indicator
Cardiac Care Unit (CCU) Excellence Manual Dr J L Meena
Cardiac Care Unit (CCU) Excellence Manual – Dr J L Meena | Page 9
MANUAL MOTTO
“Every Heartbeat on the Monitor”
“Is a Question the CCU Team Must Answer”
“Before It Becomes Silence.”
Cardiac Care Unit (CCU) Excellence Manual Dr J L Meena
Cardiac Care Unit (CCU) Excellence Manual – Dr J L Meena | Page 10
CHAPTER 1: INTRODUCTION
1. Purpose
Time is muscle. No phrase in medicine carries a more precise, more urgent, or more unforgiving truth than this
one applied to the heart. Every minute that passes between the onset of coronary occlusion and the restoration
of blood flow costs heart muscle that will never regenerate — muscle that determines not only whether a
patient survives their heart attack, but how they will live for every year that follows it. A malignant arrhythmia
detected on a monitor and treated within seconds is a save; the same arrhythmia unnoticed for even a few
additional minutes is a cardiac arrest, and often, a death. The Cardiac Care Unit exists because the heart does
not fail gradually — it fails suddenly, catastrophically, and often without more than seconds of warning, and
the team watching over it must be positioned, continuously, to act before that failure becomes irreversible.
The World Health Organization and the American Heart Association/American College of Cardiology, alongside
the European Society of Cardiology, recognize that structured, time-sensitive protocols for acute coronary
syndrome — with defined door-to-balloon and door-to-needle targets, continuous rhythm monitoring, and
rehearsed arrhythmia and cardiogenic shock response — are directly and measurably linked to reductions in
cardiac mortality and long-term heart failure burden. Research consistently demonstrates that CCUs applying
rigorous STEMI protocols, continuous cardiac monitoring with rapid arrhythmia response, and precise high-
alert cardiac medication safety achieve dramatically and measurably better survival and functional cardiac
outcomes than units relying on unstructured, delayed, or ad hoc cardiac management. In institutions where
the CCU team applies systematic rhythm monitoring, rapid reperfusion protocols, and rigorous anticoagulation
safety, patient survival and long-term cardiac function are demonstrably and measurably better. The
investment in CCU excellence is, without qualification, one of the highest-yield investments any healthcare
system can make — protecting not only a single crisis, but the decades of life a preserved heart makes possible.
Why the CCU Team Is Critical to Healthcare Quality
● Provides continuous, high-acuity cardiac rhythm monitoring where seconds, not minutes, determine
whether an arrhythmia is caught in time.
● Applies time-sensitive STEMI and acute coronary syndrome protocols that directly determine how
much heart muscle survives a myocardial infarction.
● Maintains rehearsed defibrillation and cardioversion readiness for the malignant arrhythmia that can
occur without warning.
● Applies rigorous high-alert medication safety for anticoagulants, thrombolytics, and antiarrhythmics,
drugs with among the narrowest safety margins in pharmacology.
● Coordinates cardiogenic shock recognition and mechanical circulatory support for the heart too weak
to sustain circulation alone.
● Delivers post-catheterization and post-cardiac-surgery care that protects patients through the critical
hours following intervention.
Cardiac Care Unit (CCU) Excellence Manual Dr J L Meena
Cardiac Care Unit (CCU) Excellence Manual – Dr J L Meena | Page 11
● Initiates cardiac rehabilitation and discharge planning that protects against heart failure readmission
and supports long-term cardiac health.
● Maintains regulatory compliance with national cardiac care standards and international accreditation
guidelines.
● Contributes to accreditation compliance (NABH, JCI) for cardiac critical care standards.
Key Responsibilities of the CCU Team
● Conducting systematic admission assessment and initiating continuous cardiac rhythm monitoring for
every patient.
● Applying time-sensitive STEMI protocols to minimize door-to-balloon and door-to-needle times.
● Recognizing and responding immediately to malignant arrhythmias with defibrillation or cardioversion
as indicated.
● Applying rigorous, weight- and renal-function-based dosing for high-alert cardiac medications with
independent double-check.
● Recognizing and managing cardiogenic shock, coordinating mechanical circulatory support where
indicated.
● Monitoring post-catheterization access sites and post-cardiac-surgery patients for complications.
● Managing acute heart failure decompensation and optimizing haemodynamic status.
● Initiating cardiac rehabilitation and coordinating structured discharge planning to prevent
readmission.
● Engaging in continuous professional development to maintain competence in evolving cardiac care
evidence.
2. Objectives
1. Minimize Time to Reperfusion for Acute Coronary Syndrome
Every STEMI patient must receive reperfusion therapy within evidence-based time targets. This is the CCU's
primary patient safety obligation, grounded in the principle that time is muscle.
How to Achieve:
● Apply standardized STEMI activation protocols immediately upon ECG confirmation.
● Minimize door-to-balloon time for primary PCI to within international benchmark targets.
● Minimize door-to-needle time for thrombolysis where primary PCI is not immediately available.
2. Maintain Continuous, Vigilant Rhythm Monitoring
● Apply continuous cardiac monitoring for every admitted patient, with immediate alarm response.
● Recognize malignant arrhythmias promptly and apply defibrillation or cardioversion without delay.
● Maintain rehearsed, drilled response protocols for cardiac arrest.
Cardiac Care Unit (CCU) Excellence Manual Dr J L Meena
Cardiac Care Unit (CCU) Excellence Manual – Dr J L Meena | Page 12
3. Apply Rigorous High-Alert Cardiac Medication Safety
● Apply weight- and renal-function-based dosing with independent double-check for every high-alert
cardiac medication.
● Monitor anticoagulation parameters (INR, aPTT) systematically and adjust dosing accordingly.
● Apply structured bleeding risk assessment alongside anticoagulation management.
4. Recognize and Manage Cardiogenic Shock
● Apply systematic haemodynamic assessment to recognize cardiogenic shock promptly.
● Coordinate mechanical circulatory support (IABP, ECMO) for eligible refractory cases.
5. Support Cardiac Rehabilitation and Prevent Readmission
● Initiate cardiac rehabilitation assessment and early mobilization per protocol.
● Apply structured discharge planning addressing medication adherence and risk factor modification.
6. Maintain Regulatory and Accreditation Compliance
● Comply with national cardiac care standards and international accreditation guidelines.
● Maintain NABH/JCI cardiac critical care documentation standards.
● Participate in accreditation surveys with complete, auditable CCU care records.
3. Vision
Vision Statement
“To build and maintain a Cardiac Care Unit where every STEMI receives reperfusion within evidence-based
time targets, every arrhythmia is caught and treated before it becomes catastrophic, every high-alert cardiac
medication is dosed with exacting precision, and no patient is ever harmed by a preventable delay, missed
rhythm change, or medication error.”
4. Mission
Mission Statement
“To deliver safe, rapid, evidence-based, and vigilant cardiac critical care that protects patients from harm
through time-sensitive reperfusion protocols, continuous rhythm monitoring, and rigorous high-alert
medication safety, while maintaining regulatory compliance and enabling the healthcare organization to
provide quality cardiac care with confidence in its readiness for the heart's most fragile and fastest-moving
hours.”
Expected Outcomes of an Excellent CCU Practice
● Door-to-balloon time for STEMI maintained within international benchmark targets (e.g., ≤ 90
minutes) for 100% of eligible cases.
● Door-to-needle time for thrombolysis maintained within benchmark targets (e.g., ≤ 30 minutes) where
applicable.
Cardiac Care Unit (CCU) Excellence Manual Dr J L Meena
Cardiac Care Unit (CCU) Excellence Manual – Dr J L Meena | Page 13
● 100% of high-alert cardiac medications administered with documented independent double-check.
● Continuous rhythm monitoring maintained without lapse for 100% of admitted patients.
● Cardiac arrest response time and defibrillation readiness tested and verified per regular schedule.
● Complete, accurate, and NABH/JCI-compliant cardiac care documentation.
● All significant cardiac adverse events reviewed with documented RCA and CAPA.
● Full compliance with national cardiac care standards and international accreditation guidelines.
The CCU team protects patients whose survival is measured in the minutes between coronary occlusion
and reperfusion, between a malignant arrhythmia and a defibrillator's response — their continuous
monitoring is a vigilance that must never lapse, their time-sensitive protocols are what preserve heart
muscle that cannot regenerate, and their medication precision is the safeguard between healing and harm
in drugs with the narrowest margins in all of pharmacology.
Cardiac Care Unit (CCU) Excellence Manual Dr J L Meena
Cardiac Care Unit (CCU) Excellence Manual – Dr J L Meena | Page 14
CHAPTER 2: ROLE OF THE CCU TEAM IN QUALITY HEALTHCARE
1. Admission and Continuous Rhythm Monitoring
Overview
Continuous cardiac rhythm monitoring is the foundational safety mechanism of the CCU — the uninterrupted
surveillance that catches the malignant arrhythmia in the seconds after it begins, not the minutes after it has
already caused harm.
Responsibilities
● Initiate continuous cardiac monitoring immediately upon admission for every eligible patient.
● Apply systematic admission assessment including 12-lead ECG, cardiac biomarkers, and risk
stratification.
● Respond to every monitor alarm promptly, applying clinical judgment to distinguish genuine
deterioration from artifact.
2. Acute Coronary Syndrome and STEMI Management
Overview
STEMI management represents the clearest application of “time is muscle” in all of cardiac care — every minute
of delay to reperfusion directly costs viable heart muscle that will not recover.
Responsibilities
● Apply standardized STEMI activation protocols immediately upon ECG confirmation.
● Minimize door-to-balloon time for primary PCI or door-to-needle time for thrombolysis within
evidence-based targets.
● Coordinate rapid, seamless activation of the cardiac catheterization laboratory team.
3. Arrhythmia Recognition and Defibrillation Readiness
Overview
Malignant arrhythmias — ventricular fibrillation, pulseless ventricular tachycardia — can occur without
warning in a cardiac patient, demanding continuous readiness for immediate defibrillation.
Responsibilities
● Maintain continuous defibrillator readiness at every bedside or immediately accessible location.
● Recognize malignant arrhythmias immediately and apply defibrillation or synchronized cardioversion
per protocol.
● Apply Advanced Cardiac Life Support (ACLS) protocols systematically for cardiac arrest.
Cardiac Care Unit (CCU) Excellence Manual Dr J L Meena
Cardiac Care Unit (CCU) Excellence Manual – Dr J L Meena | Page 15
4. Cardiogenic Shock and Mechanical Circulatory Support
Overview
Cardiogenic shock represents the heart's inability to sustain adequate circulation independently, requiring
rapid recognition and, in refractory cases, mechanical circulatory support.
Responsibilities
● Apply systematic haemodynamic assessment to recognize cardiogenic shock promptly.
● Coordinate pharmacological support (inotropes, vasopressors) per evidence-based protocol.
● Coordinate mechanical circulatory support (intra-aortic balloon pump, ECMO) for eligible refractory
cases.
5. High-Alert Cardiac Medication Safety
Overview
Anticoagulants, thrombolytics, and antiarrhythmics carry among the narrowest safety margins in all of
pharmacology, where a dosing error can cause catastrophic bleeding or fatal arrhythmia.
Responsibilities
● Apply weight- and renal-function-based dosing with independent double-check for every high-alert
cardiac medication.
● Monitor anticoagulation parameters (INR, aPTT) systematically and adjust dosing per protocol.
● Apply structured bleeding risk assessment alongside every anticoagulation decision.
6. Post-Catheterization and Post-Cardiac-Surgery Care
Overview
The hours following cardiac catheterization or surgery carry genuine risk of bleeding, vascular complication, or
haemodynamic instability, requiring structured, vigilant monitoring.
Responsibilities
● Monitor catheterization access sites systematically for bleeding or vascular complication.
● Apply structured post-cardiac-surgery haemodynamic and rhythm monitoring.
● Coordinate rapid escalation for any post-procedural complication.
7. Heart Failure Management
Overview
Acute heart failure decompensation requires careful haemodynamic optimization, balancing fluid
management, medication titration, and monitoring for both under- and over-correction.
Cardiac Care Unit (CCU) Excellence Manual Dr J L Meena
Cardiac Care Unit (CCU) Excellence Manual – Dr J L Meena | Page 16
Responsibilities
● Apply evidence-based decongestion and haemodynamic optimization protocols.
● Monitor fluid balance, renal function, and clinical response systematically.
● Optimize guideline-directed medical therapy before discharge.
8. Cardiac Rehabilitation and Discharge Planning
Overview
Structured cardiac rehabilitation initiation and discharge planning directly reduce heart failure readmission and
support long-term cardiac health, extending the CCU's impact beyond the acute admission.
Responsibilities
● Initiate cardiac rehabilitation assessment and early, appropriate mobilization.
● Apply structured discharge planning addressing medication adherence, risk factor modification, and
follow-up coordination.
● Provide comprehensive patient education on warning signs requiring return to care.
How the CCU Team Contributes to Quality Healthcare
● By maintaining continuous rhythm monitoring, the team catches malignant arrhythmias in the seconds
that determine survival.
● By minimizing time to reperfusion, the team preserves heart muscle that cannot regenerate once lost.
● By applying rigorous medication safety, the team prevents the catastrophic errors this narrow-margin
pharmacology is uniquely vulnerable to.
● By recognizing cardiogenic shock early, the team intervenes before circulatory collapse becomes
irreversible.
● By initiating cardiac rehabilitation, the team extends protection beyond the acute crisis into the years
of life that follow it.
The CCU team protects a heart that fails suddenly, not gradually — their continuous monitoring is a
vigilance that must never lapse, their time-sensitive reperfusion protocols preserve muscle that will not
regenerate, and their medication precision is the safeguard between healing and harm in the narrowest-
margin pharmacology in medicine.
Cardiac Care Unit (CCU) Excellence Manual Dr J L Meena
Cardiac Care Unit (CCU) Excellence Manual – Dr J L Meena | Page 17
CHAPTER 3: PROFESSIONAL STANDARDS FOR THE CCU TEAM
Cardiac critical care practice requires an uncommon combination of unblinking continuous vigilance, rapid and
accurate rhythm interpretation, technical mastery of high-alert medication management, and the decisive
composure a sudden cardiac crisis demands. The standards that govern CCU practice derive from cardiac
patient safety science, time-sensitive reperfusion principles, and the unique responsibility of protecting an
organ that fails suddenly and without warning.
1. Professional Appearance
Standards
Attire and Identification
● Wear appropriate clinical attire, PPE, and ID badge as per hospital infection control policy.
Professional Presence
● Maintain a calm, focused, and decisive demeanor, particularly during cardiac arrest or STEMI
activation.
● Model composed, meticulous practice that reflects the exacting standard cardiac critical care requires.
2. Professional Behaviour
Expected Behaviours
Vigilance Discipline
● Never allow continuous rhythm monitoring to lapse, even briefly.
● Respond to every monitor alarm promptly and with genuine clinical assessment, never dismissing an
alarm as “probably artifact” without verification.
Precision Discipline
● Never proceed with a high-alert medication without completing the independent double-check.
● Never estimate a weight- or renal-function-based dose where exact figures are available.
Accountability
● Own every clinical decision, every medication calculation, and every rhythm interpretation made for
patients under CCU care.
● Report and disclose critical incidents and adverse events honestly and promptly.
Collaborative Respect
● Treat every member of the multidisciplinary CCU team — cardiologist, nurse, catheterization
laboratory staff — as an essential, equal safety partner.
Cardiac Care Unit (CCU) Excellence Manual Dr J L Meena
Cardiac Care Unit (CCU) Excellence Manual – Dr J L Meena | Page 18
Patient-Centered Focus
● Every clinical decision is ultimately about the patient's cardiac survival and long-term function — not
merely completing a task.
3. Communication Standards
Communication with Patients and Families
● Communicate diagnosis, prognosis, and treatment urgency honestly and with genuine compassion.
● Explain every intervention and its time-sensitive rationale in clear, non-technical language.
● Support families through the sudden, often unexpected nature of cardiac crisis.
Communication Within the Team
● Communicate rapidly and clearly during cardiac emergencies using closed-loop communication.
● Use structured handover tools (SBAR or equivalent) for every shift change and transfer of care.
● Escalate any deterioration or rhythm change immediately and directly.
Written Communication Standards
● CCU documentation must be accurate, contemporaneous, and complete, reflecting precise timing,
doses, and rhythm findings.
● STEMI protocol timing (door-to-balloon, door-to-needle) must be documented precisely for every
case.
● Medication orders and administration records must be exact and legible.
4. Confidentiality and Information Security
Overview
CCU care involves continuous monitoring data and sensitive cardiac diagnoses, requiring particular
confidentiality discipline throughout admission.
Responsibilities
● Discuss patient information only in appropriate clinical settings and only with those who have a
legitimate need to know.
● Protect access credentials for EMR/HIS and cardiac monitoring systems.
● Apply particular discretion for sensitive prognostic discussions.
5. Ethical Standards
Core Ethical Principles for CCU Practice
Non-Maleficence
● Never allow a known monitoring gap or medication safety lapse to persist unaddressed.
Cardiac Care Unit (CCU) Excellence Manual Dr J L Meena
Cardiac Care Unit (CCU) Excellence Manual – Dr J L Meena | Page 19
● Never proceed with an intervention without genuine informed consent, except in genuine life-
threatening emergency.
Beneficence
● Apply evidence-based care consistently, weighing the benefit and burden of every intervention.
Honesty and Transparency
● Communicate prognosis and uncertainty honestly, including honest disclosure of complications and
errors.
Justice and Equity
● Apply the same rigorous, time-sensitive protocols to every patient, regardless of background or
circumstance.
6. Time Management and Prioritization
Clinical Priority Framework
● Immediate/Emergency: Cardiac arrest, malignant arrhythmia, STEMI activation — immediate
response, no delay.
● Urgent: Significant rhythm change, rising cardiac biomarkers, haemodynamic instability — prompt
assessment and escalation.
● Routine: Scheduled monitoring, medication administration, rehabilitation activities — managed per
defined schedule.
7. Teamwork and Collaboration
Work Effectively With
● Cardiac catheterization laboratory — for seamless STEMI and urgent PCI coordination.
● Cardiac surgery — for coordinated perioperative and post-surgical cardiac care.
● Cardiac pharmacy — for high-alert medication safety verification.
● Cardiac rehabilitation services — for coordinated recovery and secondary prevention.
● Quality department — for incident reporting, RCA, and accreditation support.
8. Professional Competence and Continuous Learning
Areas of Competence
● 12-lead ECG interpretation and rhythm recognition.
● STEMI and acute coronary syndrome management protocols.
● Advanced Cardiac Life Support (ACLS) and defibrillation/cardioversion technique.
● High-alert cardiac medication pharmacology and dosing precision.
● Cardiogenic shock recognition and mechanical circulatory support principles.
Cardiac Care Unit (CCU) Excellence Manual Dr J L Meena
Cardiac Care Unit (CCU) Excellence Manual – Dr J L Meena | Page 20
● FMEA, RCA, and CAPA methodologies for cardiac-specific quality improvement.
Continuous Learning
● Maintain current ACLS certification and equivalent cardiac resuscitation training.
● Maintain current knowledge of evolving cardiac care evidence and guidelines (AHA/ACC, ESC, CSI).
● Engage with national and international cardiology professional bodies.
● Participate regularly in cardiac emergency simulation and rhythm recognition training.
● Participate in NABH and JCI accreditation training for cardiac critical care standards.
Professional Standards Checklist
● Have I maintained continuous rhythm monitoring for every patient today, without lapse?
● Have I completed independent double-check for every high-alert medication administered?
● Have I responded to every monitor alarm with genuine clinical assessment?
● Have I verified defibrillator and emergency equipment readiness today?
● Have I communicated honestly and compassionately with every patient and family?
● Have I reported any incident or safety concern through the appropriate system?
CCU professionalism is unblinking vigilance held to an exacting precision standard — the team that never
lets monitoring lapse, never estimates a dose where an exact figure is required, and never delays
reperfusion is the team every cardiac patient depends upon in the minutes that determine whether heart
muscle survives.
Cardiac Care Unit (CCU) Excellence Manual Dr J L Meena
Cardiac Care Unit (CCU) Excellence Manual – Dr J L Meena | Page 21
CHAPTER 4: PATIENT- AND FAMILY-CENTERED COMMUNICATION IN
THE CCU
Communication in the CCU frequently begins in the middle of a crisis that neither the patient nor their family
anticipated — a chest pain that turned out to be a heart attack, a sudden collapse, a diagnosis of heart failure
that changes a family's understanding of the years ahead. Unlike many other clinical settings, cardiac
communication must often happen at speed, delivering time-sensitive information about a reperfusion
procedure or a defibrillation event within minutes of a patient's arrival, while still preserving the honesty and
compassion any serious diagnosis demands.
Why Communication Quality Matters in the CCU
● A patient facing emergency PCI needs to understand the procedure and provide genuine consent
within a window of minutes, not hours.
● Families arriving to news of a sudden cardiac event often have no context and need clear, honest,
rapidly delivered information.
● Poorly communicated discharge instructions are a leading cause of heart failure readmission.
● Honest communication about prognosis, including the reality of chronic heart disease, allows patients
to engage meaningfully in long-term risk factor modification.
The A-T-C-R-C Communication Model for the CCU
A — Acknowledge
Definition
Acknowledge the sudden, frightening nature of the cardiac event, even within a rapid, time-sensitive
conversation.
Examples
● “I know this happened without any warning — I'm going to explain quickly and clearly what we need
to do right now.”
T — Listen (Elicit Understanding and Concerns Rapidly)
Definition
Listen efficiently but genuinely for the patient's or family's specific concerns, even under time pressure.
C — Clarify (Explain the Time-Sensitive Plan Clearly)
Definition
Explain the diagnosis and the urgency of the treatment plan in clear, non-technical language appropriate to
the time available.
Cardiac Care Unit (CCU) Excellence Manual Dr J L Meena
Cardiac Care Unit (CCU) Excellence Manual – Dr J L Meena | Page 22
Examples
● “Your ECG shows a blockage in an artery to your heart — we need to open it right away, and here's
exactly what that involves.”
R — Respond (Obtain Genuine Consent and Provide Honest Prognosis)
Definition
Respond to questions honestly, obtaining genuine informed consent efficiently, and providing honest
prognosis information as the picture clarifies.
C — Confirm (Verify Understanding)
Definition
Confirm genuine understanding before proceeding with any intervention, even under time pressure, and
confirm understanding of discharge instructions before leaving the unit.
Communicating Risk, Prognosis, and Sudden Cardiac Events
Principles for Time-Sensitive Consent
● Obtain genuine informed consent efficiently for emergency procedures, respecting both urgency and
the patient's right to understand.
● Communicate honestly about procedural risk even within a compressed timeframe.
Delivering News of Sudden Cardiac Death or Poor Prognosis
● Deliver news of death or serious prognosis directly, honestly, and with profound compassion, in as
private a setting as possible.
● Allow genuine space for the family's shock and grief before continuing with further information.
● Involve chaplaincy and social work support promptly.
Communicating for Long-Term Risk Factor Modification
● Communicate the reality of chronic cardiac disease honestly, supporting genuine engagement in
secondary prevention.
● Provide clear, actionable guidance on medication adherence, lifestyle modification, and warning signs
requiring return to care.
Common CCU Communication Mistakes to Avoid
● Rushing through consent for emergency procedures without genuine explanation.
● Failing to provide honest, timely updates to waiting families during procedures.
● Delivering serious prognosis news without adequate structure or compassion, even under time
pressure.
● Providing discharge instructions without confirming genuine patient understanding, contributing to
readmission risk.
Cardiac Care Unit (CCU) Excellence Manual Dr J L Meena
Cardiac Care Unit (CCU) Excellence Manual – Dr J L Meena | Page 23
Communication in the CCU must be both rapid and genuinely honest — the team that explains time-
sensitive procedures clearly, delivers difficult news with compassion despite the crisis, and confirms
genuine understanding at every step protects patients through both the acute crisis and the years of
cardiac health that follow it.
Cardiac Care Unit (CCU) Excellence Manual Dr J L Meena
Cardiac Care Unit (CCU) Excellence Manual – Dr J L Meena | Page 24
CHAPTER 5: PATIENT SAFETY AND CARDIAC CRITICAL CARE STANDARDS
Patient safety in the CCU is defined by speed and precision applied to an organ that fails without warning — a
unit that monitors continuously, reperfuses rapidly, and doses high-alert medications exactly produces
measurably better survival and long-term cardiac function than one relying on delayed or approximate care.
The R-T-A-C-A framework applies with particular intensity to the time-critical, narrow-margin nature of cardiac
critical care.
1. RESPECT
Definition
Treating every patient's cardiac survival chance and every minute of potential delay as equally critical,
regardless of the patient's background or the time of presentation.
How the CCU Demonstrates Respect
● Respect for Every Patient's Survival Chance: Apply the same rigorous, time-sensitive protocols to every
cardiac presentation.
● Respect for the Urgency of Time: Treat every minute of delay to reperfusion as a genuine loss of
irreplaceable heart muscle.
● Equal Service Standards: Apply the same STEMI protocol rigour and clinical care to every patient,
regardless of the hour of presentation.
2. TIMELINESS
Definition
Activating reperfusion protocols, responding to arrhythmias, and escalating deterioration within timeframes
that reflect cardiac time-sensitivity.
Why Timeliness Is a Patient Safety Issue
In no other area of medicine is the relationship between time and irreversible tissue loss as direct as in acute
myocardial infarction. Every minute of delay to reperfusion costs heart muscle that will never regenerate. A
malignant arrhythmia unaddressed for even a minute can be the difference between a successful defibrillation
and a fatal cardiac arrest. Time in the CCU is not a service quality metric — it is frequently the entire
determinant of how much heart muscle, and how much life, is preserved.
CCU Timeliness Standards
● STEMI door-to-balloon time: within international benchmark targets (e.g., ≤ 90 minutes).
● STEMI door-to-needle time (thrombolysis): within international benchmark targets (e.g., ≤ 30
minutes).
● Arrhythmia response: immediate, no delay, from recognition to defibrillation/cardioversion.
Cardiac Care Unit (CCU) Excellence Manual Dr J L Meena
Cardiac Care Unit (CCU) Excellence Manual – Dr J L Meena | Page 25
● Continuous monitoring: uninterrupted for 100% of admitted patients.
3. ACCURACY
Definition
Interpreting every rhythm strip correctly, calculating every high-alert medication dose exactly, and
documenting every clinical detail with the precision cardiac critical care demands.
Why Accuracy Is Non-Negotiable in the CCU
A misread rhythm strip can delay recognition of a life-threatening arrhythmia. An anticoagulation dosing error
can cause catastrophic bleeding or, conversely, fail to prevent a thrombotic event. Accuracy in the CCU,
sustained under the pressure of genuine time-sensitivity, is what separates safe cardiac critical care from one
of medicine's highest-risk environments for preventable harm.
Areas Requiring CCU Accuracy
● Rhythm Interpretation: Every ECG and monitor rhythm must be interpreted correctly and promptly.
● Medication Dosing: Every high-alert cardiac medication dose must be exact and independently double-
checked.
● Anticoagulation Monitoring: Every INR/aPTT result must be acted upon accurately and promptly.
● Documentation: Every CCU record must accurately and completely reflect precise timing, doses, and
clinical findings.
4. COMPASSION
Definition
Recognizing that every patient and family in the CCU is navigating a sudden, often unanticipated crisis, and that
genuine compassion, delivered within the discipline of rapid cardiac response, is itself part of excellent cardiac
care.
How the CCU Demonstrates Compassion
● Provide Genuine Reassurance Despite Time Pressure: Brief, sincere communication matters even
during the most urgent STEMI activation.
● Support Families Through Sudden Crisis: Provide honest, proactive updates during procedures and
following any deterioration.
● Deliver Difficult News with Structure and Care: Sudden cardiac death disclosure deserves the same
compassionate structure as any other setting.
● Support Long-Term Engagement: Approach secondary prevention counselling with genuine
encouragement, not judgment.
Cardiac Care Unit (CCU) Excellence Manual Dr J L Meena
Cardiac Care Unit (CCU) Excellence Manual – Dr J L Meena | Page 26
5. ACCOUNTABILITY
Definition
Taking full professional responsibility for every rhythm interpretation, every medication calculation, and every
timing decision made for patients under CCU care.
CCU Accountability Standards
● Every clinical assessment and medication administration is documented with the responsible team
member's identification.
● Never allow a known monitoring gap or medication safety lapse to go unaddressed.
● Report every critical incident and adverse cardiac event honestly through the quality reporting system.
● Participate in RCA for significant incidents with complete clinical honesty.
● Participate in quality audits and accreditation surveys with accurate, complete cardiac care records.
The R-T-A-C-A Framework in the CCU
Standard Core Focus in the CCU
Respect Every patient's survival chance and every minute of delay treated as critical
Timeliness Door-to-balloon/needle targets; immediate arrhythmia response; continuous monitoring
Accuracy Correct rhythm interpretation, precise medication dosing, complete documentation
Compassion Genuine reassurance despite urgency; structured, compassionate difficult news delivery
Accountability Every decision owned and documented; every incident honestly reviewed
Daily Quality Standards Checklist for the CCU
● Maintain continuous rhythm monitoring without lapse for every patient.
● Apply STEMI protocols immediately upon ECG confirmation.
● Complete independent double-check for every high-alert medication.
● Verify defibrillator and emergency equipment readiness.
● Communicate honestly and compassionately with every patient and family.
● Document every clinical assessment and intervention completely.
● Report any incident or safety concern through the quality reporting system.
In the CCU, patient safety is measured in minutes that cannot be recovered and muscle that cannot
regenerate — a family experiences it as a heart attack caught and treated before permanent damage, an
arrhythmia defibrillated before it became fatal, and a patient who went home to years of life this unit's
vigilance and precision made possible.
Cardiac Care Unit (CCU) Excellence Manual Dr J L Meena
Cardiac Care Unit (CCU) Excellence Manual – Dr J L Meena | Page 27
CHAPTER 6: CONFIDENTIALITY, PRIVACY, AND INFORMATION
SECURITY
The CCU presents a distinctive confidentiality environment: continuous, centrally displayed monitoring data
visible to the entire unit, combined with sensitive cardiac diagnoses and, at times, end-of-life prognostic
discussions that require particular discretion.
1. Privacy in the Continuous Monitoring Environment
Responsibilities
● Use available privacy measures for sensitive conversations and examinations, even within a
continuously monitored environment.
● Never discuss one patient's case within earshot of another patient's bay or visiting family.
● Limit central monitoring station visibility to those with a legitimate clinical role.
2. Confidentiality of Sensitive Cardiac Diagnoses
Overview
Diagnoses carrying significant prognostic weight, including end-stage heart failure or sudden cardiac death risk,
require particular sensitivity in communication and documentation.
Responsibilities
● Handle sensitive prognostic information with heightened confidentiality and discretion.
● Communicate only the clinically necessary information to the wider care team.
3. Clinical Data and EMR/HIS Confidentiality
Responsibilities
● Access only the patient records necessary for current CCU care responsibilities.
● Never discuss a patient's clinical information with anyone outside the legitimate care team.
● Follow hospital IT and cybersecurity policy for all EMR/HIS and cardiac monitoring system access.
● Never leave CCU workstations unlocked or logged in when unattended.
4. Cybersecurity of Cardiac Information Systems
Why Cybersecurity Is a Patient Safety Issue
Cardiac monitoring and information systems provide the continuous, real-time rhythm data upon which safe
CCU care depends. A compromised system risks both sensitive data breach and, if monitoring or medication
data is corrupted, direct patient safety harm through delayed arrhythmia recognition or dosing error.
Cardiac Care Unit (CCU) Excellence Manual Dr J L Meena
Cardiac Care Unit (CCU) Excellence Manual – Dr J L Meena | Page 28
Responsibilities
● Use only authorized, unique login credentials for all EMR/HIS and cardiac monitoring system access.
● Never share login credentials with colleagues, regardless of workload pressure.
● Never connect personal devices to hospital clinical networks without IT authorization.
● Report any suspected unauthorized access or cybersecurity anomaly to IT security immediately.
5. Confidentiality for High-Profile and Vulnerable Patients
Responsibilities
● Maintain the same confidentiality standard for high-profile or notorious patients as for every other
patient.
● Never disclose patient identity, diagnosis, or condition to media or unauthorized persons.
Confidentiality Checklist for the CCU Team
● Use available privacy measures for sensitive conversations within the monitored environment.
● Handle sensitive prognostic diagnoses with heightened discretion.
● Use only authorized credentials for EMR/HIS and monitoring systems.
● Never connect personal devices to hospital clinical networks without IT authorization.
In the CCU, confidentiality must be actively maintained within a continuously monitored, centrally visible
environment, for cardiac diagnoses and prognoses that carry particular emotional and clinical sensitivity.
Cardiac Care Unit (CCU) Excellence Manual Dr J L Meena
Cardiac Care Unit (CCU) Excellence Manual – Dr J L Meena | Page 29
CHAPTER 7: STANDARD OPERATING PROCEDURES (SOPs) FOR THE CCU
Objectives of CCU SOPs
● Ensure consistent, safe, and rapid cardiac critical care for every patient.
● Minimize patient harm through systematic, documented reperfusion, monitoring, and medication
safety protocols.
● Support NABH/JCI accreditation compliance for cardiac critical care standards.
● Provide a defensible clinical and legal framework for incident investigation and quality improvement.
SOP 1: CCU Admission and Continuous Monitoring Setup
Purpose
To ensure systematic admission assessment and immediate continuous monitoring initiation.
Procedure
● Step 1: Conduct Immediate Assessment — conduct 12-lead ECG and initial cardiac assessment
immediately upon arrival.
● Step 2: Initiate Continuous Monitoring — initiate continuous cardiac monitoring without delay.
● Step 3: Obtain Baseline Biomarkers — obtain cardiac biomarkers and relevant laboratory studies.
● Step 4: Apply Risk Stratification — apply validated cardiac risk stratification criteria.
● Step 5: Document — document the complete admission assessment.
Quality Standards
● 100% of admissions include continuous monitoring initiated within the institutionally defined
timeframe.
SOP 2: STEMI Protocol and Door-to-Balloon Time
Purpose
To minimize door-to-balloon time for eligible STEMI patients.
Procedure
● Step 1: Obtain Immediate ECG — obtain and interpret ECG within the institutionally defined timeframe
of arrival.
● Step 2: Activate STEMI Protocol — activate the cardiac catheterization team immediately upon STEMI
recognition.
● Step 3: Administer Initial Therapy — administer evidence-based initial pharmacological therapy per
protocol.
Cardiac Care Unit (CCU) Excellence Manual Dr J L Meena
Cardiac Care Unit (CCU) Excellence Manual – Dr J L Meena | Page 30
● Step 4: Coordinate Rapid Transfer — coordinate rapid transfer to the catheterization laboratory.
● Step 5: Document — document the complete timeline from arrival to intervention.
Quality Standards
● Door-to-balloon time maintained within international benchmark target (e.g., ≤ 90 minutes) for 100%
of eligible patients.
SOP 3: Thrombolysis and Door-to-Needle Time
Purpose
To minimize door-to-needle time where primary PCI is not immediately available.
Procedure
● Step 1: Confirm Eligibility — confirm thrombolysis eligibility and absence of contraindications.
● Step 2: Administer Thrombolytic — administer thrombolytic therapy within the evidence-based time
window.
● Step 3: Monitor for Complications — monitor closely for bleeding and reperfusion arrhythmia.
● Step 4: Coordinate Transfer — coordinate transfer for PCI as clinically indicated.
● Step 5: Document — document the complete timeline and monitoring.
Quality Standards
● Door-to-needle time maintained within international benchmark target (e.g., ≤ 30 minutes) for 100%
of eligible patients.
SOP 4: Malignant Arrhythmia Recognition and Response
Purpose
To ensure immediate recognition and treatment of life-threatening arrhythmias.
Procedure
● Step 1: Recognize the Arrhythmia — recognize malignant arrhythmia on continuous monitoring
immediately.
● Step 2: Assess the Patient — assess haemodynamic status and level of consciousness rapidly.
● Step 3: Apply ACLS Protocol — apply Advanced Cardiac Life Support protocol systematically.
● Step 4: Document — document the complete arrhythmia event and response.
Quality Standards
● 100% of malignant arrhythmia events include documented immediate recognition and protocol-driven
response.
Cardiac Care Unit (CCU) Excellence Manual Dr J L Meena
Cardiac Care Unit (CCU) Excellence Manual – Dr J L Meena | Page 31
SOP 5: Defibrillation and Synchronized Cardioversion
Purpose
To ensure safe, effective, immediate defibrillation or cardioversion when indicated.
Procedure
● Step 1: Confirm Indication — confirm the rhythm indication for defibrillation or synchronized
cardioversion.
● Step 2: Prepare Equipment — verify defibrillator readiness and appropriate energy setting.
● Step 3: Deliver Therapy — deliver defibrillation or cardioversion per protocol with appropriate safety
precautions.
● Step 4: Reassess — reassess rhythm and haemodynamic status immediately following.
● Step 5: Document — document the complete procedure and outcome.
Quality Standards
● Defibrillator readiness verified per defined schedule at every bedside/accessible location.
SOP 6: Anticoagulation and Bleeding Risk Management
Purpose
To ensure safe, precise anticoagulation management balancing thrombotic and bleeding risk.
Procedure
● Step 1: Assess Bleeding Risk — apply structured bleeding risk assessment before initiating
anticoagulation.
● Step 2: Calculate Dose — calculate weight- and renal-function-based dose per standardized protocol.
● Step 3: Complete Independent Double-Check — complete independent double-check before
administration.
● Step 4: Monitor Parameters — monitor INR/aPTT per defined schedule and adjust dosing accordingly.
● Step 5: Document — document the complete anticoagulation management course.
Quality Standards
● 100% of anticoagulation orders include documented independent double-check.
SOP 7: Cardiogenic Shock and Mechanical Circulatory Support
Purpose
To ensure prompt recognition and evidence-based management of cardiogenic shock.
Procedure
● Step 1: Recognize Shock — apply systematic haemodynamic assessment to recognize cardiogenic
shock.
Cardiac Care Unit (CCU) Excellence Manual Dr J L Meena
Cardiac Care Unit (CCU) Excellence Manual – Dr J L Meena | Page 32
● Step 2: Initiate Pharmacological Support — initiate inotrope/vasopressor support per protocol.
● Step 3: Assess for Mechanical Support — assess eligibility for IABP or ECMO for refractory cases.
● Step 4: Coordinate Escalation — coordinate cardiac surgery/interventional cardiology consultation as
indicated.
● Step 5: Document — document the complete shock recognition and management course.
Quality Standards
● 100% of cardiogenic shock cases include documented systematic haemodynamic assessment.
SOP 8: Post-Catheterization Access Site Monitoring
Purpose
To detect and manage post-catheterization vascular complications promptly.
Procedure
● Step 1: Assess Access Site — assess the access site systematically per defined schedule.
● Step 2: Monitor for Complications — monitor for bleeding, haematoma, or vascular compromise.
● Step 3: Apply Immediate Intervention — apply direct pressure or escalate immediately upon
identifying complication.
● Step 4: Document — document access site assessment and any intervention.
Quality Standards
● Access site assessment documented per defined schedule for 100% of post-catheterization patients.
SOP 9: Heart Failure Decompensation Management
Purpose
To apply evidence-based management of acute heart failure decompensation.
Procedure
● Step 1: Assess Volume Status — assess volume status and haemodynamic parameters systematically.
● Step 2: Apply Decongestion Therapy — apply evidence-based diuretic and haemodynamic
optimization therapy.
● Step 3: Monitor Response — monitor fluid balance, renal function, and clinical response.
● Step 4: Optimize Medical Therapy — optimize guideline-directed medical therapy before discharge.
● Step 5: Document — document the complete management course.
Quality Standards
● 100% of heart failure decompensation cases include documented systematic volume assessment.
Cardiac Care Unit (CCU) Excellence Manual Dr J L Meena
Cardiac Care Unit (CCU) Excellence Manual – Dr J L Meena | Page 33
SOP 10: Cardiac Rehabilitation Initiation and Discharge Planning
Purpose
To ensure structured transition supporting long-term cardiac health and readmission prevention.
Procedure
● Step 1: Assess Rehabilitation Eligibility — assess eligibility for cardiac rehabilitation referral.
● Step 2: Initiate Early Mobilization — initiate appropriate early mobilization per protocol.
● Step 3: Provide Discharge Education — provide comprehensive education on medication, risk factor
modification, and warning signs.
● Step 4: Coordinate Follow-Up — coordinate structured follow-up and rehabilitation referral.
● Step 5: Document — document the complete discharge planning process.
Quality Standards
● 100% of eligible discharges include documented cardiac rehabilitation referral and structured
education.
CCU SOP Daily Compliance Checklist
● Continuous monitoring verified without lapse for every patient today.
● Any STEMI activation today meets door-to-balloon/needle timing targets.
● Every high-alert medication administered with documented double-check.
● Defibrillator and emergency equipment readiness verified.
● Any incident or safety concern reported through the appropriate system.
SOPs in the CCU are the operating instructions for protecting an organ that fails without warning. When
followed consistently, they are the systematic foundation of rapid reperfusion, continuous vigilance, and
medication precision for every cardiac patient in the unit.
Cardiac Care Unit (CCU) Excellence Manual Dr J L Meena
Cardiac Care Unit (CCU) Excellence Manual – Dr J L Meena | Page 34
CHAPTER 8: COMMUNICATION WITH SPECIAL GROUPS
The CCU team communicates across a range of high-stakes, often time-compressed circumstances — from a
patient requiring emergency consent for PCI within minutes, to a family suddenly facing the possibility of
sudden cardiac death, to the cardiac catheterization laboratory coordinating a seamless STEMI activation, to a
patient navigating the long-term reality of chronic heart disease. Excellent CCU practice requires adapted
communication for each of these circumstances.
1. Patients Requiring Emergency Procedural Consent
Communication Guidelines
● Obtain genuine informed consent efficiently, respecting both time-sensitivity and the patient's right
to understand.
● Explain risk, benefit, and urgency clearly, even within a compressed timeframe.
2. Families Facing Sudden Cardiac Crisis
Communication Guidelines
● Provide honest, timely updates during procedures, acknowledging genuine uncertainty where it exists.
● Prepare families realistically for what a cardiac arrest or resuscitation event may involve, per
institutional policy.
3. Cardiac Catheterization Laboratory Teams
Communication Guidelines
● Communicate STEMI activation and relevant clinical findings clearly and immediately.
● Coordinate seamless handover for rapid catheterization laboratory transfer.
4. Cardiac Surgery Teams
Communication Guidelines
● Communicate haemodynamic status and surgical urgency clearly for patients requiring emergency
cardiac surgery.
● Coordinate post-surgical handover with structured, complete clinical information.
5. Patients with Chronic Heart Failure
Overview
Patients with chronic heart failure often navigate a long-term relationship with cardiac care, requiring genuine
partnership rather than episodic instruction.
Cardiac Care Unit (CCU) Excellence Manual Dr J L Meena
Cardiac Care Unit (CCU) Excellence Manual – Dr J L Meena | Page 35
Communication Guidelines
● Communicate the chronic nature of the condition honestly, supporting genuine engagement in
ongoing self-management.
● Provide consistent, actionable guidance on medication adherence and symptom monitoring.
6. Families Facing End-of-Life Decisions
Overview
Some CCU families face profound end-of-life decisions for a patient with irreversible cardiac failure, requiring
the deepest compassion and clearest honesty healthcare can offer.
Communication Guidelines
● Involve palliative care, chaplaincy, and ethics consultation as appropriate.
● Communicate prognosis honestly while supporting the family's values and wishes.
7. Cardiac Rehabilitation and Follow-Up Services
Communication Guidelines
● Provide complete, structured discharge summaries supporting continuity of rehabilitation and follow-
up care.
● Coordinate directly with rehabilitation services for patients with identified adherence or risk factor
challenges.
8. Hospital Administration and Quality/Accreditation Bodies
Communication Guidelines
● Present door-to-balloon compliance, medication safety, and outcome data in management-accessible
formats.
● Advocate for necessary resources (staffing, equipment, catheterization laboratory capacity) with clear
patient safety justification.
Universal CCU Communication Principles
● Communicate honestly and efficiently, recognizing that speed and compassion are not in tension.
● Respond to every deterioration and every family's genuine concern with appropriate urgency.
● Always confirm genuine understanding, particularly for time-sensitive consent and discharge
instructions.
● Document every significant clinical communication completely.
Cardiac Care Unit (CCU) Excellence Manual Dr J L Meena
Cardiac Care Unit (CCU) Excellence Manual – Dr J L Meena | Page 36
The CCU team that communicates with equal skill toward a patient needing emergency consent within
minutes and a family navigating the long-term reality of chronic heart disease serves every stakeholder at
maximum impact — rapid clinical excellence delivered alongside the genuine compassion that cardiac care,
at every stage, demands
Cardiac Care Unit (CCU) Excellence Manual Dr J L Meena
Cardiac Care Unit (CCU) Excellence Manual – Dr J L Meena | Page 37
CHAPTER 9: HANDLING DIFFICULT SITUATIONS
Common Difficult Situations for the CCU Team
● Two or more simultaneous cardiac emergencies exceed immediate team capacity.
● A monitor alarm is initially dismissed as artifact but represents genuine deterioration.
● A patient or family declines a time-sensitive emergency procedure.
● An anticoagulation dosing calculation is questioned or a near-miss is identified.
● Cardiac catheterization laboratory capacity is delayed during a STEMI activation.
● A cardiac arrest occurs despite continuous monitoring.
● A family requests to be present during resuscitation.
● Genuine end-of-life discussion becomes necessary for irreversible cardiac failure.
● A colleague's clinical judgment or fitness for duty raises concern.
● A patient with chronic heart failure is readmitted despite apparently adequate discharge planning.
Core Principles for Handling Difficult Situations
1. Cardiac Time-Sensitivity Is Paramount
In every difficult situation, the time-critical nature of cardiac injury drives every decision — continuous
monitoring and reperfusion protocols must never be delayed for administrative or interpersonal convenience.
2. Apply Standardized Protocols Under Pressure
Cardiac emergencies are precisely when standardized protocols matter most — resist the temptation to
improvise when a proven protocol exists.
3. Escalate Immediately and Persistently
A genuine safety concern is not resolved until it reaches someone who can act on it — escalate through
alternative channels if the first attempt does not produce a response.
4. Document Everything
Every difficult clinical situation must be contemporaneously documented — what was found, what was
communicated, what decisions were made, and by whom.
Handling Simultaneous Cardiac Emergencies
Steps
● Apply triage-based prioritization based on genuine severity and immediacy of life threat.
● Mobilize additional team members and resources per institutional surge protocol.
● Coordinate with the catheterization laboratory and cardiac surgery for capacity support.
Cardiac Care Unit (CCU) Excellence Manual Dr J L Meena
Cardiac Care Unit (CCU) Excellence Manual – Dr J L Meena | Page 38
Handling a Dismissed Alarm Representing Genuine Deterioration
Steps
● Reassess the patient immediately upon recognizing the error.
● Apply appropriate emergency response without delay.
● Report the incident honestly through the quality system and participate in RCA to prevent recurrence.
Handling a Patient Declining a Time-Sensitive Procedure
Steps
● Explain the clinical rationale and risk of declining clearly and without coercion.
● Ensure genuine understanding through teach-back or equivalent confirmation.
● Respect the patient's informed decision while continuing to offer support and monitoring.
● Document the discussion and decision-making process thoroughly.
Handling a Medication Dosing Concern or Near-Miss
Steps
● Stop and verify the calculation immediately before proceeding.
● Escalate to a second qualified team member for independent verification.
● Report the near-miss honestly through the quality reporting system, regardless of whether harm
occurred.
Handling Delayed Catheterization Laboratory Capacity During STEMI
Steps
● Escalate immediately to institutional leadership and coordinate alternative pathways (thrombolysis,
transfer).
● Communicate transparently with the patient and family about the delay and alternative plan.
● Conduct thorough review following the event to strengthen future capacity coordination.
Handling a Cardiac Arrest Despite Continuous Monitoring
Steps
● Initiate immediate ACLS response per protocol.
● Communicate honestly with the family once immediate resuscitation allows.
● Conduct thorough review following stabilization, regardless of outcome.
Cardiac Care Unit (CCU) Excellence Manual Dr J L Meena
Cardiac Care Unit (CCU) Excellence Manual – Dr J L Meena | Page 39
Handling a Family Request for Presence During Resuscitation
Steps
● Support family presence per institutional policy, with a dedicated support person assigned.
● Prepare the family honestly for what they may see, wherever time allows.
Handling End-of-Life Discussion for Irreversible Cardiac Failure
Steps
● Involve palliative care, chaplaincy, and ethics consultation as appropriate.
● Communicate prognosis honestly while supporting the family's values and wishes.
Handling Concern About a Colleague's Fitness for Duty
Steps
● Address any immediate patient safety concern directly and without delay.
● Escalate to department leadership immediately if the concern involves impairment or an immediate
safety risk.
Handling Readmission Despite Apparent Adequate Discharge Planning
Steps
● Review the discharge process honestly to identify any genuine gap.
● Engage the patient and family to understand barriers to adherence or self-management.
● Use the readmission as a genuine improvement opportunity for discharge planning protocols.
The CALM Model for the CCU
● C – Control the immediate cardiac risk.
● A – Acknowledge the clinical and emotional reality accurately.
● L – Lead with evidence — STEMI protocols, ACLS algorithms, and medication safety criteria.
● M – Manage through documented escalation channels when needed.
Difficult situations in the CCU are always, ultimately, tests of whether standardized, time-sensitive protocol
holds firm under the pressure of a heart that fails without warning. The team that never delays reperfusion,
never dismisses a genuine warning sign, and escalates persistently until genuine safety is restored is
fulfilling the highest professional obligation of cardiac critical care.
Cardiac Care Unit (CCU) Excellence Manual Dr J L Meena
Cardiac Care Unit (CCU) Excellence Manual – Dr J L Meena | Page 40
CHAPTER 10: EMERGENCY RESPONSE — CRITICAL CARDIAC
PRESENTATIONS
Overview
Certain presentations demand the CCU team's most immediate, standardized, and rehearsed response —
scenarios where the difference between a coordinated, protocol-driven response and an improvised one is
measured directly in heart muscle preserved and lives saved.
Critical Presentations Requiring Immediate Response
● Cardiac arrest (VF/pulseless VT/asystole/PEA).
● STEMI.
● Cardiogenic shock.
● Malignant arrhythmia with haemodynamic compromise.
● Acute pulmonary oedema.
● Cardiac tamponade.
● Massive pulmonary embolism.
● Aortic dissection.
● Post-catheterization access site haemorrhage.
● Bradyarrhythmia requiring emergency pacing.
1. Cardiac Arrest
Immediate Response
● Initiate high-quality CPR immediately per current ACLS guidelines.
● Apply immediate defibrillation for shockable rhythms (VF/pulseless VT).
● Systematically identify and treat reversible causes.
2. STEMI
Steps
● Activate the STEMI protocol immediately upon ECG confirmation.
● Coordinate rapid catheterization laboratory activation and transfer.
● Administer evidence-based initial pharmacological therapy per protocol.
Cardiac Care Unit (CCU) Excellence Manual Dr J L Meena
Cardiac Care Unit (CCU) Excellence Manual – Dr J L Meena | Page 41
3. Cardiogenic Shock
Steps
● Apply systematic haemodynamic assessment immediately.
● Initiate pharmacological support and assess for mechanical circulatory support eligibility.
● Coordinate emergency cardiology/cardiac surgery consultation.
4. Malignant Arrhythmia with Haemodynamic Compromise
Steps
● Apply immediate synchronized cardioversion or defibrillation per rhythm and stability.
● Administer antiarrhythmic therapy per protocol as indicated.
5. Acute Pulmonary Oedema
Steps
● Apply immediate respiratory support and positioning.
● Administer diuretic and vasodilator therapy per protocol.
● Escalate to non-invasive or invasive ventilation as indicated.
6. Cardiac Tamponade
Steps
● Recognize clinical signs (Beck's triad, echocardiographic confirmation) promptly.
● Perform emergency pericardiocentesis as clinically indicated.
● Coordinate immediate cardiothoracic surgical consultation.
7. Massive Pulmonary Embolism
Steps
● Recognize haemodynamic instability with suspected massive PE promptly.
● Initiate thrombolysis or coordinate emergency embolectomy per protocol and eligibility.
● Support haemodynamic status throughout.
8. Aortic Dissection
Steps
● Recognize clinical signs (tearing chest/back pain, pulse/blood pressure differential) promptly.
● Apply immediate blood pressure and heart rate control per protocol.
● Coordinate emergency imaging and cardiothoracic surgical consultation.
Cardiac Care Unit (CCU) Excellence Manual Dr J L Meena
Cardiac Care Unit (CCU) Excellence Manual – Dr J L Meena | Page 42
9. Post-Catheterization Access Site Haemorrhage
Steps
● Apply immediate direct pressure to the access site.
● Assess haemodynamic status and escalate for vascular or surgical intervention as needed.
● Coordinate blood product support if significant blood loss occurs.
10. Bradyarrhythmia Requiring Emergency Pacing
Steps
● Apply pharmacological therapy (atropine or equivalent) per protocol as first-line.
● Initiate transcutaneous pacing immediately if pharmacological therapy is insufficient.
● Coordinate urgent transvenous pacing placement as indicated.
Emergency Response: Key Performance Targets
Emergency Scenario Maximum Response Time Key Action
Cardiac Arrest Immediate High-quality CPR; immediate
defibrillation for shockable rhythm
STEMI Within evidence-based window Activate cath lab; door-to-balloon
target
Cardiogenic Shock Immediate Haemodynamic assessment;
pharmacological/mechanical
support
Cardiac Tamponade Immediate Emergency pericardiocentesis
Massive PE Immediate Thrombolysis or emergency
embolectomy per eligibility
Emergency Preparedness Checklist for the CCU
● Defibrillator, emergency medications, and airway equipment verified and accessible at all times.
● STEMI protocol activation pathway tested and functional with the catheterization laboratory.
● Regular participation in cardiac arrest and emergency simulation training.
Emergency preparedness in the CCU is not a policy statement — it is the immediate, standardized,
rehearsed response that determines survival in the minutes before definitive treatment can begin. The
team that has practiced these critical presentations until the response is automatic protects patients in the
moments when there is no time to think, only to act correctly.
Cardiac Care Unit (CCU) Excellence Manual Dr J L Meena
Cardiac Care Unit (CCU) Excellence Manual – Dr J L Meena | Page 43
CHAPTER 11: DIGITAL COMPETENCY FOR THE CCU TEAM
Objectives
● Enable the CCU team to use cardiac monitoring, dosing, and clinical information systems accurately,
securely, and efficiently.
● Leverage technology to improve rhythm recognition, medication safety, and coordinated STEMI
response.
● Manage the cybersecurity of cardiac information systems as a core patient safety function.
Core Digital Competencies for the CCU Team
1. Continuous Cardiac Monitoring Systems
Essential Skills
● Configure and interpret continuous ECG monitoring, alarm parameters, and haemodynamic
monitoring accurately.
● Recognize and respond to system-generated arrhythmia alerts promptly, applying independent clinical
judgment.
2. STEMI Activation and Catheterization Laboratory Coordination Systems
Essential Skills
● Use automated STEMI activation and notification systems effectively.
● Track door-to-balloon/needle timing metrics through institutional systems.
3. Electronic Prescribing and Anticoagulation Dosing Systems
Essential Skills
● Use electronic weight- and renal-function-based dosing calculators and verify outputs independently.
● Apply barcode or equivalent verification systems for high-alert medication administration where
available.
4. Electronic Medical Record (EMR) / Hospital Information System (HIS)
Essential Skills
● Document clinical assessment, timing, and medication administration accurately and in real time.
5. AI-Assisted Arrhythmia Detection
Awareness
● AI and computerized ECG interpretation tools are increasingly applied to arrhythmia detection and risk
stratification.
Cardiac Care Unit (CCU) Excellence Manual Dr J L Meena
Cardiac Care Unit (CCU) Excellence Manual – Dr J L Meena | Page 44
● Understand and appropriately leverage these tools while maintaining independent clinical judgment
— AI tools are decision-support, not a substitute for continuous bedside vigilance.
6. Telemedicine for Remote Cardiology Consultation
Essential Skills
● Use telemedicine platforms for remote cardiology consultation where applicable, particularly for
referring facilities.
7. Cybersecurity and Information Security
Personal Digital Security Responsibilities
● Use unique, strong credentials for all EMR/HIS and cardiac monitoring system logins.
● Lock or log out of workstations whenever stepping away, even briefly.
● Never connect personal devices to hospital clinical networks.
● Report all cybersecurity anomalies to IT security immediately.
Digital Competency Checklist
● Navigate cardiac monitoring, dosing calculation, and EMR/HIS systems for all core functions without
assistance.
● Use STEMI activation and timing tracking systems effectively.
● Apply basic cybersecurity practices to all clinical system access.
● Know the downtime procedure for monitoring/EMR system failure.
Digital competency for the CCU team is the ability to integrate rapid, precise clinical judgment with the
monitoring, dosing, and predictive systems that modern cardiac critical care increasingly depends upon —
using technology to extend, never replace, the continuous vigilance that defines safe cardiac care.
Cardiac Care Unit (CCU) Excellence Manual Dr J L Meena
Cardiac Care Unit (CCU) Excellence Manual – Dr J L Meena | Page 45
CHAPTER 12: DAILY CCU CHECKLIST
Objectives
● Provide a structured daily framework for safe, rapid, and vigilant cardiac critical care.
● Ensure every monitoring, reperfusion, and medication safety obligation is addressed every shift.
● Support accurate clinical documentation and departmental performance data quality.
PART A: START-OF-SHIFT CHECKLIST
Personal and Professional Readiness
● Appropriate clinical attire, PPE, and ID badge displayed.
● EMR/HIS and cardiac monitoring systems functional and accessible.
Handover and Readiness Review
● Reviewed structured handover from previous shift, including any unstable patients.
● Verified defibrillator, emergency medications, and airway equipment are stocked and functional.
● Verified STEMI activation pathway and catheterization laboratory contact information current.
PART B: MONITORING CHECKLIST
● Continuous cardiac monitoring verified functional and without lapse for every patient.
● Alarm parameters verified appropriate for each patient's clinical status.
PART C: REPERFUSION AND ARRHYTHMIA CHECKLIST
● Any STEMI activation today meets door-to-balloon/needle timing targets.
● Any arrhythmia event today documented with immediate response timeline.
PART D: MEDICATION SAFETY CHECKLIST
● Every high-alert medication administered with documented independent double-check.
● Anticoagulation parameters (INR/aPTT) reviewed and dosing adjusted per protocol.
PART E: POST-PROCEDURAL CHECKLIST
● Post-catheterization access sites assessed per defined schedule.
● Post-cardiac-surgery haemodynamic and rhythm monitoring maintained.
PART F: REHABILITATION AND DISCHARGE CHECKLIST
● Cardiac rehabilitation assessment initiated for eligible patients.
Cardiac Care Unit (CCU) Excellence Manual Dr J L Meena
Cardiac Care Unit (CCU) Excellence Manual – Dr J L Meena | Page 46
● Discharge education and follow-up coordination completed for patients approaching discharge.
PART G: SAFETY AND INCIDENT CHECKLIST
● Any incident, near-miss, or medication concern reported through the appropriate system.
● CAPA actions from previous incidents reviewed for completion.
PART H: END-OF-SHIFT CHECKLIST
● All clinical records updated and complete for the shift.
● Structured handover prepared for the incoming shift.
● Clinical systems securely logged out.
Daily Self-Assessment for the CCU Team
● Did we maintain continuous rhythm monitoring for every patient today?
● Did we activate STEMI protocols immediately upon ECG confirmation?
● Did we complete independent double-check for every high-alert medication?
● Did we verify defibrillator and emergency equipment readiness?
● Did we communicate honestly and compassionately with every patient and family?
A consistent, structured daily routine — from start-of-shift equipment verification to end-of-shift handover
— transforms individual clinical vigilance into a systemic cardiac safety programme that operates reliably
across every shift, every rhythm, and every patient whose heart depends on this unit's readiness.
Cardiac Care Unit (CCU) Excellence Manual Dr J L Meena
Cardiac Care Unit (CCU) Excellence Manual – Dr J L Meena | Page 47
CHAPTER 13: KEY PERFORMANCE INDICATORS (KPIs) FOR THE CCU
Objectives
● Measure reperfusion timeliness, medication safety, and cardiac outcome performance objectively.
● Enable data-driven continuous improvement in CCU practice.
● Support NABH/JCI accreditation standards for cardiac critical care.
● Demonstrate the value and patient safety impact of the CCU to institutional leadership.
Categories of CCU KPIs
1. Reperfusion and Timeliness KPIs
KPI Definition Target
Door-to-Balloon Time (STEMI) Median time from arrival to PCI for eligible patients ≤ 90 minutes (or
institutional/international
benchmark)
Door-to-Needle Time
(Thrombolysis)
Median time from arrival to thrombolytic
administration
≤ 30 minutes (or
institutional/international
benchmark)
ECG-to-Diagnosis Time Time from ECG acquisition to STEMI recognition Minimize; track against
benchmark
2. Monitoring and Arrhythmia KPIs
KPI Definition Target
Continuous Monitoring Compliance % of patient-hours with uninterrupted cardiac
monitoring
100%
Cardiac Arrest Survival to ROSC % of in-CCU cardiac arrests achieving return of
spontaneous circulation
Track and trend
against benchmark
Defibrillator Readiness Compliance % of scheduled defibrillator checks completed 100%
3. Medication Safety KPIs
KPI Definition Target
High-Alert Medication Double-Check
Compliance
% of high-alert doses with documented independent
double-check
100%
Anticoagulation Adverse Event Rate Rate of bleeding or thrombotic events related to
anticoagulation
Minimize; track and
trend
Medication Error Rate Number of medication errors per patient-days Minimize toward
zero
Cardiac Care Unit (CCU) Excellence Manual Dr J L Meena
Cardiac Care Unit (CCU) Excellence Manual – Dr J L Meena | Page 48
4. Post-Procedural and Complication KPIs
KPI Definition Target
Post-Catheterization Vascular
Complication Rate
% of catheterizations with access site complication At or below
institutional/national
benchmark
Heart Failure 30-Day Readmission Rate % of heart failure patients readmitted within 30 days At or below
institutional/national
benchmark
5. Outcome and Governance KPIs
KPI Definition Target
Risk-Adjusted Mortality Rate Observed vs. expected mortality using standardized
cardiac severity scoring
Observed ≤
expected; track and
trend
RCA Completion Rate % of significant adverse events with completed RCA 100%
Cardiac Rehabilitation Referral Rate % of eligible patients referred to cardiac rehabilitation Track and maximize
Using KPIs for Continuous Improvement
● Review all CCU KPIs regularly at departmental quality and governance meetings.
● Analyse door-to-balloon/needle and arrhythmia response trends to identify targeted process
improvements.
● Use risk-adjusted outcome data to benchmark performance against national/international standards.
● Present KPI data to hospital management to demonstrate the patient safety impact of CCU excellence.
CCU KPIs translate rapid, vigilant cardiac care into institutional accountability — demonstrating that the
investment in reperfusion timeliness, continuous monitoring, and medication safety is a measurable,
trackable, life-saving patient safety programme for the heart's most fragile and fastest-moving hours.
Cardiac Care Unit (CCU) Excellence Manual Dr J L Meena
Cardiac Care Unit (CCU) Excellence Manual – Dr J L Meena | Page 49
CHAPTER 14: TOP 20 DO'S & TOP 20 DON'TS FOR THE CCU
Introduction
The CCU team protects an organ that fails suddenly and without warning, where every minute of delay costs
heart muscle that will never regenerate. Their daily professional decisions — about vigilance, precision, and
time-sensitive response — determine whether every cardiac patient in the unit receives the exacting standard
of care their heart's fragility demands. These Do's and Don'ts provide the practical daily architecture of CCU
excellence.
TOP 20 DO'S FOR THE CCU
● 1. Maintain Continuous Rhythm Monitoring Without Lapse — Every patient, every minute.
● 2. Activate STEMI Protocols Immediately Upon ECG Confirmation — Time is muscle, and muscle does
not wait.
● 3. Respond to Every Monitor Alarm with Genuine Assessment — Never dismiss as artifact without
verification.
● 4. Complete Independent Double-Check for Every High-Alert Medication — No exceptions, regardless
of time pressure.
● 5. Verify Defibrillator Readiness Every Shift — Readiness must be proven, not assumed.
● 6. Apply ACLS Protocols Systematically — Every cardiac arrest, every time, without deviation.
● 7. Monitor Anticoagulation Parameters Rigorously — INR/aPTT tracked and acted upon promptly.
● 8. Apply Structured Bleeding Risk Assessment — Alongside every anticoagulation decision.
● 9. Recognize Cardiogenic Shock Early — Before circulatory collapse becomes irreversible.
● 10. Monitor Post-Catheterization Access Sites Systematically — Per defined schedule, every time.
● 11. Obtain Genuine, Efficient Consent for Emergency Procedures — Speed and honesty are not in
tension.
● 12. Communicate Honestly During Sudden Cardiac Crisis — Even amid the intensity of an emergency.
● 13. Deliver Difficult News with Structure and Compassion — Sudden cardiac death disclosure deserves
full care.
● 14. Debrief After Every Cardiac Arrest — Consolidate learning while it is fresh.
● 15. Coordinate Seamlessly with the Catheterization Laboratory — Every STEMI activation, every time.
● 16. Initiate Cardiac Rehabilitation Early — Extending protection beyond the acute crisis.
● 17. Provide Structured Discharge Education — To prevent heart failure readmission.
● 18. Report Every Near-Miss Honestly — Including your own, especially in medication safety.
● 19. Provide Structured Handover for Every Transfer — SBAR or equivalent, every time.
Cardiac Care Unit (CCU) Excellence Manual Dr J L Meena
Cardiac Care Unit (CCU) Excellence Manual – Dr J L Meena | Page 50
● 20. Continue Learning — Cardiac care evidence evolves rapidly. The team that does not learn
continuously treats today's hearts with yesterday's protocols.
TOP 20 DON'TS FOR THE CCU
● 1. Don't Allow Rhythm Monitoring to Lapse — Even briefly, even during a busy shift.
● 2. Don't Delay STEMI Activation for Any Non-Clinical Reason — Minutes cost muscle that never returns.
● 3. Don't Dismiss a Monitor Alarm Without Verification — The one time it's genuine is the time that
matters.
● 4. Don't Skip Independent Double-Check for High-Alert Medications — This is a non-negotiable safety
boundary.
● 5. Don't Assume Defibrillator Readiness — Verify it, every shift, without exception.
● 6. Don't Improvise During Cardiac Arrest — Apply the standardized ACLS algorithm.
● 7. Don't Neglect Anticoagulation Monitoring — Bleeding and thrombotic risk both demand vigilance.
● 8. Don't Anticoagulate Without Bleeding Risk Assessment — Both risks must be weighed together.
● 9. Don't Mistake Compensation for Stability in Cardiogenic Shock — Early recognition saves lives.
● 10. Don't Skip Scheduled Access Site Assessment — Vascular complications can progress silently.
● 11. Don't Rush Consent Without Genuine Explanation — Even under time pressure, patients deserve
understanding.
● 12. Don't Provide Inconsistent Updates to Waiting Families — Coordinate messaging across the team.
● 13. Don't Deliver Difficult News Without Structure or Privacy — Even amid the intensity of an
emergency.
● 14. Don't Skip Team Debriefing After a Cardiac Arrest — Unprocessed events repeat their gaps.
● 15. Don't Delay Catheterization Laboratory Coordination — Seamless handoff protects reperfusion
time.
● 16. Don't Delay Cardiac Rehabilitation Referral — Early engagement improves long-term outcomes.
● 17. Don't Discharge Without Confirming Genuine Understanding — This is a leading cause of
preventable readmission.
● 18. Don't Hide or Minimize a Near-Miss — Suppressed incidents cannot drive the improvement that
prevents recurrence.
● 19. Don't Hand Over Complex Patients Informally — Structure protects against critical omissions.
● 20. Don't Practice Outside Current Cardiac Care Evidence — Personal habit or outdated method must
never override current best practice.
CCU Golden Rules
● Monitor continuously, without lapse — seconds matter in cardiac deterioration.
● Activate STEMI protocols immediately — time is muscle, and muscle does not wait.
Cardiac Care Unit (CCU) Excellence Manual Dr J L Meena
Cardiac Care Unit (CCU) Excellence Manual – Dr J L Meena | Page 51
● Verify every alarm genuinely — never dismiss without checking.
● Double-check every high-alert medication — no exceptions, ever.
● Keep the defibrillator ready — verified, not assumed.
● Apply ACLS systematically — every arrest, every time.
● Watch anticoagulation closely — both bleeding and clotting risk matter.
● Recognize shock early — before collapse becomes irreversible.
● Report every near-miss — honestly, including your own.
● Never stop learning — today's cardiac evidence is not yesterday's.
Daily Commitment Statement
“Today, I will maintain continuous rhythm monitoring, activate every time-sensitive protocol without delay,
complete independent double-check for every high-alert medication, verify emergency equipment readiness,
communicate honestly with every patient and family, and uphold every safety standard without exception —
because every heartbeat on the monitor depends on my complete vigilance.”
The Top 20 Do's and Top 20 Don'ts are the daily professional architecture of CCU excellence — each shaped
by the understanding that cardiac critical care is patient safety management practiced at the intersection
of maximum speed and maximum vigilance, and that there are no minor lapses when heart muscle, once
lost, does not return.
Cardiac Care Unit (CCU) Excellence Manual Dr J L Meena
Cardiac Care Unit (CCU) Excellence Manual – Dr J L Meena | Page 52
CHAPTER 15: CCU PROFESSIONAL PLEDGE
Introduction
A CCU Professional Pledge is a formal, collective commitment to uphold the highest standards of continuous
vigilance, time-sensitive reperfusion, and medication precision. It serves as a daily affirmation that every
rhythm watched, every minute saved, and every dose double-checked is an act of professional purpose in
service of a heart whose next few minutes will determine the years that follow.
Official CCU Professional Pledge
“We solemnly pledge that as the CCU team, we will fulfil our collective and individual responsibilities with the
highest standards of continuous vigilance, technical precision, and unwavering commitment to every patient
whose cardiac survival depends on the speed and accuracy of our response.
We will maintain continuous cardiac rhythm monitoring without lapse, respond to every alarm with genuine
clinical assessment, and never dismiss a warning sign without verification, knowing that a heart can fail
suddenly and that our vigilance is the only safeguard standing between a treatable arrhythmia and a fatal one.
We will activate every time-sensitive reperfusion protocol immediately upon recognition, minimizing door-to-
balloon and door-to-needle time to the fullest extent our system allows, knowing that every minute of delay
costs heart muscle that will never regenerate, and that this muscle determines not only survival but the quality
of every year that follows.
We will apply independent double-check to every high-alert cardiac medication, calculate every anticoagulant
dose with exacting precision, and monitor every coagulation parameter rigorously, knowing that these drugs
carry among the narrowest safety margins in all of pharmacology, and that our precision is what separates
healing from catastrophic harm.
We will communicate honestly and with genuine compassion, even amid the intensity and speed cardiac
emergencies demand, and we will support every patient's transition into cardiac rehabilitation and long-term
secondary prevention, extending our protection beyond the acute crisis into the years of life that follow it.
We will report every incident and near-miss honestly, debrief after every critical event, and continuously
expand our knowledge and skill, knowing that cardiac care evidence evolves rapidly and that the team that
does not learn continuously treats today's hearts with yesterday's protocols.
With unblinking vigilance, rapid and precise clinical judgment, and genuine compassion for every patient whose
heart depends on us, we pledge to be the CCU team that answers every question a heartbeat on the monitor
asks, before it ever becomes silence.”
Cardiac Care Unit (CCU) Excellence Manual Dr J L Meena
Cardiac Care Unit (CCU) Excellence Manual – Dr J L Meena | Page 53
Daily Commitment Statement
“Today, we commit to maintaining continuous rhythm monitoring, activating every time-sensitive protocol
without delay, completing independent double-check for every high-alert medication, communicating
honestly, and upholding every safety standard — because every patient in this unit depends on our complete
vigilance.”
Core Values Reflected in the Pledge
1. Continuous Vigilance
Uninterrupted cardiac rhythm monitoring, sustained without lapse.
2. Time-Sensitive Discipline
Immediate reperfusion protocol activation where minutes determine muscle survival.
3. Medication Precision
Exact, independently verified dosing for the narrowest-margin drugs in pharmacology.
4. Rapid, Honest Communication
Genuine compassion delivered at the speed cardiac emergencies demand.
5. Accountability
Every decision owned and documented; every incident honestly reviewed.
6. Long-Term Commitment
Protection extended beyond the acute crisis into cardiac rehabilitation and secondary prevention.
7. Continuous Learning
Cardiac care evidence evolves rapidly. Professional competence requires perpetual learning.
When the Pledge Should Be Recited
● At the beginning of every new CCU team member's appointment.
● At quality governance and morbidity/mortality review meetings.
● At NABH/JCI accreditation preparation events.
● As a periodic collective affirmation, particularly following a significant adverse cardiac event.
CCU Oath of Vigilance and Precision
“We pledge to be the vigilance that never lapses and the precision that never wavers — ensuring that every
heart in our care is watched continuously, treated within the minutes that matter, and given the fullest possible
chance at the years of life that follow this crisis.”
Cardiac Care Unit (CCU) Excellence Manual Dr J L Meena
Cardiac Care Unit (CCU) Excellence Manual – Dr J L Meena | Page 54
CCU Signature Commitment
This pledge is recited collectively by the multidisciplinary CCU team and may be individually signed by:
Name: ___________________________
Role: Cardiologist / CCU Nurse / Cardiac Catheterization Team Member / Cardiac Rehabilitation Specialist
Department: Cardiac Care Unit
Registration/Employee ID: _______________
Signature: ________________________
Date: ____________________________
Cardiac Care Unit (CCU) Excellence Manual Dr J L Meena
Cardiac Care Unit (CCU) Excellence Manual – Dr J L Meena | Page 55
CONCLUSION
Time is muscle. This single principle defines the entire discipline of cardiac critical care, and it is the principle
this manual has returned to, chapter after chapter, because no other truth in medicine carries quite the same
unforgiving urgency. A heart does not fail gradually and gently — it fails suddenly, catastrophically, and often
without more than seconds of warning, and the team watching over it must be positioned, continuously, to act
before that failure becomes irreversible. Yet for the overwhelming majority of cardiac patients, the outcome
is not tragedy but recovery: a heart attack caught and treated within the golden window, an arrhythmia
defibrillated before it became fatal, a patient who walked out of this unit carrying decades of life this team's
vigilance and precision made possible.
Throughout this manual, we have explored the full scope of CCU professional practice — from admission and
continuous rhythm monitoring, through STEMI and acute coronary syndrome management, arrhythmia
recognition and defibrillation readiness, high-alert medication safety, and cardiogenic shock response, to
cardiac rehabilitation, discharge planning, and the professional conduct that defines excellence across every
category of cardiac emergency. These responsibilities collectively define a discipline that demands both split-
second decisiveness and sustained, unwavering vigilance — because the heart, unlike almost any other organ,
offers no gradual warning before it fails.
The Importance of the CCU Team in Healthcare Quality
● The continuous watcher — maintaining rhythm monitoring that catches deterioration in the seconds
that matter.
● The time-sensitive responder — minimizing every minute between coronary occlusion and
reperfusion.
● The precision practitioner — calculating every high-alert medication dose exactly, in drugs with the
narrowest margins in pharmacology.
● The shock recognizer — catching cardiogenic shock before circulatory collapse becomes irreversible.
● The long-term protector — extending care beyond the acute crisis into cardiac rehabilitation and
secondary prevention.
● The honest reviewer — examining every incident and near-miss to protect the next patient whose
heart cannot wait.
Final Commitment
“As the CCU team, we commit to maintaining continuous rhythm monitoring, activating every time-sensitive
reperfusion protocol without delay, completing independent double-check for every high-alert medication,
communicating honestly and compassionately, and upholding every regulatory and ethical standard without
exception — because every heartbeat on the monitor depends on our complete vigilance, and every patient's
future depends on the muscle we preserve today.”
Cardiac Care Unit (CCU) Excellence Manual Dr J L Meena
Cardiac Care Unit (CCU) Excellence Manual – Dr J L Meena | Page 56
Final Motto
“Every Heartbeat on the Monitor Is a Question the CCU Team Must Answer Before It Becomes Silence.”
Together, We Are the Vigilance That Never Lapses — Ensuring Every Heart in Our Care Is Watched,
Treated in Time, and Given Every Year That Follows.
Cardiac Care Unit (CCU) Excellence Manual Dr J L Meena
Cardiac Care Unit (CCU) Excellence Manual – Dr J L Meena | Page 57
REFERENCES
Global Accreditation and Regulatory Standards
● World Health Organization (WHO) – Global Hearts Initiative and Cardiovascular Disease Management
Guidelines.
● Joint Commission International (JCI) – JCI Accreditation Standards for Hospitals: Care of Patients (COP)
Chapter, including Cardiac Critical Care Requirements.
● National Accreditation Board for Hospitals & Healthcare Providers (NABH, India) – Standards for
Cardiac Care Unit Services (5th Edition).
● International Society for Quality in Health Care (ISQua) – Guidelines and Principles for Health and Social
Care Standards, applied to Cardiac Critical Care.
Acute Coronary Syndrome and STEMI Management Standards
● American Heart Association / American College of Cardiology (AHA/ACC) – Guidelines for the
Management of Patients with ST-Elevation Myocardial Infarction.
● European Society of Cardiology (ESC) – Guidelines for the Management of Acute Myocardial Infarction
in Patients Presenting with ST-Segment Elevation.
● Cardiological Society of India (CSI) – Guidelines for Management of STEMI in the Indian Context.
Resuscitation and Advanced Cardiac Life Support Standards
● American Heart Association (AHA) – Advanced Cardiovascular Life Support (ACLS) Provider Manual and
Guidelines.
● International Liaison Committee on Resuscitation (ILCOR) – Adult Life Support Consensus on Science
and Treatment Recommendations.
Heart Failure and Cardiogenic Shock Standards
● American Heart Association / American College of Cardiology / Heart Failure Society of America –
Guidelines for the Management of Heart Failure.
● European Society of Cardiology (ESC) – Guidelines for the Diagnosis and Treatment of Acute and
Chronic Heart Failure.
● Society for Cardiovascular Angiography and Interventions (SCAI) – Classification and Management of
Cardiogenic Shock.
Anticoagulation and Medication Safety Standards
● American College of Chest Physicians (CHEST) – Antithrombotic Therapy and Prevention of Thrombosis
Guidelines.
Cardiac Care Unit (CCU) Excellence Manual Dr J L Meena
Cardiac Care Unit (CCU) Excellence Manual – Dr J L Meena | Page 58
● Institute for Safe Medication Practices (ISMP) – High-Alert Medications in Acute Care Settings.
Cardiac Rehabilitation and Secondary Prevention Standards
● American Association of Cardiovascular and Pulmonary Rehabilitation (AACVPR) – Guidelines for
Cardiac Rehabilitation Programs.
● European Association of Preventive Cardiology (EAPC) – Secondary Prevention Guidelines.
Indian Regulatory and Statutory Framework
● National Medical Commission (NMC) – Code of Medical Ethics Regulations Applicable to Cardiac Care.
● Clinical Establishments (Registration and Regulation) Act, India – Applicable Cardiac Care Regulatory
Requirements.
● Ayushman Bharat / National Health Authority (India) – Guidelines on Cardiac Care Under Government
Health Schemes.
Quality Improvement and Patient Safety Frameworks
● American College of Cardiology – National Cardiovascular Data Registry (NCDR) Quality Improvement
Standards.
● Institute for Healthcare Improvement (IHI) – Framework for Patient Safety and Quality Improvement
in Cardiac Care.
● World Health Organization – Global Patient Safety Action Plan 2021–2030.
Cybersecurity and Digital Health Records
● NIST Cybersecurity Framework – Applied to Healthcare Cardiac Monitoring and Information Systems.
● HL7 International – Health Level Seven Data Interchange Standards.
This manual has been developed using internationally recognized principles and best practices from WHO
Global Hearts Initiative, JCI Care of Patients Standards, NABH Cardiac Care Unit Standards, AHA/ACC and ESC
STEMI and Heart Failure Guidelines, ACLS Resuscitation Guidelines, SCAI Cardiogenic Shock Classification,
CHEST Antithrombotic Therapy Guidelines, ISMP High-Alert Medication Guidance, AACVPR Cardiac
Rehabilitation Guidelines, Cardiological Society of India Guidelines, applicable Indian statutory and regulatory
requirements, and international cardiac patient safety frameworks. Institutions should verify current versions
of all cited guidelines and regulatory requirements, as clinical protocols and accreditation standards are subject
to periodic revision.
ॐ जय माता द( ॐ
Cardiac Care Unit (CCU) Excellence Manual Dr J L Meena
Cardiac Care Unit (CCU) Excellence Manual – Dr J L Meena | Page 59
END OF MANUAL
Thank You
This manual has been prepared with the vision to empower the multidisciplinary CCU team with global
standards, best practices, and professional guidance to ensure safe, rapid, and vigilant care for every cardiac
patient.
Our Commitment Continues
The journey of learning never ends. As cardiac care evidence evolves and reperfusion science advances, our
commitment to patient safety, vigilance, precision, and compassion must remain unwavering.
Together, We Build Trust
Every rhythm watched, every minute saved, every dose double-checked, and every family treated with genuine
compassion contributes to one greater purpose — hearts protected in their most fragile hours, and decades of
life made possible because of it.
“Every Heartbeat on the Monitor Is a Question the CCU Team Must Answer Before It Becomes
Silence.”
REMEMBER: Safety is our priority • Vigilance is our discipline • Speed is our standard • Precision is our
strength • Learning is our journey
Thank you for being a part of this vital mission. Your dedication makes a difference every day.
Dr J L Meena