Calcium Channel Blocker
MODERATOR- Dr. Pinu Ranawat
PRESENTER- Dr.Anjul Kumar Singh
Introduction
• Calcium channel blockers (also known as calcium entry blockers and
calcium antagonists) are a diverse group of structurally unrelated
compounds that selectively interfere with inward calcium ion
movement across myocardial and vascular smooth muscle cells.
• Calcium ions play a key role in electrical excitation of cardiac cells and
vascular smooth muscle cells.
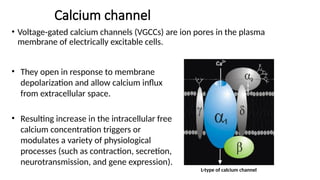
Calcium channel
• Voltage-gated calcium channels (VGCCs) are ion pores in the plasma
membrane of electrically excitable cells.
• They open in response to membrane
depolarization and allow calcium influx
from extracellular space.
• Resulting increase in the intracellular free
calcium concentration triggers or
modulates a variety of physiological
processes (such as contraction, secretion,
neurotransmission, and gene expression).
L-type of calcium channel
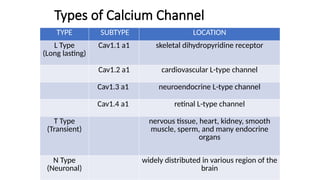
Types of Calcium Channel
TYPE SUBTYPE LOCATION
L Type
(Long lasting)
Cav1.1 a1 skeletal dihydropyridine receptor
Cav1.2 a1 cardiovascular L-type channel
Cav1.3 a1 neuroendocrine L-type channel
Cav1.4 a1 retinal L-type channel
T Type
(Transient)
nervous tissue, heart, kidney, smooth
muscle, sperm, and many endocrine
organs
N Type
(Neuronal)
widely distributed in various region of the
brain
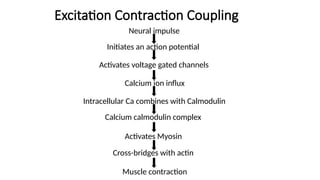
Muscle contraction
Cross-bridges with actin
Activates Myosin
Calcium calmodulin complex
Intracellular Ca combines with Calmodulin
Neural impulse
Initiates an action potential
Activates voltage gated channels
Calcium ion influx
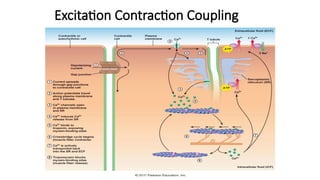
Excitation Contraction Coupling
Mechanism of Action
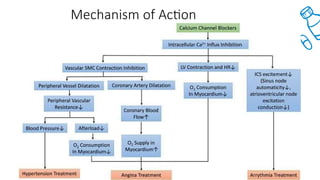
• CCB bind to receptors on voltage-gated calcium ion channels resulting in
maintenance of this channel in an inactive state.
• As a result, calcium influx is decreased and there is reduction in intracellular
calcium.
• Calcium influx through L-type channels is responsible for phase 2 of the
action potential, which is important in excitation-contraction coupling in
cardiac and vascular smooth muscle and depolarization in SA and AV Nodel
tissue.
Mechanism of Action
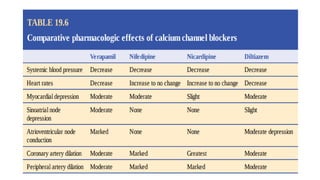
Differential effects of different CCBs
on CV cells
AV
SN
AV
SN
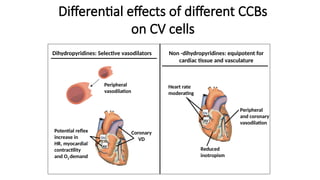
Potential reflex
increase in
HR, myocardial
contractility
and O2 demand
Coronary
VD
Dihydropyridines: Selective vasodilators Non -dihydropyridines: equipotent for
cardiac tissue and vasculature
Heart rate
moderating
Peripheral
and coronary
vasodilation
Reduced
inotropism
Peripheral
vasodilation
Classification of CCBs
Phenylalkylamine-Verapamil
• Synthetic derivative of papaverine
• The dextroisomer of verapamil is acts on
fast sodium channels, accounting for the
local anesthetic effects of verapamil (1.6
times as potent as procaine).
• The levoisomer of verapamil is specific for
slow calcium channels.
• Metabolized by N-demethylation to
norverapamil (less active).
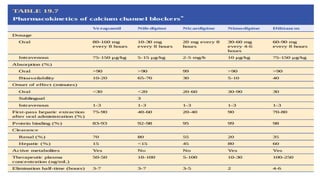
Pharmacokinetics
• Drug is metabolized quickly and, as a result, has low bioavailability.
• Liver is the main site of first-pass metabolism, forming several products.
• The preferential metabolic step involves N-dealkylation, followed by
O-
demethylation, and subsequent conjugation of the product before
elimination.
• The metabolites have no significant biological activity.
• Verapamil has an elimination half-life of 3-7 hours.
Phenylalkylamine….Verapamil
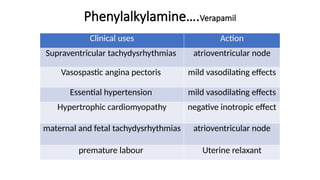
Clinical uses Action
Supraventricular tachydysrhythmias atrioventricular node
Vasospastic angina pectoris mild vasodilating effects
Essential hypertension mild vasodilating effects
Hypertrophic cardiomyopathy negative inotropic effect
maternal and fetal tachydysrhythmias atrioventricular node
premature labour Uterine relaxant
CONTRA-INDICATIONS
• Cardiogenic shock.
• Severe bradycardia.
• Sinus node dysfunction, or
• Atrioventricular nodal block
• severe left ventricular dysfunction.
• Uncompensated heart failure.
• Hypotension (systolic pressure <90 mm Hg),
• High lipid:water partition
coefficient (lipophilic).
• Have good oral absorption
but lower bioavailability
(50-65%) due to first-pass
metabolism
• 90-95% of the drug is
bound to plasma proteins.
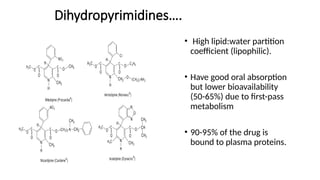
Dihydropyrimidines….
N
H
NO2
C
O
O
CH3
C
O
O
H3C
H
CH3
Nifedipine (ProcardiaR
)
N
H
C
O
O
C
O
O
H3C
H
Cl
C2H5
CH2
O (CH2)2-NH2
Amlodipine (NorvascR
)
N
H
NO2
C
O
O
C
O
O
H3C
H
CH3
(CH2)2-N
CH3
CH2
Nicardipine (CardeneR
)
N
H
C
O
O
C
O
O
H3C
H
CH3
O
N
N CH3
CH
CH3
H3C
Isradipine (DynacircR
)
• Dihydropyridines are excellent antihypertensive agents.
• Potent arterial dilator with few venodilating effects.
• Reflex activation of the sympathetic nervous system may increase HR.
• Antianginal effects result from reduced myocardial oxygen requirements
secondary to the afterload-reducing effect and to coronary vascular
dilation resulting in improved myocardial oxygen delivery.
• Can aggravate ischemic heart disease due to increased myocardial work.
Dihydropyrimidines…
Nifedipine
• Dihydropyridine derivative with greater coronary and
peripheral arterial vasodilator properties than
verapamil.
• There is minimal effect on venous capacitance
vessels.
• Unlike verapamil, nifedipine has little or no direct
depressant effect on SA or AV node activity.
Nifedipine
• Dose:
• Oral- 10-30 mg every 8 hrs
• I.V.-5-15 μg/kg
• Indications:
• Chronic stable angina,
• Prinzmetal’s angina.
• Contraindications:
• Nifedipine may produce excessive myocardial depression, especially in patients with
preexisting left ventricular dysfunction or concomitant therapy with a β-adrenergic
antagonist drug.
• Aortic stenosis may also exaggerate cardiac depressant effects of nifedipine.
•Side effects:
•Peripheral edema (venous congestion),
•Hypotension,
•Flushing,
•Dizziness,
•Headache,
•Nausea,
•Increased micturition frequency,
•Skeletal muscle weakness
•Paraesthesia
Amlodipine
• It is a third generation 1,4-dihyropyridine derivative of the prototypical molecule nifedipine.
• Only oral administration (5-10 mg)
• Elimination halftime is 30 to 40 hours, and about 90% of the drug undergoes hepatic metabolism to inactive
products.
• Have minimal detrimental effects on myocardial contractility and provides anti-ischemic effects comparable
to β-blockers in patients with acute coronary syndrome.
• Combination of amlodipine and β-blockers may be more effective in the treatment of myocardial ischemia
than either drug alone.
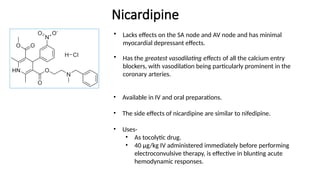
Nicardipine
• Lacks effects on the SA node and AV node and has minimal
myocardial depressant effects.
• Has the greatest vasodilating effects of all the calcium entry
blockers, with vasodilation being particularly prominent in the
coronary arteries.
• Available in IV and oral preparations.
• The side effects of nicardipine are similar to nifedipine.
• Uses-
• As tocolytic drug.
• 40 μg/kg IV administered immediately before performing
electroconvulsive therapy, is effective in blunting acute
hemodynamic responses.
Clevidipine
• Third-generation dihydropyridine
• Extremely lipophilic and ultrashort acting.
• It is U.S. F.D.A approved for the treatment of acute, severe hypertension and is only
available in an IV form.
• Cleared by plasma esterases with a metabolism half-life of approximately 1 minute.
• Dosing starts at 1 to 2 mg per hour and is doubled every 90 seconds until blood
pressure approaches goal.
• Side effects include hypotension and tachycardia
• Contraindicated in
• Hyperlipidemic states,
• Acute or chronic pancreatitis, and
• Heart failure with reduced ejection fraction as higher dose infusions have
been associated with a negative inotropic effect that could precipitate acute
decompensation
Nimodipine
• Highly lipid-soluble analogue of nifedipine.
• Lipid solubility facilitates its entrance into the CNS, where it blocks the influx of
extracellular calcium ions necessary for contraction of large cerebral arteries.
• Clinical Uses - Useful in preventing or attenuating cerebral vasospasm that often
accompanies subarachnoid hemorrhage.
• 0.7 mg/kg orally as an initial dose followed by 0.35 mg/kg every 4 hours for 21 days for
SAH.
• Nimodipine also has been evaluated for cerebral protection after global ischemia, as
associated with cardiac arrest.
Diltiazem hydrochloride
• Benzothiazepine calcium-channel blocker.
• Exerts minimal cardiodepressant effects
• Effects on the SA and AV nodes and its vasodilating properties appear to be
intermediate between those of verapamil and the dihydropyridines.
• Diltiazem have two additional effects
- Act on sodium-potasium pump.
- Inhibit calcium-calmodulin binding
• Diltiazem attenuates baroreflex increases in HR secondary to NTG and
decreases in HR secondary to phenylephrine.
•Uses
• First-line medication for the treatment of supraventricular tachydysrhythmias
• Essential hypertension
• Angina Pectoris
•Doses
• Available as an oral capsule and can also be administered IV, especially for the
management of angina pectoris.
• Recommended IV dose is 0.25 to 0.35 mg/kg over 2 minutes and is repeated
in 15 minutes, if needed.
• Unlikely to interact with beta-adrenergic blocking agents.
Pharmacokinetics
• Oral absorption is excellent with an onset of action in 15 minutes and a
peak effect in about 30 minutes
• 70% to 80% bound to proteins and is excreted as inactive metabolites
principally in bile (about 60%) and, to a lesser extent, in urine (about 35%).
• Active metabolites include desacetyl diltiazem and desmethyl diltiazem.
• Elimination half-time for the parent drug is 4 to 6 hours
Diltiazem hydrochloride
Side Effects:
CNS: Headache, fatigue, dizziness, asthenia, drowsiness, nervousness, insomnia, confusion,
tremor,
gait abnormality.
CV: Edema, arrhythmias, angina, second- or third-degree AV block, bradycardia.
CHF: flushing, hypotension, syncope, palpitations.
GI: Nausea, constipation, anorexia, vomiting, diarrhoea, impaired taste, weight increase.
Skin: Rash.
Drug Interaction
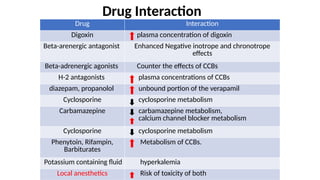
Drug Interaction
Digoxin plasma concentration of digoxin
Beta-arenergic antagonist Enhanced Negative inotrope and chronotrope
effects
Beta-adrenergic agonists Counter the effects of CCBs
H-2 antagonists plasma concentrations of CCBs
diazepam, propanolol unbound portion of the verapamil
Cyclosporine cyclosporine metabolism
Carbamazepine carbamazepine metabolism,
calcium channel blocker metabolism
Cyclosporine cyclosporine metabolism
Phenytoin, Rifampin,
Barbiturates
Metabolism of CCBs.
Potassium containing fluid hyperkalemia
Local anesthetics Risk of toxicity of both
THANK YOU