Evaluation and Physiotherapy
Management of Brain Tumors
Presented by:
Dr. Etika Rana (PT)
BPT, MPT (Neurology), PhD Scholar
Maharishi Markandeshwar Institute of Physiotherapy & Rehabilitation, Maharishi
Markandeshwar (Deemed to be University), Mullana, Haryana
Learning Objectives
✔ Define and classify brain tumors.
✔ Describe the epidemiology, etiology, and pathophysiology of brain tumors.
✔ Recognize the common clinical manifestations.
✔ Perform a comprehensive neurological and functional assessment.
✔ Formulate physiotherapy diagnosis, identify impairments, and prioritize
problems.
✔ Develop evidence-based rehabilitation goals and treatment plans.
✔ Understand current medical, surgical, and physiotherapy management
strategies.
✔ Apply neurophysiological approaches and therapeutic modalities appropriately.
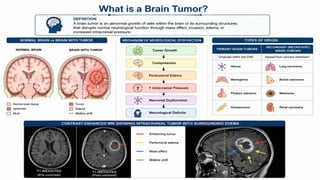
What is a Brain Tumor?
A brain tumor is an abnormal growth of cells within the brain or its
surrounding structures that may be benign (non-cancerous) or malignant
(cancerous). Tumors can arise from the brain itself (primary tumors) or
spread from cancers elsewhere in the body (secondary/metastatic tumors).
Key Characteristics
✓ May originate from: Brain parenchyma , Meninges , Cranial nerves ,
Pituitary gland , Metastatic lesions
✓ Produces neurological dysfunction by: Compression , Invasion , Edema,
Raised intracranial pressure (ICP)
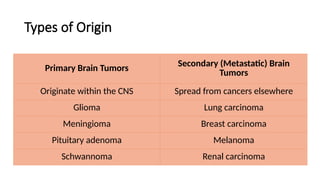
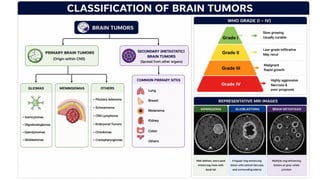
Types of Origin
Primary Brain Tumors
Secondary (Metastatic) Brain
Tumors
Originate within the CNS Spread from cancers elsewhere

Glioma Lung carcinoma
Meningioma Breast carcinoma
Pituitary adenoma Melanoma
Schwannoma Renal carcinoma
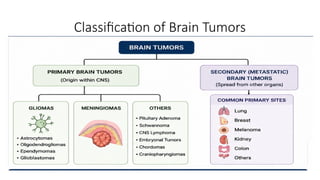
Classification of Brain Tumors
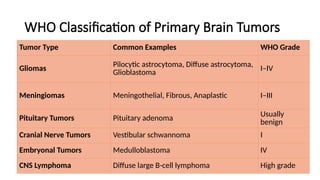
WHO Classification of Primary Brain Tumors
Tumor Type Common Examples WHO Grade
Gliomas Pilocytic astrocytoma, Diffuse astrocytoma,
Glioblastoma I–IV
Meningiomas Meningothelial, Fibrous, Anaplastic I–III
Pituitary Tumors Pituitary adenoma Usually
benign
Cranial Nerve Tumors Vestibular schwannoma I
Embryonal Tumors Medulloblastoma IV
CNS Lymphoma Diffuse large B-cell lymphoma High grade
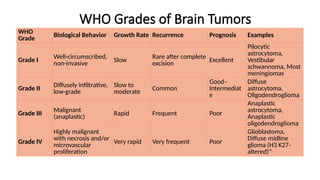
WHO Grades of Brain Tumors
WHO
Grade
Biological Behavior Growth Rate Recurrence Prognosis Examples
Grade I Well-circumscribed,
non-invasive Slow Rare after complete
excision Excellent
Pilocytic
astrocytoma,
Vestibular
schwannoma, Most
meningiomas
Grade II Diffusely infiltrative,
low-grade
Slow to
moderate Common
Good–
Intermediat
e
Diffuse
astrocytoma,
Oligodendroglioma
Grade III
Malignant
(anaplastic) Rapid Frequent Poor
Anaplastic
astrocytoma,
Anaplastic
oligodendroglioma
Grade IV
Highly malignant
with necrosis and/or
microvascular
proliferation
Very rapid Very frequent Poor
Glioblastoma,
Diffuse midline
glioma (H3 K27-
altered)*
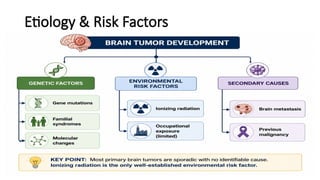
Etiology & Risk Factors
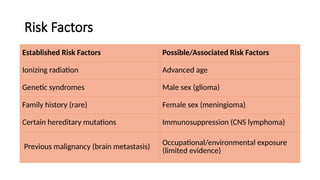
Risk Factors
Established Risk Factors Possible/Associated Risk Factors
Ionizing radiation Advanced age
Genetic syndromes Male sex (glioma)
Family history (rare) Female sex (meningioma)
Certain hereditary mutations Immunosuppression (CNS lymphoma)
Previous malignancy (brain metastasis)
Occupational/environmental exposure
(limited evidence)
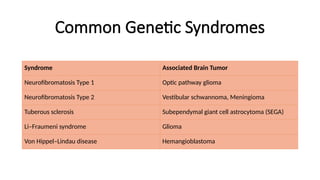
Common Genetic Syndromes
Syndrome Associated Brain Tumor
Neurofibromatosis Type 1 Optic pathway glioma
Neurofibromatosis Type 2 Vestibular schwannoma, Meningioma
Tuberous sclerosis Subependymal giant cell astrocytoma (SEGA)
Li–Fraumeni syndrome Glioma
Von Hippel–Lindau disease Hemangioblastoma
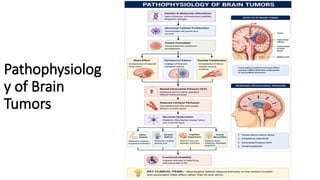
Pathophysiolog
y of Brain
Tumors
Stage Pathophysiological Changes Clinical Consequences
1. Genetic & Molecular
Alterations
Mutations in oncogenes and tumor suppressor
genes lead to uncontrolled cellular proliferation


and resistance to apoptosis.
Tumor initiation
2. Tumor Growth
Progressive expansion and infiltration of
surrounding brain tissue.
Local tissue destruction and
neurological dysfunction
3. Mass Effect Compression and displacement of adjacent
neural structures. Focal neurological deficits, seizures
4. Peritumoral Edema Disruption of the blood–brain barrier causes
vasogenic edema.
Increased intracranial pressure (ICP)
and worsening neurological deficits
5. Vascular Compression
Compression of cerebral vessels reduces
cerebral blood flow. Ischemia and neuronal injury
6. CSF Flow Obstruction Obstruction of ventricular pathways impairs CSF
circulation.
Hydrocephalus and further elevation
of ICP
7. Raised Intracranial
Pressure (ICP)
Increased intracranial volume exceeds
compensatory mechanisms (Monro–Kellie
doctrine).
Headache, vomiting, papilledema,
altered consciousness
8. Neuronal Dysfunction Impaired neuronal conduction and loss of
functional neural networks.
Motor, sensory, cognitive, cranial
nerve, and cerebellar deficits
9. Functional Disability
Progressive impairment of body functions and
activities.
Reduced mobility, ADL limitations,
decreased quality of life
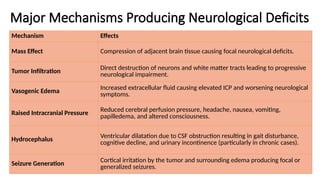
Major Mechanisms Producing Neurological Deficits
Mechanism Effects
Mass Effect Compression of adjacent brain tissue causing focal neurological deficits.
Tumor Infiltration Direct destruction of neurons and white matter tracts leading to progressive
neurological impairment.
Vasogenic Edema
Increased extracellular fluid causing elevated ICP and worsening neurological
symptoms.
Raised Intracranial Pressure Reduced cerebral perfusion pressure, headache, nausea, vomiting,
papilledema, and altered consciousness.
Hydrocephalus Ventricular dilatation due to CSF obstruction resulting in gait disturbance,
cognitive decline, and urinary incontinence (particularly in chronic cases).
Seizure Generation Cortical irritation by the tumor and surrounding edema producing focal or
generalized seizures.
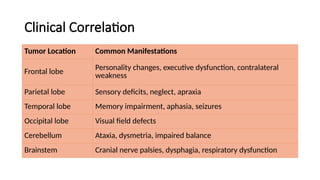
Clinical Correlation
Tumor Location Common Manifestations
Frontal lobe
Personality changes, executive dysfunction, contralateral
weakness
Parietal lobe Sensory deficits, neglect, apraxia
Temporal lobe Memory impairment, aphasia, seizures
Occipital lobe Visual field defects
Cerebellum Ataxia, dysmetria, impaired balance
Brainstem Cranial nerve palsies, dysphagia, respiratory dysfunction
Clinical Manifestations of Brain Tumors
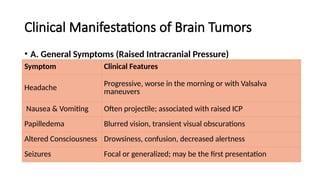
• A. General Symptoms (Raised Intracranial Pressure)
Symptom Clinical Features
Headache
Progressive, worse in the morning or with Valsalva
maneuvers
Nausea & Vomiting Often projectile; associated with raised ICP
Papilledema Blurred vision, transient visual obscurations
Altered Consciousness Drowsiness, confusion, decreased alertness
Seizures Focal or generalized; may be the first presentation
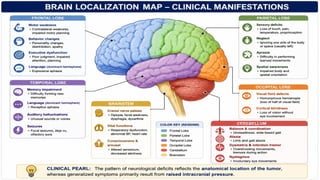
B. Focal Neurological Deficits
Affected Region Clinical Manifestations
Frontal Lobe Contralateral weakness, personality changes, executive
dysfunction, expressive aphasia (dominant hemisphere)
Parietal Lobe Sensory loss, neglect, apraxia, impaired spatial awareness
Temporal Lobe
Memory impairment, receptive aphasia, auditory hallucinations,
seizures
Occipital Lobe Visual field defects (homonymous hemianopia), cortical blindness
Cerebellum Ataxia, dysmetria, intention tremor, nystagmus
Brainstem
Cranial nerve palsies, dysphagia, dysarthria, respiratory
dysfunction
C. Red Flag Symptoms
• Progressive neurological deficits
• New-onset seizures in adults
• Persistent morning headache with vomiting
• Altered mental status
• Papilledema
• Rapid deterioration in neurological function
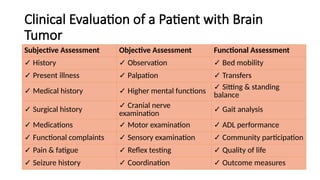
Clinical Evaluation of a Patient with Brain
Tumor
Subjective Assessment Objective Assessment Functional Assessment
✓ History ✓ Observation ✓ Bed mobility
✓ Present illness ✓ Palpation ✓ Transfers
✓ Medical history ✓ Higher mental functions ✓ Sitting & standing
balance
✓ Surgical history ✓ Cranial nerve
examination
✓ Gait analysis
✓ Medications ✓ Motor examination ✓ ADL performance
✓ Functional complaints ✓ Sensory examination ✓ Community participation
✓ Pain & fatigue ✓ Reflex testing ✓ Quality of life
✓ Seizure history ✓ Coordination ✓ Outcome measures
Goals of Clinical Evaluation
• Identify neurological impairments.
• Determine functional limitations.
• Establish baseline functional status.
• Detect medical and rehabilitation precautions.
• Formulate physiotherapy diagnosis.
• Develop individualized rehabilitation goals.
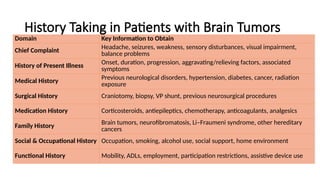
History Taking in Patients with Brain Tumors
Domain Key Information to Obtain
Chief Complaint Headache, seizures, weakness, sensory disturbances, visual impairment,
balance problems
History of Present Illness Onset, duration, progression, aggravating/relieving factors, associated
symptoms
Medical History Previous neurological disorders, hypertension, diabetes, cancer, radiation
exposure
Surgical History Craniotomy, biopsy, VP shunt, previous neurosurgical procedures
Medication History Corticosteroids, antiepileptics, chemotherapy, anticoagulants, analgesics
Family History
Brain tumors, neurofibromatosis, Li–Fraumeni syndrome, other hereditary
cancers
Social & Occupational History Occupation, smoking, alcohol use, social support, home environment
Functional History Mobility, ADLs, employment, participation restrictions, assistive device use
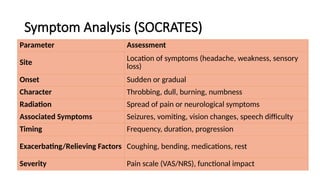
Symptom Analysis (SOCRATES)
Parameter Assessment
Site
Location of symptoms (headache, weakness, sensory
loss)
Onset Sudden or gradual
Character Throbbing, dull, burning, numbness
Radiation Spread of pain or neurological symptoms
Associated Symptoms Seizures, vomiting, vision changes, speech difficulty
Timing Frequency, duration, progression
Exacerbating/Relieving Factors Coughing, bending, medications, rest
Severity Pain scale (VAS/NRS), functional impact
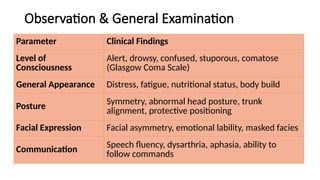
Observation & General Examination
Parameter Clinical Findings
Level of
Consciousness
Alert, drowsy, confused, stuporous, comatose
(Glasgow Coma Scale)
General Appearance Distress, fatigue, nutritional status, body build
Posture
Symmetry, abnormal head posture, trunk
alignment, protective positioning
Facial Expression Facial asymmetry, emotional lability, masked facies
Communication Speech fluency, dysarthria, aphasia, ability to
follow commands
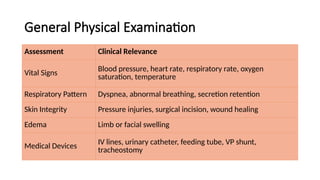
General Physical Examination
Assessment Clinical Relevance
Vital Signs
Blood pressure, heart rate, respiratory rate, oxygen
saturation, temperature
Respiratory Pattern Dyspnea, abnormal breathing, secretion retention
Skin Integrity Pressure injuries, surgical incision, wound healing
Edema Limb or facial swelling
Medical Devices
IV lines, urinary catheter, feeding tube, VP shunt,
tracheostomy
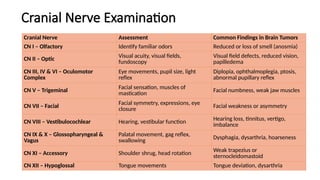
Cranial Nerve Examination
Cranial Nerve Assessment Common Findings in Brain Tumors
CN I – Olfactory Identify familiar odors Reduced or loss of smell (anosmia)
CN II – Optic
Visual acuity, visual fields,
fundoscopy
Visual field defects, reduced vision,
papilledema
CN III, IV & VI – Oculomotor
Complex
Eye movements, pupil size, light
reflex
Diplopia, ophthalmoplegia, ptosis,
abnormal pupillary reflex
CN V – Trigeminal Facial sensation, muscles of
mastication
Facial numbness, weak jaw muscles
CN VII – Facial
Facial symmetry, expressions, eye
closure
Facial weakness or asymmetry
CN VIII – Vestibulocochlear Hearing, vestibular function Hearing loss, tinnitus, vertigo,
imbalance
CN IX & X – Glossopharyngeal &
Vagus
Palatal movement, gag reflex,
swallowing
Dysphagia, dysarthria, hoarseness
CN XI – Accessory Shoulder shrug, head rotation
Weak trapezius or
sternocleidomastoid
CN XII – Hypoglossal Tongue movements Tongue deviation, dysarthria
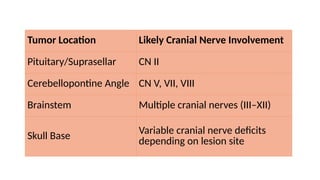
Tumor Location Likely Cranial Nerve Involvement
Pituitary/Suprasellar CN II
Cerebellopontine Angle CN V, VII, VIII
Brainstem Multiple cranial nerves (III–XII)
Skull Base
Variable cranial nerve deficits
depending on lesion site
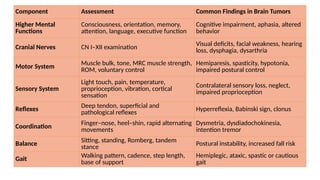
Component Assessment Common Findings in Brain Tumors
Higher Mental
Functions
Consciousness, orientation, memory,
attention, language, executive function
Cognitive impairment, aphasia, altered
behavior
Cranial Nerves CN I–XII examination Visual deficits, facial weakness, hearing
loss, dysphagia, dysarthria
Motor System Muscle bulk, tone, MRC muscle strength,
ROM, voluntary control
Hemiparesis, spasticity, hypotonia,
impaired postural control
Sensory System
Light touch, pain, temperature,
proprioception, vibration, cortical
sensation
Contralateral sensory loss, neglect,
impaired proprioception
Reflexes Deep tendon, superficial and
pathological reflexes Hyperreflexia, Babinski sign, clonus
Coordination
Finger–nose, heel–shin, rapid alternating
movements
Dysmetria, dysdiadochokinesia,
intention tremor
Balance Sitting, standing, Romberg, tandem
stance
Postural instability, increased fall risk
Gait Walking pattern, cadence, step length,
base of support
Hemiplegic, ataxic, spastic or cautious
gait
Diagnostic Investigations
Investigation Purpose Key Findings
Magnetic Resonance Imaging
(MRI) – Gold Standard
Tumor localization, size, edema,
mass effect
Contrast enhancement, midline
shift, infiltration
Computed Tomography (CT)
Emergency assessment,
hemorrhage, calcification,
hydrocephalus
Acute bleeding, bony involvement
Brain Biopsy / Histopathology Definitive diagnosis Tumor type, WHO grade, molecular
markers
Molecular & Genetic Testing Tumor classification and prognosis
IDH mutation, 1p/19q codeletion,
MGMT promoter methylation
(gliomas)
Positron Emission Tomography
(PET)
Tumor metabolism and recurrence Differentiate recurrence from
radiation necrosis
Electroencephalography (EEG) Evaluation of seizures Epileptiform discharges
Laboratory Investigations Preoperative and treatment
monitoring
CBC, coagulation profile,
electrolytes, liver & renal function
Differential Diagnosis of Brain Tumors
Condition Clinical Features Distinguishing Findings
Brain Tumor Progressive headache, seizures, focal
neurological deficits, cognitive decline
MRI shows space-occupying lesion with
mass effect
Stroke Sudden onset of neurological deficits CT/MRI demonstrates ischemia or
hemorrhage; acute presentation
Brain Abscess Fever, headache, focal deficits Ring-enhancing lesion with systemic signs
of infection
Subdural Hematoma Head injury, altered consciousness Crescent-shaped hematoma on CT scan
Meningitis/
Encephalitis
Fever, neck stiffness, altered mental
status
CSF abnormalities, meningeal signs
Multiple Sclerosis Episodic neurological deficits Multiple demyelinating plaques on MRI
Hydrocephalus Gait disturbance, cognitive impairment,
urinary incontinence Ventricular enlargement on imaging
Brain Metastasis History of systemic malignancy Multiple enhancing lesions on MRI
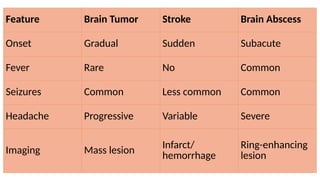
Feature Brain Tumor Stroke Brain Abscess
Onset Gradual Sudden Subacute
Fever Rare No Common
Seizures Common Less common Common
Headache Progressive Variable Severe
Imaging Mass lesion Infarct/
hemorrhage
Ring-enhancing
lesion
Medical Management of Brain Tumors
Objectives of Medical Management
• Relieve neurological symptoms
• Control tumor growth
• Reduce intracranial pressure
• Prevent complications
• Improve quality of life
• Prepare patients for surgery or rehabilitation
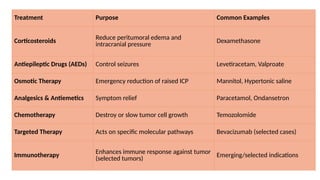
Treatment Purpose Common Examples
Corticosteroids Reduce peritumoral edema and
intracranial pressure
Dexamethasone
Antiepileptic Drugs (AEDs) Control seizures Levetiracetam, Valproate
Osmotic Therapy Emergency reduction of raised ICP Mannitol, Hypertonic saline
Analgesics & Antiemetics Symptom relief Paracetamol, Ondansetron
Chemotherapy Destroy or slow tumor cell growth Temozolomide
Targeted Therapy Acts on specific molecular pathways Bevacizumab (selected cases)
Immunotherapy Enhances immune response against tumor
(selected tumors)
Emerging/selected indications
Surgical Management of Brain Tumors
• Objectives of Surgery
• Obtain definitive diagnosis (biopsy)
• Achieve maximal safe tumor resection
• Reduce mass effect and intracranial pressure
• Relieve neurological symptoms
• Improve survival and functional outcomes
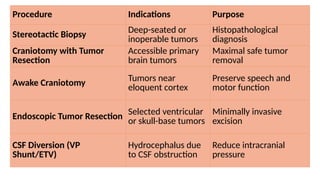
Procedure Indications Purpose
Stereotactic Biopsy Deep-seated or
inoperable tumors
Histopathological
diagnosis
Craniotomy with Tumor
Resection
Accessible primary
brain tumors
Maximal safe tumor
removal
Awake Craniotomy Tumors near
eloquent cortex
Preserve speech and
motor function
Endoscopic Tumor Resection Selected ventricular
or skull-base tumors
Minimally invasive
excision
CSF Diversion (VP
Shunt/ETV)
Hydrocephalus due
to CSF obstruction
Reduce intracranial
pressure
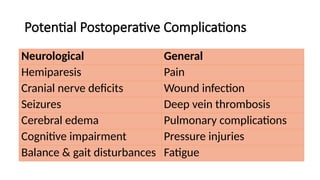
Potential Postoperative Complications
Neurological General
Hemiparesis Pain
Cranial nerve deficits Wound infection
Seizures Deep vein thrombosis
Cerebral edema Pulmonary complications
Cognitive impairment Pressure injuries
Balance & gait disturbances Fatigue
Physiotherapy Goals After Surgery
Phase Goals
Acute (0–7 days) Prevent complications, chest care, positioning,
ROM, early mobilization
Subacute Improve sitting and standing balance, transfers,
strength, gait training
Rehabilitation Restore functional independence, endurance,
community mobility, participation
Physiotherapy Management
Rehabilitation Goals
• Acute Phase (ICU/Early Postoperative)
• Prevent secondary complications
• Maintain airway clearance and optimize ventilation
• Prevent pressure injuries and contractures
• Maintain joint range of motion
• Promote early mobilization
• Improve sitting tolerance
Subacute Phase
• Improve trunk control
• Restore postural stability
• Improve muscle strength and endurance
• Enhance balance and coordination
• Facilitate gait and transfer training
• Improve functional independence
Chronic Phase
• Maximize community reintegration
• Improve participation in daily activities
• Enhance cardiovascular fitness
• Reduce fall risk
• Improve quality of life
• Encourage lifelong physical activity
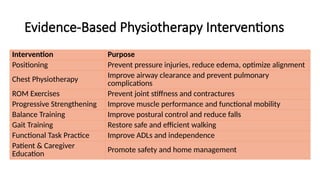
Evidence-Based Physiotherapy Interventions
Intervention Purpose
Positioning Prevent pressure injuries, reduce edema, optimize alignment
Chest Physiotherapy
Improve airway clearance and prevent pulmonary
complications
ROM Exercises Prevent joint stiffness and contractures
Progressive Strengthening Improve muscle performance and functional mobility
Balance Training Improve postural control and reduce falls
Gait Training Restore safe and efficient walking
Functional Task Practice Improve ADLs and independence
Patient & Caregiver
Education
Promote safety and home management
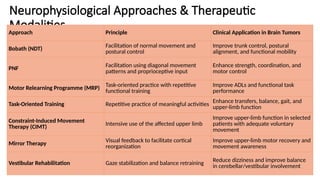
Neurophysiological Approaches & Therapeutic
Modalities
Approach Principle Clinical Application in Brain Tumors
Bobath (NDT)
Facilitation of normal movement and
postural control
Improve trunk control, postural
alignment, and functional mobility
PNF
Facilitation using diagonal movement
patterns and proprioceptive input
Enhance strength, coordination, and
motor control
Motor Relearning Programme (MRP) Task-oriented practice with repetitive
functional training
Improve ADLs and functional task
performance
Task-Oriented Training Repetitive practice of meaningful activities
Enhance transfers, balance, gait, and
upper-limb function
Constraint-Induced Movement
Therapy (CIMT)
Intensive use of the affected upper limb
Improve upper-limb function in selected
patients with adequate voluntary
movement
Mirror Therapy
Visual feedback to facilitate cortical
reorganization
Improve upper-limb motor recovery and
movement awareness
Vestibular Rehabilitation Gaze stabilization and balance retraining
Reduce dizziness and improve balance
in cerebellar/vestibular involvement
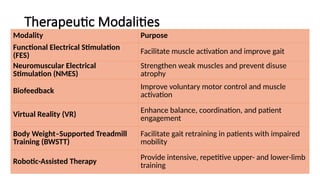
Therapeutic Modalities
Modality Purpose
Functional Electrical Stimulation
(FES)
Facilitate muscle activation and improve gait
Neuromuscular Electrical
Stimulation (NMES)
Strengthen weak muscles and prevent disuse
atrophy
Biofeedback
Improve voluntary motor control and muscle
activation
Virtual Reality (VR)
Enhance balance, coordination, and patient
engagement
Body Weight–Supported Treadmill
Training (BWSTT)
Facilitate gait retraining in patients with impaired
mobility
Robotic-Assisted Therapy
Provide intensive, repetitive upper- and lower-limb
training
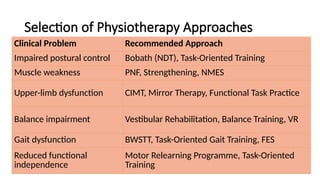
Selection of Physiotherapy Approaches
Clinical Problem Recommended Approach
Impaired postural control Bobath (NDT), Task-Oriented Training
Muscle weakness PNF, Strengthening, NMES
Upper-limb dysfunction CIMT, Mirror Therapy, Functional Task Practice
Balance impairment Vestibular Rehabilitation, Balance Training, VR
Gait dysfunction BWSTT, Task-Oriented Gait Training, FES
Reduced functional
independence
Motor Relearning Programme, Task-Oriented
Training
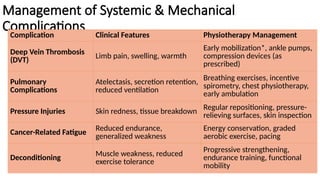
Management of Systemic & Mechanical
Complications
Complication Clinical Features Physiotherapy Management
Deep Vein Thrombosis
(DVT)
Limb pain, swelling, warmth
Early mobilization*, ankle pumps,
compression devices (as
prescribed)
Pulmonary
Complications
Atelectasis, secretion retention,
reduced ventilation
Breathing exercises, incentive
spirometry, chest physiotherapy,
early ambulation
Pressure Injuries Skin redness, tissue breakdown Regular repositioning, pressure-
relieving surfaces, skin inspection
Cancer-Related Fatigue
Reduced endurance,
generalized weakness
Energy conservation, graded
aerobic exercise, pacing
Deconditioning Muscle weakness, reduced
exercise tolerance
Progressive strengthening,
endurance training, functional
mobility
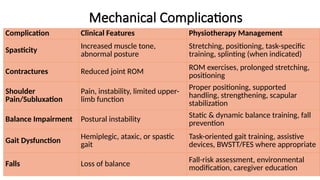
Mechanical Complications
Complication Clinical Features Physiotherapy Management
Spasticity Increased muscle tone,
abnormal posture
Stretching, positioning, task-specific
training, splinting (when indicated)
Contractures Reduced joint ROM
ROM exercises, prolonged stretching,
positioning
Shoulder
Pain/Subluxation
Pain, instability, limited upper-
limb function
Proper positioning, supported
handling, strengthening, scapular
stabilization
Balance Impairment Postural instability Static & dynamic balance training, fall
prevention
Gait Dysfunction Hemiplegic, ataxic, or spastic
gait
Task-oriented gait training, assistive
devices, BWSTT/FES where appropriate
Falls Loss of balance
Fall-risk assessment, environmental
modification, caregiver education
Prevention Strategies
• Early mobilization
• Regular positioning and pressure relief
• Daily range-of-motion exercises
• Progressive strengthening and endurance training
• Appropriate assistive devices
• Patient and caregiver education
• Home safety assessment
• Regular reassessment and follow-up
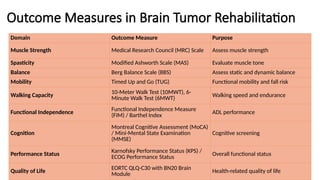
Outcome Measures in Brain Tumor Rehabilitation
Domain Outcome Measure Purpose
Muscle Strength Medical Research Council (MRC) Scale Assess muscle strength
Spasticity Modified Ashworth Scale (MAS) Evaluate muscle tone
Balance Berg Balance Scale (BBS) Assess static and dynamic balance
Mobility Timed Up and Go (TUG) Functional mobility and fall risk
Walking Capacity
10-Meter Walk Test (10MWT), 6-
Minute Walk Test (6MWT)
Walking speed and endurance
Functional Independence
Functional Independence Measure
(FIM) / Barthel Index
ADL performance
Cognition
Montreal Cognitive Assessment (MoCA)
/ Mini-Mental State Examination
(MMSE)
Cognitive screening
Performance Status
Karnofsky Performance Status (KPS) /
ECOG Performance Status
Overall functional status
Quality of Life
EORTC QLQ-C30 with BN20 Brain
Module
Health-related quality of life
Key Take-Home Messages
• Brain tumors may be primary or metastatic and can produce significant neurological impairment through mass effect,
edema, and raised intracranial pressure.
• Clinical manifestations depend primarily on the tumor location, growth rate, and degree of intracranial pressure
rather than tumor size alone.
• Contrast-enhanced MRI is the imaging modality of choice, while histopathological and molecular analyses confirm the
diagnosis and WHO grade.
• Comprehensive neurological and functional assessment is essential for identifying impairments and planning
individualized rehabilitation.
• Early surgical intervention, when indicated, combined with appropriate medical management improves neurological
outcomes and survival.
• Physiotherapy should begin as early as the patient's medical condition allows to prevent secondary complications and
promote functional recovery.
• Task-specific, goal-oriented, and individualized rehabilitation is the cornerstone of neurorehabilitation following brain
tumor treatment.
• Effective rehabilitation requires a multidisciplinary approach involving neurosurgeons, oncologists, physiatrists,
physiotherapists, occupational therapists, speech-language pathologists, psychologists, nurses, and caregivers.
• Regular reassessment using standardized outcome measures is necessary to monitor progress and optimize
rehabilitation goals.
• The ultimate goal of rehabilitation is to maximize independence, community participation, and quality of life.
REFRENCES
• Braddom RL, editor. Braddom's Physical Medicine and Rehabilitation. 7th ed. Philadelphia: Elsevier; 2026.
• O'Sullivan SB, Schmitz TJ, Fulk GD. Physical Rehabilitation. 8th ed. Philadelphia: F.A. Davis; 2023.
• Umphred DA, Lazaro RT, Roller ML, Burton GU. Umphred's Neurological Rehabilitation. 7th ed. St. Louis:
Elsevier; 2020.
• Goodman CC, Fuller KS. Pathology: Implications for the Physical Therapist. 5th ed. St. Louis: Elsevier; 2023.
• World Health Organization Classification of Tumours Editorial Board. Central Nervous System Tumours. WHO
Classification of Tumours Series. 5th ed. Lyon: International Agency for Research on Cancer; 2021.
• Louis DN, Perry A, Wesseling P, et al. The 2021 WHO Classification of Tumors of the Central Nervous System:
A Summary. Neuro Oncol. 2021;23(8):1231–1251.
• Weller M, van den Bent M, Preusser M, et al. EANO guidelines on the diagnosis and treatment of diffuse
gliomas of adulthood. Nat Rev Clin Oncol. 2021;18(3):170–186.
• Le Rhun E, Guckenberger M, Smits M, et al. EANO–ESMO Clinical Practice Guidelines for diagnosis, treatment
and follow-up of patients with brain metastases from solid tumours. Ann Oncol. 2021;32(11):1332–1347.
• National Institute for Health and Care Excellence (NICE). Brain Tumours (Primary) and Brain Metastases in
Adults (NG99). Updated 2021.
Thank You