
medicoseacademics@gmail.com
0310-7990649
Blood Types,
Transfusion, and
Tissue
and Organ
Transplantation
Dr Faiza
MBBS (Best Graduate, AIMC Lahore)
FCPS Physiology,
MHPE (Riphah Int University, Islamabad)
ICMT, CHPE, DHPE (STMU)
MPH (GC University, Faisalabad)
MBA (Virtual University of Pakistan)
medicoseacademics@gmail.com
0310-7990649
Physiological Basis of
Blood Grouping
Dr Faiza
MBBS (Best Graduate, AIMC Lahore)
FCPS Physiology,
MHPE (Riphah Int University, Islamabad)
ICMT, CHPE, DHPE (STMU)
MPH (GC University, Faisalabad)
MBA (Virtual University of Pakistan)
medicoseacademics@gmail.com
0310-7990649
Learning Objectives
• Describe the physiological basis of major blood grouping
systems.
• Discuss pathophysiology, features, and treatment of ABO
and Rh incompatibility.
medicoseacademics@gmail.com
0310-7990649
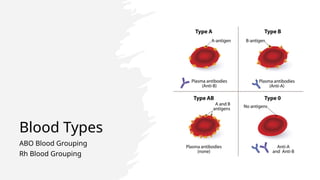
Blood Types
ABO Blood Grouping
Rh Blood Grouping
medicoseacademics@gmail.com
0310-7990649
Antigenicity and Immune Reactions in
Blood
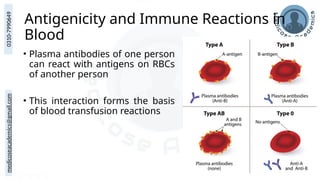
• Plasma antibodies of one person
can react with antigens on RBCs
of another person
• This interaction forms the basis
of blood transfusion reactions
medicoseacademics@gmail.com
0310-7990649
Antigenicity and Immune Reactions in
Blood
• RBC membranes contain many antigens
• At least 30 common antigens exist
• Hundreds of rare antigens are also present
• Any of these antigens may occasionally cause immune
reactions
• Most RBC antigens are weak
• They are mainly useful for studying genetic inheritance
• These antigen patterns may help in parentage testing
medicoseacademics@gmail.com
0310-7990649
Major Antigen Systems in Transfusion
• Two antigen systems are most important in blood
transfusion:
• ABO (O-A-B) blood group system
• Rh blood group system
• These systems cause most clinically significant transfusion
reactions
medicoseacademics@gmail.com
0310-7990649
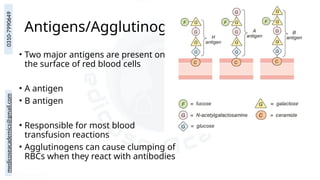
Antigens/Agglutinogens
• Two major antigens are present on
the surface of red blood cells
• A antigen
• B antigen
• Responsible for most blood
transfusion reactions
• Agglutinogens can cause clumping of
RBCs when they react with antibodies
medicoseacademics@gmail.com
0310-7990649
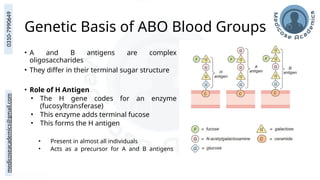
Genetic Basis of ABO Blood Groups
• A and B antigens are complex
oligosaccharides
• They differ in their terminal sugar structure
• Role of H Antigen
• The H gene codes for an enzyme
(fucosyltransferase)
• This enzyme adds terminal fucose
• This forms the H antigen
• Present in almost all individuals
• Acts as a precursor for A and B antigens
medicoseacademics@gmail.com
0310-7990649
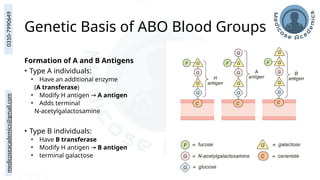
Genetic Basis of ABO Blood Groups
Formation of A and B Antigens
• Type A individuals:
• Have an additional enzyme
(A transferase)
• Modify H antigen → A antigen
• Adds terminal
N-acetylgalactosamine
• Type B individuals:
• Have B transferase
• Modify H antigen → B antigen
• terminal galactose
medicoseacademics@gmail.com
0310-7990649
Distribution of A and B Agglutinogens
• Because of genetic inheritance, RBCs may contain:
• No agglutinogen
• Only A agglutinogen
• Only B agglutinogen
• Both A and B agglutinogens
• This variation forms the basis of the ABO blood group
system
medicoseacademics@gmail.com
0310-7990649
Genetic Basis of ABO Blood Groups
• ABO blood group is determined by three alleles
• IA
• IB
• IO
• These alleles represent different forms of the same gene
medicoseacademics@gmail.com
0310-7990649
Genetic Basis of ABO Blood Groups
• IA
and IB
produce A and B agglutinogens on RBC surface
• IO
allele does not produce agglutinogens
• IA
and IB
show codominance
• IO
allele is recessive to both IA
and IB
medicoseacademics@gmail.com
0310-7990649
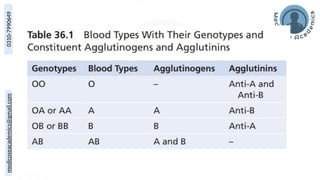
Genotypes of ABO Blood Groups
• Each person inherits two alleles (one from each parent)
• Possible genotype combinations:
• OO
• OA
• OB
• AA
• BB
• AB
• These combinations are called genotypes
• Genotype determines the blood group phenotype
medicoseacademics@gmail.com
0310-7990649
medicoseacademics@gmail.com
0310-7990649
Major ABO Blood Types
• Blood groups are classified based on presence or absence
of agglutinogens
• Type O: No A or B agglutinogens
• Type A: A agglutinogen present
• Type B: B agglutinogen present
• Type AB: Both A and B agglutinogens present
medicoseacademics@gmail.com
0310-7990649
Frequency of ABO Blood Groups
• Approximate prevalence in a studied population:
• Blood group O: 47%
• Blood group A: 41%
• Blood group B: 9%
• Blood group AB: 3%
• O and A genes occur more frequently than B gene
medicoseacademics@gmail.com
0310-7990649
Antigenicity of Blood
• Blood types differ in antigenic properties
• Plasma antibodies of one blood type may react with RBC antigens
of another type
• If incompatible blood is transfused:
• Agglutination (clumping) occurs
• Hemolysis of RBCs may follow
• Proper blood matching helps prevent transfusion reactions
medicoseacademics@gmail.com
0310-7990649
Plasma Antibodies (Agglutinins)
• Antibodies develop against absent antigens
• Type O blood
• Anti-A antibodies
• Anti-B antibodies
• Type A blood
• Anti-B antibodies
• Type B blood
• Anti-A antibodies
• Type AB blood
• No antibodies
medicoseacademics@gmail.com
0310-7990649
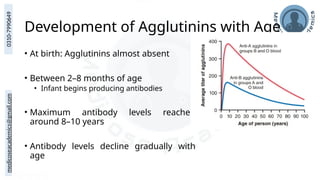
Development of Agglutinins with Age
• At birth: Agglutinins almost absent
• Between 2–8 months of age
• Infant begins producing antibodies
• Maximum antibody levels reached
around 8–10 years
• Antibody levels decline gradually with
age
medicoseacademics@gmail.com
0310-7990649
Origin of Agglutinins
• Agglutinins are gamma globulin antibodies
• Produced by bone marrow and lymphoid cells
• Mainly IgM and IgG immunoglobulins
• Exposure to A or B antigens in food and bacteria stimulates
antibody formation
• Neonates have few antibodies, showing production occurs
after birth
medicoseacademics@gmail.com
0310-7990649
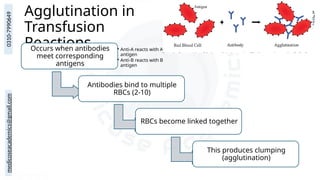
Agglutination in
Transfusion
Reactions
Occurs when antibodies
meet corresponding
antigens
• Anti-A reacts with A
antigen
• Anti-B reacts with B
antigen
Antibodies bind to multiple
RBCs (2-10)
RBCs become linked together
This produces clumping
(agglutination)
medicoseacademics@gmail.com
0310-7990649
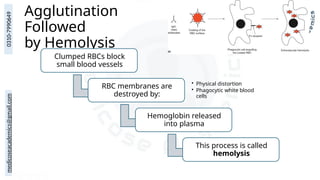
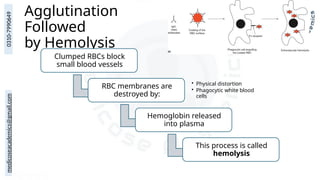
Agglutination
Followed
by Hemolysis
Clumped RBCs block
small blood vessels
RBC membranes are
destroyed by:
• Physical distortion
• Phagocytic white blood
cells
Hemoglobin released
into plasma
This process is called
hemolysis
medicoseacademics@gmail.com
0310-7990649
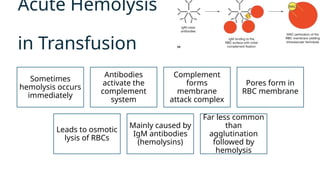
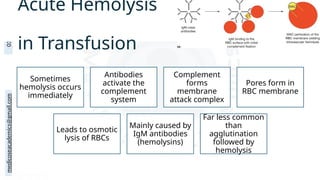
Sometimes
hemolysis occurs
immediately
Antibodies
activate the
complement
system
Complement
forms
membrane
attack complex
Pores form in
RBC membrane
Leads to osmotic
lysis of RBCs
Mainly caused by
IgM antibodies
(hemolysins)
Far less common
than
agglutination
followed by
hemolysis
Acute Hemolysis
in Transfusion
medicoseacademics@gmail.com
0310-7990649
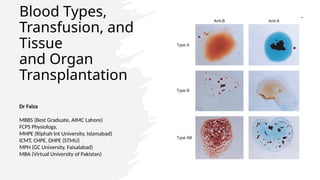
Blood Typing Before
Transfusion
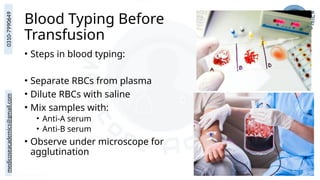
• Steps in blood typing:
• Separate RBCs from plasma
• Dilute RBCs with saline
• Mix samples with:
• Anti-A serum
• Anti-B serum
• Observe under microscope for
agglutination
medicoseacademics@gmail.com
0310-7990649
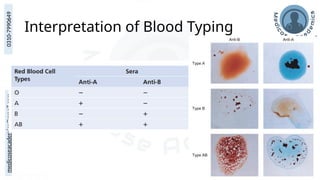
Interpretation of Blood Typing
medicoseacademics@gmail.com
0310-7990649
Rh Blood Group System
Dr Faiza
MBBS (Best Graduate, AIMC Lahore)
FCPS Physiology,
MHPE (Riphah Int University, Islamabad)
ICMT, CHPE, DHPE (STMU)
MPH (GC University, Faisalabad)
MBA (Virtual University of Pakistan)
medicoseacademics@gmail.com
0310-7990649
Rh Blood Group System
• Rh system is the second major blood group system after
ABO
• Important in blood transfusion compatibility
• Unlike ABO system, Rh antibodies do not form naturally
• Antibodies develop only after exposure to Rh antigen
• Exposure occurs through
• Blood transfusion
• Pregnancy
medicoseacademics@gmail.com
0310-7990649
Rh Antigens
• Six common Rh antigens exist
• These are called Rh factors
• Types include:
• C, D, E, c, d, e
• Each person inherits one antigen from each pair
• Examples of antigen pairs
• C or c
• D or d
• E or e
medicoseacademics@gmail.com
0310-7990649
Rh Positive and Rh Negative
• D antigen is the most important Rh antigen
• It is highly antigenic
• If D antigen is present → Rh positive
• If D antigen is absent → Rh negative
• Other Rh antigens may still cause reactions, but these are
usually mild
medicoseacademics@gmail.com
0310-7990649
Distribution of Rh Blood Types
• Approximate prevalence in populations:
• Whites
• Rh positive: 85%
• Rh negative: 15%
• Black Americans
• Rh positive: 95%
• Black Africans
• Nearly 100% Rh positive
• Native Americans and East Asians
• Over 95% Rh positive
• Worldwide frequency
• Rh positive: ~95%
• Rh negative: ~5–6%
medicoseacademics@gmail.com
0310-7990649
Formation of Anti-Rh Antibodies
• Occurs when Rh-positive RBCs enter Rh-negative person
• Immune system recognizes Rh antigen as foreign
• Anti-Rh antibodies develop slowly
• Maximum antibody levels appear after 2–4 months
• Repeated exposure causes strong sensitization
medicoseacademics@gmail.com
0310-7990649
Rh Transfusion Reactions
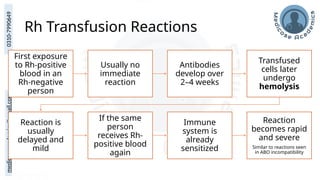
First exposure
to Rh-positive
blood in an
Rh-negative
person
Usually no
immediate
reaction
Antibodies
develop over
2–4 weeks
Transfused
cells later
undergo
hemolysis
Reaction is
usually
delayed and
mild
If the same
person
receives Rh-
positive blood
again
Immune
system is
already
sensitized
Reaction
becomes rapid
and severe
Similar to reactions seen
in ABO incompatibility
medicoseacademics@gmail.com
0310-7990649
Erythroblastosis Fetalis
medicoseacademics@gmail.com
0310-7990649
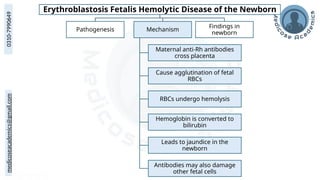
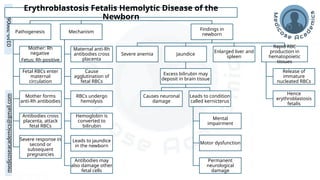
Erythroblastosis Fetalis
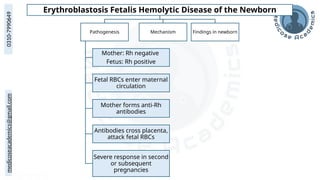
• Also called Hemolytic Disease of the Newborn
• Occurs when:
• Mother is Rh negative
• Fetus is Rh positive
• Fetal RBCs enter maternal circulation
• Mother forms anti-Rh antibodies
• These antibodies cross the placenta and attack fetal RBCs
medicoseacademics@gmail.com
0310-7990649 Erythroblastosis Fetalis Hemolytic Disease of the Newborn
Pathogenesis
Mother: Rh negative
Fetus: Rh positive
Fetal RBCs enter maternal
circulation
Mother forms anti-Rh
antibodies
Antibodies cross placenta,
attack fetal RBCs
Severe response in second
or subsequent
pregnancies
Mechanism Findings in newborn
medicoseacademics@gmail.com
0310-7990649 Erythroblastosis Fetalis Hemolytic Disease of the Newborn
Pathogenesis Mechanism
Maternal anti-Rh antibodies
cross placenta
Cause agglutination of fetal
RBCs
RBCs undergo hemolysis
Hemoglobin is converted to
bilirubin
Leads to jaundice in the
newborn
Antibodies may also damage
other fetal cells
Findings in
newborn
medicoseacademics@gmail.com
0310-7990649
Erythroblastosis Fetalis Hemolytic Disease of the Newborn
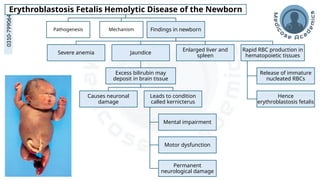
Pathogenesis Mechanism Findings in newborn
Severe anemia Jaundice
Excess bilirubin may
deposit in brain tissue
Causes neuronal
damage
Leads to condition
called kernicterus
Mental impairment
Motor dysfunction
Permanent
neurological damage
Enlarged liver and
spleen
Rapid RBC production in
hematopoietic tissues
Release of immature
nucleated RBCs
Hence
erythroblastosis fetalis
medicoseacademics@gmail.com
0310-7990649 Erythroblastosis Fetalis Hemolytic Disease of the
Newborn
Pathogenesis
Mother: Rh
negative
Fetus: Rh positive
Fetal RBCs enter
maternal
circulation
Mother forms
anti-Rh antibodies
Antibodies cross
placenta, attack
fetal RBCs
Severe response in
second or
subsequent
pregnancies
Mechanism
Maternal anti-Rh
antibodies cross
placenta
Cause
agglutination of
fetal RBCs
RBCs undergo
hemolysis
Hemoglobin is
converted to
bilirubin
Leads to jaundice
in the newborn
Antibodies may
also damage other
fetal cells
Findings in
newborn
Severe anemia Jaundice
Excess bilirubin may
deposit in brain tissue
Causes neuronal
damage
Leads to condition
called kernicterus
Mental
impairment
Motor dysfunction
Permanent
neurological
damage
Enlarged liver and
spleen
Rapid RBC
production in
hematopoietic
tissues
Release of
immature
nucleated RBCs
Hence
erythroblastosis
fetalis
medicoseacademics@gmail.com
0310-7990649
Incidence in Pregnancies
• First Rh-positive baby usually not affected
• Because sensitization occurs during first pregnancy
• Incidence increases in later pregnancies:
• Second Rh-positive baby about 3% affected
→
• Third baby about 10% affected
→
• Risk rises with each subsequent pregnancy
medicoseacademics@gmail.com
0310-7990649
Treatment of Erythroblastosis Fetalis
• Main treatment: Exchange transfusion
• Procedure:
• Neonate’s Rh-positive blood removed
• Replaced with Rh-negative blood
• Process takes about 1.5 hours
• May be repeated during first weeks of life
• Goals:
• Reduce bilirubin levels
• Prevent kernicterus
medicoseacademics@gmail.com
0310-7990649
Outcome After Treatment
• Transfused Rh-negative cells circulate temporarily
• Infant gradually produces own Rh-positive RBCs
• Maternal antibodies disappear within 6 weeks
• Disease resolves as antibodies are cleared from circulation
medicoseacademics@gmail.com
0310-7990649
Prevention of Erythroblastosis Fetalis
• Prevention uses Rh immunoglobulin (Anti-D antibody)
• Given to Rh-negative pregnant women
• Administered at 28–30 weeks of gestation
• Also given after delivery of Rh-positive baby
• Prevents maternal sensitization to D antigen
medicoseacademics@gmail.com
0310-7990649
Mechanism of Rh Immunoglobulin
• Anti-D antibodies work by:
• Binding to Rh-positive fetal RBCs
• Removing them before maternal immune
system reacts
• Suppressing B-cell antibody production
• Preventing formation of anti-Rh antibodies
• This greatly reduces the risk of hemolytic
disease in future pregnancies.
medicoseacademics@gmail.com
0310-7990649
Hazards of Blood Transfusion
Dr Faiza
MBBS (Best Graduate, AIMC Lahore)
FCPS Physiology,
MHPE (Riphah Int University, Islamabad)
ICMT, CHPE, DHPE (STMU)
MPH (GC University, Faisalabad)
MBA (Virtual University of Pakistan)
medicoseacademics@gmail.com
0310-7990649
Learning Objectives
• Enlist changes occurring in stored blood
• Discuss features and complications of mismatched blood
transfusion
• Describe hazards of blood transfusion
• Elaborate transplantation of tissues and organs
• Explain the process of tissue typing
• Explain prevention of graft rejection by immune suppression
medicoseacademics@gmail.com
0310-7990649
Requirement for Blood Transfusion
• A typical blood bag contains 1 pint of blood (approximately 450 ml)
• Most of the times, 1 pint of blood is transfused at one instant
• Blood transfusions are commonly required for the following
conditions:
1. Anemia (iron deficiency, thalassemia)
2. Hemorrhage (accidental, during surgery)
3. Kidney and liver disorders
4. Cancers
medicoseacademics@gmail.com
0310-7990649
Blood Transfusion Reactions
• Hemolysis
• Acute
• Delayed
• Jaundice
• Acute Kidney Failure
medicoseacademics@gmail.com
0310-7990649
Transfusion Reactions from Mismatched Blood
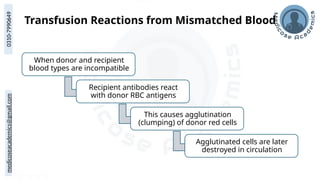
When donor and recipient
blood types are incompatible
Recipient antibodies react
with donor RBC antigens
This causes agglutination
(clumping) of donor red cells
Agglutinated cells are later
destroyed in circulation
medicoseacademics@gmail.com
0310-7990649
Why Donor Cells Are Usually Affected
• Donor plasma becomes diluted in recipient plasma
• This dilution reduces donor antibodies
• Therefore, donor antibodies rarely affect recipient RBCs
• Recipient plasma antibodies remain concentrated
• These antibodies attack donor RBCs
medicoseacademics@gmail.com
0310-7990649
Hemolysis in Transfusion Reactions
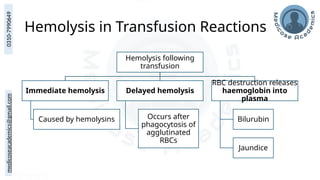
Hemolysis following
transfusion
Immediate hemolysis
Caused by hemolysins
Delayed hemolysis
Occurs after
phagocytosis of
agglutinated
RBCs
RBC destruction releases
haemoglobin into
plasma
Bilurubin
Jaundice
medicoseacademics@gmail.com
0310-7990649
Agglutination in
Transfusion
Reactions
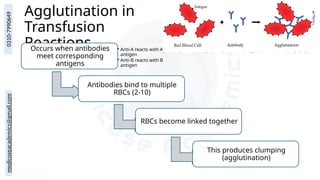
Occurs when antibodies
meet corresponding
antigens
• Anti-A reacts with A
antigen
• Anti-B reacts with B
antigen
Antibodies bind to multiple
RBCs (2-10)
RBCs become linked together
This produces clumping
(agglutination)
medicoseacademics@gmail.com
0310-7990649
Agglutination
Followed
by Hemolysis
Clumped RBCs block
small blood vessels
RBC membranes are
destroyed by:
• Physical distortion
• Phagocytic white blood
cells
Hemoglobin released
into plasma
This process is called
hemolysis
medicoseacademics@gmail.com
0310-7990649
Sometimes
hemolysis occurs
immediately
Antibodies
activate the
complement
system
Complement
forms
membrane
attack complex
Pores form in
RBC membrane
Leads to osmotic
lysis of RBCs
Mainly caused by
IgM antibodies
(hemolysins)
Far less common
than
agglutination
followed by
hemolysis
Acute Hemolysis
in Transfusion
medicoseacademics@gmail.com
0310-7990649
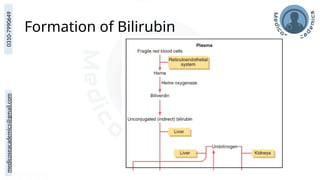
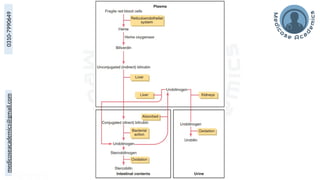
Formation of Bilirubin
medicoseacademics@gmail.com
0310-7990649
medicoseacademics@gmail.com
0310-7990649
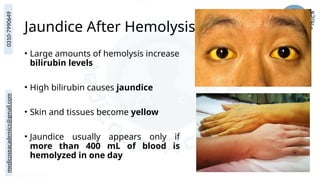
Jaundice After Hemolysis
• Large amounts of hemolysis increase
bilirubin levels
• High bilirubin causes jaundice
• Skin and tissues become yellow
• Jaundice usually appears only if
more than 400 mL of blood is
hemolyzed in one day
medicoseacademics@gmail.com
0310-7990649
Acute Kidney Failure in Transfusion
Reaction
• One of the most dangerous complications is acute kidney
injury
• Can begin within minutes to hours
• May progress to acute renal failure
• Can lead to death if untreated
medicoseacademics@gmail.com
0310-7990649
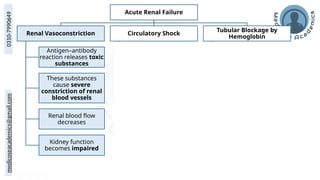
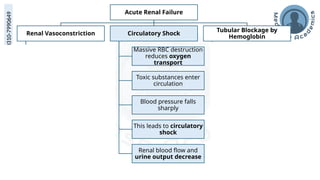
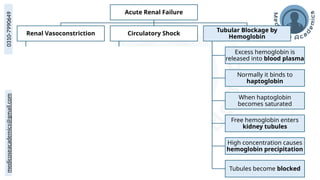
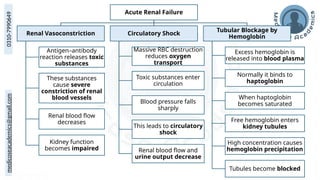
Acute Renal Failure
Renal Vasoconstriction
Antigen–antibody
reaction releases toxic
substances
These substances
cause severe
constriction of renal
blood vessels
Renal blood flow
decreases
Kidney function
becomes impaired
Circulatory Shock
Massive RBC destruction
reduces oxygen
transport
Toxic substances enter
circulation
Blood pressure falls
sharply
This leads to circulatory
shock
Renal blood flow and
urine output decrease
Tubular Blockage by
Hemoglobin
Excess hemoglobin is
released into blood plasma
Normally it binds to
haptoglobin
When haptoglobin
becomes saturated
Free hemoglobin enters
kidney tubules
High concentration causes
hemoglobin precipitation
Tubules become blocked
medicoseacademics@gmail.com
0310-7990649
Acute Renal Failure
Renal Vasoconstriction
Antigen–antibody
reaction releases toxic
substances
These substances
cause severe
constriction of renal
blood vessels
Renal blood flow
decreases
Kidney function
becomes impaired
Circulatory Shock
Massive RBC destruction
reduces oxygen
transport
Toxic substances enter
circulation
Blood pressure falls
sharply
This leads to circulatory
shock
Renal blood flow and
urine output decrease
Tubular Blockage by
Hemoglobin
Excess hemoglobin is
released into blood plasma
Normally it binds to
haptoglobin
When haptoglobin
becomes saturated
Free hemoglobin enters
kidney tubules
High concentration causes
hemoglobin precipitation
Tubules become blocked
medicoseacademics@gmail.com
0310-7990649
Acute Renal Failure
Renal Vasoconstriction
Antigen–antibody
reaction releases toxic
substances
These substances
cause severe
constriction of renal
blood vessels
Renal blood flow
decreases
Kidney function
becomes impaired
Circulatory Shock
Massive RBC destruction
reduces oxygen
transport
Toxic substances enter
circulation
Blood pressure falls
sharply
This leads to circulatory
shock
Renal blood flow and
urine output decrease
Tubular Blockage by
Hemoglobin
Excess hemoglobin is
released into blood plasma
Normally it binds to
haptoglobin
When haptoglobin
becomes saturated
Free hemoglobin enters
kidney tubules
High concentration causes
hemoglobin precipitation
Tubules become blocked
medicoseacademics@gmail.com
0310-7990649
Acute Renal Failure
Renal Vasoconstriction
Antigen–antibody
reaction releases toxic
substances
These substances
cause severe
constriction of renal
blood vessels
Renal blood flow
decreases
Kidney function
becomes impaired
Circulatory Shock
Massive RBC destruction
reduces oxygen
transport
Toxic substances enter
circulation
Blood pressure falls
sharply
This leads to circulatory
shock
Renal blood flow and
urine output decrease
Tubular Blockage by
Hemoglobin
Excess hemoglobin is
released into blood plasma
Normally it binds to
haptoglobin
When haptoglobin
becomes saturated
Free hemoglobin enters
kidney tubules
High concentration causes
hemoglobin precipitation
Tubules become blocked
medicoseacademics@gmail.com
0310-7990649
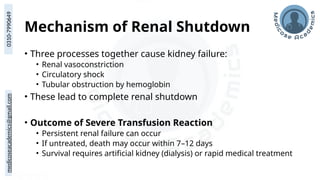
Mechanism of Renal Shutdown
• Three processes together cause kidney failure:
• Renal vasoconstriction
• Circulatory shock
• Tubular obstruction by hemoglobin
• These lead to complete renal shutdown
• Outcome of Severe Transfusion Reaction
• Persistent renal failure can occur
• If untreated, death may occur within 7–12 days
• Survival requires artificial kidney (dialysis) or rapid medical treatment
medicoseacademics@gmail.com
0310-7990649
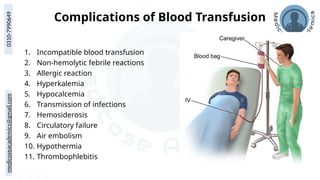
Complications of Blood Transfusion
1. Incompatible blood transfusion
2. Non-hemolytic febrile reactions
3. Allergic reaction
4. Hyperkalemia
5. Hypocalcemia
6. Transmission of infections
7. Hemosiderosis
8. Circulatory failure
9. Air embolism
10. Hypothermia
11. Thrombophlebitis
medicoseacademics@gmail.com
0310-7990649
• To avoid complications of blood transfusion:
1. Crossmatching should be done to rule out ABO and Rh
incompatibility
2. Donor should be screened for transmissible infections
3. Blood should be stored in sterile conditions and at
adequate temperature
4. Whenever possible, fresh blood should be transfused
medicoseacademics@gmail.com
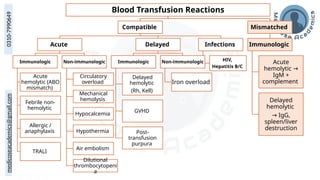
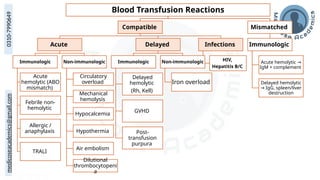
0310-7990649 Blood Transfusion Reactions
Compatible
Acute
Immunologic
Acute
hemolytic (ABO
mismatch)
Febrile non-
hemolytic
Allergic /
anaphylaxis
TRALI
Non-immunologic
Circulatory
overload
Mechanical
hemolysis
Hypocalcemia
Hypothermia
Air embolism
Dilutional
thrombocytopeni
a
Delayed
Immunologic
Delayed
hemolytic
(Rh, Kell)
GVHD
Post-
transfusion
purpura
Non-immunologic
Iron overload
Infections
HIV,
Hepatitis B/C
Mismatched
Immunologic
Acute
hemolytic →
IgM +
complement
Delayed
hemolytic
→ IgG,
spleen/liver
destruction
medicoseacademics@gmail.com
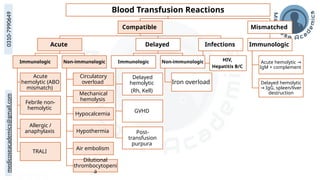
0310-7990649 Blood Transfusion Reactions
Compatible
Acute
Immunologic
Acute
hemolytic (ABO
mismatch)
Febrile non-
hemolytic
Allergic /
anaphylaxis
TRALI
Non-immunologic
Circulatory
overload
Mechanical
hemolysis
Hypocalcemia
Hypothermia
Air embolism
Dilutional
thrombocytopeni
a
Delayed
Immunologic
Delayed
hemolytic
(Rh, Kell)
GVHD
Post-
transfusion
purpura
Non-immunologic
Iron overload
Infections
HIV,
Hepatitis B/C
Mismatched
Immunologic
Acute hemolytic →
IgM + complement
Delayed hemolytic
IgG, spleen/liver
→
destruction
medicoseacademics@gmail.com
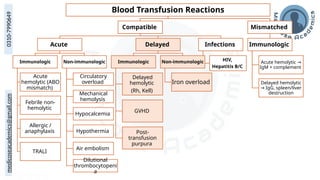
0310-7990649 Blood Transfusion Reactions
Compatible
Acute
Immunologic
Acute
hemolytic (ABO
mismatch)
Febrile non-
hemolytic
Allergic /
anaphylaxis
TRALI
Non-immunologic
Circulatory
overload
Mechanical
hemolysis
Hypocalcemia
Hypothermia
Air embolism
Dilutional
thrombocytopeni
a
Delayed
Immunologic
Delayed
hemolytic
(Rh, Kell)
GVHD
Post-
transfusion
purpura
Non-immunologic
Iron overload
Infections
HIV,
Hepatitis B/C
Mismatched
Immunologic
Acute hemolytic →
IgM + complement
Delayed hemolytic
IgG, spleen/liver
→
destruction
medicoseacademics@gmail.com
0310-7990649 Blood Transfusion Reactions
Compatible
Acute
Immunologic
Acute
hemolytic (ABO
mismatch)
Febrile non-
hemolytic
Allergic /
anaphylaxis
TRALI
Non-immunologic
Circulatory
overload
Mechanical
hemolysis
Hypocalcemia
Hypothermia
Air embolism
Dilutional
thrombocytopeni
a
Delayed
Immunologic
Delayed
hemolytic
(Rh, Kell)
GVHD
Post-
transfusion
purpura
Non-immunologic
Iron overload
Infections
HIV,
Hepatitis B/C
Mismatched
Immunologic
Acute hemolytic →
IgM + complement
Delayed hemolytic
IgG, spleen/liver
→
destruction
medicoseacademics@gmail.com
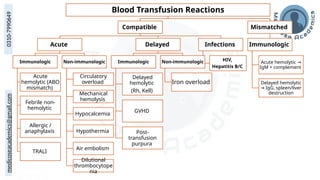
0310-7990649 Blood Transfusion Reactions
Compatible
Acute
Immunologic
Acute
hemolytic (ABO
mismatch)
Febrile non-
hemolytic
Allergic /
anaphylaxis
TRALI
Non-immunologic
Circulatory
overload
Mechanical
hemolysis
Hypocalcemia
Hypothermia
Air embolism
Dilutional
thrombocytope
nia
Delayed
Immunologic
Delayed
hemolytic
(Rh, Kell)
GVHD
Post-
transfusion
purpura
Non-immunologic
Iron overload
Infections
HIV,
Hepatitis B/C
Mismatched
Immunologic
Acute hemolytic →
IgM + complement
Delayed hemolytic
IgG, spleen/liver
→
destruction
medicoseacademics@gmail.com
0310-7990649
Allergic Reaction
• Occurs against the plasma proteins in transfused blood
• Presentation includes itching, rashes, fever
• Treated with antihistamine
medicoseacademics@gmail.com
0310-7990649
Anaphylactic Reaction
• Severe allergic reaction
• Against blood products
• Presentation includes shortness of breath, hypotension,
respiratory arrest, shock
• Treated with epinephrine
medicoseacademics@gmail.com
0310-7990649
Febrile Nonhemolytic Reaction
• Host antibodies against recipient’s HLA antigens and
WBCs
• Presentation includes fever, headaches, chills and flushing
• Treated with corticosteroids
medicoseacademics@gmail.com
0310-7990649
Transfusion-related Acute Lung Injury
(TRALI)
• Acute onset of hypoxemia and pulmonary edema on CXR
• Within 6 hrs of TX without evidence of cardiac failure.
• Primary Suspect:
• Donor antibodies to recipient WBCs
• Biologically active lipids in the lungs causing edema
• Symptoms
• Chills, fever, cough, cyanosis, hypotension, increased difficulty breathing
medicoseacademics@gmail.com
0310-7990649
Graft vs Host Disease (GVHD)
• Donor CD8+ T-Lymphocytes attack recipient (host) tissues.
• Very rare in blood stored 4+ days due to WBC inactivation
• Groups at risk: Immunocompromised patients (Cancer, fetus, neonatal,
bone marrow transplant).
• Prevention: Irradiation of blood products.
medicoseacademics@gmail.com
0310-7990649
Post-transfusion Purpura
• Antibodies to platelet antigens (HP1a)
• Causes abrupt onset of severe thrombocytopenia (platelet count <10,000/l)
• 5-10 days following transfusion.
• Signs:
• Purpura, bleeding, fall in platelet count
• Treatment:
• IVIG, plasmapheresis or corticosteroids; platelet transfusions usually NOT
recommended
medicoseacademics@gmail.com
0310-7990649
Changes Occurring in the Stored Blood:
1. RBCs become rigid, spherical and osmotically fragile
2. Platelets become non-functional and disappear within 24 hrs of collection
3. Decreased ATP
4. Decreased 2,3-DPG
5. Increased potassium
6. Decreased pH
7. Decreased levels of clotting factors V and VIII
8. Increased levels of lactate
medicoseacademics@gmail.com
0310-7990649
Alternatives to Blood Transfusion
• Major Approaches under consideration
• Hemoglobin-based products
• Modified human/bovine/genetically engineered Hb
• Liposome-encapsulated “neo RBCs”
• Synthetic O₂ carriers
• Perfluorocarbons (PFCs)
• Artificial Hb-like molecules
• Stem cell–derived RBCs
• Lab-grown universal donor (O negative)
medicoseacademics@gmail.com
0310-7990649
Transplantation of Tissues
and Organs
Dr Faiza
MBBS (Best Graduate, AIMC Lahore)
FCPS Physiology,
MHPE (Riphah Int University, Islamabad)
ICMT, CHPE, DHPE (STMU)
MPH (GC University, Faisalabad)
MBA (Virtual University of Pakistan)
medicoseacademics@gmail.com
0310-7990649
Transplantation of Tissues and Organs
• Cells of the body contain many antigens
• These antigens are also present on RBCs and other tissues
• When foreign tissue enters the body, the immune system
recognizes it as non-self
• This triggers an immune reaction
• The body may attack transplanted tissue just like bacteria,
viruses, or foreign cells
medicoseacademics@gmail.com
0310-7990649
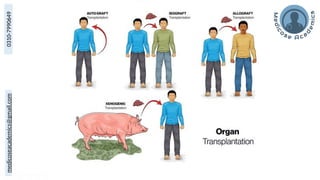
Types of Tissue Grafts
• Based on the source of the transplanted tissue:
• Autograft
• Tissue transferred within the same person
• Isograft
• Transplant between identical twins
• Allograft
• Transplant between two individuals of the same species
• Xenograft
• Transplant between different species
medicoseacademics@gmail.com
0310-7990649
medicoseacademics@gmail.com
0310-7990649
Autologous Blood Transfusion
• Patient’s own blood is collected before elective surgery
• Blood is stored and reinfused during surgery if needed
• Volume and Preparation
• With iron supplementation:
• 1000–1500 mL blood can be collected
• Over a period of about 3 weeks

• Why it is used
• Reduces risk of infectious disease transmission
• Seen in donor (heterologous) transfusions
• Eliminates risk of transfusion reactions
medicoseacademics@gmail.com
0310-7990649
Survival of Transplanted Tissues
• Autografts and isografts
• Cells have same antigens as recipient
• Grafts usually survive permanently
• Xenografts
• Strong immune response occurs
• Graft cells often die within 1 day to 5 weeks unless immune
reaction is suppressed
medicoseacademics@gmail.com
0310-7990649
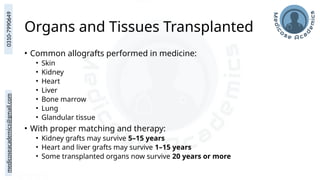
Organs and Tissues Transplanted
• Common allografts performed in medicine:
• Skin
• Kidney
• Heart
• Liver
• Bone marrow
• Lung
• Glandular tissue
• With proper matching and therapy:
• Kidney grafts may survive 5–15 years
• Heart and liver grafts may survive 1–15 years
• Some transplanted organs now survive 20 years or more
medicoseacademics@gmail.com
0310-7990649
Preventing Immune Reactions in
Transplantation
• Transplant rejection occurs because of antigen–antibody
reactions
• Two major approaches help prevent rejection:
• Tissue typing
• Immunosuppressive therapy
medicoseacademics@gmail.com
0310-7990649
Tissue Typing
• The most important antigens involved in graft rejection are:
• Human Leukocyte Antigens (HLA)
• These antigens are present on tissue cell membranes
• Each person has six major HLA antigens
• Around 150 different HLA types exist
• Possible combinations exceed 1 trillion
medicoseacademics@gmail.com
0310-7990649
Importance of HLA Matching
• Even small differences in HLA can
trigger graft rejection
• Exact matching is rare
• Identical twins have identical HLAs
• Therefore grafts between twins are
rarely rejected
• Good matches are often found
between siblings or parents and
children
medicoseacademics@gmail.com
0310-7990649
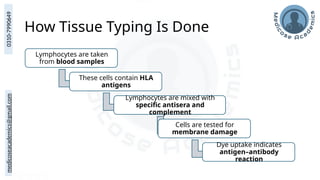
How Tissue Typing Is Done
Lymphocytes are taken
from blood samples
These cells contain HLA
antigens
Lymphocytes are mixed with
specific antisera and
complement
Cells are tested for
membrane damage
Dye uptake indicates
antigen–antibody
reaction
medicoseacademics@gmail.com
0310-7990649
Immunosuppression to Prevent
Rejection
• Suppressing the immune system can prevent graft rejection
• T cells play the major role in destroying grafted tissue
• Therefore treatment mainly targets T-cell activity
medicoseacademics@gmail.com
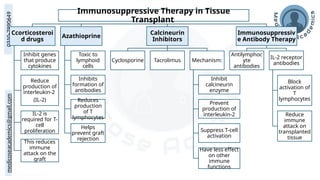
0310-7990649 Immunosuppressive Therapy in Tissue
Transplant
Ccorticosteroi
d drugs
Inhibit genes
that produce
cytokines
Reduce
production of
interleukin-2
(IL-2)
IL-2 is
required for T-
cell
proliferation
This reduces
immune
attack on the
graft
Azathioprine
Toxic to
lymphoid
cells
Inhibits
formation of
antibodies
Reduces
production
of T
lymphocytes
Helps
prevent graft
rejection
Calcineurin
Inhibitors
Cyclosporine Tacrolimus Mechanism:
Inhibit
calcineurin
enzyme
Prevent
production of
interleukin-2
Suppress T-cell
activation
Have less effect
on other
immune
functions
Immunosuppressiv
e Antibody Therapy
Antilymphoc
yte
antibodies
IL-2 receptor
antibodies
Block
activation of
T
lymphocytes
Reduce
immune
attack on
transplanted
tissue
medicoseacademics@gmail.com
0310-7990649
Risks of Immunosuppressive Therapy
• Increased bacterial infections
• Increased viral infections
• Higher risk of cancer
• Because the immune system normally destroys early cancer cells
medicoseacademics@gmail.com
0310-7990649
Dr Faiza, FCPS Physiology
Thank You
References:
• Guyton, A. C., & Hall, J. E. (2021). Textbook of Medical Physiology (15th ed., Chapter 36:
Blood Types, Transfusion, and Tissue and Organ Transplantation). Philadelphia, PA: Elsevier.
• Barrett, K. E., Barman, S. M., Brooks, H. L., & Yuan, J. X.-J. (2019). Ganong’s Review of Medical
Physiology (26th ed., Chapter 31: Blood as a Circulatory Fluid & the Dynamics of Blood &
Lymph Flow). New York, NY: McGraw-Hill Education.
• Sherwood, L. (2015). Human Physiology: From Cells to Systems (9th ed., Chapter 11: Blood).
Boston, MA: Cengage Learning.