Page | 1
INDEX
SL. No. Topic Name Page
No.
01 Introduction 03
02 Bioequivalence Studies 03-04
03 Method of performing Bioequivalence studies 04-05
04 Research 05-06
05 Branded Drugs & Generic drugs.
06 Importance of Research 06
07 Clinical research 06
08 Purposes of clinical research 07
09 Bioequivalence studies of drugs prescribed mainly for women 07
10 Sex dependent pharmacokinetics and bioequivalence--time for a
change
08
11 The role of metabolites in bioequivalence 08-09
12 Metabolites and bioequivalence: past and present 09-10
13 Micro dialysis sampling for investigations of bioavailability and
bioequivalence of topically administered drugs: current state and
future perspectives
10-11
14 Bioequivalence studies of pharmaceutical preparations 11
15 Variability and impact on design of bioequivalence studies 11-12
16 New questions regarding bioequivalence of levothyroxine
preparations: a clinician's response
12
17 Bioequivalence requirements in the European Union: critical
discussion
12-13
18 Interactions between active pharmaceutical ingredients and
excipients affecting bioavailability: impact on bioequivalence
13
19 Analysis of risk factors in human bioequivalence study that incur
bioinequivalence of oral drug products
14-15
20 Analysis of Intra- and Intersubject Variability in Oral Drug
Absorption in Human Bioequivalence Studies of 113 Generic
Products
15
Page | 2
21 Computer simulations of bioequivalence trials: selection of
design and analyte in BCS drugs with first-pass hepatic
metabolism: Part II. Non-linear kinetics
15-16
22 Bioequivalence of generic alendronate sodium tablets (70 mg) to
Fosamax® tablets (70 mg) in fasting, healthy volunteers: a
randomized, open-label, threeway, reference-replicated crossover
study
16-17
23 Bioequivalence Study of Amitriptyline Hydrochloride Tablets in
Healthy Chinese Volunteers Under Fasting and Fed Conditions
17-18
24 Bioequivalence of a Generic Nateglinide Formulation in Healthy
Chinese Volunteers under Fasting and Fed Conditions: A
Randomized, Open-Label, Double-Cycle, Double-Crossover
Study
18
25 Bioequivalence Study of Palbociclib Capsules in Healthy
Chinese Subjects Under Fasting and Fed Conditions
18-19
26 Bioequivalence study of ant diabetic activity between two
marketed formulations of metformin on glucocorticoid induces
hyperglycemia in rabbit
19-20
27 Bioequivalence study of omeprazole and sodium bicarbonate
dry suspensions
21
28
Bioequivalence study of two marketed Bupropion HCL named
Budeprion XL 300 mg Wellbutrin XL 300 mg by FDA
22
29 Bioequivalence study of zonisamide 100 and 300 mg and
immediate-release reference capsules
22
26 Conclusion 22-23
Page | 3
Introduction
Development of generic drugs is one of the effective strategies to increase patient access to
therapeutic drugs. Regulatory agencies have adopted an abbreviated approval process for generic
drugs. Demonstration of bioequivalence (BE) is required for approval of generic drugs, instead
of repeating clinical trials on safety and efficacy. As a result of this abbreviated approval
process, generic drugs can be supplied at lower cost.
Bioequivalence is the biochemical similarity of two (or more) drugs that share the same active
ingredient(s) and desired outcome(s) for patients.
Pharmacokinetic studies must be done to determine whether a commercially available brand and
a potential generic version share core attributes. Bioequivalence or pharmaceutical equivalence
must be present showing that the two drugs release the active ingredient into the bloodstream at
the same amount, the same rate, and have the same quality.
The scientific concept of BE is defined uniformly across various regulatory agencies BE is
achieved when the bioavailability of two drugs “lie within acceptable predefined limits” to
ensure “similarity in terms of safety and efficacy, thus demonstrating “the absence of significant
difference in the rate and extent of absorption under similar experimental conditions”
BE can be demonstrated in vivo and in vitro, although in vitro assessment has limited
acceptance, i.e., only for drugs with high solubility and A standard approach for demonstrating
BE is a two-way crossover (2 × 2) clinical trial conducted in healthy subjects.
Although the concept of BE is accepted globally, regulatory requirements and standards for BE
are not consistent among countries. The difference is observed even among the members of
International Council for Harmonization of Technical Requirements for Pharmaceuticals for
Human Use (ICH). The difference lies in terms of recommended study design, method for
pharmacokinetic (PK) parameter estimation, and modification ofBE criteria for highly variable
drugs.
Bioequivalence Studies
Bioequivalence (BE) studies are a special type of studies designed to compare the (i.e. the
amount of drug that enters systemic circulation) of two products that are using the same active
ingredient or molecule and to verify how similar they are to each other.
Once a pharmaceutical company develops a new drug (i.e. an innovator drug) which is based on
a newly discovered active ingredient or molecule, that company will apply for a patent that will
give it the complete control and production of that molecule. However, the patent only lasts for a
Page | 4
certain amount of time (20 years in Canada for example). , the Pharmaceutical company must
demonstrate the drug’s safety and efficacy through clinical studies of Phase I, II and III. The aim
of the company is to get their drug on the market as quickly as possible so that the marketed drug
can be under patent protection as long as possible. That way, the pharmaceutical company has no
competition for that specific drug and can generate revenues quicker.
Once that patent expires, other pharmaceutical companies can start producing their own version
of the innovator drug (i.e. a generic drug). To be marketed, a generic drug must have the same
effects (i.e. same absorption, distribution, metabolism and excretion) as the innovator one. In
other words, they must be bioequivalent.
The U.S. Food and Drug Administration (FDA) regulates and approves drugs to ensure they
meet the FDA's bioequivalence standards. When assessing how well a generic drug works,
scientists evaluate its bioequivalence to the name-brand version.
Criteria:
The test and reference drug formulation must contain:
 Pharmaceutically equivalent drug.
 At the same dose strength.
 At a similar dosage form. (immediate/controlled release)
 Given by the same route of administration.
 Approval from institutional review board of the testing unit.
 Consists of both single dose and multiple dose studies.
Branded drug/Innovator drug:
The company that discovered a new drug would submit an application for patent protection to
stop other companies from making and marketing the drug. In order to recoup its investment and
turn a profit during this 20-year patent pending period, the company will manufacture and
market the drug under a brand name. Over time, people start to associate this name with the drug.
However, other businesses are permitted to make a comparable drug once the patent expires. It is
the source of drug brand and generic names.
Generic drug:
A generic drug is a medication created to be the same as an already marketed brand-name drug
in dosage form, safety, strength, route of administration, quality, performance characteristics,
and intended use. These similarities help to demonstrate bioequivalence, which means that a
generic medicine works in the same way and provides the same clinical benefit as the brand-
Page | 5
name medicine. In other words, you can take a generic medicine as an equal substitute for its
brand-name counterpart. Any generic medicine must perform the same in the body as the brand-
name medicine.
It must be the same as a brand-name medicine in dosage, form and route of administration,
safety, effectiveness, strength, and labeling (with certain limited exceptions). It must also meet
the same high standards of quality and manufacturing as the brand-name product, and it must
be and quality, taken and used in the same way as well. This standard applies to all generic
medicines. Generic medicines use the same active ingredients as brand-name medicines and
work the same way, so they have the same risks and benefits as the brand-name medicines.
Method of performing Bioequivalence studies
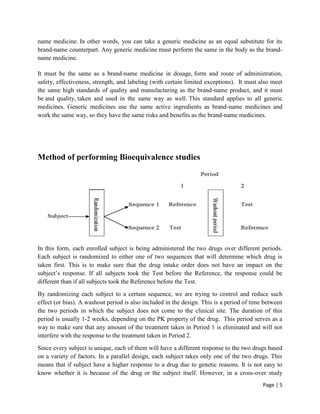
In this form, each enrolled subject is being administered the two drugs over different periods.
Each subject is randomized to either one of two sequences that will determine which drug is
taken first. This is to make sure that the drug intake order does not have an impact on the
subject’s response. If all subjects took the Test before the Reference, the response could be
different than if all subjects took the Reference before the Test.
By randomizing each subject to a certain sequence, we are trying to control and reduce such
effect (or bias). A washout period is also included in the design. This is a period of time between
the two periods in which the subject does not come to the clinical site. The duration of this
period is usually 1-2 weeks, depending on the PK property of the drug. This period serves as a
way to make sure that any amount of the treatment taken in Period 1 is eliminated and will not
interfere with the response to the treatment taken in Period 2.
Since every subject is unique, each of them will have a different response to the two drugs based
on a variety of factors. In a parallel design, each subject takes only one of the two drugs. This
means that if subject have a higher response to a drug due to genetic reasons. It is not easy to
know whether it is because of the drug or the subject itself. However, in a cross-over study
Page | 6
design, the big advantage is that each subject acts as its own control. In other words, unlike a
parallel design where, the effect of a drug on each subject is reduced to the fact that they all are
taking the two drugs. We therefore have less subject related bias when we want to compare the
response to the two formulations.
By comparing how similar the two formulations are, we are looking at the amount of active
ingredient in the blood or plasma. For example, the active ingredient in common pain
medications is ibuprofen. To measure the amount, we use the concentration of active ingredient
in the blood or plasma. The figure below, shows an example of how much active ingredient is in
the blood after administration.
Figure: Bioequivalence of a drug after oral administration
We can see that, at first, the concentration of active ingredient in the plasma goes up quite
quickly until it reaches a maximum concentration or Cmax. Afterward, the concentration slowly
goes down until it is almost not present anymore. The time at which the Cmax is attained is
called Tmax. This type of curve will be observed for each subject and each formulation. We
want those curves to be similar between the generic and innovator treatment. If we have that and
after some statistical calculations, then we can say that the two treatments are similar or
bioequivalent.
Research
Research is "creative and systematic work undertaken to increase the stock of knowledge". It
involves the collection, organization and analysis of evidence to increase understanding of a
topic, characterized by a particular attentiveness to controlling sources of bias and error. These
activities are characterized by accounting and controlling for biases. A research project may be
an expansion on past work in the field. To test the validity of instruments, procedures, or
experiments, research may replicate elements of prior projects or the project as a whole.
Page | 7
The primary purposes of basic research (as opposed to applied research) are documentation,
discovery, interpretation, and the research and development (R&D) of methods and systems for
the advancement of human knowledge.
Importance of Research
Research is important because it helps us understand the world around us. It allows us to test
hypotheses and make predictions about how things work. Research also helps us to find new
solutions to problems and to improve existing ones.
Without research, we would not have many of the conveniences that we enjoy today. For
example, research led to the development of the telephone, the automobile, and the computer. It
also helps us to understand the causes of diseases and to find new treatments for them.Research
is essential for ensuring that our knowledge is up-to-date and accurate. It allows us to build on
what we already know and to correct errors or misconceptions. Research is also necessary for
keeping up with advances in technology and for developing new technologies.
Clinical research
Clinical research is the comprehensive study of the safety and effectiveness of the most
promising advances in patient care. Clinical research is different than laboratory research. It
involves people who volunteer to help us better understand medicine and health. Lab research
generally does not involve people — although it helps us learn which new ideas may help
people.
Every drug, device, tool, diagnostic test, technique and technology used in medicine today was
once tested in volunteers who took part in clinical research studies.
At Johns Hopkins Medicine, we believe that clinical research is key to improve care for people
in our community and around the world. Once you understand more about clinical research, you
may appreciate why it’s important to participate — for yourself and the community.
Page | 8
Purposes of clinical research
Typically, clinical research entails a thorough examination of people, data, and/or tissue samples.
This allows those involved to find new methods of…
 Detection
 Diagnosis
 Treatment
 Prevention
Ultimately, the goal is to increase medical knowledge and improve patient care.
Due to the importance of clinical research, doctors and scientists must perform a systematic
investigation when collecting information. There are specific protocols that must be followed,
such as obtaining regulatory approvals and taking steps to ensure legal and ethical compliance.
Various clinical researches are available in bioequivalence studies for developing the
pharmaceutical sector in various ways. Some research work about bioequivalence studies are
given below:
Bioequivalence studies of drugs prescribed mainly for women
The basic components of pharmacokinetics are absorption, distribution, metabolism, and
excretion. During pregnancy there may be changes in one or many of these components. Early
drug studies did not include a representative proportion of women, however, researchers as well
as regulators agree that studies on the sex differences in the disposition of drugs are important,
but at what stage in the clinical trial process.
Except for drugs used only in women, such as those for estrogen-dependent breast cancer,
caution prevails and the differences are usually studied at phase 3. Studies in pregnant women
are much rarer but some do get done, e.g., with antivirals and anti-malarials, where the positive
risk-benefit of these agents is the likelihood that fetal transfer of these drugs might help protect
the fetus.
Women are being included in pharmacokinetic studies for new drug applications in accordance
with the International Conference on Harmonization of Technical Requirements for Registration
of Pharmaceuticals for Human Use (ICH), U.S. Food and Drug Administration (FDA), and
Health Canada (HC) guidances. A new look at bioequivalence studies, to compare results in men
and women, would help determine if interactions of formulation and gender are a problem.
Page | 9
Sex dependent pharmacokinetics and bioequivalence--time for a change
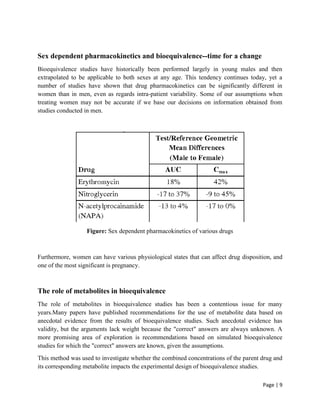
Bioequivalence studies have historically been performed largely in young males and then
extrapolated to be applicable to both sexes at any age. This tendency continues today, yet a
number of studies have shown that drug pharmacokinetics can be significantly different in
women than in men, even as regards intra-patient variability. Some of our assumptions when
treating women may not be accurate if we base our decisions on information obtained from
studies conducted in men.
Figure: Sex dependent pharmacokinetics of various drugs
Furthermore, women can have various physiological states that can affect drug disposition, and
one of the most significant is pregnancy.
The role of metabolites in bioequivalence
The role of metabolites in bioequivalence studies has been a contentious issue for many
years.Many papers have published recommendations for the use of metabolite data based on
anecdotal evidence from the results of bioequivalence studies. Such anecdotal evidence has
validity, but the arguments lack weight because the "correct" answers are always unknown. A
more promising area of exploration is recommendations based on simulated bioequivalence
studies for which the "correct" answers are known, given the assumptions.
This method was used to investigate whether the combined concentrations of the parent drug and
its corresponding metabolite impacts the experimental design of bioequivalence studies.
Page | 10
Enalpril and sildenafil were selected to assess bioequivalence as both drugs have active
metabolites.
The bioequivalence study of enalpril was conducted under fasting conditions, while the
bioequivalence assessment of sildenafil was conducted under both fasting and fed conditions.
For the three studies, the bioequivalence criteria of 80-125% was applied to assess the parent
compounds alone, the active metabolites alone, and both the parent drugs and the active
metabolites.
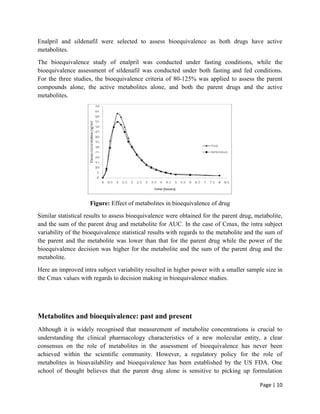
Figure: Effect of metabolites in bioequivalence of drug
Similar statistical results to assess bioequivalence were obtained for the parent drug, metabolite,
and the sum of the parent drug and metabolite for AUC. In the case of Cmax, the intra subject
variability of the bioequivalence statistical results with regards to the metabolite and the sum of
the parent and the metabolite was lower than that for the parent drug while the power of the
bioequivalence decision was higher for the metabolite and the sum of the parent drug and the
metabolite.
Here an improved intra subject variability resulted in higher power with a smaller sample size in
the Cmax values with regards to decision making in bioequivalence studies.
Metabolites and bioequivalence: past and present
Although it is widely recognised that measurement of metabolite concentrations is crucial to
understanding the clinical pharmacology characteristics of a new molecular entity, a clear
consensus on the role of metabolites in the assessment of bioequivalence has never been
achieved within the scientific community. However, a regulatory policy for the role of
metabolites in bioavailability and bioequivalence has been established by the US FDA. One
school of thought believes that the parent drug alone is sensitive to picking up formulation
Page | 11
differences, whereas another school of thought believes that establishing bioequivalence criteria
on all the species that contribute to safety and efficacy is the only way to ensure the switchability
of two products. In this paper, a brief review of the pharmacokinetics of metabolites under
different scenarios is presented and the history of the role of metabolites in the assessment of
bioequivalence is summarized. Relevant examples from the literature illustrating conflicting
opinions on the need for the measurement of metabolites in bioequivalence studies are given.
Cases from the literature in which the parent drug is able to meet the 90% confidence intervals
while the metabolite(s) fail to do so, and vice versa, are presented to illustrate the difficulty in
choosing the pertinent entity to measure. The relevant current US FDA policy and guidelines
related to bioavailability and bioequivalence are discussed and contrasted with the rules and
regulations applicable in Canada and Europe.
Micro dialysis sampling for investigations of bioavailability and
bioequivalence of topically administered drugs: current state and future
perspectives
Micro dialysis (MD) in the skin is a unique technique for in vivo sampling of topically as well as
systemically administered drugs at the site of action, e.g. sampling the unbound tissue
concentrations in the dermis and subcutaneous tissue. MD as a research method has undergone
significant development, improvement and validation during the last decade and has proved to be
a versatile, safe and valuable tool for pharmacokinetic and pharmacodynamics studies.
Figure: Micro dialysis sampling for investigations of bioavailability and bioequivalence
This review gives an overview of the current state and future perspectives of dermal MD
sampling. Methodological issues such as choice of instrumentation, calibration and experimental
Page | 12
procedures are discussed along with the analytical considerations necessary for successful
sampling. Clinical MD studies in the skin are reviewed with emphasis on pharmacokinetic
studies of topically applied drugs with or without impairment of skin barrier function by skin
disease or barrier perturbation. A comparison between MD and other tissue sampling techniques
reveals the advantages and limitations of the method. Subsequently, an in-depth discussion of the
application of MD for the evaluation of bioavailability and bioequivalence of topical
formulations is concluded by the current regulatory point of view. The future perspective
includes further expansion and validation of the use of MD in the experimental and clinical
setting as well as in the optimization of the method for regulatory purposes, i.e. the
commercialization of bioequivalent, generic drug products.
Bioequivalence studies of pharmaceutical preparations
Bioequivalence studies are very important for the development of a pharmaceutical preparation
in the pharmaceutical industry. Their rationale is the monitoring of pharmacokinetic and
pharmacodynamic parameters after the administration of tested drugs. The target of such study is
to evaluate the therapeutic compatibility of tested drugs (pharmaceutical equivalents or
pharmaceutical alternatives). The importance of bioequivalence studies is increasing also due to
the large growth of the production and consumption of generic products. Generic products
represent approximately 50 % of the whole consumption in many European countries and USA.
The search output of bioequivalence study is together with the pharmaceutical quality data of
medical product one of the main part of the registration file submitted to a national regulatory
authorities. The registration of generic products does not demand complicated and expensive
clinical study contrary to original product.
The comparison of the original and the generic product via bioequivalence study is suggested as
sufficient. The aim of this article is to provide to a medical public a summary about the types of
bioequivalence studies, their range, rules of their practise and let them gain their own attitude to
this question.
Variability and impact on design of bioequivalence studies
In 2008, the European Agency for the Evaluation of Medicinal Products released a draft
guidance on the investigation of bioequivalence for immediate release dosage forms with
systemic action to replace the former guidance of a decade ago. Revisions of the regulatory
guidance are based upon many questions over the past years and sometimes continuing scientific
discussions on the use of the most suitable statistical analysis methods and study designs,
particularly for drugs and drug products with high within-subject variability. Although high
within-subject variability is usually associated with a coefficient of variation of 30% or more,
new approaches are available in the literature to allow a gradual increase and a levelling off of
Page | 13
the bioequivalence limits to some maximum wider values (e.g. 75-133%), dependent on the
increase in the within-subject variability. The two-way, cross-over single dose study measuring
parent drug is still the design of first choice. A partial replicate design with repeating the
reference product and scaling the bioequivalence for the reference variability are proposed for
drugs with high within-subject variability. In case of high variability, more regulatory authorities
may accept a two-stage or group-sequential bioequivalence design using appropriately adjusted
statistical analysis. This review also considers the mechanisms why drugs and drug products may
exhibit large variability. The physiological complexity of the gastrointestinal tract and the
interaction with the physicochemical properties of drug substances may contribute to the
variation in plasma drug concentration-time profiles of drugs and drug products and to variability
between and within subjects. A review of submitted bioequivalence studies at the Food and Drug
Administration's Office of Generic Drugs over the period 2003-2005 indicated that extensive
pre-systemic metabolism of the drug substance was the most important explanation for
consistently high variability drugs, rather than a formulation factor. These scientific efforts are
expected to further lead to revisions of earlier regulatory guidance in other regions as is the
current situation in Europe.
New questions regarding bioequivalence of levothyroxine preparations: a
clinician's response
A recent decision by the Food and Drug Administration (FDA) to declare various brands of
levothyroxine bioequivalent has provoked objections from several physicians' organizations.
These organizations assert that the method of testing bioequivalence is flawed, and that
indiscriminate switching among preparations could lead to serious instances of undertreatment
and overtreatment of hypothyroid patients. In this review we first list common indications for
thyroid hormone administration, distinguishing its use as replacement therapy in hypothyroidism
from its use to suppress thyrotrophic (TSH) secretion in cases of thyroid cancer, nodules, and
goiter. The dangers associated with changing to a preparation with different bioavailability are
summarized, noting the particular danger of giving a more active preparation to a patient
receiving TSH-suppressive doses of levothyroxine. However, these dangers are part of a larger
problem: there are data showing that large numbers of patients are already receiving an improper
dosage of levothyroxine, as judged from measurements of serum TSH. The recent history of
FDA actions concerning levothyroxine bioequivalence and the arguments of those in
disagreement are summarized. The immediate response to these problems should be better
education of both patients and physicians. It is also recommended that there be further discussion
of the problems in determining bioequivalence, and that consideration be given to more accurate
and clinically relevant methods. Such methods should include assessment of the changes in TSH
induced by each preparation in thyrotrophic patients.
Page | 14
Bioequivalence requirements in the European Union: critical discussion
The aim of the present paper is to summarize the revised European Union (EU) Guideline on the
Investigation of Bioequivalence and to discuss critically with respect to previous European
requirements and present US Food and Drug Administration guidelines its more relevant
novelties such as the following: in order to facilitate the development of generic medicinal
products, the EU guideline includes the eligibility for Bio pharmaceutics Classification System
(BCS)-based bio waivers not only for BCS class I drugs but also for class III drugs with tighter
requirements for dissolution and excipient composition. The permeability criterion of BCS
classification has been substituted with human absorbability, as per the Biopharmaceutical Drug
Disposition Classification System. The widening of the acceptance range for C (max) is possible
only for highly variable reference products with an additional clinical justification. This scaled
widening is carried out with a proportionality constant of 0.760 which is more conservative than
the FDA approach and maintains the consumer risk at a 5% level when the intra-subject CV is
close to 30%, due to the smooth transition between the scaled and the constant criteria. The
guideline allows for the possibility of two-stage designs to obtain the necessary information on
formulation differences and variability from interim analyses as a part of the pivotal
bioequivalence study, instead of undertaking pilot studies. The guideline also specifies that the
statistical analyses should be performed considering all factors as fixed, which has implications
in the case of replicate designs.
Interactions between active pharmaceutical ingredients and excipients
affecting bioavailability: impact on bioequivalence
The aim of the present paper is to illustrate the impact that excipients may have on the
bioavailability of drugs and to review existing US-FDA, WHO and EMA regulatory guidelines
on this topic. The first examples illustrate that small amounts of sorbitol (7, 50 or 60mg) affect
the bioavailability of risperidone, a class I drug, oral solution, in contrast to what is stated in the
US-FDA guidance. Another example suggests, in contrast to what is stated in the US-FDA BCS
biowaivers guideline, that a small amount of sodium lauryl sulphate (SLS) (3.64mg) affects the
bioavailability of risperidone tablets, although the reference product also includes SLS in an
amount within the normal range for that type of dosage form. These factors are considered
sufficient to ensure that excipients do not affect bioavailability according to the WHO guideline.
The alternative criterion, defined in the WHO guideline and used in the FIP BCS biowaivers
monographs, that asserts that excipients present in generic products of the ICH countries do not
affect bioavailability if used in normal amounts, is shown to be incorrect with an example of
alendronate (a class III drug) tablets, where 4mg of SLS increases bioavailability more than 5-
fold, although a generic product in the USA contains SLS. Finally, another example illustrates
that a 2mg difference in SLS may affect bioavailability of a generic product of a class II drug,
even if SLS is contained in the comparator product, and in all cases its amount was within the
Page | 15
normal range. Therefore, waivers of in vivo bioequivalence studies (e.g., BCS biowaivers,
waivers of certain dosage forms in solution at the time of administration and variations in the
excipient composition) should be assessed more cautiously.
Analysis of risk factors in human bioequivalence study that incur
bioinequivalence of oral drug products
In the study of human bioequivalence (BE), newly developed oral products sometimes fail to
prove BE with a reference product due to the high variability in pharmacokinetic (PK)
parameters after oral absorption. In this study, risk factors that incur bioinequivalence in BE
study were analyzed by applying the Biopharmaceutics Classification System (BCS). Forty-four
generic products were selected from a database of BE studies in the past 10 years at Towa
Pharmaceutical Co., Ltd. (Osaka, Japan), and 90% confidence interval (CI) of AUC and C(max)
in human BE study for all products were converted into coefficient of variation (CV(90)). Then,
the required number of subjects to confirm BE was estimated from the 90% CI in human BE
study of new products. It was found that both the permeability of drugs to human intestinal
membrane (P(eff)) and the dose number calculated from their water solubility did not correlate
well to CV(90) and the estimated subject number in human BE study, suggesting the
contribution of other factors to cause the variability in oral drug absorption.
Figure: Analysis of risk factors in human bioequivalence study that incur bioinequivalence of
oral drug products
Page | 16
As the PK parameter of drugs, the value of AUC/dose was calculated and plotted against CV(90)
and the estimated subject number by classifying drugs into 4 BCS classes. For drugs in classes 1
and 3, AUC/dose gave a clear criterion to distinguish the drugs with a high risk of
bioinequivalence, where drugs with low AUC/dose showed high CV(90) and large number of
subjects. It was suggested that the high metabolic clearance (for class 1 drug) and low oral
absorption (for class 3 drug) could be significant factors to incur bioinequivalence in human BE
study, although for drugs in classes 2 and 4, clear factors were not defined. Consequently, for
drugs in BCS classes 1 and 3, risks in human BE study to incur bioinequivalence could be
predicted by calculating the AUC/dose. In the case of generic drugs, since the parameter of
AUC/dose is available before initiating human BE study, this finding is expected to promote an
efficient and cost-saving strategy for the development of oral drug products.
Analysis of Intra- and Intersubject Variability in Oral Drug Absorption in
Human Bioequivalence Studies of 113 Generic Products
In this study, the data of 113 human bioequivalence (BE) studies of immediate release (IR)
formulations of 74 active pharmaceutical ingredients (APIs) conducted at Sawai Pharmaceutical
Co., Ltd., was analyzed to understand the factors affecting intra- and intersubject variabilities in
oral drug absorption. The ANOVA CV (%) calculated from area under the time-concentration
curve (AUC) in each BE study was used as an index of intrasubject variability (Vintra), and the
relative standard deviation (%) in AUC was used as that of intersubject variability (Vinter).
Although no significant correlation was observed between Vintra and Vinter of all drugs, Vintra
of class 3 drugs was found to increase in association with a decrease in drug permeability
(P(eff)). Since the absorption of class 3 drugs was rate-limited by the permeability, it was
suggested that, for such drugs, the low P(eff) might be a risk factor to cause a large intrasubject
variability. To consider the impact of poor water solubility on the variability in BE study, a
parameter of P(eff)/Do (Do; dose number) was defined to discriminate the solubility-limited and
dissolution-rate-limited absorption of class 2 drugs. It was found that the class 2 drugs with a
solubility-limited absorption (P(eff)/Do < 0.149 × 10(-4) cm/s) showed high intrasubject
variability. Furthermore, as a reason for high intra- or intersubject variability in AUC for class 1
drugs, effects of drug metabolizing enzymes were investigated. It was demonstrated that
intrasubject variability was high for drugs metabolized by CYP3A4 while intersubject variability
was high for drugs metabolized by CYP2D6. For CYP3A4 substrate drugs, the Km value
showed the significant relation with Vintra, indicating that the affinity to the enzyme can be a
parameter to predict the risk of high intrasubject variability. In conclusion, by analyzing the in
house data of human BE study, low permeability, solubility-limited absorption, and high affinity
to CYP3A4 are identified as risk factors for high intrasubject variability in oral drug absorption.
This information is of importance to design the human BE study for oral drug products
containing APIs with a risk of large intrasubject variability in oral absorption.
Page | 17
Computer simulations of bioequivalence trials: selection of design and analyte
in BCS drugs with first-pass hepatic metabolism: Part II. Non-linear kinetics
The objective of this work is to use a computer simulation approach to define the most sensitive
analyte and study design of the in vivo bioequivalence study for all types of
BiopharmaceuticsClassification System (BCS) drugs undergoing first-pass hepatic metabolism
under non-linear conditions. A semi-physiological model was developed in NONMEM VI to
simulate bioequivalence trials. Eight classes from class I to IV BCS drugs (with high or low
intrinsic clearance) in two variability scenarios (high-low) and in six drug products of decreasing
quality were simulated in non-linear conditions to complete a total of 96 scenarios that were
tested in single dose and steady state studies and compared with the previous results obtained
under linear conditions. Parent drug in single dose is the most sensitive analyte and study design
for bioequivalence trials in almost all the studied scenarios. However, this general rule has an
exception not only in drugs with low permeability (class III and IV) and low intrinsic clearance,
for which parent drug in steady state showed differences in the rate of exposure (Cmax) and also
in some occasions in the extent of absorption (AUC), that are not reflected with the same
sensitivity in the single dose scenario, but it could also be possible for Cmax in class III drugs
with high intrinsic clearance. Metabolite data shows less sensitivity detect differences in
biopharmaceutics quality in most of the scenarios or it gives the same information as the parent
compound.
Figure: Computer simulations of bioequivalence trials
Page | 18
Bioequivalence of generic alendronate sodium tablets (70 mg) to Fosamax®
tablets (70 mg) in fasting, healthy volunteers: a randomized, open-label, three-
way, reference-replicated crossover study
The aim of this study was to evaluate the bioequivalence of a generic product 70 mg alendronate
sodium tablets with the reference product Fosamax® 70 mg tablet.
A single-center, open-label, randomized, three-period, three-sequence, reference-replicated
crossover study was performed in 36 healthy Chinese male volunteers under fasting conditions.
In each study period, the volunteers received a single oral dose of the generic or reference
product (70 mg). Blood samples were collected at pre-dose and up to 8 h after administration.
The bioequivalence of the generic product to the reference product was assessed using the US
Food and Drug Administration (FDA) and European Medicines Agency (EMA) reference-scaled
average bioequivalence (RSABE) methods.
Bioequivalence study of Amitriptyline Hydrochloride tablets in healthy
Chinese volunteers under fasting and fed conditions
This study compares the pharmacokinetic and safety profiles between a new generic and a
branded reference formulation of amitriptyline hydrochloride tablets, and assesses the
bioequivalence of the two products in healthy Chinese volunteers to obtain sufficient evidence
for the marketing approval of the generic drug.
A randomized, open-label, two-period crossover study (clinicaltrials.gov, NCT03646526) was
conducted under both fasting and fed conditions in healthy Chinese volunteers (24
subjects/condition). Eligible subjects randomly received a single 25 mg dose of either the test or
the reference formulation, followed by a 3-week washout period. Blood samples were collected
until 144 h following administration. The pharmacokinetic parameters were acquired based on
the concentration-time profiles, including the areas under the plasma concentration-time curve
(AUC0-t, AUC0-∞), the peak plasma concentration (Cmax), the time to achieve Cmax (Tmax),
and the elimination half-life (t1/2). The geometric mean ratios (GMRs) and the corresponding
90% confidence intervals (CIs) of amitriptyline were acquired for bioequivalence analysis, and
values of these parameters for nortriptyline were used for comparison of therapeutic outcomes.
Safety assessments included laboratory tests, physical examination, vital signs, and incidence of
adverse events (AEs).
Page | 19
Figure: Bioequivalence study of Amitriptyline Hydrochloride
This study demonstrated that the generic and reference products were well tolerated by the
subjects and bioequivalent, according to the rate and extent of the drug absorption.
Bioequivalence of a Generic Nateglinide Formulation in Healthy Chinese
Volunteers under Fasting and Fed Conditions: A Randomized, Open-Label,
Double-Cycle, Double-Crossover Study
Nateglinide or N-(trans-4-isopropylcyclohexyl-1-carbonyl)-D-phenylalanine is a drug with a
rapid hypoglycemic effect that is mainly used in the treatment of type 2 diabetes. Very few
studies have assessed bioequivalence based on feeding status. This study aimed to assess the
pharmacokinetic bioequivalence and safety of nateglinide-containing tablets (0.12 g) in healthy
Chinese volunteers under fasting and fed conditions.
The studies were performed in 2017-2018 in the Phase I Clinical Trial Ward of the Affiliated
Hospital of Liaoning University of Traditional Chinese Medicine, China. Eligible Chinese
volunteers received a single 0.12-g dose of the test or reference formulation, followed by a 7-day
washout period and administration of the alternate formulation. Blood samples were collected at
various time intervals, and plasma nateglinide concentrations were analyzed by liquid
chromatography-tandem mass spectrometry. Then, the adverse events, laboratory test results,
vital signs, and physical exam findings were compared between the 2 groups.
The test formulation (0.12 g) met the CFDA's regulatory definition for bioequivalence to the
reference formulation. Both formulations were well tolerated by healthy Chinese subjects.
Page | 20
Bioequivalence Study of Palbociclib Capsules in Healthy Chinese Subjects
Under Fasting and Fed Conditions
Palbociclib is an oral small-molecule inhibitor of cyclin-dependent kinase 4/6 used for the
treatment of advanced breast cancer. This study compared the pharmacokinetic and safety
profiles between a new generic and a branded reference formulation of palbociclib capsules in
healthy Chinese subjects under fasting and fed conditions and evaluated the bioequivalence of
two palbociclib products to obtain sufficient evidence for the marketing approval of the new
generic drug.
A randomized, open-label, two-period crossover study was conducted in healthy Chinese
volunteers under both fasting and fed conditions (30 subjects/condition). Eligible healthy
subjects received a single 125-mg dose of the palbociclib test or reference formulation followed
by a 14-day washout period. Serial blood samples were collected at scheduled timepoints, and
plasma concentrations were determined by a validated high-performance liquid chromatography-
tandem mass spectrometry method. A non-compartment method was used to calculate the main
pharmacokinetic parameters, including the area under the plasma concentration-time curve
(AUC) from time 0 to the time of the last measurable concentration (AUC0-t), the AUC from
time 0 to infinity (AUC0-∞), the maximum plasma concentration (Cmax), the time to maximum
plasma concentration, and the elimination half-life. The geometric mean ratios and the
corresponding 90% confidence intervals of palbociclib were acquired for the bioequivalence
analysis. Safety and tolerability were assessed by monitoring adverse events, laboratory
assessments, vital signs, physical examinations, and 12-lead electrocardiograms.
Pharmacokinetic bioequivalence of palbociclib in healthy subjects was established between the
palbociclib test formulation and the reference formulation under fasting and fed conditions
according to predetermined regulatory criteria. The two formulations were safe and well
tolerated.
Bioequivalence study of anti diabetic activity between two marketed
formulations of metformin on glucocorticoid induces hyperglycemia in rabbit
Bioequivalence studies are the commonly accepted methods displaying therapeutic equivalence
between two products. This study was conducted to evaluate the bioequivalence study of anti-
diabetic activity between two formulations of metformin tablets which were marketed in India.
Metformin hydrochloride is a widely prescribed oral anti-diabetic drug and its official in I. P.
2014. Several brands of Metformin tablets are available in the market leading to a confusion of
their quality and prices. The objective of the present study was to make a comparative in vitro
and in vivo evaluation of two different brands of Metformin hydrochloride which are
Page | 21
commercially available in Guwahati, India. They were subjected to a number of quality control
tests in order to assess their biopharmaceutical equivalence.
Glucocorticoids in excess inhibit insulin secretion from pancreatic beta-cells, decrease glucose
utilization and stimulate glucagon secretion, lipolysis, proteolysis and hepatic glucose
production. Glucocorticoids can modulate the insulin action at both binding sites and post
binding sites and cause decreased glucose utilization in muscles. Glucocorticoids also cause
insulin resistance by decreasing hepatic glucose utilization and decreasing glycogen synthesis
In the present study, it was found that dexamethasone causes a decrease in body weight and
increases glucose levels leading to hyperglycemia. Metformin prevented the rise in glucose,
cholesterol and LDL caused by dexamethasone. Further, this also prevented the progressive
decrease in HDL and body weight caused by dexamethasone.
The study demonstrated that the in vitro drug release profile and anti-diabetic activity of both the
formulation are approximately similar to each other so both the formulations of metformin are
considered as bioequivalent and useful in the management of diabetes.
Bioequivalence study of omeprazole and sodium bicarbonate dry suspensions
Omeprazole and sodium bicarbonate dry suspension are effective treatments for acid-related
disorders. The study was done to compare the bioequivalence and safety of the two formulations
of omeprazole and sodium bicarbonate powder and assessed how CYP2C19 gene
polymorphisms affect pharmacokinetics (PK).
This study has shown that the pharmacokinetic parameters of the two formulations are not
significantly different, which showed bioequivalence and exemplary safety. CYP2C19 gene
polymorphism significantly differed in the PK parameters of omeprazole sodium bicarbonate
powder.
Bioequivalence study of two marketed Bupropion HCL named Budeprion
XL 300 mg Wellbutrin XL 300 mg by FDA
FDA has approved five generic versions of Wellbutrin XL 300 mg. Each of these generics was
approved based on bioequivalence studies comparing the 150 mg strength of the products to
Wellbutrin XL 150 mg. Studies were not performed directly on the 300 mg strength of the
products. Rather, the bioequivalence studies were performed using the 150 mg strength, and the
results were extrapolated to establish bioequivalence of the 300 mg product.
Page | 22
The result found was Budeprion XL 300 mg tablets manufactured by Impax and marketed by
Teva are not therapeutically equivalent to Wellbutrin XL 300 mg and will be removed from the
market by Impax/Teva. FDA’s actions with respect to Budeprion XL 300 mg reflect FDA’s
ongoing role in monitoring drugs on the market to ensure their continued safety and efficacy.
Bioequivalence study of oral dispersible tablets of zonisamide 100 and 300 mg
and immediate-release reference capsules
The bioequivalence of oral dispersible tablets of zonisamide 100 and 300 mg and immediate-
release reference capsules has been assessed in two open, randomized-sequence, single-dose, 2-
period, 2-treatment, crossover studies; the test formulation met regulatory criteria
for bioequivalence.
Original attempts to market zonisamide in the USA were halted by reports of nephrolithiasis, but
successful marketing in Japan resulted in renewed interest elsewhere [1]. Zonisamide has a broad
spectrum of efficacy in the treatment of seizures, including infantile spasms and myoclonic
seizures. It may also have neuroprotective and antimanic effects.
Conclusion
The concept of BE has been adopted by the pharmaceutical industry and national
regulatoryauthorities throughout the world for over 20 years. Because of this, thousands of
generic drugs have been manufactured and marketed by the industry after regulatory approval. A
lot of advances have been made during these years in developing various approaches to assess
BE through research that would assure high quality interchangeable and affordable drugs.
However, a lot remains to be done. There is a continuing attempt by national regulatory
authorities, international public health organization, pharmaceutical, and basic scientists to
understand and develop more efficient and scientifically valid approaches to assess
bioequivalence of various dosage forms including some of the tough complex special dosage
forms.
The consolidation and harmonization of the methodology has been reflected in the guidance of
major health authorities such as the European CPMP, the Canadian HPB and the US FDA. There
is, however, increasing awareness that some fundamentals of bioequivalence assessment need to
be reconsidered, such as the single bioequivalence criterion for all drugs, independent of the
therapeutic window or the intra-subject variability of the drug, and the differentiation between
switchability and prescribability when average bioequivalence is measured. While prescribability
Page | 23
implies prescribing a generic formulation to a first-time user (this is adequately addressed by
existing bioequivalence determinations), switchability is concerned with the equivalence issues
of switching individual patients already on the reference formulation to a generic formulation.
In the future, there will be continued efforts toward achieving clinically and therapeutically
relevant, cost-effective bioequivalence assessment procedures, on a case-by-case basis for each
drug or classes of drugs. With the promise of expanding opportunities for generic formulations in
the immediate future, there is also a need for all national regulatory agencies, especially in the
emerging markets, to align themselves as well as constantly update their regulatory approval
processes, in accordance with the current international thinking on the subject.