Dr. D. K. Brahma
Associate Professor
Department of Pharmacology
NEIGRIHMS, Shillong
What are they ?
• Have Beta-lactam rings
• Important groups are (PCcM)
• Penicillin – the first antibiotic
 Cephalosporins
 Carbapenems
 Monobactams
Penicillins
 First ever antibiotic - 1941 – Flemming, Florey and Chain
 Sources – Fungus Penicillium notatum and P. crysogenum
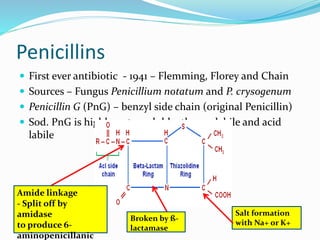
 Penicillin G (PnG) – benzyl side chain (original Penicillin)
 Sod. PnG is highly water soluble, thermolabile and acid
labile
Amide linkage
- Split off by
amidase
to produce 6-
aminopenicillanic
Salt formation
with Na+ or K+
Broken by ß-
lactamase
Penicillin - MOA
MOA – Penicillin Image
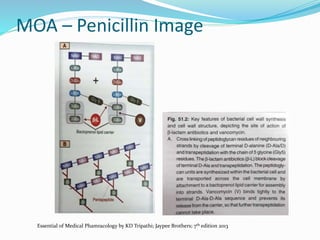
Essential of Medical Phamracology by KD Tripathi; Jaypee Brothers; 7th edition 2013
Mechanism of action
 The principal bacteriocidal mechanism is inhibition of cell
wall synthesis
 The bacterial cell wall is a structure of highly cross-linked
mucopeptide complex, in which peptidoglycan is a main
component
 Bacteria synthesize UDP–N-acetylmuramic acid pentapeptide
(Park neucleotide) and UDP–N-acetyl glucosamine
 They are linked together forming long strands and UDP splits
off
 The final step is cleavage of the terminal D-alanine
 The energy released is utilized in cross-linking with adjacent
peptide chains – by 5 glycine (Gly5)
Penicillin - MOA
 Pencillin binding proteins (PBP) – enzymes and proteins –
several PBPs and also different among species
 ß-lactum antibiotics inhibit transpeptidase – cross linking
prevented – defective cell wall
 Results in Cell wall deficient (CWD) forms – hyperosmotic
inside swells up and bursts
 Also may be bizarre shaped and filamentous forms
 Globular giant forms or protoplasts
 Rapidly multiplying organisms – more victims
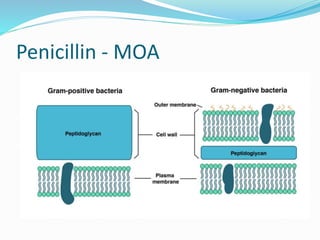
 Gm+ve bacteria entirely peptidoglycan and gm-ve
alternating with lipoprotein
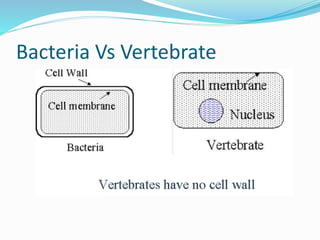
 Peptidoglycan cell wall unique in bacteria
MOA Penicillin - Video
Bacteria Vs Vertebrate
PnG – antibacterial spectrum
 Narrow spectrum – mainly gm+ve and few gm-ve
 Cocci: Streptococci, pneumococi, Staph. aureus
 Gm-ve cocci – Neisseria gonorrhoeae, N. meningitidis,
Gonococci
 Bacilli: gm+ve bacilli – B. anthracis, C. diphtheriae,
all Clostridia, Listeria, Spirochaetes (T. pallidum,
Leptospira) – Fragilis
 Gm-ve bacilli: Mycobacterium tuberculosis,
rickettsiae, chlamydiae, protozoa, fungi, viruses – Not
sensitive
Mechanism of Resistance
1. Inherently insensitive – PBP deeper
2. Penicillinase: Narrow spectrum ß-lactamase inactivates
PnG – opens the ß-lactam ring
• Gm+ve Staphylococci and gonococci, E. Coli, H. influenzae
etc. – elaborate large amounts – diffuses to surroundings
• Gm-ve bacteria in small quantity
• Staphylococcal penicillinase – inducible by methicillin
3. Penicillin tolerant bacteria – low affinity for penicillin –
altered PBP (pneumococci)
• Methicillin resistant Staph. aureus (MRSA) – altered PBP
4. Less permeability to penicillin – low level penicillinase
resistant gonococci and also H. influenzae – plasmid
5. Porins channels – gm-ve bacteria
PnG - Kinetics
 Absorption: Acid labile – 1/3rd a dose absorbed orally
 IM administration – good, rapid and complete absorption –
peak 30 min.
 Distribution: extracellularly and reaches most body fluids
– serous cavities and CNS poor
 In presence of inflammation – good penetration (meningitis,
sinovitis)
 Metabolism: Little metabolized – rapid excretion
 Excretion: 10% glomerular filtration – tubular secretion –
30 min plasma half life
 Longer tubular secretion in neonates – shorter during
childhood – long for elderly and renal failure
 Probenecid
Preparations and doses
 Unitage: 1 U of CPPnG = 0.6µg of standard preparation; 1
g = 1.6 million unit
 Sodium penicillin G (crystalline penicillin): dry
powder in vial – also repository PnG injections
 Repository penicillin G injections: deep IM
 Procaine penicillin G injections: aqueous suspension –
sustained effects 12 – 24 hours
 Fortified procaine penicillin: 3 L U procaine penicillin + 1 L U
Na+ penicillin
 Benzathine penicilline G: 0.6 to 2.4 MU IM every 2 -4
weeks
PnG - ADRs
 Upto 20 MU
 Local irritancy and direct toxicity – Pain, nausea and thrombophlebitis; CNS
toxicities – muscular twitching, convulsion, coma; also bleeding, arachnoiditis
 Hypersensitivity (1-10%) – PnG – rash, itching, urticaria, fever; also wheezing,
angioneurotic edema, serum sickness and exfoliative dermatitis – Anaphylaxis 1
– 4/10,000 – all penicillins may cause
 Most common in parenteral administration – procaine
 Also cross sensitivity
 Scratch test (2 – 10 MU) intradermal
 Negative intradermal test
 Topical application – highly sensitizing - banned except freshly prepared
solution
 Superinfection – rare
 Jarisch-Herxheimer reaction – fever, shivering, myalgia and exagerbation of
lesions – vascular collapse
PnG - Uses Streptococcal infections – Pharyngitis, otitis media,, scarlet fever,
rheumatic fever … SABE by Str. Viridans and fecalis – high dose 10 – 20
MU daily with gentamicin
 Pneumococcal infections – lobar pneumonia, meningitis - rarely used
now
 Menigococcal infections: Mostly responsive - IV
 Gonorrhoea – unreliable – Ophthalmia neonatorum – irrigation with
saline and PnG
 Syphilis: 1. 2 MU daily X 10 days Procaine penicillin, or 2.4 MU weekly;
Late syphilis – Benzathine penicillin 2.4 MU weekly X 4 weeks
 Diphtheria (carrier state), Tetanus and gas gangrene (adjuvant)
 DOC in anthrax, actinomycetes, rat bite fever - PnG
 Prophylactic: Rheumatic fever – Benzathine penicillin – 4 weekly
upto 18 years; Bacterial endocarditis and aggranulocytosis
Semisynthetic penicillins
 Produced chemically by altering side chain or
incorporating precursors
1. Acid resistant Penicillin: Phenoxymethyl penicillin
(Penicillin V) – 1 hour – 1/5th lower grade infections
2. Penicillinase resistant penicillin: Methicillin
(MRSA) – penicillinase resistant but not acid
resistant
 Cloxacillin and dicloxacillin (acid resistant) – weaker
than PnG but stronger than methicillin
Other penicillins
1. Extended spectrum:
a) Aminopenicillins: Ampicillin, Becampicillin,
Amoxicillin
b) Carboxypenicillins: Carbanecillin
c) Ureidopenicillins: Piperacillin, Mezlocillin
2. ß-lactamase inhibitors: Clavulanic acid, sulbactam
and tazobactam
Ampicillin Active against organisms sensitive to PnG with additional H.
influenzae, E. coli, Proteus, Salmonella, Shigella
 More effective than PnG in Strep. Viridans, enterococci and
gonococci
 Not resistant to penicillinase and developed resistance
 Not usefull against gm-ve - pseudomonas, Klebsiella, indole
positive Proteus
 Kinetics: acid stable, food interferes absorption, enterohepatic
circulation
 Uses: UTI, RTI (bronchitis, sinusitis, otitis media), Meningitis
(1st line before), Gonorrhoea (1st line for non-penicillinase
producing gonococci), Typhoid fever, Bacillary dysentery,
Cholecystitis, SABE, H. pylori, Septicaemias
 ADRs: Diarrhoea, alteration of gut flora, high incidence of rash
– in AIDS patients … history of hypersensitivity
 Becampicillin and Amoxicillin – similar drugs
Amoxcillin
 Close congener of Ampicillin
 Faster oral absorption, no food interference, lesser
diarrhoea, more sustained effect and higher plasma
conc.
 Less effective against H. influenzae and Shigella
 Effective against Penicillin resistant Strep. Pneumoniae
 Uses: Bronchitis, UTI, SABE and gonorrhoea, H. pylori
Carboxypenicillins - carbenicillin Active against Ps. aeruginosa and indole positive Proteus
 Less effective against Salmonella, E. coli, Enterobacter,
Klebsiella and gm+ cocci
 Resistance strains of Ps. Aeruginosa developed
 Not acid resistant, not penicillinase resistant – given IM or
IV – available as Na+ salt – CHF and renal failure, bleeding
 Uses: seriuos infection caused by Pseudomonas e.g. burns,
UTI, septicaemia - combined with gentamicin (1 -2 mg
IM/IV 4 – 6 hrly)
 Ureidopenicilins (Piperacillin): 8 times more active
than carbenicillin, good against Klebsiella and many
enterobacteriaceae. Used for treating seriuous gm-ve
infectionsin immunocompromised and neutropenic
patients
Beta-lactamase inhibitors
 Enzymes produced by gm+ve and gm-ve bacteria –
inactivate ß-lactum antibiotics by opening ß-lactum ring –
Clavulanic acid, Sulbactum and Tazobactum
 Clavulanic acid: Streptomyces clavuligerus; has a beta
lactum ring but no antibacterial actuvity – inhibits a wide
variety of lactamases (+ and -)
 MOA: Progressive inhibitor; binds to ß-lactamases
reversibly initially followed by covalent later – sucide
inhibitor
 Permeates the outer layer of gm-ve cell wall an inhibits
periplasmically located ß-lactamases
 Kinetics: Orally absorbed and can also be given
parenterally; elimination half-life 1 hr – matches
Amoxicillin - Coamoxiclav
Clavulanic acid
 Uses: Clavulanic acid re-establishes activity of
amoxicillin against resistant Staph. Aureus (but not
MRSA), Influenzae, Gonorrhoea, E. coli, Proteus,
Klebsiella, Salmonella and Shigella
 Skin and soft tissue infections, intraabdominal and
gynaecological sepsis, UTI, RTI and biliary infections
 Gonorrhoea including PPNG – single dose Amoxicillin
3 gm – Clavulanic acid 0.5 gm and Probenecid 1 gm
 ADRs: Same as amoxicillin but poorer GI tolerance,
candida stomatitis/vaginitis and rashes
Sulbactum
 Semisynthetic and related to Clavulanic acid
 Progressive inhibitor of ß-lactamases
 2-3 times less potent than clavulanic acid
 Does not produce chromosomal ß-lactamases
 Given parenterally – erratic oral absorption
 Combined with ampicillin – Sultamicillin
 Uses: PPNG, mixed aerobic and anaerobic infections,
intra-abdominal, gynaecological, surgical and skin-
soft tissue infections – hospital acquired
Tazobactum
 ß-lactamases inhibitor – similar to sulbactum
 Combined with Piperacillin
 Used in Peritonitis, Pelvic/urinary/ respiratory
infections caused by beta lactamase producing bacilli
 Not useful against inducible chromosomal ß-
lactamases produced by enterobacteriaceae and
piracillin resistant pseudomonas
Cephalosporins
 Obtained from Cephalosporium acremonium
 The nucleus consist of a lactam ring + Dihydrothiazine
ring
 7-aminocephalosporanic acid
 Same MOA as Penicillin
 R1 and R2 – spectrum and pharmacokinetic activity
respectively
Common features
Excreted primarily by the kidney
Exceptions Cefoperazone, Ceftriaxone ( Bile less in urine)
Probenecid slows the tubular secretion
CSF concentration good
Cross the placenta
High concentrations in synovial & pericardial fluids and
aqueous humor
Resistance
 Altering the PBPs reducing affinity
 Impermeability to the antibiotic or its efflux
 Elaboration of beta-lactamases
 Individual cephalosporins differ
 Antibacterial spectrum and potency
 Susceptibility to beta-lactamases
 Pharmacokinetic properties
First generation
Parenteral: Cefazolin and Cephalothin
Oral: Cephalexin, Cephradine, Cefadroxil
Good activity against gram +ve bacteria
Relatively modest activity against gram-ve bacteria
Not effective against Enterococci, MRSA, S.
epidermidis and B. fragilis
Cefazolin: Surgical prophylaxis (2 hours half life)
Cefadroxil has good tissue penetration
Second generation
Parenteral: Cefuroxime, Cefotetan, Cefoxitin
Oral: Cefuroxime axetil, Cefaclor
Increased activity against gram -ve microorganisms
Enterobacter spp., indole-positive Proteus spp., and
Klebsiella spp.
Cefuroxime & Cefoxitin: resistant to gram –ve β-lactamases
Cefoxitin, Cefotetan also active against anaerobes (B.
fragilis)
Third generation
Parenteral: Cefotaxime, Ceftizoxime, Ceftriaxone,
Ceftazidime, Cefoperazone
Oral: Cefixime, Cefpodoxime proxetil, Ceftibuten,
Cefditoren pivoxil
Much more active against the Enterobacteriaceae
Highly resistant to β-lactamases
Antipseudomonal: Ceftazidime and Cefoperazone
Uses - Cefotaxime
1.Gram –ve meningitis
2.Hospital Acquired Infections
3.Septicemia in immunocompromised patients
4.Single dose therapy of Gonorrhoea
(1 g Cefotaxime im + 1g Probenecid oral)
Ceftizoxime inhibit B. fragilis
Ceftriaxone
1. Meningitis
2.Multiresistant typhoid fever
3.Complicated UTI
4.Abdominal Sepsis & Septicemia
5.Gonorrhoea & Chancroid
Third generation – contd.
Ceftazidime
Antipseudomonal
Cause Neutropenia, thrombocytopenia, ↑ transaminase
& ↑ blood urea
Cefoperazone
Antipseudomonal
Cause Hypoprothrombinemia & Disulfiram like reaction
Fourth generation
Parenteral: Cefepime, Cefpirome
Extended spectrum of activity compared with the third
generation
Increased stability from hydrolysis by plasmid and
chromosomally mediated β-lactamases
Empirical treatment of serious infections in hospitalized
patients when gram +ve microorganisms,
Enterobacteriaceae, and Pseudomonas all are potential
etiologies
Adverse effects - cephalosporins
 Pain after IM and thrombophlebitis
 Diarrhoea
 Hypersensitivity reaction – like penicillin -10%
 Nephrotoxicity
 Bleeding – hypoprothombinaemia – cefoperazone,
ceftriaxone
 Neutropenia
 Disulfiram like reaction - cefoperazone
Semisynthetic Penicillins are still usefull
in various serious infections if used
judiciously