

Beta blockers and calcium channel blockers are
widely prescribed for a range of conditions and are
now widely used in the management of
cardiovascular disease.



In 1958, the first beta blocker, dichloroisoproterenol,
was synthesised by Eli Lilly Laboratories.



Sir James W Black in 1962, found the first clinically
significant beta blockers – Propranolol and
Pronethalol



Calcium channel blockers were first identified in the
lab
of
German
pharmacologist
Albrecht
Fleckenstein beginning in 1964 and are now widely
used and have potent vasodialatory effect.
.


Beta blockers, also known
as
beta-adrenergic
blocking agents or beta
antagonists,
or
betaadrenergic
antagonists,
are
medications
that
reduce
blood pressure.
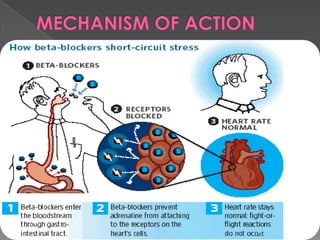
Beta blockers work by
blocking the effects of the
hormone epinephrine, also
known as adrenaline.


Beta receptors are found on cells of the
heart muscles, smooth muscles, airways,
arteries, kidneys, and other tissues that
are part of the sympathetic nervous
system and lead to stress responses,
especially when they are stimulated by
epinephrine (adrenaline).
Three types of beta receptors are known,
designated β1, β2 and β3 receptors.
 β1-adrenergic receptors are located
mainly in the heart and in the kidneys.
 β2-adrenergic receptors are located
mainly in the lungs, gastrointestinal tract,
liver, uterus, vascular smooth muscle,
and skeletal muscle.
 β3-adrenergic receptors are located in
fat cells.

Angina pectoris
 Atrial fibrillation
 Cardiac arrhythmia
 Congestive heart failure
 Essential tremor
 Glaucoma
 Hypertension
 Migraine prophylaxis
 Mitral valve prolapse
 Myocardial infarction












Phaeochromocytoma, in conjunction with
α-blocker
Postural orthostatic tachycardia syndrome
Symptomatic control (tachycardia, tremor)
in anxiety and hyperthyroidism
Theophylline overdose
Acute aortic dissection
Hypertrophic obstructive cardiomyopathy
Marfan syndrome (treatment with
propranolol slows progression of aortic
dilation and its complications)
Prevention of variceal bleeding in portal
hypertension
cocaine-induced tachycardia
 sinus bradycardia
 partial AV block
 peripheral vascular diseases
 diabetes mellitus
 chronic obstructive pulmonary disease
(COPD) and
 asthma















Nausea
diarrhea
bronchospasm
dyspnea
cold extremities
exacerbation of Raynaud's syndrome
bradycardia
hypotension,
heart failure
heart block
fatigue











dizziness
alopecia (hair loss)
abnormal vision
hallucinations
insomnia
nightmares
sexual dysfunction
alteration of glucose and lipid metabolism.
Adverse effects associated with β2adrenergic receptor antagonist activity
(bronchospasm, peripheral
vasoconstriction, alteration of glucose and
lipid metabolism)
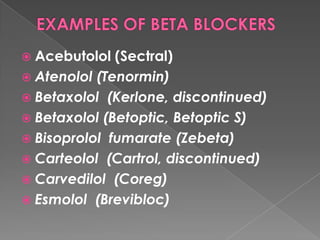
 Acebutolol

(Sectral)
 Atenolol (Tenormin)
 Betaxolol (Kerlone, discontinued)
 Betaxolol (Betoptic, Betoptic S)
 Bisoprolol fumarate (Zebeta)
 Carteolol (Cartrol, discontinued)
 Carvedilol (Coreg)
 Esmolol (Brevibloc)
Labetalol (Trandate, Normodyne)
 Metoprolol (Lopressor, Toprol XL)
 Nadolol (Corgard)
 nebivolol (Bystolic)
 penbutolol (Levatol)
 pindolol (Visken, discontinued)
 propranolol (Inderal, InnoPran)
 sotalol (Betapace)
 timolol (Blocadren, discontinued)
 timolol ophthalmic solution (Timoptic)



Combining propranolol (Inderal) or
pindolol
(Visken)
with
thioridazine
(Mellaril) or chlorpromazine (Thorazine)
may result in low blood pressure
(hypotension) and abnormal heart
rhythms because the drugs interfere with
each others' elimination and result in
increased levels of the drugs.
Dangerous elevations in blood pressure may
occur when clonidine (Catapres) is combined
with a beta blocker
 Phenobarbital and similar agents may increase
the breakdown and reduce blood levels of
propanolol (Inderal) or metoprolol (Lopressor,
Toprol XL). This may reduce effectiveness of the
beta blocker.
 Aspirin and other nonsteroidal antiinflammatory
drugs (NSAIDs) (for example, ibuprofen) may
counteract the blood pressure reducing effects
of beta blockers by reducing the effects of
prostaglandins. Prostaglandins play a role in
control of blood pressure.



Glucagon is the specific antidote for betablocker poisoning, because it increases
intracellular cAMP and cardiac contractility



Patients who experience Bronchospasm
due to the Beta2 blocking effects of
nonselective beta blockers may be treated
with anticholinergic drugs, such as
Ipratropium, which are safer than beta
agonists in patients with cardiovascular
disease. Another antidote for beta blocker
poisoning are Salbutamol and Isoprenaline.


A calcium channel
blocker (CCB) is a
chemical that disrupts the
movement of calcium
(Ca2+) through calcium
channels. Calcium
channel blockers are used
as antihypertensive drugs.


CCBs used as medications primarily have
three effects:



by acting on vascular smooth muscle they
reduce contraction of the arteries and cause
an
increase
in
arterial
diameter,
a
phenomenon called vasodilation (CCBs do
not work on venous smooth muscle)



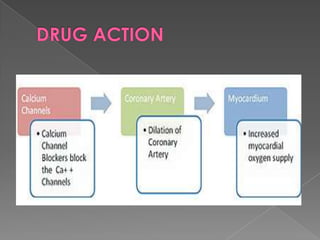
by acting on cardiac muscles (myocardium),
they reduce the force of contraction of the
heart



by slowing down the conduction of electrical
activity within the heart, they slow down the
heart beat.
1.








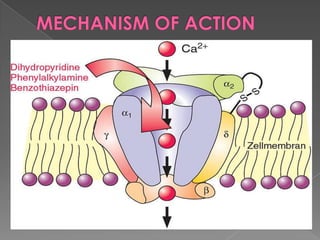
Dihydropyridine
Dihydropyridine calcium channel blockers
are
derived
from
the
molecule
dihydropyridine and often used to reduce
systemic vascular resistance and arterial
pressure, but are not used to treat angina
This CCB class is easily identified by the suffix
"-dipine"
Amlodipine (Norvasc)
Aranidipine (Sapresta)
Azelnidipine (Calblock)
2.Non-dihydropyridine
 Phenylalkylamine
 Phenylalkylamine
calcium
channel
blockers are relatively selective for
myocardium,
reduce
myocardial
oxygen demand and reverse coronary
vasospasm, and are often used to treat
angina
 EXAMPLES ARE:
 Verapamil (Calan, Isoptin)
 Gallopamil
 Fendiline
3.Benzothiazepine
Benzothiazepine calcium channel blockers
belong to the benzothiazepine class of
compounds and are an intermediate class
between
phenylalkylamine
and
dihydropyridines in their selectivity for
vascular calcium channels.
 EXAMPLE :Diltiazem (Cardizem) (also used
experimentally to prevent migraine)

4.Nonselective
 While most of the agents listed above are
relatively selective, there are additional
agents that are considered nonselective.
These include mibefradil, bepridil, flunarizine
5. Ziconotide
 Ziconotide, a peptide compound derived
from the omega-conotoxin, is a selective Ntype calcium channel blocker that has
potent analgesic properties.
AMLODIPINE (NORVASC)
 CLEVIDIPINE (CLEVIPREX)
 DILTIAZEM (CARDIZEM),
 FELODIPINE (PLENDIL),
 ISRADIPINE (DYNACIRC),
 NIFEDIPINE (ADALAT, PROCARDIA),
 NICARDIPINE (CARDENE),
 NIMODIPINE (NIMOTOP),
 NISOLDIPINE (SULAR), AND
 VERAPAMIL (CALAN, ISOPTIN).











CCBs are used for treating high blood
pressure, angina, and abnormal heart
rhythms.
They also may be used after a heart attack
They also are used for treating:
pulmonary hypertension,
Raynaud's syndrome,
cardiomyopathy, and
subarachnoid hemorrhage.
CCBs are also used in the prevention of
migraine headaches







AMLODIPINE (NORVASC®):
Adult (usual) Angina: 5-10 mg po qd.
BEPRIDIL (VASCOR®):
usual dose: 300 mg/day; maximum daily
dose: 400 mg
CLEVIDIPINE -CLEVIPREX ®
Intravenous infusion of Cleviprex at 1-2
mg/hour.
DILTIAZEM (CARDIZEM ®):
 Adult (usual) Oral:usual dose 180-360 mg
po daily (ANGINA)
 usual dose 120-180 mg bid
(HYPERTENSION)
 FELODIPINE (PLENDIL®):
 Adults: hypertension: Oral: 2.5-10 mg
once daily.
 NIFEDIPINE (PROCARDIA®):
 10-30 mg 3 times/day as capsules

Constipation
 nausea
 Headache
 Rash
 edema (swelling of the legs with fluid)
 low blood pressure
 drowsiness and dizziness
 sexual dysfunction.



Verapamil and diltiazem decrease the
elimination of a number of drugs by the
liver. Through this mechanism, verapamil
and
diltiazem
may
reduce
the
elimination and increase the blood levels
of carbamazepine (Tegretol), simvastatin
(Zocor), atorvastatin
(Lipitor), and
lovastatin (Mevacor). This can lead to
toxicity from these drugs.
Mild CCB toxicity is treated with supportive
care
 For severe overdoses, treatment usually
includes close monitoring of vital signs and
the addition of vasopressive agents and
intravenous fluids for blood pressure
support. IV calcium gluconate (or calcium
chloride if a central line is available) and
atropine are first-line therapies.



Cardiovascular disease remains the leading
cause of morbidity and mortality among
transplant
recipients.
Therefore,
antihypertensive therapy should focus on
those agents with proven benefit in reducing
the progression of cardiovascular disease.
Despite their effectiveness, CCB's often have
a high mortality rate over extended periods
of use, and have been known to have
multiple side effects. Beta-blockers, however,
have been, are, and will remain the
cornerstone for the treatment of heart failure
Beta blockers and calcium channel blockers