AGENDA :-
Basicsof Hemostasis & Classification of Hemostatic disorders
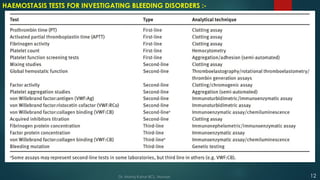
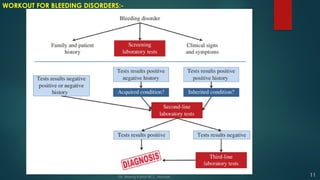
Introduction to first line Investigations in bleeding disorders
Differential Diagnosis based on result of first line investigations
Attributes of a proper PT/APTT/FIBRINOGEN reagents
Principles of coagulometer
Pre analytical factors affecting PT/APTT/FIBRINOGEN results
Quality Control in first line investigations in bleeding disorders
Required performance specifications for PT/APTT &
FIBRINOGEN tests
Dr. Manoj Kahar BCL, Navsari. 3
4.
INTRODUCTION :-
Thehaemostasis pathway is very complex, and includes various
elements of activation and regulation.
The investigation of aberrant haemostasis or the monitoring of
anticoagulant therapy requires the performance of a multitude of test
procedures.
These in turn can be influenced by many factors ranging from
anticoagulant therapy, liver disease, and infections, in addition to
congenital and acquired defects.
Specific procedures for test collection, sample preparation, test
performance, and quality assurance need to be established in every
laboratory to ensure provision of accurate and reliable results to
enable appropriate patient management and care.
IQC and EQA facilitate this process to ensure the quality of test results.
Dr. Manoj A Kahar, BCL, Navsari 4
5.
HEMOSTATIC RESPONSE:-
5
Dr. ManojKahar BCL, Navsari.
(INTERPLAY OF BLOOD VESSELS PLATELETS
AND BLOOD COAGULATION IN NORMAL
HAEMOSTASIAS) SCHEMATIC DIAGRAM OF HEMOSTASIS.
6.
OVERVIEW OF HEMOSTASIS:-
6
Dr.Manoj Kahar BCL, Navsari.
Coagulation is initiated via two pathways, the primary extrinsic pathway (right) and the
accessory (historically called the contact or intrinsic) pathway (left).
An illustration of the multistep processes is as follows: enzymes (small circles), inhibitors
(large circles), zymogens (boxes), or complexes (ovals).
The accessory pathway has no known bleeding etiology associated with it; thus, this
pathway is considered an accessory to hemostasis.
Upon injury to the vessel wall, tissue factor, the cofactor for the extrinsic tenase complex,
is exposed to circulating factor (F) VIIa and forms the vitamin K–dependent complex
extrinsic tenase.
FIX and FX are converted to the serine proteases factor IXa (FIXa) and factor Xa (FXa),
which then form the intrinsic tenase and prothrombinase complexes, respectively. The
combined actions of intrinsic and extrinsic tenase complexes and the prothrombinase
complex lead to an explosive burst of thrombin (FIIa).
Thrombin not only functions as a procoagulant but also acts as an anticoagulant when
complexed with the cofactor thrombomodulin in the protein Case complex.
The product of the protein Case reaction, activated protein C (APC), inactivates the
cofactors FVa and FVIIIa.
The cleaved species, factor Vai (FVai) and factor VIIIai (FVIIIai), no longer support the
respective procoagulant activities of the prothrombinase and intrinsic tenase complexes.
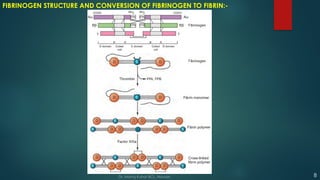
When thrombin is generated through procoagulant mechanisms, thrombin cleaves
fibrinogen, releasing fibrinopeptide A (FPA) and fibrinopeptide B (FPB), and activates FXIII
to form a cross-linked fibrin clot.
Thrombin–thrombomodulin also activates thrombin activatable fibrinolysis inhibitor (TAFI),
which delays fibrin degradation by plasmin.
The procoagulant response is downregulated by the stoichiometric inhibitors tissue factor
pathway inhibitor (TFPI) and antithrombin (AT).
TFPI attenuates the activity of extrinsic tenase, the trigger of coagulation.
AT directly inhibits thrombin, FIXa, and FXa. The accessory pathway provides an alternate
route for the generation of FIXa.
Thrombin has also been shown to activate FXI. HMWK, High-molecular-weight kininogen.
7.
SCHEMATIC DIAGRAMOF
PHYSIOLOGIC BLOOD COAGULATION.
Organization of the coagulation system
based on current assays.
7
Dr. Manoj Kahar BCL, Navsari.
HEMOSTATIC DISORDERS :-
Bleeding can occur if there is
abnormal platelet plug
formation and/ or reduced
thrombin generation and
subsequent fibrin clot formation
at the site of vascular injury,
disorders of primary and
secondary hemostasis,
respectively.
Bleeding also can occur if the
platelet/ fibrin clot is
prematurely degraded
because of excessive
fibrinolysis; a disorder of tertiary
hemostasis.
Comparison of the Features of Disorders of Primary,
Secondary, or Tertiary Hemostasis
9
Dr. Manoj Kahar BCL, Navsari.
10.
DISORDERS OF TERTIARYHEMOSTASIS
DISORDERS OF PRIMARY HEMOSTASIS
DISORDERS OF SECONDARY HAEMOSTASIS
10
Dr. Manoj Kahar BCL, Navsari.
Prothrombin time (PT)and activated partial thromboplastin time (APTT) are
the standard screening coagulation assays
(a) PT is performed by adding tissue factor and
phospholipid to platelet poor plasma (PPP) at room
temperature in the presence of calcium. Here,
supraphysiological concentrations of TF drive the
generation of FXa and FIIa via extrinsic and common
pathways, resulting in the rapid formation of a fibrin
clot.
(b) APTT measures the plasma clotting time following
the activation of the contact factor FXII.
Autoactivation of FXII to FXIIa is facilitated by the
addition of contact activators kaolin, silica or ellagic
acid to PPP, followed by incubation. FXIIa activates
FXI and generates FXa and FIIa through intrinsic and
common pathways and fibrin clot formation.
Under normal physiological conditions, FXI activation
is catalysed by thrombin rather than FXIIa.
Deficiencies in any of the factors along the pathway
result in the prolongation of PT and APTT.
13
Dr. Manoj Kahar BCL, Navsari.
14.
THROMBIN
TIME:-
Thrombintime (TT) is usually not a
commonly ordered test because of its
limited utility in laboratory assessment of
most bleeding disorders.
In the TT test, bovine thrombin (3–5
U/mL) is added to the patient’s plasma
and the clotting time recorded.
The upper limit of the normal range
should be adjusted close to 25 sec to
make TT more sensitive to detect
dysfibrinogenemia.
The most frequent cause of prolonged
TT is heparin followed by
hypofibrinogenemia and then
dysfibrinogenemia.
Direct thrombin inhibitors (oral and
parenteral) significantly prolong TT.
14
Dr. Manoj Kahar BCL, Navsari.
15.
FIBRINOGEN ASSAY :-
Fibrinogen assay should be measured routinely in a bleeding patient and
patients with cirrhosis.
The fibrinogen assay is based on TT (Clauss method) in which a standard
curve is generated by using known calibrators and bovine thrombin at a
very high concentration of 50 U/mL (for TT 3–5 U/mL) so that the clotting time
is independent of thrombin concentration.
Bovine thrombin is added to the patient’s plasma and the clotting time
obtained is used to extrapolate fibrinogen value from the standard curve.
A very high amount of the direct thrombin inhibitor will give false low
fibrinogen levels.
If there is clinical suspicion for hypofibrinogenemia, the direct fibrinogen
assay should be performed rather than relying on PT and APTT to be
prolonged because, in the majority of patients with mild to moderate
hypofibrinogenemia, PT and APTT are likely to be normal.
15
Dr. Manoj Kahar BCL, Navsari.
LIMITATION OF AUTOMATEDPT AND APTT TO DETECT MILD TO MODERATE HYPOFIBRINOGENEMIA :-
When PT and APTT were performed manually in the
past, the endpoint was a solid, firm clot formation
on the side of the test tube.
However, with automation, the endpoint of PT/APTT
is the change in optical density or turbidity due to
formation of fibrin strands.
Therefore, the endpoint is often sooner than the
manual method; hence, automated PT and APTT
are usually normal, with mild to moderate
hypofibrinogenemia.
17
Dr. Manoj Kahar BCL, Navsari.
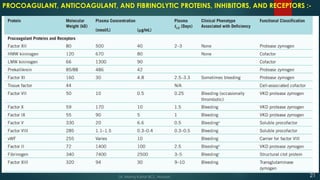
Anticoagulant Proteins, Inhibitors,and Receptors
22
Dr. Manoj Kahar BCL, Navsari.
PROCOAGULANT, ANTICOAGULANT, AND FIBRINOLYTIC PROTEINS, INHIBITORS, AND RECEPTORS :-
23.
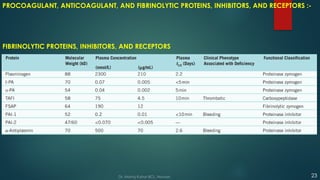
FIBRINOLYTIC PROTEINS, INHIBITORS,AND RECEPTORS
23
Dr. Manoj Kahar BCL, Navsari.
PROCOAGULANT, ANTICOAGULANT, AND FIBRINOLYTIC PROTEINS, INHIBITORS, AND RECEPTORS :-
24.
SELECTION OF REAGENTSFOR PT & APTT TESTS
ATTRIBUTES OF A PROPER PT REAGENTS:-
Recombinant thromboplastins are manufactured using recombinant
human tissue factor produced in Escherichia coli and synthetic
phospholipids, which do not contain any other clotting factors.
Therefore, they are highly sensitive to factor deficiencies and oral
anticoagulant-treated patient plasma samples and have an
International Sensitivity Index (ISI) close to 1.
Each preparation has a different sensitivity to clotting factor
deficiencies and defects, in particular the defect induced by oral
anticoagulants.
For control of oral anticoagulation, a preparation calibrated against
the International Reference Thromboplastin should be used
CaCl2 . 0.025mol/l.
24
Dr. Manoj Kahar BCL, Navsari.
25.
NORMAL VALUES:-
Normalvalues Normal values depend on the
thromboplastin used, the exact technique and whether
visual or instrumental end-point reading is used.
With most rabbit thromboplastins the normal range of the
PT is between 11 and 16 sec; for recombinant human
thromboplastin it is somewhat shorter (10–12sec).
Each laboratory should establish its own normal range.
25
Dr. Manoj Kahar BCL, Navsari.
26.
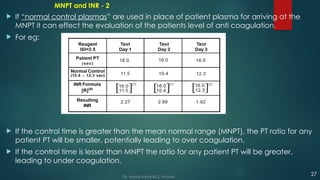
MNPT and INR- 1
MNPT is a critical requirement in the derivation of INR
Ideally each laboratory must derive its own MNPT from 20 or more normal
patients for a given PT reagent and Lot under use.
This corrects within laboratory test variables that influence PT results.
obtained for a particular patient sample as if the WHO reference
thromboplastin itself (ISI=1.0) had been used in the PT determination.
INR = [R] ISI
A PT ratio is obtained by dividing the patient PT in seconds by the “Mean of the
normal range”(MNPT).
This ratio is then “normalized” by raising the results to the power of the ISI of the
PT reagent used.
26
Dr. Manoj Kahar BCL, Navsari.
27.
MNPT and INR- 2
If “normal control plasmas” are used in place of patient plasma for arriving at the
MNPT it can effect the evaluation of the patients level of anti coagulation.
For eg:
If the control time is greater than the mean normal range (MNPT), the PT ratio for any
patient PT will be smaller, potentially leading to over coagulation.
If the control time is lesser than MNPT the ratio for any patient PT will be greater,
leading to under coagulation.
27
Dr. Manoj Kahar BCL, Navsari.
28.
A RECOMMENDED APPROACHTO THE CLINICAL LABORATORY CALIBRATION, ESTIMATION, AND
VALIDATION OF ISI AND MNPT VALUES FOR USE IN THE INR SYSTEM ASSOCIATED WITH VKA THERAPY :-
Dr. Manoj Kahar BCL, Navsari. 28
29.
INTERPRETATION OF PTRESULT:-
The common causes of a prolonged PT are as follows:
1. Administration of oral anticoagulant drugs (vitamin K
antagonists)
2. The presence of a direct acting inhibitor of factor Xa
3. Liver disease, particularly obstructive jaundice
4. Vitamin K deficiency
5. Disseminated intravascular coagulation
6. Rarely, a previously undiagnosed factor VII, X, V or
prothrombin deficiency or defect.
Note: With prothrombin, FX or factor V deficiency the APTT will also
be prolonged.
29
Dr. Manoj Kahar BCL, Navsari.
30.
ATTRIBUTES OF APROPER APTT REAGENT :-
Kaolin. 5g/l (laboratory grade) in barbitone buffered saline, pH7.4
Add a few glass beads to aid resuspension.
The suspension is stable at room temperature.
Other insoluble surface-active substances such as silica, celite or ellagic acid can also
be used. Phospholipid.
Many reagents are available; these contain different phospholipids.
When choosing a reagent for the APTT, it is important to establish that the activator–
phospholipid-incubation time combination is sensitive to deficiencies of factors VIII, IX
and XI at concentrations of 0.35–0.4 iu/ml.
Combinations that do not produce a prolonged clotting time at these levels are too
insensitive.
The system should also be responsive to unfractionated heparin over the therapeutic
range of approximately 0.3–0.7 anti-Xa iu/ml.
In addition, some laboratories will wish the system to be sensitive to the presence of
lupus anticoagulants.
30
Dr. Manoj Kahar BCL, Navsari.
31.
CONCENTRATION OF CALCIUMCHLORIDE TO BE USED FOR APTT :-
The optimum concentration of Calcium chloride to be used for
APTT test should be 0.02M.
- The concentration of 0.02M CaCl2 replaces the calcium
necessary to activate the intrinsic coagulation cascade.
- This ultimately generates thrombin from prothrombin via the
coagulation cascade.
- Appropriate volumes of CaCl2 should be aspirated for the days
work.
- Prewarmed CaCl2 should always be discarded at the end of the
working day.
31
Dr. Manoj Kahar BCL, Navsari.
32.
NORMAL RANGE FORAPTT RESULT :-
The normal range is typically 26 to 40s.
The actual times depend on the reagents used and
the duration of the preincubation period, which varies
in manufacturers’ recommendations for different
reagents.
Laboratories can choose appropriate conditions to
achieve the sensitivity they require. Each laboratory
should calculate its own normal range.
32
Dr. Manoj Kahar BCL, Navsari.
33.
INTERPRETATION OF APTTRESULT:-
The common causes of a prolonged APTT are as follows:
1. Disseminated intravascular coagulation
2. Liver disease
3. Massive transfusion with plasma-depleted red blood cells
4. Administration of or contamination with heparin or other anticoagulants
5. A nonspecific circulating anticoagulant (such as an LAC)
6. The presence of a direct acting anticoagulant drug (e.g. anti-IIa or anti-Xa
agents)
7. Deficiency of a coagulation factor other than factor VII The APTT is also
moderately prolonged in patients taking oral anticoagulant drugs and in the
presence of vitamin K deficiency.
Occasionally, a patient with previously undiagnosed hemophilia or another
congenital coagulation disorder presents with an isolated prolonged APTT.
If the patient’s APTT is abnormally long, mixing tests, an inhibitor screen and factor
assays should be considered (see below).
33
Dr. Manoj Kahar BCL, Navsari.
34.
ATTRIBUTES OF APROPER TT REAGENT :-
Thrombin solution:- A commercial bovine thrombin is
used. It is stored frozen as a 50 National Institutes of
Health (NIH) unit solution, and it is freshly diluted in
barbitone buffered saline in a plastic tube so as to
give a clotting time of normal plasma of 15s (usually
approximately 7–8 NIH thrombin units per ml).
Shorter times with normal plasma may fail to detect
mild abnormalities.
34
Dr. Manoj Kahar BCL, Navsari.
35.
NORMAL RANGE :-
A patient’s TT should be within 2s of the control (i.e. 15 to
19s).
Times of 20s and longer are definitely abnormal.
35
Dr. Manoj Kahar BCL, Navsari.
36.
INTERPRETATION OF RESULTS:-
The common causes of prolonged TT are as follows:
1. Hypofibrinogenemia as found in DIC and, more rarely, in a congenital deficiency
2. Dysfibrinogenemia, either inherited or acquired, in liver disease or in neonates
3. Extreme prolongation of the TT is nearly always a result of thrombin inhibition; typically
unfractionated heparin but also oral or parenteral direct thrombin inhibitors.
If a thrombin inhibitor is suspected, a reptilase time test can be carried out or the test can be
repeated after the addition of heparinase.
Low molecular weight heparin (LMWH) produces only a slight prolongation at therapeutic levels
4. Raised concentrations of fibrin degradation products (FDP), as encountered in DIC or liver
disease
5. Hypoalbuminaemia
6. Paraproteinemia.
Shortening of the TT occurs in conditions of coagulation activation.
A transparent bulky clot is found if fibrin polymerization is abnormal, as is the case in liver disease
and some congenital dysfibrinogenemia’s.
A gross elevation of the plasma fibrinogen concentration may also prolong the TT.
Correction can be obtained by diluting the patient’s plasma with saline.
36
Dr. Manoj Kahar BCL, Navsari.
37.
ATTRIBUTES OF APROPER REAGENT FOR FIBRINOGEN ASSAY (CLAUSS TECHNIQUE) :-
Thrombin solution. Freshly reconstituted to 100 NIH
u per ml in 9g/l NaCl.
Owren veronal buffer
• Sodium acetate: 3.89g
• Barbitone sodium: 5.89g
• Sodium chloride: 6.8g
• Dissolve the salts in 800ml of water.
• Add 21.5ml of 1mol/l HCl, then make up to 1 liter
with water, mix and check that the pH is 7.4.
37
Dr. Manoj Kahar BCL, Navsari.
38.
NORMAL RANGE OFFIBRINOGEN BY (CLAUSS TECHNIQUE) :-
The normal range is approximately 1.8 to 3.6g/l.
Dr. Manoj Kahar BCL, Navsari. 38
39.
INTERPRETATION OF FIBRINOGENASSAY BY (CLAUSS TECHNIQUE) :-
The Clauss fibrinogen assay is usually low in inherited
dysfibrinogenaemia but is insensitive to heparin unless the level is very
high (>0.8 u/ml).
High levels of FDPs (>190 μg/ml), may also interfere with the assay.
Because the chronometric Clauss assay is a functional assay it will
generally give a relevant indication of fibrinogen function in plasma.
When an inherited disorder of fibrinogen is suspected, a
physicochemical estimation should be obtained (e.g. clot weight
estimate of fibrinogen or total clottable fibrinogen or an
immunological assay).
If a dysfibrinogenaemia is present, it will reveal a discrepancy
between the (functional) Clauss assay and the physical amount of
fibrinogen present.
Dr. Manoj Kahar BCL, Navsari. 39
40.
PRINCIPLE OF COAGULOMETER:-
Mechanical Detection
Object Movement: An instrument moves a small
object, such as a steel ball or magnet, within a
plasma sample.
Clot Impediment: As the plasma clots and fibrin
strands form, they impede the movement of the
object.
Endpoint Detection: A sensor detects the change
in the object's movement, indicating the
completion of the coagulation process.
Optical Detection
Light Transmission/Scattering: A beam of light
is passed through the plasma sample.
Clot Interference: As fibrin forms, it increases
the turbidity of the sample, either by
scattering light or by reducing the amount of
light transmitted through the sample.
Endpoint Detection: The instrument measures
these changes in light intensity or scattering
to pinpoint the exact moment of clot
formation. 40
41.
ANALYTICAL ERRORS:-
Most ofthe problems are attributable to
equipment malfunction,
release of results despite poor quality controls,
inappropriate reagent/instrument calibrations, reagent
problems (e.g., not properly reconstituted or used
beyond stability),
methodological issues (poor methodologies),
analytical interferences,
poor standardization of the tests.
41
Dr. Manoj Kahar BCL, Navsari.
42.
42
PREPARATION OF PLATELET-POORPLASMA :-
Most routine coagulation investigations are performed on
platelet-poor plasma (PPP), which is prepared by
centrifugation at 2000g for 15min at 4°C (approximately 4000
rev/min in a standard bench cooling centrifuge).
The sample should be kept at room temperature if it is to be
used for PT tests, lupus anticoagulant (LAC) or factor VII assays
and it should be kept at 4°C for other assays.
The testing should preferably be completed within 2h of
collection.
Care must be taken not to disturb the buffy coat layer when
removing the PPP.
Platelet poor plasma containing ≤ 10 x platelets/L.
Dr. Manoj Kahar BCL, Navsari.
43.
CONSEQUENCES OF INCORRECTRESULTS IN COAGULATION TESTING :-
1) a falsely prolonged “screening” coagulation test might influence
a clinical decision to undertake further costly and time consuming
(eg, “specific diagnostic”) investigations, unnecessarily delay
invasive procedures, and raise unnecessary anxiety in the patient
being investigated;
2) a false-normal screening test result might prevent further
evaluation of factor assays, thus incorrectly discounting hemophilia
and possibly placing a patient at an unjustified risk of bleeding with
invasive procedures (ie, surgery, dental extraction, biopsies); and
3) a false low or high coagulation test time in a patient being
monitored for anticoagulant therapy may lead to subsequent
incorrect dosing of anticoagulant therapy with a risk of thrombosis
or bleeding depending on the direction of the error.
Dr. Manoj Kahar BCL, Navsari. 43
44.
ADJUSTMENT OF CITRATECONCENTRATION FOR PATIENTS WITH HCT MORE THAN 55% (>0.55) :-
1. For patients with a hematocrit greater than 55% (>0.55), the evacuated tube or syringe
should have the appropriate volume of 3.2% citrate removed.
2. To calculate the amount of citrate to be present in the blood drawing tube or syringe,
use the following formula
C = (1.85 × )(100 – Hct)(VBlood)
where C is the volume of citrate remaining in the tube, Hct is the hematocrit of the patient,
and V is the volume of blood to be added. (If a 5-mL tube is used, the volume is 4.5 mL.)
3. A nomogram can be used (see appendix of CLSI document H21-A4 or the most current
version).
4. Add the correct amount of blood to the tube containing the adjusted citrate
concentration.
5. Mix and process the sample in the same manner as the other coagulation samples.
6. A note should be added to the laboratory record and patient record stating that the
hematocrit value was elevated and the citrate concentration adjusted.
7. For hematocrit values of less than 25% (<0.25), the citrate concentration does not need to
be adjusted.
Dr. Manoj Kahar BCL, Navsari.
44
45.
ADJUSTMENT OF RATIOOF BLOOD TO ANTICOAGULANT:-
The standard ratio of blood to anticoagulant of 9:1 is for normal haematocrit or PCV
- For occasional patients with PCV less than 20% (e.g.: Microcytic hypochromic anemia)
and greater than 55% (e.g.:Polycythemia vera) the anticoagulant to blood ratio must be
readjusted using the following formula,
C = 1.85 X 10⁻³ (100-H) V
C = Volume of sodium citrate in ml.
V = Volume of whole blood - Sodium citrate in ml
H = Haematocrit in percentage
- When the PCV is higher than 55% the patient blood contains so little plasma that excess
unutilized anticoagulant remains and is available to bind reagent calcium leading to
prolongation of test results.
- On the other hand if the PCV is less than 20% the patient blood contains excess of plasma
but less of anticoagulant and the chelating activity of citrate will not be sufficient to bind
the calcium present in sample. This will lead to formation of clots in vitro, consumption of
factors and prolongation of results.
45
Dr. Manoj Kahar BCL, Navsari.
46.
RATIO OF CITRATETO BLOOD :-
The optimum ratio of citrate to blood is 1 part of anticoagulant to 9 parts of
blood.
When the molarity of citrate is accurate the anticoagulant supplied in this
amount and ratio is sufficient to bind all the available calcium in the collected
sample so as to prevent clotting.
A shift in this ratio leads to erroneous results as follows:
More blood less citrate: The chelating activity of citrate will not be sufficient
to bind the calcium present in the sample.
- This will lead to formation of clots, consumption of factors an subsequent
prolongation of results during test.
More citrate less blood: Excess citrate remaining in the blood sample would
consume the calcium from the reagents thereby giving prolonged results.
46
Dr. Manoj Kahar BCL, Navsari.
47.
SAMPLE QUALITY CONTROLSPECIFICATIONS FOR COAGULATION AND HAEMOSTASIS :-
Dr. Manoj Kahar BCL, Navsari. 47
INTERNAL QUALITY CONTROLMATERIALS:-
In respect of hemostatic tests and assays, IQC
materials are stable over a restricted time period,
often dependent on the storage conditions.
For IQC materials it is advantageous for the same
batch or lot number of material to be used over a
period of months.
This limits the frequency with which the batch
number is changed and facilitates detection of drift
in the assay system under assessment.
49
Dr. Manoj Kahar BCL, Navsari.
50.
FREQUENCY OF IQCTESTING - 1
For tests that are performed in discrete batches at
least one level of QC material should be included
with each batch.
Where there is continuous processing, e.g. when
using many types of modern auto-analyzer, then a
QC sample should be included at regular intervals.
There is some evidence that a combination of IQC
testing at fixed time intervals with further IQC testing
performed randomly at additional times may be
better for detection of error conditions.
50
Dr. Manoj Kahar BCL, Navsari.
51.
FREQUENCY OF IQCTESTING - 2
When large numbers of samples are processed then QC
testing can be fixed at timed intervals or after a certain
number of test samples.
For screening tests such as PT/INR or aPTT in departments
processing more than 100 samples per day, testing every
2 hours is recommended.
Such, decisions should also take account of the
consequences of releasing incorrect results.
The frequency should be set so that recall of erroneous
patient results is avoided.
51
Dr. Manoj Kahar BCL, Navsari.
52.
FREQUENCY OF IQCTESTING - 3
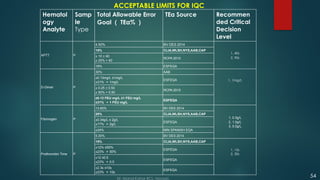
CLSI recommends testing at least two levels of control
material every 8 hours for all non-manual PT and aPTT
coagulation test systems.
CLSI also recommends that when continuous sample
processing occurs, as in many large laboratories in
established centers, then at least one from the two or three
levels of IQC should be alternately tested at least every 4
hours.
CLSI also states that the first test performed after reagent
addition or important instrument change should be the QC
sample. This is of particular importance after daily instrument
maintenance.
52
Dr. Manoj Kahar BCL, Navsari.
53.
QC FREQUENCY FORFIBRINOGEN TESTING
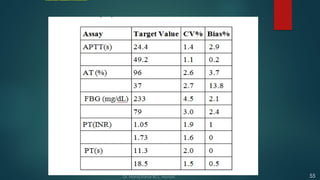
Inclusion of at least one abnormal control with a decreased fibrinogen level
of 0.8–1.2 g/L with each batch of samples has been recommended,
although in practice any abnormal control with a level between 0.3 and 1.4
g/L is probably suitable.
Testing normal and abnormal samples at a minimum of every 20 samples in
laboratories where many fibrinogen determinations are determined.
For current auto-analyzers, a single normal IQC every 20 samples is
acceptable for routine purposes.
The inclusion of an abnormal control at least daily gives additional
confidence that the method is under control for measurement at a level
where inaccurate results are of particular importance for patient
management.
53
Dr. Manoj Kahar BCL, Navsari.
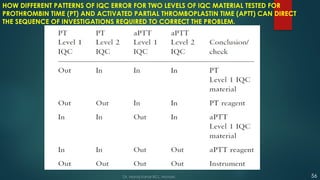
HOW DIFFERENT PATTERNSOF IQC ERROR FOR TWO LEVELS OF IQC MATERIAL TESTED FOR
PROTHROMBIN TIME (PT) AND ACTIVATED PARTIAL THROMBOPLASTIN TIME (APTT) CAN DIRECT
THE SEQUENCE OF INVESTIGATIONS REQUIRED TO CORRECT THE PROBLEM.
56
Dr. Manoj Kahar BCL, Navsari.
PREANALYTICAL VARIABLES INCOAGULATION TESTING: SETTING THE STAGE FOR
ACCURATE RESULTS :-
Preanalytical variables pertaining to routine
coagulation testing can be classified into three
major categories:
1) specimen collection (including patient selection),
(2) specimen transportation and stability, and
(3) specimen processing and storage.
Within each of these there are several individual
variables, each of which may have a major
impact on testing
Dr. Manoj Kahar BCL, Navsari. 61
62.
POSSIBLE CAUSES OFA PROLONGED APTT OR PT DUE TO PREANALYTICAL OR PATIENT-RELATED
ISSUES :-
Dr. Manoj Kahar BCL, Navsari. 62
63.
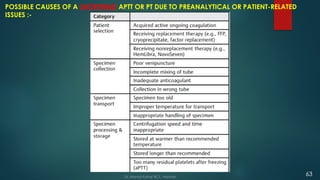
POSSIBLE CAUSES OFA SHORTENED APTT OR PT DUE TO PREANALYTICAL OR PATIENT-RELATED
ISSUES :-
Dr. Manoj Kahar BCL, Navsari.
63
64.
SUMMARY OF PREANALYTICALRECOMMENDATIONS FOR COAGULATION-RELATED TESTING :-
Dr. Manoj Kahar BCL, Navsari. 64
65.
Dr. Manoj KaharBCL, Navsari.
65
SUMMARY OF PREANALYTICAL RECOMMENDATIONS FOR COAGULATION-RELATED TESTING :-
66.
Dr. Manoj KaharBCL, Navsari. 66
SUMMARY OF PREANALYTICAL RECOMMENDATIONS FOR COAGULATION-RELATED TESTING :-
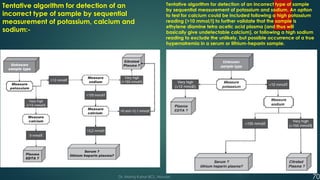
Tentative algorithm fordetection of an
incorrect type of sample by sequential
measurement of potassium, calcium and
sodium:-
70
Dr. Manoj Kahar BCL, Navsari.
Tentative algorithm for detection of an incorrect type of sample
by sequential measurement of potassium and sodium. An option
to test for calcium could be included following a high potassium
reading (>10 mmol/l) to further validate that the sample is
ethylene diamine tetra acetic acid plasma (and thus will
basically give undetectable calcium), or following a high sodium
reading to exclude the unlikely, but possible occurrence of a true
hypernatremia in a serum or lithium-heparin sample.
Dr. Manoj KaharBCL, Navsari.
75
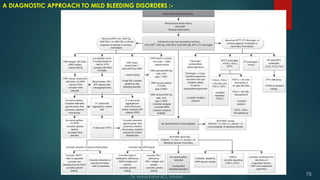
A DIAGNOSTIC APPROACH TO MILD BLEEDING DISORDERS :-
76.
REFERENCES :-
1) Hemostasispractice: state-of-the-art
Giuseppe Lippi, Emmanuel J. Favaloro. , J Lab Precis Med 2018;3:67, 07 August 2018.
doi: 10.21037/jlpm.2018.07.07.
2) Laboratory hemostasis: from biology to the bench , Giuseppe Lippi* and Emmanuel J. Favaloro , Clin Chem Lab Med
2018; aop , January 19, 2018 ,
https://doi.org/10.1515/cclm-2017-1205.
3) Preanalytical Variables in Coagulation Testing: Setting the Stage for Accurate Results , Robert C. Gosselin, CLS,
Richard A. Marlar, PhD , DOI https://doi.org/ 10.1055/s-0039-1692700 , Semin Thromb Hemost 2019;45:433–448.
4) Preanalytical and Postanalytical Variables: The Leading Causes of Diagnostic Error in Hemostasis? , Emmanuel J.
Favaloro, Ph.D., M.A.I.M.S., Giuseppe Lippi, M.D., and Dorothy M. Adcock, M.D. , Semin Thromb Hemost 2008;34:612–
634 , DOI 10.1055/s-0028-1104540. ISSN 0094-6176.
5) Pre-analytical Variables in Coagulation Testing Associated With Diagnostic Errors in Hemostasis. Emmanuel J.
Favaloro, et al. , DOI: 10.1309/LM749BQETKYPYPVM, February 2012 , Volume 43 Number 2 , LABMEDICINE.
6) Right or wrong sample received for coagulation testing? Tentative algorithms for detection of an incorrect type of
sample. G. LIPPI*, G. L. SALVAGNO et al. , doi:10.1111/j.1751-553X.2009.01142.x . 2009 Blackwell Publishing Ltd, Int. Jnl.
Lab. Hem. 2010.
7) Quality in coagulation and haemostasis testing. Roslyn Bonar, et al. , Biochemia Medica 2010;20(2):184–99
8) How I investigate for bleeding disorders. C. P. M. Hayward. Int J Lab Hem. 2018;40(Suppl. 1):6–14.
9) A diagnostic approach to mild bleeding disorders. Johan Boender, et al. J Thromb Haemost 2016; 14: 1507-16.
Dr. Manoj Kahar BCL, Navsari. 76




 Most read




 Most read