Audiologist Excellence Manual Dr J L Meena
Audiologist Excellence Manual โ€“ Dr J L Meena | Page 1
AUDIOLOGIST
EXCELLENCE MANUAL
Global Standards for Audiology Excellence, Hearing & Balance Care, and Quality
Healthcare
A Comprehensive Reference for
THE MULTIDISCIPLINARY AUDIOLOGY TEAM
Audiologists โ€ข Newborn Hearing Screening Specialists โ€ข Hearing Aid & Cochlear Implant Specialists โ€ข Vestibular
& Allied Professionals
โ€œA Child's Brain Only Waits So Long for Sound โ€” We Screen by One Month, Diagnose by
Three, Intervene by Six, Because a Missed Window for Language Can Never Be Reopened.โ€
Dr J L Meena
Audiologist Excellence Manual Dr J L Meena
Audiologist Excellence Manual โ€“ Dr J L Meena | Page 2
DEDICATION
This book is dedicated to all those who are committed to advancing healthcare through a discipline that races against
a genuinely closing window: an infant's brain is only so patient for sound before the neural pathways for spoken
language begin to organize around whatever input, or absence of input, it actually receives. A hearing loss missed at
birth is invisible, painless, and utterly silent โ€” and every month it goes undetected is a month of language
development that can never fully be recovered.
To Every Infant Screened Before They Ever Left the Hospital
For whom a newborn hearing screening performed correctly, a diagnostic confirmation completed by three months,
and an intervention begun by six months represents a promise kept: that the window for spoken language was found
open, and was not allowed to narrow while a hearing loss went unnoticed.
To Every Patient Whose Progressive Hearing Loss Was Caught Before It Became Severe
For whom regular audiological monitoring, whether for age-related change, noise exposure, or ototoxic medication,
caught a decline early enough to intervene meaningfully, rather than after the damage had become extensive and
irreversible.
To My Family
For their unwavering love, patience, and encouragement, which have been the foundation of this journey.
To My Mentors & Teachers
For inspiring my passion, guiding my path, and instilling in me the understanding that audiology confronts a disability
that is genuinely invisible โ€” no outward sign announces a newborn's hearing loss, no visible marker distinguishes a
noise-damaged ear from a healthy one โ€” and that time itself, particularly in the first months of a child's life, is a
resource that cannot be recovered once spent.
To My Colleagues & Friends
For their support, collaboration, and shared dedication to a discipline where the difference between screening a
newborn correctly on the first attempt and needing a rescreen is measured in weeks that a child's developing brain
does not have to spare.
To Every Member of the Audiology Team
Audiologists, newborn hearing screening specialists, hearing aid and cochlear implant specialists, and every
professional who has fitted one more device precisely enough to genuinely restore access to sound โ€” the guardians
of a sense whose loss is silent, and whose window for full recovery is genuinely finite.
Your vigilance, your race against a genuinely closing window, and your unwavering commitment to catching a
silent, invisible loss before it becomes permanent are the silent pillars of a healthcare system that gives every
child, and every patient, the fullest possible chance to hear the world around them. This book is for you, and
because of you. Thank you to everyone who has been a part of this journey.
Dr J L Meena
Audiologist Excellence Manual Dr J L Meena
Audiologist Excellence Manual โ€“ Dr J L Meena | Page 3
FOREWORD
There is a discipline in healthcare that races against a genuinely closing window: an infant's brain is only so
patient for sound before the neural pathways for spoken language begin to organize around whatever input,
or absence of input, it actually receives. A hearing loss missed at birth produces no outward sign at all โ€” it is
invisible, painless, and utterly silent โ€” and unlike many conditions where a delay of a few months carries
modest consequence, every month a congenital hearing loss goes undetected is a month of critical language-
acquisition neuroplasticity that cannot fully be recovered later. This is what the internationally recognized โ€œ1-
3-6โ€ principle exists to prevent: screen every newborn's hearing by one month of age, complete diagnostic
confirmation by three months, and begin intervention by six months, because the alternative is a child who
reaches school age with a spoken-language gap that need never have opened at all.
The โ€œAudiologist Excellence Manual: Global Standards for Audiology Excellence, Hearing & Balance Care, and
Quality Healthcareโ€ has been developed to provide a comprehensive professional framework for the
multidisciplinary Audiology team โ€” Audiologists, newborn hearing screening specialists, hearing aid and
cochlear implant specialists, and allied vestibular professionals โ€” working together across the full lifespan,
from a newborn's first hearing screen to an elderly patient's balance assessment.
This manual brings together internationally recognized principles of universal newborn hearing screening and
the 1-3-6 timeline, diagnostic audiological assessment across the lifespan, precise hearing aid and cochlear
implant fitting and verification, vestibular and balance assessment, tinnitus management, ototoxicity
monitoring, and occupational hearing conservation. It is built around globally accepted accreditation
frameworks โ€” the World Health Organization's World Report on Hearing, NABH, JCI, and international
standards from the American Academy of Audiology (AAA) and the Joint Committee on Infant Hearing (JCIH)
โ€” to provide a rigorous, regulation-compliant framework for Audiology excellence.
The chapters of this manual guide the Audiology team through every dimension of the role โ€” from time-critical
newborn hearing screening and diagnostic confirmation, through precise hearing device fitting and verification,
to vestibular assessment, hearing conservation, and the professional conduct that defines excellence across
every category of audiology practice: the newborn screened correctly before hospital discharge, the diagnostic
confirmation completed within the critical three-month window rather than allowed to drift, and the hearing
aid fitted and verified with real-ear measurement precision rather than simply handed over and assumed to
work.
Audiology is not simply a service that tests hearing and dispenses hearing aids โ€” it is a distinct discipline built
on the understanding that hearing loss is frequently invisible with no outward sign at all, that the earliest
months of a child's life represent a genuinely finite window for spoken language development that cannot be
reopened once it narrows, and that this team's speed and precision in that window is often the single greatest
determinant of a child's lifelong communication outcome. Their work is defined by a vigilance that treats every
week of delay as a cost that cannot later be refunded.
Audiologist Excellence Manual Dr J L Meena
Audiologist Excellence Manual โ€“ Dr J L Meena | Page 4
It is hoped that this manual will serve as an indispensable resource for Audiologists, newborn hearing screening
specialists, hearing aid and cochlear implant specialists, hospital administrators, quality heads, and all those
committed to building a healthcare system where no child's window for spoken language closes for want of a
screening, a diagnosis, or an intervention delivered on time.
โ€œA Child's Brain Only Waits So Long for Sound โ€” We Screen by One Month, Diagnose by Three, Intervene
by Six, Because a Missed Window for Language Can Never Be Reopened.โ€
With Best Wishes, Dr J L Meena
Audiologist Excellence Manual Dr J L Meena
Audiologist Excellence Manual โ€“ Dr J L Meena | Page 5
TABLE OF CONTENTS
FOREWORD............................................................................................................................................3
LIST OF ABBREVIATIONS........................................................................................................................8
MANUAL MOTTO.................................................................................................................................10
CHAPTER 1: Introduction.....................................................................................................................11
Purpose...........................................................................................................................................................11
Objectives .......................................................................................................................................................12
Vision & Mission .............................................................................................................................................13
CHAPTER 2: Role of the Audiology Team in Quality Healthcare ........................................................14
Universal Newborn Hearing Screening & the 1-3-6 Rule................................................................................14
Diagnostic Audiological Assessment Across the Lifespan...............................................................................14
Hearing Aid Fitting & Verification...................................................................................................................15
Cochlear Implant Candidacy & Programming.................................................................................................15
Vestibular & Balance Assessment...................................................................................................................16
Tinnitus Management.....................................................................................................................................16
Ototoxicity Monitoring ...................................................................................................................................17
Occupational Hearing Conservation ...............................................................................................................17
CHAPTER 3: Professional Standards for the Audiology Team ............................................................17
Professional Appearance & Behaviour ...........................................................................................................17
Communication Standards .............................................................................................................................18
Confidentiality & Information Security...........................................................................................................19
Ethical Standards ............................................................................................................................................19
Time Management, Teamwork & Continuous Learning.................................................................................20
CHAPTER 4: Patient- and Family-Centered Communication in Audiology.........................................21
The A-T-C-R-C Communication Model............................................................................................................21
Communicating a New Hearing Loss Diagnosis to Families............................................................................22
CHAPTER 5: Patient Safety and Time-Critical Screening Standards ...................................................23
The R-T-A-C-A Framework ..............................................................................................................................23
Daily Quality Standards Checklist ...................................................................................................................25
CHAPTER 6: Confidentiality, Privacy, and Information Security ........................................................27
Privacy in Audiology Practice..........................................................................................................................27
Cybersecurity of Audiology Information Systems...........................................................................................28
CHAPTER 7: Standard Operating Procedures (SOPs)..........................................................................29
SOP 1: Universal Newborn Hearing Screening................................................................................................29
SOP 2: Diagnostic Follow-Up Within the 1-3-6 Timeline ................................................................................29
Audiologist Excellence Manual Dr J L Meena
Audiologist Excellence Manual โ€“ Dr J L Meena | Page 6
SOP 3: Diagnostic Audiological Assessment ...................................................................................................30
SOP 4: Hearing Aid Fitting and Real-Ear Verification......................................................................................30
SOP 5: Cochlear Implant Candidacy and Programming..................................................................................31
SOP 6: Vestibular and Balance Assessment....................................................................................................31
SOP 7: Tinnitus Assessment and Management ..............................................................................................32
SOP 8: Ototoxicity Monitoring Protocol .........................................................................................................32
SOP 9: Occupational Hearing Conservation Program.....................................................................................33
SOP 10: Equipment Calibration and Sound Booth Quality Control.................................................................33
CHAPTER 8: Communication with Special Groups..............................................................................34
CHAPTER 9: Handling Difficult Situations ...........................................................................................36
CHAPTER 10: Emergency Response โ€” Critical Audiology Presentations...........................................39
CHAPTER 11: Digital Competency for the Audiology Team................................................................42
CHAPTER 12: Daily Audiology Checklist ..............................................................................................44
CHAPTER 13: Key Performance Indicators (KPIs)................................................................................46
CHAPTER 14: Top 20 Do's & Top 20 Don'ts.........................................................................................48
CHAPTER 15: Audiology Professional Pledge......................................................................................51
CONCLUSION........................................................................................................................................53
REFERENCES.........................................................................................................................................54
Audiologist Excellence Manual Dr J L Meena
Audiologist Excellence Manual โ€“ Dr J L Meena | Page 7
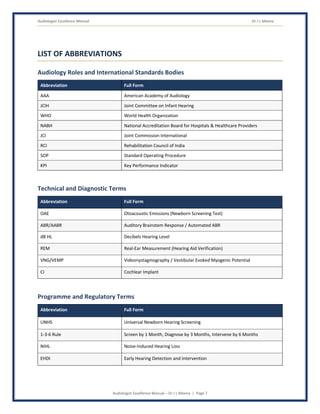
LIST OF ABBREVIATIONS
Audiology Roles and International Standards Bodies
Abbreviation Full Form
AAA American Academy of Audiology
JCIH Joint Committee on Infant Hearing
WHO World Health Organization
NABH National Accreditation Board for Hospitals & Healthcare Providers
JCI Joint Commission International
RCI Rehabilitation Council of India
SOP Standard Operating Procedure
KPI Key Performance Indicator
Technical and Diagnostic Terms
Abbreviation Full Form
OAE Otoacoustic Emissions (Newborn Screening Test)
ABR/AABR Auditory Brainstem Response / Automated ABR
dB HL Decibels Hearing Level
REM Real-Ear Measurement (Hearing Aid Verification)
VNG/VEMP Videonystagmography / Vestibular Evoked Myogenic Potential
CI Cochlear Implant
Programme and Regulatory Terms
Abbreviation Full Form
UNHS Universal Newborn Hearing Screening
1-3-6 Rule Screen by 1 Month, Diagnose by 3 Months, Intervene by 6 Months
NIHL Noise-Induced Hearing Loss
EHDI Early Hearing Detection and Intervention
Audiologist Excellence Manual Dr J L Meena
Audiologist Excellence Manual โ€“ Dr J L Meena | Page 8
Governance and Documentation Terms
Abbreviation Full Form
SBAR Situation, Background, Assessment, Recommendation
RCA Root Cause Analysis
CAPA Corrective and Preventive Action
EMR/HIS Electronic Medical Record / Hospital Information System
Recommended Note for Manual
The abbreviations in this manual assist Audiologists, newborn hearing screening specialists, hearing aid and
cochlear implant specialists, hospital administrators, quality professionals, and all healthcare staff in
understanding commonly used terms related to hearing screening, diagnostic assessment, and audiology
quality standards.
Quick Reference โ€“ Most Frequently Used Abbreviations
โ— UNHS โ€“ Universal Newborn Hearing Screening
โ— 1-3-6 Rule โ€“ Screen by 1, Diagnose by 3, Intervene by 6 Months
โ— OAE โ€“ Otoacoustic Emissions
โ— ABR/AABR โ€“ Auditory Brainstem Response / Automated ABR
โ— REM โ€“ Real-Ear Measurement
โ— CI โ€“ Cochlear Implant
โ— NIHL โ€“ Noise-Induced Hearing Loss
โ— EHDI โ€“ Early Hearing Detection and Intervention
โ— SOP โ€“ Standard Operating Procedure
โ— KPI โ€“ Key Performance Indicator
Audiologist Excellence Manual Dr J L Meena
Audiologist Excellence Manual โ€“ Dr J L Meena | Page 9
MANUAL MOTTO
โ€œA Child's Brain Only Waits So Long for Sound โ€”โ€
โ€œWe Screen by One, Diagnose by Three, Intervene by Six
โ€”โ€
โ€œBecause a Missed Window Can Never Be Reopened.โ€
Audiologist Excellence Manual Dr J L Meena
Audiologist Excellence Manual โ€“ Dr J L Meena | Page 10
CHAPTER 1: INTRODUCTION
1. Purpose
There is a discipline in healthcare that races against a genuinely closing window: an infant's brain is only so
patient for sound before the neural pathways for spoken language begin to organize around whatever input,
or absence of input, it actually receives. A hearing loss missed at birth produces no outward sign at all โ€” it is
invisible, painless, and utterly silent. This manual exists because this invisibility, paired with a genuinely finite
developmental window, demands a discipline of speed and precision that treats every week of delay as a cost
that cannot later be refunded.
The World Health Organization and international audiology bodies โ€” AAA, JCIH โ€” recognize that universal
newborn hearing screening completed within the internationally recommended 1-3-6 timeline, and rigorous
diagnostic and rehabilitative practice across the lifespan, are directly and measurably linked to significantly
better spoken language and educational outcomes for children with hearing loss. Research consistently
demonstrates that audiology services applying standardized screening protocols, timely diagnostic follow-up,
and precise, verified hearing device fitting achieve dramatically and measurably better outcomes than services
where screening, diagnosis, or intervention drifts past the critical developmental window. In institutions where
the Audiology team applies systematic screening discipline, rigorous verification, and honest, complete family
communication, patient outcomes are demonstrably and measurably better. The investment in Audiology
excellence is, without qualification, one of the highest-yield investments any healthcare system can make โ€”
because a window for spoken language, once closed, cannot be reopened.
Why the Audiology Team Is Critical to Healthcare Quality
โ— Provides universal newborn hearing screening, catching an invisible, painless condition before it can
silently narrow a child's window for spoken language.
โ— Applies rigorous diagnostic follow-up within the internationally recommended 1-3-6 timeline, ensuring
no child's diagnosis or intervention drifts past the critical window.
โ— Delivers diagnostic audiological assessment across the full lifespan, from infant hearing loss to age-
related decline.
โ— Applies precise hearing aid fitting and verification, ensuring devices genuinely restore functional
access to sound rather than being assumed to work.
โ— Provides cochlear implant candidacy assessment and programming, restoring hearing access for
patients with severe to profound loss.
โ— Applies vestibular and balance assessment, addressing a frequently overlooked but genuinely disabling
condition.
โ— Delivers tinnitus management, improving quality of life for patients with this frequently distressing
condition.
Audiologist Excellence Manual Dr J L Meena
Audiologist Excellence Manual โ€“ Dr J L Meena | Page 11
โ— Applies ototoxicity monitoring and occupational hearing conservation, preventing avoidable,
irreversible hearing loss.
โ— Contributes to accreditation compliance (NABH, JCI, AAA) for audiology service standards.
Key Responsibilities of the Audiology Team
โ— Applying universal newborn hearing screening before hospital discharge or within the recommended
timeframe.
โ— Applying rigorous diagnostic follow-up within the 1-3-6 timeline for every referred infant.
โ— Applying comprehensive diagnostic audiological assessment across the lifespan.
โ— Applying precise hearing aid fitting with real-ear measurement verification.
โ— Applying cochlear implant candidacy assessment and post-implantation programming.
โ— Applying vestibular assessment for patients with balance complaints.
โ— Applying ototoxicity monitoring for patients on ototoxic medication regimens.
โ— Engaging in continuous professional development to maintain competence in evolving audiology
evidence.
2. Objectives
1. Never Let the Window Close Unnoticed
Every newborn must be screened, every referred infant must be diagnosed by three months, and every
confirmed hearing loss must begin intervention by six months โ€” this is the Audiology team's foundational,
non-negotiable obligation, because a hearing loss that goes undetected during this window costs a child
language development that cannot later be fully recovered.
How to Achieve:
โ— Apply universal newborn hearing screening without exception, before discharge or within the
recommended window.
โ— Apply rigorous tracking and follow-up ensuring no referred infant is lost before diagnostic
confirmation.
โ— Never allow scheduling or resource constraints to delay a diagnosis or intervention past the critical
timeline.
2. Diagnose Accurately Across the Lifespan
โ— Apply comprehensive, evidence-based diagnostic assessment matched to the patient's age and
presentation.
โ— Apply differential diagnosis distinguishing conductive, sensorineural, and mixed hearing loss.
3. Fit and Verify Devices Precisely
โ— Apply real-ear measurement verification for every hearing aid fitting.
โ— Never assume a device functions correctly without genuine, objective verification.
Audiologist Excellence Manual Dr J L Meena
Audiologist Excellence Manual โ€“ Dr J L Meena | Page 12
4. Address the Full Scope of Auditory and Vestibular Health
โ— Apply vestibular assessment for patients with balance complaints.
โ— Apply tinnitus management supporting genuine quality-of-life improvement.
5. Prevent Avoidable Hearing Loss
โ— Apply rigorous ototoxicity monitoring for at-risk patients.
โ— Apply occupational hearing conservation programme support.
6. Communicate Honestly and Compassionately with Families
โ— Communicate a new hearing loss diagnosis honestly, compassionately, and completely.
โ— Support genuine, informed family decision-making about intervention options.
7. Maintain Regulatory and Accreditation Compliance
โ— Comply with national audiology standards and international accreditation guidelines.
โ— Maintain NABH/JCI/AAA audiology documentation standards.
โ— Participate in accreditation surveys with complete, auditable screening and diagnostic timeline
records.
3. Vision
Vision Statement
โ€œTo build and maintain an Audiology service where every newborn is screened, every diagnosis is confirmed
within the critical window, every hearing device is precisely verified, and no patient's window for spoken
language or quality of life is ever narrowed by an avoidable delay.โ€
4. Mission
Mission Statement
โ€œTo deliver time-critical, evidence-based, and rigorously verified audiology services across the full lifespan,
through universal newborn hearing screening within the 1-3-6 timeline, precise diagnostic assessment, verified
device fitting, and honest family communication, enabling every patient to access the fullest possible
experience of sound, however their hearing may be affected.โ€
Expected Outcomes of an Excellent Audiology Practice
โ— 100% of newborns screened before discharge or within the recommended timeframe.
โ— 100% of referred infants receive diagnostic confirmation by three months of age.
โ— 100% of confirmed hearing losses begin intervention by six months of age.
โ— 100% of hearing aid fittings verified through real-ear measurement.
โ— Full compliance with national audiology standards and international accreditation guidelines.
Audiologist Excellence Manual Dr J L Meena
Audiologist Excellence Manual โ€“ Dr J L Meena | Page 13
The Audiology team races against a genuinely closing window โ€” an infant's brain is only so patient for
sound before the neural pathways for spoken language begin to organize around whatever input it
receives. Their screening discipline, diagnostic speed, and verification rigour are what ensure that window
is never allowed to close for want of a test performed on time.
Audiologist Excellence Manual Dr J L Meena
Audiologist Excellence Manual โ€“ Dr J L Meena | Page 14
CHAPTER 2: ROLE OF THE AUDIOLOGY TEAM IN QUALITY HEALTHCARE
1. Universal Newborn Hearing Screening and the 1-3-6 Rule
Overview
Because congenital hearing loss produces no outward sign, universal screening of every newborn, followed by
diagnostic confirmation by three months and intervention by six months, is the only reliable safeguard against
a silently narrowing developmental window.
Responsibilities
โ— Apply universal newborn hearing screening before discharge or within the recommended timeframe.
โ— Apply rigorous tracking ensuring no referred infant is lost before diagnostic confirmation.
2. Diagnostic Audiological Assessment Across the Lifespan
Overview
Hearing loss affects every stage of life differently, from congenital and early childhood loss through noise-
induced and age-related decline, each requiring assessment matched to the specific population.
Responsibilities
โ— Apply comprehensive, evidence-based diagnostic assessment matched to patient age and
presentation.
โ— Apply differential diagnosis distinguishing conductive, sensorineural, and mixed hearing loss.
3. Hearing Aid Fitting and Verification
Overview
A hearing aid that is fitted but not objectively verified may not actually be delivering the amplification a
patient's hearing loss requires โ€” real-ear measurement is what confirms a device genuinely works.
Responsibilities
โ— Apply real-ear measurement verification for every hearing aid fitting.
โ— Apply genuine patient and family counselling supporting realistic expectations and consistent use.
4. Cochlear Implant Candidacy and Programming
Overview
For patients with severe to profound hearing loss who do not benefit sufficiently from hearing aids, cochlear
implants offer restored access to sound, requiring careful candidacy assessment and precise post-implantation
programming.
Audiologist Excellence Manual Dr J L Meena
Audiologist Excellence Manual โ€“ Dr J L Meena | Page 15
Responsibilities
โ— Apply rigorous, evidence-based candidacy assessment.
โ— Apply precise post-implantation programming and ongoing optimization.
5. Vestibular and Balance Assessment
Overview
Balance disorders are frequently overlooked but genuinely disabling, requiring specialized vestibular
assessment to identify the underlying cause and guide appropriate management.
Responsibilities
โ— Apply comprehensive vestibular assessment for patients with balance complaints.
โ— Coordinate closely with medicine and vestibular rehabilitation for integrated management.
6. Tinnitus Management
Overview
Tinnitus can significantly impair quality of life, requiring evidence-based assessment and management
supporting genuine symptom relief and coping.
Responsibilities
โ— Apply comprehensive tinnitus assessment identifying contributing factors.
โ— Apply evidence-based management, including sound therapy and counselling approaches.
7. Ototoxicity Monitoring
Overview
Certain medications carry a genuine risk of causing hearing loss, making baseline and serial monitoring for
patients on ototoxic regimens an essential preventive safeguard.
Responsibilities
โ— Apply baseline and serial audiological monitoring for patients on ototoxic medication.
โ— Communicate any identified change promptly to the prescribing physician.
8. Occupational Hearing Conservation
Overview
Noise-induced hearing loss is entirely preventable, making occupational hearing conservation programme
support a genuine public health contribution.
Responsibilities
โ— Apply baseline and periodic audiometric monitoring for noise-exposed workers.
โ— Support hearing protection education and programme compliance.
Audiologist Excellence Manual Dr J L Meena
Audiologist Excellence Manual โ€“ Dr J L Meena | Page 16
How the Audiology Team Contributes to Quality Healthcare
โ— By screening every newborn universally, the team catches an invisible condition before it can silently
narrow a child's developmental window.
โ— By diagnosing within the 1-3-6 timeline, the team ensures no child's intervention drifts past the critical
period.
โ— By verifying every hearing device objectively, the team ensures a fitted aid genuinely restores
functional access to sound.
โ— By monitoring ototoxicity and supporting hearing conservation, the team prevents entirely avoidable,
irreversible hearing loss.
โ— By assessing vestibular function, the team addresses a frequently overlooked but genuinely disabling
condition.
The Audiology team races against a genuinely closing window โ€” an infant's brain is only so patient for
sound before the neural pathways for spoken language begin to organize around whatever input it
receives. Their screening discipline, diagnostic speed, and verification rigour are what ensure that window
is never allowed to close for want of a test performed on time.
Audiologist Excellence Manual Dr J L Meena
Audiologist Excellence Manual โ€“ Dr J L Meena | Page 17
CHAPTER 3: PROFESSIONAL STANDARDS FOR THE AUDIOLOGY TEAM
Audiology practice requires an uncommon combination of the urgency to treat every week of an infant's
undiagnosed hearing loss as a genuine developmental cost, the technical precision to verify a hearing device
objectively rather than assume it works, and the compassion to guide a family through a diagnosis that
reshapes how they imagine their child's future. The standards that govern Audiology practice derive from a
discipline whose central condition, hearing loss, is frequently entirely invisible until deliberately, specifically
tested for.
1. Professional Appearance
Standards
Attire and Identification
โ— Wear appropriate professional attire and ID badge as per facility policy.
Professional Presence
โ— Maintain rigorous attention to screening and diagnostic timelines throughout every shift.
โ— Model unwavering urgency for time-critical infant hearing screening and follow-up.
2. Professional Behaviour
Expected Behaviours
Screening and Timeline Discipline
โ— Never allow a newborn to be discharged without documented hearing screening or an appropriate,
tracked follow-up plan.
โ— Never allow a referred infant's diagnostic follow-up to drift past the three-month window without
active, persistent tracking.
Verification Discipline
โ— Never conclude a hearing device is functioning correctly without objective, real-ear verification.
โ— Escalate immediately upon any identified screening, tracking, or verification gap.
Accountability
โ— Own every screening decision, every diagnostic determination, and every fitting verification made
under this team's responsibility.
โ— Report and disclose critical incidents and adverse events honestly and promptly.
Audiologist Excellence Manual Dr J L Meena
Audiologist Excellence Manual โ€“ Dr J L Meena | Page 18
Collaborative Respect
โ— Treat every member of the multidisciplinary Audiology team โ€” audiologist, screening specialist,
hearing aid specialist โ€” as an essential, equal partner.
Patient-Centered Focus
โ— Every screening and every verification is ultimately about a patient's fullest possible access to sound
โ€” never about convenience or speed for its own sake.
3. Communication Standards
Communication with Patients and Families
โ— Communicate a new hearing loss diagnosis honestly, compassionately, and completely.
โ— Communicate device fitting expectations and realistic outcomes honestly.
Communication Within the Team
โ— Communicate any tracking gap or verification uncertainty rapidly and clearly.
โ— Use structured handover tools (SBAR or equivalent) for every transfer of patient responsibility.
โ— Escalate any missed screening or diagnostic timeline concern immediately and directly.
Written Communication Standards
โ— Audiology documentation must be accurate, contemporaneous, and complete, reflecting screening,
diagnostic, and verification rationale.
โ— Reports must be exact and free of language that could be misinterpreted regarding hearing status or
device function.
4. Confidentiality and Information Security
Overview
Audiology involves sensitive diagnostic information, including newborn screening results and diagnostic
hearing loss determinations, requiring heightened confidentiality discipline.
Responsibilities
โ— Discuss patient and screening information only in appropriate settings and only with those who have
a legitimate need to know.
โ— Protect access credentials for EMR/HIS and audiology information systems.
โ— Apply particular discretion for sensitive newborn screening and diagnostic information.
Audiologist Excellence Manual Dr J L Meena
Audiologist Excellence Manual โ€“ Dr J L Meena | Page 19
5. Ethical Standards
Core Ethical Principles for Audiology Practice
Non-Maleficence
โ— Never allow a known screening or tracking gap to persist unaddressed.
โ— Never conclude device function without genuine, objective verification.
Beneficence
โ— Apply rigorous, evidence-based practice consistently, ensuring the most accurate diagnosis and
effective intervention achievable.
Honesty and Transparency
โ— Communicate genuine diagnostic uncertainty, device limitations, and any error honestly.
Justice and Equity
โ— Apply the same rigorous screening and diagnostic standard to every patient, regardless of setting, age,
or socioeconomic background.
6. Time Management and Prioritization
Clinical Priority Framework
โ— Immediate/Emergency: Sudden sensorineural hearing loss requiring urgent medical referral โ€”
immediate response, no delay.
โ— Urgent: Referred infant approaching the three-month diagnostic deadline โ€” prompt, prioritized
scheduling.
โ— Routine: Standard diagnostic and rehabilitative care โ€” managed per defined schedule, with
unwavering thoroughness.
7. Teamwork and Collaboration
Work Effectively With
โ— Paediatrics and neonatology โ€” for newborn screening coordination and referral.
โ— ENT and neurology โ€” for medical evaluation of confirmed hearing loss and vestibular disorders.
โ— Early intervention and speech-language therapy โ€” for integrated developmental support.
โ— Quality department โ€” for incident reporting, RCA, and accreditation support.
8. Professional Competence and Continuous Learning
Areas of Competence
โ— Universal newborn hearing screening methodology and the 1-3-6 timeline.
โ— Diagnostic audiological assessment across the lifespan.
Audiologist Excellence Manual Dr J L Meena
Audiologist Excellence Manual โ€“ Dr J L Meena | Page 20
โ— Hearing aid and cochlear implant fitting and verification technique.
โ— Vestibular assessment methodology.
โ— FMEA, RCA, and CAPA methodologies for audiology-specific quality improvement.
Continuous Learning
โ— Maintain current certification in relevant audiology competencies.
โ— Maintain current knowledge of evolving audiology evidence and guidelines (AAA, JCIH, WHO).
โ— Engage with national and international audiology professional bodies.
โ— Participate regularly in newborn screening and device verification simulation training.
โ— Participate in NABH, JCI, and AAA accreditation training for audiology standards.
Professional Standards Checklist
โ— Have I applied universal newborn hearing screening to every applicable infant today?
โ— Have I tracked every referred infant toward diagnostic confirmation within the three-month window?
โ— Have I applied real-ear measurement verification to every hearing aid fitting?
โ— Have I communicated honestly and compassionately with every family today?
โ— Have I applied appropriate ototoxicity or occupational monitoring where indicated?
โ— Have I reported any incident or safety concern through the appropriate system?
Audiology professionalism is urgency applied to a genuinely closing developmental window, paired with
the rigour to verify every device objectively rather than assume it works โ€” the team that tracks every
infant relentlessly and verifies every fitting is the team that ensures no patient's access to sound is ever
narrowed by an avoidable delay.
Audiologist Excellence Manual Dr J L Meena
Audiologist Excellence Manual โ€“ Dr J L Meena | Page 21
CHAPTER 4: PATIENT- AND FAMILY-CENTERED COMMUNICATION IN
AUDIOLOGY
Communication in Audiology must accomplish something genuinely distinctive: families receiving a new infant
hearing loss diagnosis are often processing profound, unexpected news about their child's future, while
simultaneously needing to absorb urgent, time-sensitive information about intervention options that cannot
wait for their grief to fully settle.
Why Communication Quality Matters in Audiology
โ— Honest, compassionate delivery of a new hearing loss diagnosis supports genuine family adjustment
and informed decision-making.
โ— Clear communication about the urgency of the 1-3-6 timeline helps families understand why prompt
action, even amid grief, genuinely matters.
โ— Realistic communication about hearing aid or cochlear implant expectations prevents discouragement
from unmet expectations.
โ— Compassionate communication about progressive or sudden hearing loss in adults supports genuine
emotional adjustment.
The A-T-C-R-C Communication Model for Audiology
A โ€” Acknowledge
Definition
Acknowledge the genuine emotional weight of a new hearing loss diagnosis, for a child or an adult.
Examples
โ— โ€œI know this isn't the news you were expecting today โ€” let's take the time you need, and then talk
through exactly what this means and what we can do.โ€
T โ€” Listen (Elicit Genuine Concerns and Priorities)
Definition
Listen genuinely to the family's specific concerns, questions, and priorities for their child's or their own
communication future.
C โ€” Clarify (Communicate Findings and Options Honestly)
Definition
Communicate the diagnosis, its severity, and the full range of genuinely appropriate intervention options in
clear, non-technical language.
Audiologist Excellence Manual Dr J L Meena
Audiologist Excellence Manual โ€“ Dr J L Meena | Page 22
Examples
โ— โ€œYour baby has a hearing loss in both ears. This does not mean they cannot learn to communicate โ€”
it means we need to act soon, and there are real, effective options to help them do that.โ€
R โ€” Respond (Answer Questions Honestly)
Definition
Respond to questions honestly, including honest disclosure of genuine uncertainty about prognosis or device
outcomes.
C โ€” Confirm (Verify Genuine Understanding)
Definition
Confirm the family genuinely understands the diagnosis, the urgency of next steps, and the options available
before they leave.
Communicating a New Hearing Loss Diagnosis to Families
Principles for Communicating Diagnosis Honestly
โ— Communicate the diagnosis clearly and honestly, without unnecessary alarm or false reassurance.
โ— Communicate the genuine urgency of timely intervention without overwhelming a family already
processing difficult news.
Communicating Device Expectations Realistically
โ— Communicate hearing aid and cochlear implant outcomes honestly, avoiding both understatement
and overpromising.
โ— Communicate the genuine adjustment period and ongoing support available.
Communicating with Adults Facing New or Progressive Hearing Loss
โ— Communicate honestly about genuine prognosis and realistic expectations for intervention.
โ— Communicate compassionately, recognizing the genuine identity and social impact of hearing loss.
Common Audiology Communication Mistakes to Avoid
โ— Overwhelming a newly diagnosed family with excessive technical detail before they have processed
the initial news.
โ— Failing to communicate the genuine urgency of the 1-3-6 timeline clearly enough for a family to act on
it.
โ— Overpromising hearing aid or cochlear implant outcomes, risking discouragement later.
โ— Failing to verify genuine family understanding before they leave the appointment.
Audiologist Excellence Manual Dr J L Meena
Audiologist Excellence Manual โ€“ Dr J L Meena | Page 23
Communication in Audiology must deliver genuinely urgent information to families who are simultaneously
absorbing profound news โ€” the team that communicates honestly, compassionately, and with verified
understanding protects both a family's emotional wellbeing and a child's genuinely time-critical
developmental window.
Audiologist Excellence Manual Dr J L Meena
Audiologist Excellence Manual โ€“ Dr J L Meena | Page 24
CHAPTER 5: PATIENT SAFETY AND TIME-CRITICAL SCREENING
STANDARDS
Patient safety in Audiology is uniquely defined by a genuinely closing developmental window โ€” a service that
screens universally, tracks relentlessly, and verifies every device objectively produces measurably better
lifelong outcomes than one where any of these safeguards is compressed by resource constraints or
assumption. The R-T-A-C-A framework applies with particular intensity to a discipline whose central risk is
silent, invisible, and time-limited all at once.
1. RESPECT
Definition
Treating every newborn's screening and every referred infant's diagnostic timeline as equally deserving of the
Audiology team's full urgency, regardless of resource pressure or how routine a screening day appears.
How the Audiology Team Demonstrates Respect
โ— Respect for the Genuinely Finite Window: Apply the same urgency to the thousandth newborn
screening as to the first.
โ— Respect for Genuine Device Verification: Never assume a hearing aid works without objective, real-ear
confirmation.
โ— Respect for Every Team Member's Vigilance: Value the screening specialist's tracking discipline as
highly as the audiologist's diagnostic determination.
โ— Equal Service Standards: Apply the same rigorous protocol to every patient, regardless of setting or
socioeconomic background.
2. TIMELINESS
Definition
Recognizing that the 1-3-6 timeline is not an administrative target but a genuine developmental deadline, and
responding to it with an urgency that never allows drift, while still applying the full diagnostic thoroughness
every assessment requires.
Why Timeliness Is a Patient Safety Issue โ€” and Why It Cuts Both Ways
A missed newborn screening or a diagnostic confirmation that drifts past three months can mean a child's
spoken-language window narrows before intervention ever begins. Yet the opposite lesson applies equally:
rushing a diagnostic assessment to simply meet the deadline on paper, without genuine thoroughness, can
produce an inaccurate diagnosis just as costly as a delayed one. Timeliness in Audiology means treating the 1-
3-6 timeline as a genuine deadline while still applying the full diagnostic rigour every assessment requires
within it.
Audiologist Excellence Manual Dr J L Meena
Audiologist Excellence Manual โ€“ Dr J L Meena | Page 25
Audiology Timeliness Standards
โ— Newborn screening: universal, before discharge or within the recommended timeframe, without
exception.
โ— Diagnostic confirmation: complete by three months of age for every referred infant, tracked
persistently.
โ— Intervention initiation: begun by six months of age for every confirmed hearing loss.
3. ACCURACY
Definition
Applying every screening and diagnostic test exactly, verifying every hearing device objectively, and
documenting every finding precisely, sustained without deviation across every patient.
Why Accuracy Is Non-Negotiable in Audiology
An inaccurate newborn screening can produce a false pass, allowing a genuine hearing loss to go undetected
through the critical window. An unverified hearing aid fitting can leave a patient with a device that appears to
be working but is not delivering adequate amplification. Accuracy in Audiology, sustained across screening,
diagnosis, and verification alike, is what separates a discipline that genuinely protects a finite developmental
window from one whose assumptions quietly cost a child language they can never fully recover.
Areas Requiring Audiology Accuracy
โ— Newborn Screening: Every test must be performed correctly, with genuine attention to technique and
calibration.
โ— Diagnostic Assessment: Every determination must be evidence-based and genuinely conclusive before
intervention planning proceeds.
โ— Device Verification: Every hearing aid and cochlear implant must be objectively verified, never
assumed functional.
โ— Documentation: Every audiology record must accurately and completely reflect screening, diagnostic,
and verification rationale.
4. COMPASSION
Definition
Recognizing that a hearing loss diagnosis, whether in an infant or an adult, reshapes how a family or patient
imagines their communication future, and that genuine compassion in this communication is as important as
diagnostic accuracy.
How the Audiology Team Demonstrates Compassion
โ— Communicate Diagnosis with Genuine Warmth: Recognizing the profound weight of the news for a
family.
โ— Support Urgency Without Overwhelming: Balancing genuine timeline pressure with a family's need to
process.
Audiologist Excellence Manual Dr J L Meena
Audiologist Excellence Manual โ€“ Dr J L Meena | Page 26
โ— Respect Deaf Identity and Culture: Presenting intervention options without presuming a single correct
choice for every family.
โ— Support Adults Through Progressive Loss: Recognizing the genuine social and identity impact of
hearing decline.
5. ACCOUNTABILITY
Definition
Taking full professional responsibility for every screening decision, every diagnostic determination, and every
device verification made under Audiology team responsibility.
Audiology Accountability Standards
โ— Every screening, diagnostic, and verification decision is documented with the responsible team
member's identification.
โ— Never allow a known tracking gap or verification uncertainty to go unaddressed.
โ— Report every critical incident and adverse audiology event honestly through the quality reporting
system.
โ— Participate in RCA for significant incidents, including any missed screening or diagnostic delay, with
complete clinical honesty.
โ— Participate in quality audits and accreditation surveys with accurate, complete audiology records.
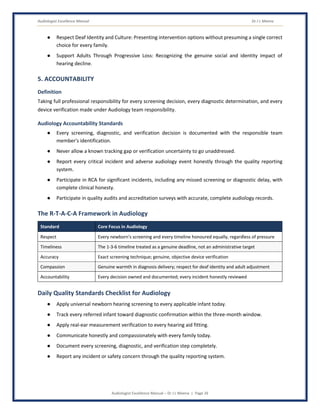
The R-T-A-C-A Framework in Audiology
Standard Core Focus in Audiology
Respect Every newborn's screening and every timeline honoured equally, regardless of pressure
Timeliness The 1-3-6 timeline treated as a genuine deadline, not an administrative target
Accuracy Exact screening technique; genuine, objective device verification
Compassion Genuine warmth in diagnosis delivery; respect for deaf identity and adult adjustment
Accountability Every decision owned and documented; every incident honestly reviewed
Daily Quality Standards Checklist for Audiology
โ— Apply universal newborn hearing screening to every applicable infant today.
โ— Track every referred infant toward diagnostic confirmation within the three-month window.
โ— Apply real-ear measurement verification to every hearing aid fitting.
โ— Communicate honestly and compassionately with every family today.
โ— Document every screening, diagnostic, and verification step completely.
โ— Report any incident or safety concern through the quality reporting system.
Audiologist Excellence Manual Dr J L Meena
Audiologist Excellence Manual โ€“ Dr J L Meena | Page 27
In Audiology, patient safety is measured against a window that genuinely closes โ€” a family experiences it
not as any single test, but as a child who reached intervention in time to build spoken language on a
foundation that was never allowed to narrow.
Audiologist Excellence Manual Dr J L Meena
Audiologist Excellence Manual โ€“ Dr J L Meena | Page 28
CHAPTER 6: CONFIDENTIALITY, PRIVACY, AND INFORMATION
SECURITY
Audiology involves sensitive diagnostic information, including newborn screening results and diagnostic
hearing loss determinations, requiring heightened confidentiality discipline.
1. Privacy in Audiology Practice
Responsibilities
โ— Conduct assessments and diagnostic discussions in as private a setting as available.
โ— Never discuss one patient's screening or diagnostic findings within earshot of another patient or
unauthorized staff.
โ— Apply particular discretion when discussing newborn screening results.
2. Confidentiality of Sensitive Findings
Overview
A newborn hearing loss diagnosis and its genetic or syndromic associations carry particular sensitivity requiring
heightened discretion.
Responsibilities
โ— Handle newborn screening and diagnostic findings with heightened confidentiality until appropriate
clinical communication occurs.
โ— Communicate only the clinically necessary information to the wider care team.
3. Clinical Data and EMR/HIS Confidentiality
Responsibilities
โ— Access only the patient and screening records necessary for current responsibilities.
โ— Never discuss a patient's screening or diagnostic information with anyone outside the legitimate care
team.
โ— Follow hospital IT and cybersecurity policy for all EMR/HIS and audiology information system access.
โ— Never leave audiology workstations unlocked or logged in when unattended.
4. Cybersecurity of Audiology Information Systems
Why Cybersecurity Is a Patient Safety Issue
Audiology information systems store screening, diagnostic, and tracking data upon which the entire time-
critical 1-3-6 pathway depends. A compromised system risks both sensitive data breach and, if tracking data is
lost or corrupted, a referred infant slipping through the follow-up system undetected.
Audiologist Excellence Manual Dr J L Meena
Audiologist Excellence Manual โ€“ Dr J L Meena | Page 29
Responsibilities
โ— Use only authorized, unique login credentials for all EMR/HIS and audiology information system
access.
โ— Never share login credentials with colleagues, regardless of workload pressure.
โ— Never connect personal devices to hospital clinical networks without IT authorization.
โ— Report any suspected unauthorized access or cybersecurity anomaly to IT security immediately.
5. Confidentiality for High-Profile and Vulnerable Patients
Responsibilities
โ— Maintain the same confidentiality standard for high-profile or notorious patients as for every other
patient.
โ— Never disclose patient identity, diagnosis, or condition to media or unauthorized persons.
Confidentiality Checklist for the Audiology Team
โ— Conduct assessments and diagnostic discussions with maximum available privacy.
โ— Handle newborn screening and diagnostic findings with heightened discretion.
โ— Use only authorized credentials for EMR/HIS and audiology information systems.
โ— Never connect personal devices to hospital clinical networks without IT authorization.
In Audiology, confidentiality must be actively maintained for screening and diagnostic information carrying
particular sensitivity, demanding a discretion this team applies without exception.
Audiologist Excellence Manual Dr J L Meena
Audiologist Excellence Manual โ€“ Dr J L Meena | Page 30
CHAPTER 7: STANDARD OPERATING PROCEDURES (SOPs) FOR
AUDIOLOGY
Objectives of Audiology SOPs
โ— Ensure consistent, rigorous screening and diagnostic timeline discipline for every patient.
โ— Minimize harm through systematic, documented safety and quality protocols.
โ— Support NABH/JCI/AAA accreditation compliance for audiology service standards.
โ— Provide a defensible clinical framework for incident investigation and quality improvement.
SOP 1: Universal Newborn Hearing Screening
Purpose
To ensure every newborn is screened for hearing loss before an invisible condition can go undetected.
Procedure
โ— Step 1: Apply Standardized Screening Protocol โ€” apply OAE or AABR screening per institutional
protocol before discharge.
โ— Step 2: Apply Correct Technique โ€” apply correct technique ensuring reliable, valid results.
โ— Step 3: Document Result and Next Steps โ€” document pass/refer outcome and required follow-up
clearly.
โ— Step 4: Document โ€” document the complete screening record.
Quality Standards
โ— 100% of newborns screened before discharge or within the recommended timeframe.
SOP 2: Diagnostic Follow-Up Within the 1-3-6 Timeline
Purpose
To ensure no referred infant is lost before diagnostic confirmation or timely intervention.
Procedure
โ— Step 1: Apply Systematic Tracking โ€” apply active tracking of every referred infant's follow-up status.
โ— Step 2: Apply Persistent Follow-Up Contact โ€” apply repeated family contact attempts when
appointments are missed.
โ— Step 3: Escalate Approaching Deadlines โ€” escalate cases approaching the three- or six-month deadline
for priority scheduling.
โ— Step 4: Document โ€” document the complete tracking and follow-up record.
Audiologist Excellence Manual Dr J L Meena
Audiologist Excellence Manual โ€“ Dr J L Meena | Page 31
Quality Standards
โ— 100% of referred infants tracked with documented status through diagnostic confirmation.
SOP 3: Diagnostic Audiological Assessment
Purpose
To provide comprehensive, accurate audiological diagnosis across the lifespan.
Procedure
โ— Step 1: Apply Age-Appropriate Test Battery โ€” apply assessment matched to patient age and
presentation.
โ— Step 2: Apply Differential Diagnosis โ€” distinguish conductive, sensorineural, and mixed hearing loss.
โ— Step 3: Correlate with Medical History โ€” correlate findings with relevant medical and developmental
history.
โ— Step 4: Document โ€” document the complete assessment and diagnostic rationale.
Quality Standards
โ— 100% of assessments include documented differential diagnosis rationale.
SOP 4: Hearing Aid Fitting and Real-Ear Verification
Purpose
To ensure every hearing aid genuinely delivers the amplification a patient's hearing loss requires.
Procedure
โ— Step 1: Apply Prescriptive Fitting โ€” apply evidence-based prescriptive targets matched to the patient's
hearing loss.
โ— Step 2: Apply Real-Ear Measurement โ€” apply objective verification against prescriptive targets.
โ— Step 3: Apply Patient Counselling โ€” apply genuine counselling on use, care, and realistic expectations.
โ— Step 4: Document โ€” document the complete fitting and verification record.
Quality Standards
โ— 100% of hearing aid fittings verified through real-ear measurement.
SOP 5: Cochlear Implant Candidacy and Programming
Purpose
To ensure appropriate candidacy determination and precise post-implantation programming.
Procedure
โ— Step 1: Apply Comprehensive Candidacy Assessment โ€” apply evidence-based candidacy criteria.
โ— Step 2: Coordinate with the Surgical Team โ€” coordinate closely on surgical planning and timing.
Audiologist Excellence Manual Dr J L Meena
Audiologist Excellence Manual โ€“ Dr J L Meena | Page 32
โ— Step 3: Apply Precise Post-Implantation Programming โ€” apply systematic mapping and ongoing
optimization.
โ— Step 4: Document โ€” document the complete candidacy assessment and programming record.
Quality Standards
โ— 100% of cochlear implant candidates receive documented, evidence-based candidacy assessment.
SOP 6: Vestibular and Balance Assessment
Purpose
To identify the underlying cause of balance complaints and guide appropriate management.
Procedure
โ— Step 1: Apply Comprehensive Vestibular History โ€” apply structured history-taking for balance
complaints.
โ— Step 2: Apply Appropriate Vestibular Testing โ€” apply VNG, VEMP, or other indicated testing.
โ— Step 3: Coordinate on Management โ€” coordinate with medicine and vestibular rehabilitation.
โ— Step 4: Document โ€” document the complete assessment and management plan.
Quality Standards
โ— 100% of vestibular assessments include documented, comprehensive history and testing rationale.
SOP 7: Tinnitus Assessment and Management
Purpose
To provide evidence-based tinnitus assessment and genuine quality-of-life-focused management.
Procedure
โ— Step 1: Apply Comprehensive Tinnitus Assessment โ€” assess characteristics, impact, and contributing
factors.
โ— Step 2: Apply Evidence-Based Management โ€” apply sound therapy, counselling, or other indicated
approaches.
โ— Step 3: Apply Follow-Up Monitoring โ€” monitor genuine symptom and quality-of-life change.
โ— Step 4: Document โ€” document the complete assessment and management plan.
Quality Standards
โ— 100% of tinnitus assessments include documented impact evaluation.
SOP 8: Ototoxicity Monitoring Protocol
Purpose
To detect medication-related hearing change early enough to inform treatment decisions.
Audiologist Excellence Manual Dr J L Meena
Audiologist Excellence Manual โ€“ Dr J L Meena | Page 33
Procedure
โ— Step 1: Apply Baseline Assessment โ€” apply baseline audiological assessment before ototoxic
treatment begins.
โ— Step 2: Apply Serial Monitoring โ€” apply monitoring at clinically appropriate intervals during
treatment.
โ— Step 3: Communicate Changes Promptly โ€” communicate any significant change immediately to the
prescribing physician.
โ— Step 4: Document โ€” document the complete monitoring record.
Quality Standards
โ— 100% of at-risk patients receive documented baseline and serial ototoxicity monitoring.
SOP 9: Occupational Hearing Conservation Program
Purpose
To prevent avoidable noise-induced hearing loss in occupationally exposed workers.
Procedure
โ— Step 1: Apply Baseline Audiometric Testing โ€” apply baseline testing before noise exposure begins.
โ— Step 2: Apply Periodic Monitoring โ€” apply monitoring at regulatory-required intervals.
โ— Step 3: Support Hearing Protection Compliance โ€” support education and programme adherence.
โ— Step 4: Document โ€” document the complete monitoring and programme record.
Quality Standards
โ— 100% of programme-enrolled workers receive documented baseline and periodic monitoring.
SOP 10: Equipment Calibration and Sound Booth Quality Control
Purpose
To ensure equipment delivers accurate, reliable diagnostic results.
Procedure
โ— Step 1: Apply Scheduled Calibration โ€” apply routine equipment calibration per manufacturer and
regulatory schedule.
โ— Step 2: Apply Sound Booth Ambient Noise Verification โ€” verify sound booth meets ambient noise
standards.
โ— Step 3: Address Any Deviation Immediately โ€” apply immediate corrective action for any identified
deviation.
โ— Step 4: Document โ€” document the complete calibration and quality control record.
Audiologist Excellence Manual Dr J L Meena
Audiologist Excellence Manual โ€“ Dr J L Meena | Page 34
Quality Standards
โ— 100% compliance with scheduled equipment calibration and sound booth verification.
Audiology SOP Daily Compliance Checklist
โ— Every newborn screened per standardized protocol today.
โ— Every referred infant's tracking status reviewed and updated.
โ— Every hearing aid fitting verified through real-ear measurement.
โ— Any incident or safety concern reported through the appropriate system.
SOPs in Audiology are the operating instructions for racing a genuinely closing developmental window.
When followed consistently, they are the systematic foundation of universal screening, relentless tracking,
and objective verification for every patient this team serves.
Audiologist Excellence Manual Dr J L Meena
Audiologist Excellence Manual โ€“ Dr J L Meena | Page 35
CHAPTER 8: COMMUNICATION WITH SPECIAL GROUPS
The Audiology team communicates across a distinctive range of circumstances โ€” from new parents receiving
a hearing screening referral, to an adult adjusting to progressive hearing loss, to a Deaf community member
navigating intervention options within their own cultural context, to an occupational health team
implementing a hearing conservation programme. Excellent audiology practice requires adapted
communication for each of these circumstances.
1. Parents of Newborns Receiving a Screening Referral
Communication Guidelines
โ— Communicate a screening โ€œreferโ€ result calmly, explaining it requires follow-up, not that hearing loss
is confirmed.
โ— Communicate the genuine urgency of prompt follow-up without causing undue alarm.
2. Families Receiving a Confirmed Diagnosis
Communication Guidelines
โ— Communicate the diagnosis honestly and compassionately, allowing genuine time to process.
โ— Communicate intervention options completely, respecting family values and priorities.
3. Deaf Community Members and Culturally Deaf Individuals
Communication Guidelines
โ— Respect Deaf identity and culture, never presuming amplification or implantation is the only valid
choice.
โ— Provide complete, unbiased information supporting genuine informed choice.
4. Adults Adjusting to Progressive or Sudden Hearing Loss
Communication Guidelines
โ— Communicate honestly about genuine prognosis and realistic expectations.
โ— Communicate compassionately, recognizing the genuine social and identity impact of hearing change.
5. Elderly Patients and Their Families
Overview
Age-related hearing loss often develops gradually, and patients or families may not recognize its impact on
cognition, safety, and social engagement.
Audiologist Excellence Manual Dr J L Meena
Audiologist Excellence Manual โ€“ Dr J L Meena | Page 36
Communication Guidelines
โ— Communicate the genuine link between untreated hearing loss and broader wellbeing concerns
honestly.
โ— Communicate device options and realistic adjustment expectations clearly.
6. Occupational Health and Employer Partners
Communication Guidelines
โ— Communicate hearing conservation programme requirements and findings clearly.
โ— Support genuine employer understanding of prevention's value.
7. Referring Physicians and the Interdisciplinary Team
Communication Guidelines
โ— Communicate diagnostic findings and recommendations completely and promptly.
โ— Coordinate closely on integrated care planning, particularly for infants requiring early intervention.
8. Hospital Administration and Quality/Accreditation Bodies
Communication Guidelines
โ— Present screening compliance, 1-3-6 timeline performance, and verification data in management-
accessible formats.
โ— Advocate for necessary resources (staffing, screening equipment, tracking systems) with clear patient
safety justification.
Universal Audiology Communication Principles
โ— Communicate with exact, honest language, given the developmental and quality-of-life decisions built
on every word.
โ— Respond to every genuine time-sensitive need with appropriate urgency, without compromising
thoroughness.
โ— Always confirm genuine understanding, particularly for diagnosis and intervention timeline
communication.
โ— Document every significant clinical communication completely.
The Audiology team that communicates with equal urgency toward a newborn's referral and equal respect
toward a Deaf adult's cultural identity serves every stakeholder at maximum impact โ€” honest, timely
communication delivered alongside the genuine respect every patient's choices deserve.
Audiologist Excellence Manual Dr J L Meena
Audiologist Excellence Manual โ€“ Dr J L Meena | Page 37
CHAPTER 9: HANDLING DIFFICULT SITUATIONS
Common Difficult Situations for the Audiology Team
โ— A family misses repeated follow-up appointments as the three-month deadline approaches.
โ— A newborn screening result is genuinely ambiguous or difficult to interpret.
โ— A family declines recommended intervention for cultural or personal reasons.
โ— A hearing aid fitting fails real-ear verification despite correct programming.
โ— A colleague appears to have concluded device function without genuine verification.
โ— An adult patient is in denial about a significant hearing loss.
โ— A cochlear implant candidacy determination is genuinely borderline.
โ— Equipment calibration reveals a deviation affecting recent diagnostic results.
โ— A patient on ototoxic medication shows early signs of hearing change.
โ— An occupational hearing conservation programme faces poor compliance.
Core Principles for Handling Difficult Situations
1. Timeline Discipline and Verification Integrity Are Never Compromised
In every difficult situation, genuine urgency for the 1-3-6 timeline and objective device verification drive every
decision โ€” no family reluctance or convenience, however genuine, justifies abandoning either.
2. Apply Standardized Protocols Under Pressure
Missed appointments and ambiguous results are precisely when standardized protocols matter most โ€” resist
the temptation to improvise when a proven protocol exists.
3. Escalate Immediately and Persistently
A genuine safety or timeline concern is not resolved until it reaches someone who can act on it โ€” escalate
through alternative channels if the first attempt does not produce a response.
4. Document Everything
Every difficult situation must be contemporaneously documented โ€” what was found, what was
communicated, what decisions were made, and by whom.
Handling Repeated Missed Follow-Up Appointments
Steps
โ— Apply persistent, varied contact attempts (phone, letter, community health worker outreach).
โ— Escalate to social work or public health resources if genuine access barriers are identified.
Audiologist Excellence Manual Dr J L Meena
Audiologist Excellence Manual โ€“ Dr J L Meena | Page 38
Handling an Ambiguous Screening Result
Steps
โ— Apply repeat testing or escalate to diagnostic-level assessment promptly.
โ— Never allow ambiguity to delay the overall diagnostic timeline unnecessarily.
Handling a Family's Decision to Decline Intervention
Steps
โ— Provide complete, unbiased information supporting genuine informed decision-making.
โ— Respect the family's autonomous decision while ensuring they understand all options remain available
later.
Handling a Hearing Aid Failing Verification
Steps
โ— Apply systematic troubleshooting of the device, coupling, and programming.
โ— Never dispense or continue a fitting that has not achieved genuine verification.
Handling Concern About a Colleague's Verification Practice
Steps
โ— Address the concern directly and professionally with the colleague.
โ— Escalate to department leadership if the concern involves a pattern or remains unresolved.
Handling Patient Denial About Hearing Loss
Steps
โ— Communicate findings honestly while allowing genuine space for the patient's emotional process.
โ— Revisit the conversation over time rather than forcing immediate acceptance.
Handling a Borderline Cochlear Implant Candidacy
Steps
โ— Apply additional assessment or multidisciplinary team review to resolve genuine uncertainty.
โ— Communicate the genuine uncertainty honestly with the family.
Handling Equipment Calibration Deviation
Steps
โ— Apply immediate equipment correction and identify affected patient results.
โ— Communicate with and, where indicated, retest affected patients.
Audiologist Excellence Manual Dr J L Meena
Audiologist Excellence Manual โ€“ Dr J L Meena | Page 39
Handling Early Ototoxic Change
Steps
โ— Communicate the finding immediately to the prescribing physician.
โ— Support informed treatment decision-making balancing genuine clinical priorities.
Handling Poor Hearing Conservation Programme Compliance
Steps
โ— Provide additional education and support addressing genuine barriers to compliance.
โ— Escalate to occupational health leadership if compliance genuinely persists as inadequate.
The CALM Model for Audiology
โ— C โ€“ Control the immediate safety or timeline risk.
โ— A โ€“ Acknowledge the clinical reality accurately, including genuine uncertainty.
โ— L โ€“ Lead with evidence โ€” screening protocols, verification standards, and the 1-3-6 timeline.
โ— M โ€“ Manage through documented escalation channels when needed.
Difficult situations in Audiology are always, ultimately, tests of whether timeline urgency and verification
integrity hold firm under family or clinical pressure. The team that never compromises either, escalates
persistently, and communicates honestly even when uncertain is fulfilling the highest professional
obligation of audiology practice.
Audiologist Excellence Manual Dr J L Meena
Audiologist Excellence Manual โ€“ Dr J L Meena | Page 40
CHAPTER 10: EMERGENCY RESPONSE โ€” CRITICAL AUDIOLOGY
PRESENTATIONS
Overview
Certain presentations demand the Audiology team's most immediate, standardized, and rehearsed response
โ€” scenarios where the difference between a coordinated, protocol-driven response and an improvised one is
measured directly in whether a time-critical opportunity for hearing preservation or restoration is protected.
Critical Presentations Requiring Immediate Response
โ— Sudden sensorineural hearing loss requiring urgent medical referral within the treatment window.
โ— An infant approaching the three-month diagnostic deadline with no completed assessment.
โ— An infant approaching the six-month intervention deadline with no initiated intervention.
โ— A cochlear implant device malfunction affecting a patient's only source of auditory access.
โ— Suspected acute ototoxicity during active ototoxic medication treatment.
โ— A patient presenting with acute vertigo and risk of fall injury.
โ— Equipment calibration failure affecting active diagnostic testing.
โ— A newborn discharged without documented hearing screening or follow-up plan.
โ— Suspected acoustic trauma from acute noise exposure.
โ— A hearing aid or cochlear implant battery/device failure in a patient with critical communication
dependence (e.g., during a medical emergency).
1. Sudden Sensorineural Hearing Loss
Immediate Response
โ— Apply immediate, urgent referral to ENT/otolaryngology given the narrow treatment window.
โ— Communicate the urgency clearly to the patient and referring physician.
2. Infant Approaching the Three-Month Deadline
Steps
โ— Apply immediate priority scheduling for diagnostic completion.
โ— Escalate to department leadership if scheduling barriers threaten the deadline.
3. Infant Approaching the Six-Month Intervention Deadline
Steps
โ— Apply immediate priority coordination with early intervention services.
Audiologist Excellence Manual Dr J L Meena
Audiologist Excellence Manual โ€“ Dr J L Meena | Page 41
โ— Escalate any coordination barrier immediately.
4. Cochlear Implant Device Malfunction
Steps
โ— Apply immediate troubleshooting and backup device provision where available.
โ— Arrange urgent device repair or replacement.
5. Suspected Acute Ototoxicity
Steps
โ— Apply immediate audiological assessment.
โ— Communicate findings immediately to the prescribing physician for urgent treatment reconsideration.
6. Acute Vertigo with Fall Risk
Steps
โ— Apply immediate safety precautions and appropriate urgent referral.
โ— Coordinate immediately with the emergency response team as clinically indicated.
7. Equipment Calibration Failure During Active Testing
Steps
โ— Apply immediate test cessation and equipment correction.
โ— Identify and retest any patient whose results may be affected.
8. Newborn Discharged Without Documented Screening
Steps
โ— Apply immediate outreach to arrange urgent outpatient screening.
โ— Investigate the discharge process gap and apply corrective action.
9. Suspected Acoustic Trauma
Steps
โ— Apply immediate audiological assessment and appropriate urgent referral.
10. Device Failure During Critical Communication Dependence
Steps
โ— Apply immediate backup communication strategy.
โ— Arrange urgent device repair or replacement.
Audiologist Excellence Manual Dr J L Meena
Audiologist Excellence Manual โ€“ Dr J L Meena | Page 42
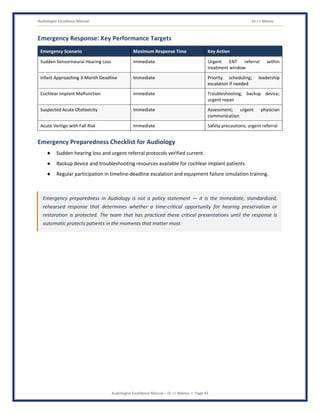
Emergency Response: Key Performance Targets
Emergency Scenario Maximum Response Time Key Action
Sudden Sensorineural Hearing Loss Immediate Urgent ENT referral within
treatment window
Infant Approaching 3-Month Deadline Immediate Priority scheduling; leadership
escalation if needed
Cochlear Implant Malfunction Immediate Troubleshooting; backup device;
urgent repair
Suspected Acute Ototoxicity Immediate Assessment; urgent physician
communication
Acute Vertigo with Fall Risk Immediate Safety precautions; urgent referral
Emergency Preparedness Checklist for Audiology
โ— Sudden hearing loss and urgent referral protocols verified current.
โ— Backup device and troubleshooting resources available for cochlear implant patients.
โ— Regular participation in timeline-deadline escalation and equipment failure simulation training.
Emergency preparedness in Audiology is not a policy statement โ€” it is the immediate, standardized,
rehearsed response that determines whether a time-critical opportunity for hearing preservation or
restoration is protected. The team that has practiced these critical presentations until the response is
automatic protects patients in the moments that matter most.
Audiologist Excellence Manual Dr J L Meena
Audiologist Excellence Manual โ€“ Dr J L Meena | Page 43
CHAPTER 11: DIGITAL COMPETENCY FOR THE AUDIOLOGY TEAM
Objectives
โ— Enable the Audiology team to use screening, diagnostic, and tracking systems accurately, securely, and
efficiently.
โ— Leverage technology to improve newborn hearing screening tracking and device verification
documentation.
โ— Manage the cybersecurity of audiology information systems as a core patient safety function.
Core Digital Competencies for the Audiology Team
1. Electronic Medical Record (EMR) / Hospital Information System (HIS)
Essential Skills
โ— Use EMR/HIS accurately for screening documentation, diagnostic records, and interdisciplinary
communication.
2. Newborn Hearing Screening Tracking Systems
Essential Skills
โ— Use EHDI tracking systems accurately to monitor every referred infant's status through the 1-3-6
timeline.
3. Real-Ear Measurement and Hearing Aid Fitting Software
Essential Skills
โ— Use real-ear measurement and fitting software accurately to verify device performance objectively.
4. Cochlear Implant Programming Software
Essential Skills
โ— Use manufacturer-specific programming software accurately for post-implantation mapping.
5. AI-Assisted Diagnostic and Fitting Tools
Awareness
โ— AI-assisted tools are increasingly applied to support automated threshold estimation and fitting
optimization.
โ— Understand and appropriately leverage these tools while maintaining independent clinical judgment
โ€” AI tools are decision-support, not a substitute for genuine audiological assessment.
Audiologist Excellence Manual Dr J L Meena
Audiologist Excellence Manual โ€“ Dr J L Meena | Page 44
6. Teleaudiology Platforms
Essential Skills
โ— Use teleaudiology platforms accurately for remote assessment and follow-up where clinically
appropriate.
7. Cybersecurity and Information Security
Personal Digital Security Responsibilities
โ— Use unique, strong credentials for all EMR/HIS and audiology information system logins.
โ— Lock or log out of workstations whenever stepping away, even briefly.
โ— Never connect personal devices to hospital clinical networks.
โ— Report all cybersecurity anomalies to IT security immediately.
Digital Competency Checklist
โ— Navigate EMR/HIS, EHDI tracking, and fitting verification systems for all core functions without
assistance.
โ— Apply accurate, complete screening, diagnostic, and verification documentation.
โ— Apply basic cybersecurity practices to all clinical system access.
โ— Know the downtime procedure for EMR/HIS system failure.
Digital competency for the Audiology team is the ability to integrate genuine clinical urgency with the
screening, tracking, and verification systems that modern audiology increasingly depends upon โ€” using
technology to extend, never replace, the timeline discipline that defines excellent audiology practice.
Audiologist Excellence Manual Dr J L Meena
Audiologist Excellence Manual โ€“ Dr J L Meena | Page 45
CHAPTER 12: DAILY AUDIOLOGY CHECKLIST
Objectives
โ— Provide a structured daily framework for time-critical screening and verification discipline.
โ— Ensure every screening, tracking, and verification obligation is addressed every shift.
โ— Support accurate clinical documentation and departmental performance data quality.
PART A: START-OF-SHIFT CHECKLIST
Personal and Professional Readiness
โ— Appropriate professional attire and ID badge displayed.
โ— EMR/HIS systems functional and accessible.
Equipment and Readiness Review
โ— Verified screening, diagnostic, and fitting equipment calibrated and functional.
โ— Verified sound booth ambient noise levels within standard.
PART B: SCREENING AND TRACKING CHECKLIST
โ— Every applicable newborn screened per standardized protocol today.
โ— Every referred infant's tracking status reviewed against the 1-3-6 timeline.
PART C: DIAGNOSTIC CHECKLIST
โ— Every diagnostic assessment includes documented differential diagnosis rationale.
โ— Every finding correlated with relevant medical and developmental history.
PART D: DEVICE VERIFICATION CHECKLIST
โ— Every hearing aid fitting verified through real-ear measurement.
โ— Every cochlear implant programming session documented completely.
PART E: SAFETY AND MONITORING CHECKLIST
โ— Every applicable ototoxicity or occupational monitoring completed and documented.
โ— Any change in patient status reassessed promptly.
PART F: SAFETY AND INCIDENT CHECKLIST
โ— Any incident, near-miss, or timeline concern reported through the appropriate system.
โ— CAPA actions from previous incidents reviewed for completion.
Audiologist Excellence Manual Dr J L Meena
Audiologist Excellence Manual โ€“ Dr J L Meena | Page 46
PART G: END-OF-SHIFT CHECKLIST
โ— All clinical records updated and complete for the shift.
โ— Structured handover prepared for the incoming shift.
โ— Clinical systems securely logged out.
Daily Self-Assessment for the Audiology Team
โ— Did we apply universal newborn hearing screening to every applicable infant today?
โ— Did we track every referred infant toward diagnostic confirmation within the three-month window?
โ— Did we apply real-ear measurement verification to every hearing aid fitting?
โ— Did we communicate honestly and compassionately with every family today?
โ— Did we apply appropriate ototoxicity or occupational monitoring where indicated?
A consistent, structured daily routine โ€” from start-of-shift equipment verification to end-of-shift handover
โ€” transforms individual screening discipline into a systemic audiology safety programme that races a
genuinely closing developmental window, every single day.
Audiologist Excellence Manual Dr J L Meena
Audiologist Excellence Manual โ€“ Dr J L Meena | Page 47
CHAPTER 13: KEY PERFORMANCE INDICATORS (KPIs) FOR AUDIOLOGY
Objectives
โ— Measure screening, diagnostic timeline, and verification performance objectively.
โ— Enable data-driven continuous improvement in Audiology practice.
โ— Support NABH/JCI/AAA accreditation standards for audiology services.
โ— Demonstrate the value and patient safety impact of the Audiology team to institutional leadership.
Categories of Audiology KPIs
1. Newborn Screening KPIs
KPI Definition Target
Newborn Screening Rate % of newborns screened before discharge or within the
recommended timeframe
100%
Referral-to-Diagnosis Timeline
Compliance
% of referred infants receiving diagnostic confirmation by
3 months
โ‰ฅ 95%
Diagnosis-to-Intervention Timeline
Compliance
% of confirmed cases beginning intervention by 6 months โ‰ฅ 95%
2. Diagnostic Quality KPIs
KPI Definition Target
Diagnostic Assessment Completeness % of assessments including documented differential
diagnosis rationale
100%
Loss-to-Follow-Up Rate % of referred infants lost to follow-up before
diagnostic confirmation
Minimize toward
zero
3. Device Verification KPIs
KPI Definition Target
Real-Ear Verification Compliance % of hearing aid fittings verified through real-ear
measurement
100%
Cochlear Implant Programming
Compliance
% of post-implantation sessions with documented
mapping
100%
4. Prevention KPIs
KPI Definition Target
Ototoxicity Monitoring Compliance % of at-risk patients with documented baseline/serial
monitoring
100%
Audiologist Excellence Manual Dr J L Meena
Audiologist Excellence Manual โ€“ Dr J L Meena | Page 48
KPI Definition Target
Occupational Monitoring Compliance % of enrolled workers with documented
baseline/periodic testing
100%
5. Outcome and Governance KPIs
KPI Definition Target
RCA Completion Rate % of significant adverse events with completed RCA 100%
Equipment Calibration Compliance % compliance with scheduled equipment calibration 100%
Patient/Family Satisfaction Score % positive patient/family feedback on audiology
service
โ‰ฅ 85%
Using KPIs for Continuous Improvement
โ— Review all Audiology KPIs regularly at departmental quality and governance meetings.
โ— Analyse timeline compliance and loss-to-follow-up trends to identify targeted process improvements.
โ— Use verification compliance data to identify training and equipment needs.
โ— Present KPI data to hospital management to demonstrate the patient safety impact of Audiology
excellence.
Audiology KPIs translate the discipline of racing a genuinely closing developmental window into
institutional accountability โ€” demonstrating that the investment in universal screening, relentless
tracking, and objective verification is a measurable, trackable programme that ensures no child's window
for spoken language closes for want of a test performed on time.
Audiologist Excellence Manual Dr J L Meena
Audiologist Excellence Manual โ€“ Dr J L Meena | Page 49
CHAPTER 14: TOP 20 DO'S & TOP 20 DON'TS FOR AUDIOLOGY
Introduction
The Audiology team races against a genuinely closing developmental window โ€” an infant's brain is only so
patient for sound before the neural pathways for spoken language begin to organize around whatever input it
receives. Their daily professional decisions โ€” about screening, tracking, and verification โ€” determine whether
every patient's window for spoken language and quality of life is protected. These Do's and Don'ts provide the
practical daily architecture of Audiology excellence.
TOP 20 DO'S FOR AUDIOLOGY
โ— 1. Screen Every Newborn Universally โ€” Before discharge or within the recommended timeframe.
โ— 2. Track Every Referred Infant Relentlessly โ€” Toward diagnostic confirmation by 3 months.
โ— 3. Escalate Approaching Deadlines Immediately โ€” The 1-3-6 timeline is a genuine deadline.
โ— 4. Apply Real-Ear Measurement to Every Fitting โ€” Never assume a device works.
โ— 5. Apply Differential Diagnosis Rigorously โ€” Every assessment, every time.
โ— 6. Communicate Diagnosis with Genuine Compassion โ€” Allow families time to process.
โ— 7. Verify Genuine Family Understanding โ€” Before they leave the appointment.
โ— 8. Respect Deaf Identity and Culture โ€” Never presume a single correct choice.
โ— 9. Apply Ototoxicity Monitoring for At-Risk Patients โ€” Baseline and serial, without exception.
โ— 10. Support Occupational Hearing Conservation โ€” Prevention is entirely achievable.
โ— 11. Debrief After Every Significant Event โ€” Consolidate learning while it is fresh.
โ— 12. Provide Structured Handover for Every Transfer โ€” SBAR or equivalent, every time.
โ— 13. Communicate with Exact, Honest Language โ€” Developmental outcomes depend on every word.
โ— 14. Report Every Near-Miss Honestly โ€” Including your own, especially in tracking.
โ— 15. Apply Persistent, Varied Follow-Up Contact โ€” For every missed appointment.
โ— 16. Coordinate Proactively with Early Intervention โ€” For every confirmed infant hearing loss.
โ— 17. Apply the Same Rigour to Every Patient โ€” Regardless of setting or socioeconomic status.
โ— 18. Calibrate Equipment on Schedule โ€” Accurate diagnosis depends on it.
โ— 19. Communicate Realistic Device Expectations โ€” Neither overpromising nor understating.
โ— 20. Continue Learning โ€” Audiology evidence evolves. The team that does not learn continuously treats
today's patients with yesterday's protocols.
Audiologist Excellence Manual Dr J L Meena
Audiologist Excellence Manual โ€“ Dr J L Meena | Page 50
TOP 20 DON'TS FOR AUDIOLOGY
โ— 1. Don't Discharge a Newborn Without Screening or a Tracked Follow-Up Plan โ€” Ever.
โ— 2. Don't Let a Referred Infant Drift Past 3 Months Unaddressed โ€” Track relentlessly.
โ— 3. Don't Assume a Hearing Aid Works Without Verification โ€” Real-ear measurement, always.
โ— 4. Don't Skip Differential Diagnosis โ€” Every assessment deserves genuine rigour.
โ— 5. Don't Overwhelm a Newly Diagnosed Family โ€” Allow genuine time to process.
โ— 6. Don't Assume Family Understanding from a Nod โ€” Verify genuinely.
โ— 7. Don't Presume Amplification Is the Only Valid Choice โ€” Respect Deaf identity.
โ— 8. Don't Skip Ototoxicity Monitoring for At-Risk Patients โ€” Baseline and serial, always.
โ— 9. Don't Neglect Occupational Hearing Conservation โ€” It is entirely preventable harm.
โ— 10. Don't Skip Team Debriefing After a Critical Event โ€” Unprocessed events repeat their gaps.
โ— 11. Don't Hand Over Complex Cases Informally โ€” Structure protects against critical omissions.
โ— 12. Don't Use Ambiguous Language in Any Report โ€” Every word carries developmental weight.
โ— 13. Don't Hide or Minimize a Near-Miss โ€” Suppressed incidents cannot drive the improvement that
prevents recurrence.
โ— 14. Don't Give Up After One Missed Appointment โ€” Apply persistent, varied contact.
โ— 15. Don't Work in Isolation from Early Intervention โ€” Coordinate proactively.
โ— 16. Don't Let Volume Erode Screening Rigour โ€” Every patient deserves the same standard.
โ— 17. Don't Skip Equipment Calibration โ€” Accurate diagnosis depends on it.
โ— 18. Don't Overpromise Device Outcomes โ€” Honest expectations, always.
โ— 19. Don't Delay Urgent Referral for Sudden Hearing Loss โ€” The treatment window is narrow.
โ— 20. Don't Practice Outside Current Audiology Evidence โ€” Personal habit or outdated method must
never override current best practice.
Audiology Golden Rules
โ— Screen every newborn universally โ€” before an invisible loss can go undetected.
โ— Track every referred infant relentlessly โ€” toward the 3-month deadline.
โ— Verify every device objectively โ€” never assume it works.
โ— Apply differential diagnosis rigorously โ€” every assessment, every time.
โ— Communicate diagnosis with genuine compassion โ€” always.
โ— Respect Deaf identity and culture โ€” never presume a single choice.
โ— Monitor ototoxicity and support hearing conservation โ€” prevention matters.
โ— Coordinate proactively with early intervention โ€” for every confirmed case.
โ— Report every near-miss โ€” honestly, including your own.
Audiologist Excellence Manual Dr J L Meena
Audiologist Excellence Manual โ€“ Dr J L Meena | Page 51
โ— Never stop learning โ€” today's audiology evidence is not yesterday's.
Daily Commitment Statement
โ€œToday, I will screen every applicable newborn, track every referred infant relentlessly, verify every device
objectively, and communicate honestly and compassionately โ€” because a child's brain only waits so long for
sound, and a missed window can never be reopened.โ€
The Top 20 Do's and Top 20 Don'ts are the daily professional architecture of Audiology excellence โ€” each
shaped by the understanding that this discipline races against a genuinely finite developmental window,
and that there are no minor lapses when a delay costs a child language they can never fully recover.
Audiologist Excellence Manual Dr J L Meena
Audiologist Excellence Manual โ€“ Dr J L Meena | Page 52
CHAPTER 15: AUDIOLOGY PROFESSIONAL PLEDGE
Introduction
An Audiology Professional Pledge is a formal, collective commitment to uphold the highest standards of
universal screening, time-critical tracking, and objective device verification. It serves as a daily affirmation that
no patient's window for spoken language or quality of life is ever narrowed by an avoidable delay.
Official Audiology Professional Pledge
โ€œWe solemnly pledge that as the Audiology team, we will fulfil our collective and individual responsibilities with
the highest standards of screening discipline, timeline urgency, and unwavering commitment to a genuinely
closing developmental window.
We will apply universal newborn hearing screening to every applicable infant, track every referred infant
relentlessly toward diagnostic confirmation by three months, and ensure every confirmed hearing loss begins
intervention by six months, treating this timeline as a genuine deadline rather than an administrative target.
We will apply comprehensive, evidence-based diagnostic assessment across the lifespan, verify every hearing
aid and cochlear implant fitting through objective, real-ear measurement, and never conclude a device
functions correctly without genuine confirmation.
We will communicate a new hearing loss diagnosis honestly and compassionately, respecting Deaf identity and
culture, and we will apply rigorous ototoxicity monitoring and support occupational hearing conservation,
preventing entirely avoidable, irreversible hearing loss.
We will report every incident and near-miss honestly, resist any pressure to compromise screening or
verification integrity, and continuously expand our knowledge and skill, knowing that audiology evidence
evolves and that the team that does not learn continuously treats today's patients with yesterday's protocols.
With unwavering urgency, genuine verification rigour, and profound respect for a window that, once closed,
cannot be reopened, we pledge to be the Audiology team that never lets a patient's access to sound be
narrowed by an avoidable delay.โ€
Daily Commitment Statement
โ€œToday, we commit to screening every applicable newborn, tracking every referred infant relentlessly, verifying
every device objectively, and communicating honestly and compassionately โ€” because a child's brain only
waits so long for sound, and a missed window can never be reopened.โ€
Audiologist Excellence Manual Dr J L Meena
Audiologist Excellence Manual โ€“ Dr J L Meena | Page 53
Core Values Reflected in the Pledge
1. Universal Screening Discipline
Every newborn screened without exception, treating an invisible condition as genuinely present until tested
for.
2. Timeline Urgency
The 1-3-6 rule treated as a genuine developmental deadline, never an administrative aspiration.
3. Objective Verification
Every hearing device confirmed through real-ear measurement, never assumed functional.
4. Respect for Identity and Choice
Deaf identity and culture respected genuinely, without presuming a single correct intervention path.
5. Prevention
Ototoxicity monitoring and hearing conservation applied genuinely, preventing avoidable harm.
6. Accountability
Every decision owned and documented; every incident honestly reviewed.
7. Continuous Learning
Audiology evidence evolves. Professional competence requires perpetual learning.
When the Pledge Should Be Recited
โ— At the beginning of every new Audiology team member's appointment.
โ— At quality governance and screening timeline review meetings.
โ— At NABH/JCI/AAA accreditation preparation events.
โ— As a periodic collective affirmation, particularly following a significant adverse event.
Audiology Oath of the Closing Window
โ€œWe pledge that no child's window for spoken language will ever close for want of a screening, a diagnosis, or
an intervention delivered on time.โ€
Audiology Signature Commitment
This pledge is recited collectively by the multidisciplinary Audiology team and may be individually signed by:
Name: ___________________________
Role: Audiologist / Newborn Hearing Screening Specialist / Hearing Aid Specialist
Department: Audiology
Audiologist Excellence Manual Dr J L Meena
Audiologist Excellence Manual โ€“ Dr J L Meena | Page 54
Registration/Employee ID: _______________
Signature: ________________________
Date: ____________________________
Audiologist Excellence Manual Dr J L Meena
Audiologist Excellence Manual โ€“ Dr J L Meena | Page 55
CONCLUSION
There is a discipline in healthcare that races against a genuinely closing window: an infant's brain is only so
patient for sound before the neural pathways for spoken language begin to organize around whatever input,
or absence of input, it actually receives. This manual has returned, again and again, to why this invisibility,
paired with a genuinely finite developmental window, demands a discipline that treats every week of delay as
a cost that cannot later be refunded โ€” universal screening that catches an invisible condition, relentless
tracking that ensures no infant is lost before diagnosis, and objective verification that ensures a fitted device
genuinely works rather than merely appears to.
Throughout this manual, we have explored the full scope of Audiology professional practice โ€” from universal
newborn hearing screening and the 1-3-6 timeline, through diagnostic assessment and precise device fitting,
to vestibular assessment, tinnitus management, ototoxicity monitoring, and the professional conduct that
defines excellence across every category of audiology practice. These responsibilities collectively define a
discipline that demands both genuine urgency for a finite developmental window and the compassion to guide
families and patients through a diagnosis that reshapes how they imagine their communication future.
The Importance of the Audiology Team in Healthcare Quality
โ— The universal screener โ€” catching an invisible condition before it can silently narrow a child's
developmental window.
โ— The relentless tracker โ€” ensuring no referred infant is lost before diagnostic confirmation.
โ— The objective verifier โ€” confirming every device genuinely delivers the amplification a patient needs.
โ— The compassionate communicator โ€” guiding families through a diagnosis with honesty and genuine
warmth.
โ— The prevention advocate โ€” monitoring ototoxicity and supporting hearing conservation against
entirely avoidable harm.
โ— The honest reviewer โ€” examining every incident and near-miss to protect the next patient whose
window for spoken language depends on this team's discipline.
Final Commitment
โ€œAs the Audiology team, we commit to screening every applicable newborn, tracking every referred infant
relentlessly, verifying every device objectively, and communicating honestly and compassionately โ€” because
a child's brain only waits so long for sound, and a missed window can never be reopened.โ€
Audiologist Excellence Manual Dr J L Meena
Audiologist Excellence Manual โ€“ Dr J L Meena | Page 56
Final Motto
โ€œA Child's Brain Only Waits So Long for Sound โ€” We Screen by One Month, Diagnose by Three, Intervene by
Six, Because a Missed Window for Language Can Never Be Reopened.โ€
Together, We Race a Window That Truly Closes โ€” So That No Child's Voice Is Ever Silenced by a Delay.
Audiologist Excellence Manual Dr J L Meena
Audiologist Excellence Manual โ€“ Dr J L Meena | Page 57
REFERENCES
Global Accreditation and Regulatory Standards
โ— World Health Organization (WHO) โ€“ World Report on Hearing.
โ— Joint Commission International (JCI) โ€“ JCI Accreditation Standards for Hospitals: Assessment of
Patients (AOP) Chapter, including Rehabilitation and Screening Services Requirements.
โ— National Accreditation Board for Hospitals & Healthcare Providers (NABH, India) โ€“ Standards for
Rehabilitation and Allied Health Services.
Newborn Hearing Screening and Early Intervention Standards
โ— Joint Committee on Infant Hearing (JCIH) โ€“ Year 2019 Position Statement and the 1-3-6 Early Hearing
Detection and Intervention Timeline.
โ— World Health Organization โ€“ Guidelines on Newborn and Infant Hearing Screening.
Audiology Practice Standards
โ— American Academy of Audiology (AAA) โ€“ Clinical Practice Guidelines for Diagnostic Audiology.
โ— American Speech-Language-Hearing Association (ASHA) โ€“ Scope of Practice in Audiology.
Hearing Aid and Cochlear Implant Verification Standards
โ— American Academy of Audiology (AAA) โ€“ Clinical Practice Guidelines for Hearing Aid Fitting and Real-
Ear Verification.
โ— American Cochlear Implant Alliance โ€“ Cochlear Implant Candidacy and Programming Guidelines.
Vestibular, Tinnitus, and Ototoxicity Standards
โ— American Academy of Audiology (AAA) โ€“ Clinical Practice Guidelines for Vestibular Assessment and
Tinnitus Management.
โ— American Speech-Language-Hearing Association (ASHA) โ€“ Ototoxicity Monitoring Guidelines.
Occupational Hearing Conservation Standards
โ— Occupational Safety and Health Administration (OSHA) / National Institute for Occupational Safety and
Health (NIOSH) โ€“ Hearing Conservation Program Standards.
Indian Regulatory and National Framework
โ— Rehabilitation Council of India (RCI) โ€“ Professional Standards and Registration Requirements for
Audiologists.
โ— Indian Speech and Hearing Association (ISHA) โ€“ Clinical Practice Guidelines.
Audiologist Excellence Manual Dr J L Meena
Audiologist Excellence Manual โ€“ Dr J L Meena | Page 58
โ— National Medical Commission (NMC) โ€“ Code of Ethics Regulations Applicable to Allied Health Practice.
Quality Improvement and Patient Safety Frameworks
โ— Institute for Healthcare Improvement (IHI) โ€“ Framework for Patient Safety and Quality Improvement
in Rehabilitation Services.
โ— World Health Organization โ€“ Global Patient Safety Action Plan 2021โ€“2030.
Cybersecurity and Digital Health Records
โ— NIST Cybersecurity Framework โ€“ Applied to Healthcare Rehabilitation Information Systems.
โ— HL7 International โ€“ Health Level Seven Data Interchange Standards.
This manual has been developed using internationally recognized principles and best practices from WHO
World Report on Hearing, JCI Assessment of Patients Standards, NABH Rehabilitation Services Standards, JCIH
1-3-6 Position Statement, AAA Clinical Practice Guidelines, ASHA Scope of Practice, American Cochlear Implant
Alliance Guidelines, OSHA/NIOSH Hearing Conservation Standards, India's RCI Professional Standards, ISHA
Clinical Practice Guidelines, and applicable Indian statutory and regulatory requirements. Institutions should
verify current versions of all cited guidelines and regulatory requirements, as clinical protocols and
accreditation standards are subject to periodic revision.
เฅ เคœเคฏ เคฎเคพเคคเคพ เคฆ( เฅ
Audiologist Excellence Manual Dr J L Meena
Audiologist Excellence Manual โ€“ Dr J L Meena | Page 59

END OF MANUAL
Thank You
This manual has been prepared with the vision to empower the multidisciplinary Audiology team with global
standards, best practices, and professional guidance to protect every patient's window for spoken language
and lifelong access to sound.
Our Commitment Continues
The journey of learning never ends. As audiology technology and evidence evolve, our commitment to universal
screening, timeline urgency, and objective verification must remain unwavering โ€” because a window for
spoken language, once closed, cannot be reopened.
Together, We Build Trust
Every newborn screened universally, every referred infant tracked relentlessly, every device verified
objectively, and every family guided honestly through a new diagnosis contributes to one greater purpose โ€”
a healthcare system where no child's voice is ever silenced by a delay that could have been prevented.
โ€œA Child's Brain Only Waits So Long for Sound โ€” We Screen by One Month, Diagnose by Three,
Intervene by Six, Because a Missed Window for Language Can Never Be Reopened.โ€
REMEMBER: Screening is our first defence โ€ข Timeline is our urgency โ€ข Verification is our proof โ€ข Every voice
deserves access โ€ข Learning is our journey
Thank you for being a part of this vital mission. Your dedication makes a difference every day.
Dr J L Meena