Aortic Stenosis
Pratap Sagar Tiwari
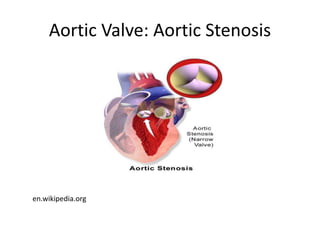
Aortic Valve: Aortic Stenosis
en.wikipedia.org
Aortic stenosis
• Aortic stenosis (AS) is narrowing of the aortic
valve resulting in obstruction of blood flow
from the left ventricle to the ascending aorta
during systole.
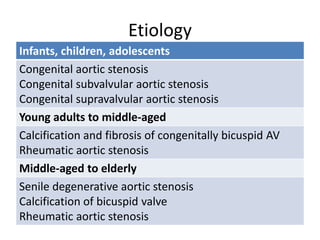
Etiology
Infants, children, adolescents
Congenital aortic stenosis
Congenital subvalvular aortic stenosis
Congenital supravalvular aortic stenosis
Young adults to middle-aged
Calcification and fibrosis of congenitally bicuspid AV
Rheumatic aortic stenosis
Middle-aged to elderly
Senile degenerative aortic stenosis
Calcification of bicuspid valve
Rheumatic aortic stenosis
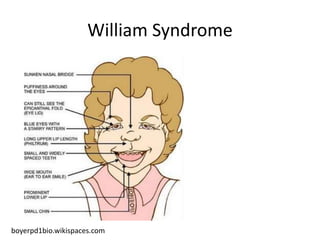
William Syndrome
boyerpd1bio.wikispaces.com
↑ intraventricular pressure to maintain CO
Pathophysiology: AS
Angina , Syncope,
Dyspnea
Valve
obstruction
Impaired passive fillingLVH ↓ Compliance
↑preload dependance on
atrial contraction
↑LVEDP Subendocardial ischemia (↓ myocardial perfusion pressure)
Progressive valvular obstruction & increrasing wall stress
↑ Filling pressure , ventricular dilatation, contractile
dysfunction, ischemia, arrythmia
Ventricular wall hypertrophy (to reduce wall stress)
Symptoms
• The classic symptoms due to AS are heart failure
(HF), syncope, and angina. However, these
“classic” symptoms reflect end-stage disease.
• Now, with earlier diagnosis by echocardiography
and prospective followup of patients, the most
common presenting symptoms are:
1. Dyspnea on exertion or decreased exercise
tolerance
2. Exertional dizziness
3. Exertional angina
Dyspnea and decreased exercise
tolerance
• The MC symptom of AS is dyspnea, usually with exertion.
• 2 factors can contribute: diastolic dysfunction, with an ↑ in
LV filling pressures with exercise, and an inability of LV to ↑
the CO during exercise because the stiff AV obstructs flow.
• Systolic LVdysfunction is rare and overt HF is a late, end-
stage finding, usually in who havent received regular
medical care. Once overt HF occurs, the patient may
complain of SOB, easy fatigability, debilitation, and other
S/S of a low CO state.
• AF, which is uncommon in isolated AS, often accompanies
HF.
Inspection: Carotid pulse
• The quality of the arterial pulse reflects the obstruction
to blood flow into the peripheral arterial circulation.
• The arterial pulse :as "parvus and tardus", ie, it is small
or weak and rises slowly.
• Best appreciated in the carotid artery where the pulse
is reduced in amplitude and delayed in occurrence.
• The delay can be appreciated by simultaneous
palpation of the apex (PMI) and the carotid artery.
• There may be :an associated carotid artery thrill or
coarse vibration ("shuddering") due to the marked
turbulence of blood flow across the stenotic valve.
Palpation of Precordium
• The cardiac impulse at the apex is sustained
and is initially normal in location. (However, it
becomes displaced late in the course of AS
when left ventricular failure occurs. )
• A systolic thrill :at the base of the heart (2nd
ICS ), especially during full expiration with the
patient leaning forward.
Cardiac auscultation :Heart Sounds
• S2 :soft and single since A2(due to Avclosure), is delayed and tends
to occur simultaneously with P2(due to PV closure).
• S2 may become paradoxically split when the stenosis is severe and
associated with LV dysfunction .
• With increasingly severe, fixed AS, the A2 closing sound may
disappear.
• The presence of a normal split S2 is the most reliable finding to
exclude severe AS in adults.
• The S1 is usually N. However, an aortic ejection click, which is more
commonly heard with a congenital bicuspid valve, may be heard
after S1 (when the leaflets are stiff, but still somewhat compliant
and mobile) .
• Vigorous LA contraction can lead to a S4.
AS: MURMUR
• The hallmark finding is a crescendo-decrescendo
ejection murmur, heard best with the diaphragm of
the stethoscope at the right upper sternal border when
a patient is sitting upright leaning forward.
• The murmur typically radiates to one or both carotid
arteries and has a harsh or grating quality.
• The intensity of the systolic murmur does not
correspond to the severity of AS; rather, the timing of
the peak and the duration of the murmur corresponds
to the severity of AS. The more severe the stenosis, the
longer the duration of the murmur and the more likely
it peaks at late systole.
• In elderly persons with calcific AS, however, the murmur
may be more prominent at the apex, because of radiation
of its high-frequency components (Gallavardin
phenomenon). This may lead to its misinterpretation as a
murmur of MR.
• The murmur is soft when stenosis is less severe, grows
louder as stenosis progresses, and becomes longer and
peaks in volume later in systole (ie, crescendo phase
becomes longer and decrescendo phase becomes shorter)
as stenosis becomes more severe.
• As LV contractility decreases in critical AS, the murmur
becomes softer and shorter. The intensity of the murmur
may therefore be misleading in these circumstances.
• The murmur of AS typically increases with maneuvers
that increase LV volume and contractility (eg, leg-
raising, squatting, Valsalva release,) and decreases with
maneuvers that decrease LV volume (Valsalva
maneuver) or increase afterload (isometric handgrip).
• These dynamic maneuvers have the opposite effect on
the murmur of hypertrophic cardiomyopathy, which
can otherwise resemble that of AS.
• The murmur of MR due to prolapse of the posterior
leaflet may also mimic AS.
other
• A high-pitched, diastolic blowing murmur may be
present if the patient has associated aortic
regurgitation.
• Rarely, right ventricular failure with systemic venous
congestion, hepatomegaly, and edema precede LV
failure. This is probably due to the bulging of the
interventricular septum into the right ventricle, with
impedance in filling, elevated jugular venous pressure,
and a prominent a wave (Bernheim effect).
•
Management
• Patients with symptomatic severe AS should have
prompt AV replacement.
• Old age is not a contraindication to valve
replacement .
• Aortic balloon valvuloplasty is useful in
congenital aortic stenosis but is of no value in
older patients with calcific aortic stenosis.
• Anticoagulants are only required in patients who
have Afib or those who have had a valve
replacement with a mechanical prosthesis.
End of slides
References:
• Medscape
• Uptodate 20.3
• Harrison’s Internal medicine
• Davidson’s
• Merck’s mannual