














































Nursing Path
www.nursingpath.in
ANXIETY DISORDERS
(Neurotic Disorder)
Anxiety and Related Disorders
2
-Definition:Vague,subjective, nonspecific feeling of uneasiness,
tension, apprehension,& sometimes dread or impending doom.
-Symptoms:hypertension, tachycardia, muscle hypertonia,
hyperactivity,irritability.
7/16/2019www.nursingpath.in
3
-Common disorders that have anxiety
symptoms:
1- Neurotic Disorders: Hysterical Disorder,
Depression, PTSD.
2- Psychotic Disorders: Major depressive disorder,
Schizophrenia.
3- Organic Disorders: Hyperthyrodism,
Athersoclerosis, Hypoglycemia, Post-concussion,
Menopause, Pre-menstruation.
7/16/2019www.nursingpath.in
4
*Predisposing factors: (2)
1-Hereditary factors:
-Average of anxiety in identical twins: >50%.
2- Age:
-Anxiety increases in Children (Immature nervous system).
-Anxiety increases in Elderly (Atrophic nervous system).
Sx in pediatric: phobia in night, phobia from strangers, animals,
older children, being alone, nightmares, urinal or fecal incontinence,
walking during sleeping.
Sx in adolescent: unsuitability, irritability, social embarrassment esp.
when facing or meeting the other sex, guilty feeling, anxious about
genital area, being very shy, speech stutter.
Sx in in Adulthood: DECREASE.
Sx in in elderly: INCREASE (regarding dz., death)
7/16/2019www.nursingpath.in
Types of anxiety (according to level)
5
1. Mild anxiety:
a. Physiologic: V/S normal, minimal muscle
tension, pupils normal, constricted.
b. Cognitive: perceptual field is broad
-Thought may be random but controlled.
c. Emotional/Behavioral: relative comfort &safety,
relaxed, calm appearance & voice.
**Habitual behaviors occur here.
7/16/2019www.nursingpath.in
6
2. Moderate Anxiety:
a. Physiologic: V/S normal or slightly elevated,
Tension experienced, may be uncomfortable.
b. Cognitive: alert; perception narrowed, focused
(Optimum state for solving & learning), Attentive.
c. Emotional/ Behavioral: Readiness & challenge
(energize), engage in competitive activity & learn
new skills, voice & facial expression concerned.
7/16/2019www.nursingpath.in
7
3. Severe Anxiety: symptoms
a. Physiologic: Fight or flight, autonomic N. system
excessively stimulated (highly increase in v/s,
diaphoresis, urine urgency & frequency, diarrhea, dry
mouth, decrease appetite, dilated pupil), muscles rigid,
tension, decrease heating & pain sensation.
b. Cognitive / perceptual: Perceptual field greatly
narrowed, problem solving: difficult, automatic behavior,
selective attention (focus on one detail).
c. Emotional/Behavioral: Feels threatened, seem or feel
depressed, becomes very disorganized or withdrawn,
may close eyes to shut out environment.
7/16/2019www.nursingpath.in
8
•Panic Attack:
Definition: A discrete period of intense fear or discomfort in
which four or more of the following Sx developed abruptly and
reached a peak within10 minutes.
1-Palpitations
2-Sweating
3-Trembling or shaking
4-Sensations of shortness of breath
5-Feeling of shocking
6-Chest pain or discomfort
7-Nausea or abdominal distress
8-Feeling dizzy, unsteady or Faint
9-Realization of losing control
10-Fear of dying
11-Parenthesis
12-Chills or hot flashes
7/16/2019www.nursingpath.in
1. Phobias
9
-Pt. experiences panic attack in response to particular
situations or learns to avoid situations that evoke panic
attack.
-Phobia results even pt. knows that it won’t happen & no
danger if exposed to situation.
-Even pt. knows that very well he/she can’t control phobia
and doesn’t confront internal conflict but convert it into
external Sx.
7/16/2019www.nursingpath.in
10
Types of phobias:
1-Agoraphobia: Anxiety about being in places or
situations from which escape may be difficult (or
embarrassing) or in which help might not be readily
available in event of unexpected panic attack.
-This includes: fear of being alone, being in crowded area
or standing in a line, being, on a bridge, traveling in a bus;
becomes in need to have a companion.
7/16/2019www.nursingpath.in
11
2- Social phobia: fear from being under observation from
others, which may lead to avoiding social need.
-Usually accompanied with low self-esteem (evaluation and
fear of criticism).
Course & prognosis:
-Usually starts in late childhood & early adolescence.
-May become chronic & decreases after midlife.
-Rarely that disorder is severe & interfere with vocational
performance because of avoidance.
-Complications:
-Addiction (Alcohol, anti-anxiety).
-Depression.
7/16/2019www.nursingpath.in
12
Rx:
1-Drugs: anti-anxiety or anti-depression.
2-Psychotherapy:
Behavioral psychotherapy: with drugs in severe cases by
Gradual Desensitization by exposing him to the fear object
gradually and could be accompanied by some drugs or
relaxation training or Flooding: by exposing pt. suddenly to
fear object in reality or imagination.
Insight psychotherapy: To make pt. understand the cause
phobia & secondary gain symptoms, role of resistance and
this will make him able to find methods more acceptable to
control anxiety with motivating pt. to be exposed to phobia
situation.
7/16/2019www.nursingpath.in
13
3- Simple phobia (isolated phobia) (specific
phobia) :
-Includes specifies conditions:
1-Claustrophobia: Fear of closed places.
2-Mysophobia: fear of dirt, germs and contamination.
3-Acrophobia: fear of heights.
4-Zoophobia: fear of animals.
5-Aqua phobia (or hydrophobia): fear of water.
6-Nectrophobia: fear of darkness.
7-Pyrophobia: fear of fire.
8-Hematophobia: fear of blood.
9-Necrophobia: fear of dead bodies.
10-Xenophobia: fear of strangers.
11-Astrophobia: fear of lightening.
7/16/2019www.nursingpath.in
14
Course & prognosis:
-Beginning of simple phobias is varied.
-Zoophobia starts in childhood.
-Hematophobia often starts in adolescence or
early adulthood.
-Acrophobia often starts in the fourth decade.
-Most of other phobias that start in childhood
disappear without treatment.
-Disability results from simple phobias is slight if
avoidance was easy as zoophobia, but disability is
increasing if stimulus is common, spread & not
avoidable as fear of riding cars for student.
7/16/2019www.nursingpath.in
2-Post Traumatic Stress Disorder (PTSD)
15
-Pt. must have experienced traumatic event prior
to onset of Sx.
-Pt. may have experienced event, witnessed it, or
have been confronted with event that involved
actual or threatened death or serious injury.
-Event should be outside range of usual human
experience.
-Pt. response: intense fear, helplessness or horror.
7/16/2019www.nursingpath.in
-Pt. will have Sx from 1-3 months (Acute) or 3-6
months(Chronic)
- Event cause this disorder could be:
1-Natural: Earthquakes, volcans.
2-Man-made: Rape, Torture.
-PTSD could happen in one individual or more among
group.
7/16/201916 www.nursingpath.in
17
-Pt. will have the following Sx:
1-Re-experiencing the event:
a. Recurrent dreams of the event.
b. Sudden acting or feeling as if traumatic event was
recurring (including sense of re-living the experience,
illusions, hallucinations).
2-Persistent avoidance of stimuli associated with
trauma.
3-Persistent Sx of increased arousal (difficulty to
sleep, irritability, concentration).
7/16/2019www.nursingpath.in
Course & prognosis:
-May occur in any age after event (1wk-30 yrs).
-Sx: fluctuating & become severe during stressful events.
-Acute PTSD lasts for <3 months but it could become
chronic (>3 months).
-30% of pts. with PTSD recovers, 40%slight symptoms,
20%moderate symptoms,10% become worse.
-Prognosis is conditioned by: rapid onset, good pre-morbid
functioning & good social support.
-Complications: social phobia disturbance in relations with
others guilty feeling that may lead to suicide.
7/16/201918 www.nursingpath.in
19
*Rx:
1-Drugs:
Tofranil ( Imipramine), Inderal ( Propanolol).
Catapress (Clonidine).
2-Psychotherapy:
-Cognitive-behavioral approach:
1-Building good relationship with pt.
2-Cognitive appraisal of event & explaining to pt.
effect of stress on human being & that symptoms
are a normal outcome to an abnormal situation.
7/16/2019www.nursingpath.in
20
3-Relation training & desensitization by building a
hierarchy of stressful moments & relaxation.
4-Social support & involving family & friends in caring
& understanding pt.'s condition.
7/16/2019www.nursingpath.in
3-Acute Stress Disorder
21
 The same condition of PTSD, but the
period to have the Sx is 2 days-1
month.
7/16/2019www.nursingpath.in
4-Generalized Anxiety Disorder
22
-Excessive worry & anxiety about 2 or > of life conditions:
Worry of a child of being dying or exposing to any harm (in
fact no danger at all).
-3 or more of the following sx will appear:
1- Restlessness
2- Easily to be fatigued
3- Irritability
4- Difficulties in concentration
5- Muscle tension
6- Sleep disturbances
.
7/16/2019www.nursingpath.in
23
Prognosis:
-May start in any age but is > in 20s & 30s.
-Mainly chronic & may continue for life.
-Complication: is panic attack.
-other complication: addiction because of self-treatment.
Rx:
1-Drugs: should decrease prescribed anti-anxiety as possible
(because disorder is chronic).
2-Psychotherapy: Rx of choice.
a-Psychoanalytic psychotherapy: through long-term insight.
b-Behavioral psychotherapy: focuses on desensitization with
entrance to cognitive therapy aims to stop conditioning in
addition to relaxation & modifying behavior.
7/16/2019www.nursingpath.in
5- Obsessive Compulsive Disorder
24
1-Obsession: undesirable but persistent thought or idea
forced into consciousness & can’t be erased or dismissed,
thought may be trivial or morbid. Always distressing or
anxiety provoking.
2-Compulsion: unwanted urge to perform act or ritual
contrary to pt.'s ordinary conscious wishes or standards.
-Uncontrolled & done to relieve extreme tension.
-Obsession produces anxiety managed by compulsive act.
3-Obsession compulsion: repetitive acts or rituals to release
tension or relieve anxiety.
-Pt. carries out these acts even if he recognizes that they are
inappropriate or foolish.
7/16/2019www.nursingpath.in
25
Examples:
a. Endless hand washing.
b. Checking re-checking doors if they're locked.
c. Elaborate dressing rituals.
-Pt. is trying to resist this, but because of long period of
disorder, resistance may decrease.
-As a result, pt. will have much difficulties in social r/s.
-Pt. is neurotic (because pt. believes that these ideas are
not true & silly).
7/16/2019www.nursingpath.in
26
Course & prognosis:
-Usually starts in adolescence.
-Chronic disorder & pt. may not present to psychiatrist
for 5-10 years.
-About 30% of pts.: good improvement, 30-40%: mild
improvement, & the rest: chronic or worse.
-Some pts. may have depression, suicide or addiction.
7/16/2019www.nursingpath.in
27
Rx:
1-Drugs:
-Anfranil (Clomipramin): Drug of choice (6-12months).
2-Behavioral therapy:
-Effective in 60-70% of pts. (may be Rx of choice).
-Techniques used: Desensitization, thought stopping, flooding
& implosion therapy.
Aversive conditioning: means giving a painful shock or loud
noise when thought occurs.
-Some use response preventing as: forcibly stopping pt. from
responding to obsession.
3-Psychodynamic psychoanalytic therapy:
-Aims to help pt. get insight into his aggressive impulses &
strengthens ego to deal with aggression in mature ways.
7/16/2019www.nursingpath.in
6-Somatororm Disorders
28
-Focusing is physical sx in absence of clinically
significant organic disease.
A-Body Dysmorphic Disorder
-Preoccupation with imagined defect in appearance.
-Slight anomaly: concern is excessive.
-Significant distress or impairment in social or
occupational functioning.
-Preoccupation is not better accounted for by another
mental disorder.
7/16/2019www.nursingpath.in
Course & prognosis:
-Starts in adolescence, 20’s or 30’s, stays constantly &
may have result of social & vocational disability.
-Complication: Plastic surgeries without any need.
Rx:
-Pts. refuse psychotherapy despite their severe suffering
& insist on having plastic surgeries so it is important for
plastic surgeon to refer them to psychiatrist or
psychologist.
-Meds. may relief Sx (anti-anxiety, anti-depression).
-Long-term psychotherapy is recommended.
7/16/201929 www.nursingpath.in
30
B- Pain disorder
-Clinical presentation of pain in 1 or > anatomical sites.
-Pain is severe to warrant clinical attention & causes
major impairment in 1 or > areas of functioning.
-Psychological factors play important role in onset,
severity exacerbation, or maintenance of pain.
-Acute: less than 6 months (duration).
-Chronic: more than 6 months (duration).
Course & prognosis:
-In female double than males.
-Increase at 4th & 5th decade & b/w poor persons.
7/16/2019www.nursingpath.in
Rx:
Drugs: Giving analgesics or narcotics is not useful
(?addiction).
-Anti-depressant can be given: (Elatrol) or (Prozac).
-Anxiolotics or analgesics usually not effective.
Psychotherapy: Important that therapist helps pt.
recognize psychogenic origin of pain.
-Explain to pt. how person state of mind affects how
much pain he can feel.
-Relaxation technique, sports exercice.
-Biofeedback.
-Sometimes, admission to hospital is needed to control
feeling of pain (behavioral, cognitive & group
psychotherapy may be used).
7/16/201931 www.nursingpath.in
32
C- Somatization Disorder
-Frequently seeking & obtaining medical Rx for multiple
clinically significant somatic complaints.
-Complaints must begin before 30 & cannot be explained by
any medical disorder or direct effects of substance.
-Multiple sclerosis pt. would not be dxed by somatization.
-Differentiated from medical conditions if:
-Involvement of multiple organ systems (GI, neurological..).
-Sx exhibit early onset & chronic course, without
development of physical signs or structural abnormalities.
-Absence of clinical (laboratory) abnormalities.
7/16/2019www.nursingpath.in
Course & prognosis:
-Females > males.
-Less occurrence if high social class, more among poor
& illiterate persons.
-Starts before 30.
-Increase among first-degree relatives.
-Chronic & pt. is rarely free of sx or for medical seeking.
7/16/201933 www.nursingpath.in
Rx:
-Long & empathic r/s with one therapist.
-Using meds. is not recommended but anti-depressant
or anxiolytics can be used symptomatically if anxiety or
depression is present (?addiction).
7/16/201934 www.nursingpath.in
35
D-Conversion Disorder (Hysterical neurosis,
Conversion Type):
-Loss or change in beady functioning that can’t be
explained by any medical disorder, & occurs in response
to psychological stress.
-In females > males.
-Usually starts in adolescence or young adulthood.
-Medical exams do not reveal physical abnormality.
-Pt. is not conscious of producing sx.
-Histrionic personality pt: more exposed than others.
-Could happen if exposed to great stress.
-Loss or change can give sensory/motor sx or both.
7/16/2019www.nursingpath.in
36
Motor sx:Abnormal tremors, jerky movements.
* Note: hysterical conversion tremors: it is irregular &
disappears if attention moved to another subject, etc…
-It differs from tremor in anxiety.
-Hysterical aphonia: Pt. can’t speak, but can understand
what is said.
* Note: to differentiate, ask pt. to cough, if he does so,
means vocal cords ok & is hysterical.
7/16/2019www.nursingpath.in
Comparison b/w organic & hysterical paralysis:
Tics: involuntary movement increases in embarrassing
situations.
Hysterical comas: like normal sleep, doesn’t respond to
stimuli, needs care for urination & defecation, usually needs
hospitalization, used to escape from reality.
Hysterical fits: differ from organic epilepsy as following:
Sensory symptoms:
Anesthesia or loss of sensation in a part of body or one half of
body.
Hysterical deafness.
Loss of olfactory or taste senses.
Hysterical blindness.
7/16/201937 www.nursingpath.in
Prognosis:
-Duration is brief.
-Starts & stops abruptly.
-Tends to recur.
-Prognosis is poor if secondary gain is high.
*Primary gain: Gain achieved by converting anxiety to
somatic sx (symbolic of unconscious conflict).
*Secondary gain: Gain achieved by sx, pt. pain relieved
from work or gets attention & sympathy from family by
taking sick role.
7/16/201938 www.nursingpath.in
Rx:
-Exclude organic disease by physical exam.
-Psychotherapy:
-Telling pt. that he has no physical problems & sx are
psychological stress & will disappear if pt. expresses his
feelings.
-Amytal: may be used to produce a state of relaxation &
re-experience trauma which enable pt. to talk freely
about her troubles.
7/16/201939 www.nursingpath.in
40
E-Hypochondriasis
-6 major criteria associated with disorder:
1-Pt is preoccupied with fears of having-or idea of having
serious medical disorder based on his/her interpretation.
2-Misinterpretation of bodily sx persists despite
appropriate medical evaluation & reassurance.
3-Pt’s preoccupation with Sx is not as intense or
distorted as in body dysmorphic disorder.
7/16/2019www.nursingpath.in
41
4-Preoccupation causes clinically significant distress or
impairment in social, occupational, or major areas of
functioning.
5-Duration of disturbance at least 6 months.
6-Condition is not better accounted for by another
anxiety disorder, somatization disorder, or major
depressive episode (Pt. may show sx of anxiety or
depression).
7/16/2019www.nursingpath.in
Course & prognosis:
-Mostly starts in 20’s.
-1/3 of pts. don’t improve & social/vocation disturbed.
-Males & female: equal.
Rx:
-Exclude any organic factor.
-Invasive procedure should be avoided.
-Psychotherapy: preferred treatment even pt. resists this
therapy (may accept it by a physician).
-Group psychotherapy: Rx of choice (pt.’s social support
& interaction can improve their condition).
-Drugs not used unless depression/anxiety present.
7/16/201942 www.nursingpath.in
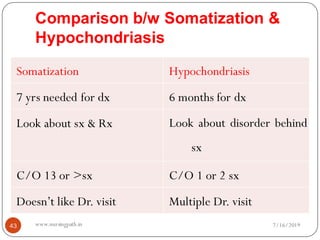
Comparison b/w Somatization &
Hypochondriasis
43
Somatization Hypochondriasis
7 yrs needed for dx 6 months for dx
Look about sx & Rx Look about disorder behind
sx
C/O 13 or >sx C/O 1 or 2 sx
Doesn’t like Dr. visit Multiple Dr. visit
7/16/2019www.nursingpath.in
7-Dissociative Disorders
44
-Disruption in usually integrated functions of consciousness,
memory, identity & perception of environment.
A. Dissociative Amnesia
-1or > episodes of inability to recall important personal
information (traumatic or stressful nature); too extensive to be
explained by ordinary forgetting.
-Disturbance doesn’t occur during Dissociative Identity
Disorder.
-Not due to substance effects or general medical condition.
-Most common in females.
7/16/2019www.nursingpath.in
45
-Usually pt. is aware of memory loss.
-Pt. is usually alert & not confused (Some pts. describe a
state of clouded consciousness).
-Onset is sudden & recovery is sudden & complete.
-Recurrence is rare.
7/16/2019www.nursingpath.in
Rx:
-It is important to differentiate psychogenic amnesia from
organic amnesia ( CVA,P.C, etc..).
-Amytal interview: Pt. is given short or medium acting
barbiturates as Amytal IV & in a state of alleged
consciousness pt. is helped to remember.
-Hypnosis: Under hypnosis, pt. is relaxed & in a
somnolent state in which inhabitations are weekend, &
repressed memories can be reached.
-Psychotherapy: After repressed memory is reached
psychotherapy helps pt. resolve conflicts.
7/16/201946 www.nursingpath.in
47
B. Dissociative Fugue
-Sudden, unexpected travel away from one’s home or place of
work, with inability to recall one’s past.
-Confusion about personal identity or assumes new identity,
which may be partial (filling in the blanks).
-Disturbance doesn’t occur in context of a dissociative identity
disorder, & is not due to effects of a substance or to a general
medical condition.
7/16/2019www.nursingpath.in
-When fugue is over, pt. remembers all he had forgotten but
forgets what happened during fugue.
-Course is usually short.
-Pt. recovers suddenly & completely to find himself in a
strange place.
-Recurrence is rare.
Rx:
-No Rx is required if duration is short.
-Hyposis & Amytal interview maybe used to help pt.
remember his identity.
7/16/201948 www.nursingpath.in
49
C. Multiple Personality Disorder (Dissociative
Identity Disorder)
-2 or > personalities (each complete & integrated).
-At any time, pt. is dominated by one personality &
unaware of presence of other personalities.
->in females.
-Mostly occur in adolescence or early adulthood.
-Predisposing factor: severe physical/sexual abuse in
childhood.
-Epilepsy is found in 25% of pts.
-EEG shows difference in activity in different
personalities in the same pt.
7/16/2019www.nursingpath.in
-Each personality is integrated & differ in mood, attitude,
name, etc…
-Usually each personality doesn’t recognize presence of
other personalities (Sometimes one of them knows about
the other).
-Pt. may find himself in strange place or hearing voices
inside him or another person taking control over him.
-Chronic disorder.
Prognosis:
-Poor if onset is early & if >2 personalities.
7/16/201950 www.nursingpath.in
Rx:
Psychotherapy: Helps pt. resolve conflict & childhood
memories.
-Helps in communication b/w different personalities to
reintegrate pt.
-Hypnosis: Helps in confirming Dx by enhancing
memories & resolving deep conflicts.
7/16/201951 www.nursingpath.in
ThankYou
52 7/16/2019www.nursingpath.in