Antiplatelet drugs
Dr Monica Jain,
Senior Professor,
Department of Pharmacology,
SMS Medical College , Jaipur.
Receptors and their function
• ADP not only causes primary aggregation of platelets but is also
responsible for the secondary aggregation induced by ADP and other
agonists.
• ADP also induces platelet shape change, secretion from storage
granules, influx and intracellular mobilization of Ca2+, and inhibition
of stimulated adenylyl cyclase activity
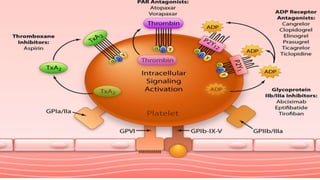
• is well established that ADP activates platelets through 3 purinergic
receptors, namely P2Y1, P2Y12 and P2X1.
Glycoprotein IIb/IIIa (GP IIb/IIIa) receptors
also known as integrin αIIbβ3)
• It is a receptor for fibrinogen and von Willebrand factor
• Glycoprotein IIb/IIIa (GP IIb/IIIa) inhibitors prevent platelet
aggregation by blocking glycoprotein IIb/IIIa receptors on their
platelet's plasma membrane and inhibit fibrinogen binding.
Defination
• Drugs which interfere with platelet function and are useful in
prophylaxis of thromboembolic episode
• Platelet exhibit several glycoprotein receptor on their surface Gpa and
GBb
• Reactive proteins like collagen and von willebrand factor are exposed
when there is damage to vascular endothelium which then react with
platelet receptor
• Platelet activation occur and release of proaggregatory and
vasoconstrictor mediators like TXA2,ADP and 5 HT
Contd
• The platelet GP11b/111a receptor undergo a conformational change
favoring binding of fibrinogen and vW that cross links platelets and
induce aggregation and adhere to vessel wall / other surfaces forming
platelet plug
• In vein due to sluggish flow fibrnious tail is formed which traps RBCs
the red tail
• In arteries platelet mass is main so antiplatelet effective
• In venous thrombosis anticoagulant important
• PGI2 is inhibitor of platelet aggregation and balance between TXA2
and PGI2 controls IV thrombus formation
Classification
• Thromboxane synthesis inhibitor –Aspirin
• Platelet cAMP enhancer – Dipyrimadole
• P2Y12 blockers – Ticlopidine ,clopidogrel ,prasugrel ,Ticagrelor
• GP11b/ 111a antagonists – Abciximab ,Eptifibatide , tirifiban
Aspirin
• Acetylates the enzyme COX1 and TX –synthase inactivating them
irreversibly TXA2 activates platelets to change shape and release
mediator Rich granules which promotes aggregation
• TXA2 is main product generated by platelets And platelet are ex
to Aspirin in the portal circulation before it deacetylates during
past metabolism In the liver and platelet cannot synthesize fresh
enzyme ,TXA2 formation is suppressed at very low doses and til
platelet are formed
• So prolong bleeding time to 5 to 7 days
• 75 to 162 mg/ day
Aspirin
• Inhibits release of ADP from platelet and their sticking to each other
but as no effect on platelet survival time and their adhesion to
damage vessel wall
• Others NSAID action reversible So not used
Dipyrimadole
• Inhibits phosphodiesterase as well as blocks uptake of adenosine to
increase platelet cAMP which turn potentiate PGI2 and inteeferes
with aggregation
• Level of TXA2 and PGI2 are not altered but improves platelet survival
time
• With warfarin along with which it is used to decrease the incidence of
thromboembolism in patient with prosthetic valve
• Dipyridamole has also been used to enhance the antiplatelet action
of aspirin
• Combination may additional lower risk of stroke in patient of TIA
Ticlopidine
• First thienopyridine drug that acts by blocking the P2Y12 type of
puringenic receptor on the surface of platelets and inhibits ADP-
induced aggregation
• Beneficial effect in TIA ,stroke prevention,UA,secondary prophylaxis
of MI and synergized with aspirin to lower the incidence of restenosis
after PCI and stent stenosis
• Produces ADR neutropenia,thrombocytopenia,haemolysis,jaundice,
• Dose 250mg BD with meals,effect persist several days after several
days after discontinuation
Clopidogrel
• More potent congener of ticlopidineblocks P2Y12 type on surface of
platelet
• Act in same way as ticlopidine but better tolerated and safer
• Block irreversibly
• Neutropenia rare
• Lower risk of ishemic events than those taking aspirin
• Combination of clopidogrel and aspirin is synergistic in preventing
ischemic events 20 %reduction in MI,stroke and CV death in cases of
UA and NSTEMI
• Also used in checking restenosis of stented coronaries
Clopidogrel
• Its prodrug
• 50% of ingested dose is absorbed
• Only fraction of drug slowly activated in liver into active thiol metabolite
using CYP2C19
• Slowly acting drug antiplatelt action takes about 4 hrs to start and develops
over days
• CYP2C19 Exhibits genetic polymorphisms so show interindivual variation
• Omeperazole inhibits CYP2C19 reduces activation of clopidogrel
• Action 5 to 7 days due to irrversible blockade of platelet P2Y12 receptor
Adverse effect
• Bleeding
• If combine with aspirin double chances of bleeding
• Diarrhoea ,epigastric pain and rashes
• 300mg loading dose then 75 mg OD
Prasugrel
• More potent
• Fast acting
• Used in ACS and STEMI as well as when strong antiplatelet action required
• Prodrug
• More rapidly absorbed
• More completely activated
• Faster and more consistent platelet inhibition
• CYP2C19 involved but faster and genetic variation and omeperazole
inhibition is less
• Recovery of platelets from prasugrel takes 7 days
Prasugrel
• Stent thrombosis less
• Bleeding more frequent and serious
• Loading dose 60mg followed by 10mg OD
• Ticagrelor
• Not a thienopyridine but blocks platelet aggregation by inhibiting binding
of ADP to the P2Y12 receptor
• Action reversible
• Faster action and quicker offset of action,given twice daily
• Intracrainal bleeding was higher with ticagrelor
• High dose aspirin may interefere with its action not low doses
Ticagrelor
• Side effects – dizziness,nausea,shortness of breath ,tight of chest, and
irregular pulse
• Faster,more potent and more consistent acting P2Y12
• 180 mg loading followed by 90 mg BD
Glycoprotein IIb/IIIa receptor antagonists
• A newer class potent act by blocking the key receptor involved in
platelet aggregation
• GPIIb/ IIIa is an adhesive receptor on platelet Surface for fibrinogen
and vWF through which agonists like collagen,thrombin,TXA2,ADP
finally induce platelet Aggregation
• GPIib/ IIIa antagonist block aggregation induce by all platelet agonist
• Used only in patients with ACS and to cover PCI or coronary artery
bypass grafting
Abciximab
• Fab fragment of a chimeric monoclonal antibody against GPIIb/ IIIa protein
but is nonspecific and binds to other surface proteins too
• Given along with aspirin +heparin during PCI it has markedly reduce the
incidence of restenosis, subsequent MI and death
• After a bolus dose platelet Aggregation remains inhibited for 12 to 24 hrs
• Dose 0.25 mg/ kg IV 10 to 60 min before PCI followed by 10 microgm /min
for 12 hrs
• Nonantigenic main risk haemorrhage And thrombocytopenia so not used
second time
• Constipation.ileus and arrhythmia can occur ,used in unstable angina
adjuvant to coronary thrombolysis / PCI with stent replacement
Eptifibatide
• Synthetic Cyclic peptide that selectively binds to platelet surface
GPIIb/IIIa receptor and inhibits platelet aggregation
• T1/2 2.5hrs is longer than that Abciximab,platelet inhibition reverses
in shorter time within 6 to 10 hrs because it quickly dissociates from
receptor
• Unstable angina- 180 microgm/ kg I.V bolus followed by 2 microgm
/kg/ min infusion upt to 72 hrs
• Coronary angiography- 180 microgm /kg i.v bolus after procedure
follow with 2microgm /kg/min for 12 to 24 hrs
Tirofiban
• Nonpeptide but specific GPIIb/IIIa
• Plasma half life 2hrs
• Acute coronary syndromes- PCI 0.4microgm/kg/ min for 30 min
followed by 0.1microgm/kg/min up to 48 hrs
Uses of platelet
• Aim- use is to prevent intravascular thrombosis And embolization
with minimal risk of haemorrhage
• Single drug- CAD or risk factor for stroke
• Dual drug with different mechanism – ACS, maintainence of vascular
recannilization ,stent replacement,vessel grafting
Coronary artery disease
• Aspirin – 75- 150 mg in post MI
• Reduces risk of fatal and nonfatal MI
• Clopidogrel alternative to symptomatic person of Ischemia
• Continued aspirin / clopidogrel prophylaxis prevents reinfarction
• Acute coronary syndrome –
• UA,STEMI,NSTEMI
• STEMI – complete occulsion
• Soluble aspirin 325 mg and LMW heparin sc given to all
Unstable angina
• Aspirin reduces risk of MI and sudden death
• clopidogrel with aspirin given
• Maximum protection antiplatelet with heparin
NSTEMI
Aspirin plus clopidogrel or ticagrelor
STEMI
PCI with or without stent replacement is procedure of choice
Prasugrel or ticagrelor act rapidly and more predictably than clopidogrel
Prasugrel preferred in diabetics
Contd
• Abciximab / Eptifibatide/ tirofiban are most potent antiplatelet drugs
• Combine with aspirin for high risk patients undergoing PCI
• These along with apsirin and subcutaneous heparin markedly reduce
incidence of restenosis and subsequent MI after coronary angioplasty
• Coronary artery bypass surgery also civered by intensive antiplatelet
regimen
• 12 months continuation
• Dual antiplatelet therapy needed after stent replacement
• Prasugrel used when stent thrombosis occur during clopidogrel
treatment
Cerebrovascular diseases
• Drugs do not alter course of stroke due to cerebral thrombosis
• Aspirin reduces TIA incidence and of stroke in patients wirh TIA
PROSTHETIC heart valves and arteriovenous shunts
Antiplatelet used with warfarin reduce formation of microthrombi on
artificial heart valves and incidence of embolism
Prolong patency of AV shunts implanted for haemodialysis
VENOUS THROMBOEMOLISM
Anticoagulant used in DVT and PE
PVD- aspirin and clopidogrel produce some improvement in intermittent
claudication