






























A 64-year-old architect complains of
right-hand tremor at rest, which
interferes with his writing and drawing.
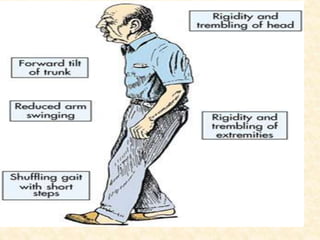
He also notes a stooped posture, a
tendency to drag his left leg when
walking, and slight unsteadiness on
turning. He remains independent in all
activities of daily living.
 It is a Extrapyramidal motor disorder occurs due to
degeneration of dopaminergic neurons in the
substantia nigra pars compacta (SN-PC) result in
dopamine deficiency
 It occur in 2% elderly population
 Classically disease of 7th decade of life
 An imbalance between dopaminergic(inhibitory
neuron) and excitatory cholinergic neuron
Cholinergic over activity
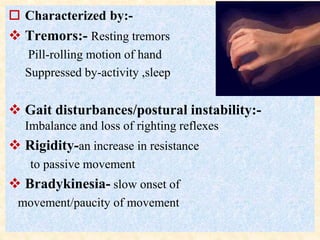
 Characterized by:-
 Tremors:- Resting tremors
Pill-rolling motion of hand
Suppressed by-activity ,sleep
 Gait disturbances/postural instability:-
Imbalance and loss of righting reflexes
 Rigidity-an increase in resistance
to passive movement
 Bradykinesia- slow onset of
movement/paucity of movement
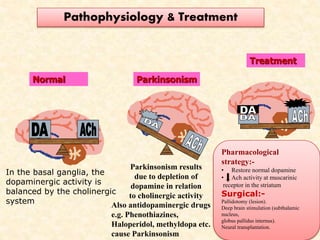
Normal Parkinsonism
Treatment
In the basal ganglia, the
dopaminergic activity is
balanced by the cholinergic
system
Parkinsonism results
due to depletion of
dopamine in relation
to cholinergic activity
Also antidopaminergic drugs
e.g. Phenothiazines,
Haloperidol, methyldopa etc.
cause Parkinsonism
Pathophysiology & Treatment
Pharmacological
strategy:-
• Restore normal dopamine
• Ach activity at muscarinic
receptor in the striatum
Surgical:-
Pallidotomy (lesion).
Deep brain stimulation (subthalamic
nucleus,
globus pallidus internus).
Neural transplantation.
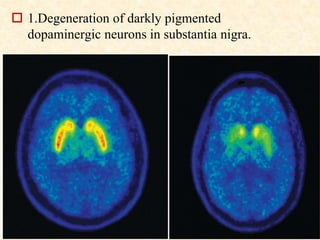
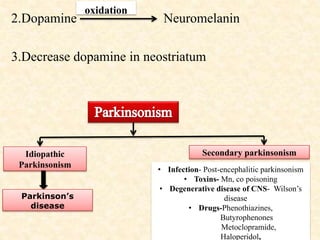
 1.Degeneration of darkly pigmented
dopaminergic neurons in substantia nigra.
2.Dopamine Neuromelanin
3.Decrease dopamine in neostriatum
oxidation
Idiopathic
Parkinsonism
Secondary parkinsonism
• Infection- Post-encephalitic parkinsonism
• Toxins- Mn, co poisoning
• Degenerative disease of CNS- Wilson’s
disease
• Drugs-Phenothiazines,
Butyrophenones
Metoclopramide,
Haloperidol,
Parkinson’s
disease
Anti-parkinsonian Drugs
Dopaminergic Drugs Anticholinergic Drugs
Dopamine
Precursor
•Levodopa
Dopamine Agonists
•Bromocriptine
•Pergolide
•Premipexole
Peripheral Decarboxylase Inhibitors
•Carbidopa
•Benserazide
MAO-B Inhibitor
•Selegiline (Deprenyl)
•Rasagiline
COMT Inhibitor
•Entacapone
•Tolcapone
Dopamine
Facilitator
Amantadine
Anticholinergics
•Trihexyphenidyl
(Benzhexol)
•Procyclidine
•Biperiden
Antihistaminic
•Orphenadrine
•promethazine
 Metabolic precursor of dopamine
 Inactive by itself
 95% of an oral dose is decarboxylated in the peripheral
tissues (mainly gut and liver) and converted into DA
 Only about 1-2% of administered levodopa crosses to the
brain
 Always used in combination with
carbidopa/benserazide(Peripheral decarboxylase inhibitor )
Levodopa(l-dopa)
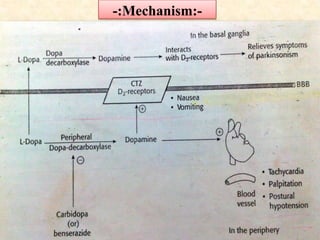
-:Mechanism:-
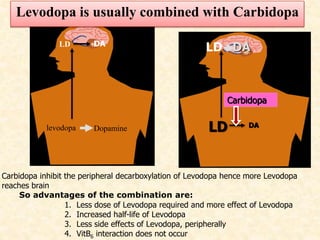
levodopa
1. Less dose of Levodopa required and more effect of Levodopa
2. Increased half-life of Levodopa
3. Less side effects of Levodopa, peripherally
4. VitB6 interaction does not occur
Dopamine LD
LD
LD DA
DA
DA
Carbidopa
So advantages of the combination are:
Carbidopa inhibit the peripheral decarboxylation of Levodopa hence more Levodopa
reaches brain
Levodopa is usually combined with Carbidopa
-:Pharmacokinetics:-
 Absorption:-
 Absorbed orally by active transport
 by the presence of food (especially amino acids)
 Administered on empty stomach
 Bioavailability affected by:
Amino acids present in food compete for the same
carrier for absorption
(# should be given 30-60 min before meal)
 Distribution: L-dopa crosses BBB (CNS disturbance)
 The plasma t 1/2 of levodopa is 1 - 2 hours
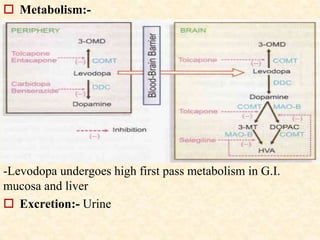
 Metabolism:-
-Levodopa undergoes high first pass metabolism in G.I.
mucosa and liver
 Excretion:- Urine
On CNS:-
 Marked symptomatic improvement occurs in Parkinsonian
patients
 Effect on behavior: ‘General alerting response’
On CVS:-
 (+inotropic action )-The peripherally formed DA can cause
tachycardia acting on β adrenergic receptors
 DA and NA formed in brain central sympathetic flow-Postural
hypotension
Pharmacodynamics
On CTZ:-
 Dopaminergic receptors are present in this area and DA acts as an
excitatory transmitter
 Peripherally formed DA gains access to the CTZ elicits nausea
and vomiting
Endocrine action:-
 DA acts on pituitary mammotropes to inhibit prolactin release
 In Parkinson's Disease:-
Levodopa can reduce all sign and symptoms of PD.
It doesn’t stop the progression of disease
USES
At the initiation of therapy:-
a) CNS manifestations:
1. Euphoria, anxiety, agitation, insomnia, psychological
disturbances as confusion, delusions, hallucinations,
2. Dyskinesia (abnormal involuntary movements which is
corrected by dose reduction)
b) GIT manifestations:-
Anorexia, nausea, and vomiting due to stimulation of D2-receptors
in CTZ
 Tolerance may develop to this adverse effect, but if nausea and
vomiting persist, antiemetics are given; e.g. domperidone (D2
antagonist which does not pass BBB)
 Constipation and bleeding peptic ulcer may occur.
Adverse effects
c) CVS manifestations:
 Postural hypotension- central sympathetic flow
 Tachycardia (direct β1stimulation)
 Hypertension occurs with large doses or with non-selective
MAO inhibitors (α1stimulation).
Others:-
 Alteration of smell, taste sensation
 Abnormal movements-facial tics
After prolong therapy:-
 Wearing off phenomenon:-
After prolong therapy(3-5 year)
Duration of beneficial effect shortens as therapy progress
Disease control become poor
Fluctuation in symptoms occur frequently
-This may be due to the interaction of DOPAC with H2O2 leading
to formation of toxic oxygen free radicals which destroy
dopamine storage vesicles
(this can be prevented by adding selective MAO-B inhibitors as
seligeline)
 ‘On-off phenomenon:-
may be due to variable levels of dopamine in CNS
In on state:- Patient enjoys normal mobility
In off state:- loss of beneficial effect of drugs
eg-patient unable to raise from chair on which he had sat
few min ago.
Fluctuation in plasma level because of short half life
Treatment:-
1. Sustained released formulation of (L-dopa+carbidopa)
2. COMT-inhibitors
3. Frequent administration of levodopa
 Levodopa Non selective MAO-inhibitor-
(hypertensive crisis)
 Levodopa Vit-B6-(metabolism, therapeutic failure)
 Levodopa Reserpine, phenothiazine-(block
dopamine effect )
 Levodopa Tricyclic antidepressant- ( absorption of
levodopa )
Contraindication:-
 Psychoses
 Narrow angle glaucoma
 Peptic ulcer
 Liver & kidney disorder
Interaction
 Decrease peripheral decarboxylation of L-dopa
 Don’t cross BBB.
 Currently use fixed dose combinations:-
L-dopa + carbidopa(4:1/10:1) ratio
L-dopa + Benserazide (4:1)
Advantage:- (1) BA-dopamine in BG. Hence dose of L-
dopa can be reduced by 75%
2.Prolongation of half life of L-dopa
3. Systemic conc.of dopamine, hence incidence of GI-
side effect
4. Cardiovascular complication-minimized
5. Better patient compliance
Carbidopa
Dopamine Agonist
 An alternative to Levodopa-longer duration than levodopa
 These will act on striatal dopamine receptors even in
advanced patients.(more selective receptor action-lesser
Side effect)
 Do not require enzymatic conversion
Ergot derivative
Don’t require enzymatic conversion to active metabolites
Longer duration of action than l-dopa
Prevent motor complication
Mechanism:- partial D1-Agonist
Strong D2-Agonist
Bromocriptine
 USES:-
1. Parkinsonism-
• can be used alone, use as- adjuent to levodopa
• Serves improve control-’wearing of dose’ & ‘on off
fluctuation’
2. Use in suppression of lactation (safer than estrogen)
3.Acromegaly and ACTH-dependent tumors
Adverse effect:-
hallucination,confusion,vomiting
Contraindication:- Peptic ulcer,MI,mental illness
 Ergot derivative
 Mechanism:- agonist at D1,D2 receptor
 Pharmacokinetics:-
Absorption-rapidly orally
Metabolism:- liver by CYP-450 system
50% BA(undergo-first pass metabolism)
Excretion:- urine
USES:- Idiopathic PD treatment
AE:- Dyspepsia,constipation,hallucination
Interaction:- pergolide CYP1A2 inhibitor
(Ciprofloxacin, Diltiazem)
 It Non-ergot derivative dopamine agonist.
 It binds to presynaptic& postsynaptic dopamine D2 &D3receptors,
but has the highest affinity for the D3 receptor subtype.
Mechanism of action :-
 It stimulates presynaptic and post synaptic dopamine D2
receptors.
Therapeutic uses:-
 Used as monotherapy in early PD.
 As an adjunct to levodopa in patients with advanced PD.
Pramipexole
Adverse effects:-
 In early PD nausea, dizziness, constipation, and hallucinations.
 In patients with advanced disease, the most common adverse
effect is orthostatic hypotension.
Drug interaction:-
 cimetidine, ranitidine, diltiazem, verapamil, quinidine,triamterene
decrease the oral clearance of pramipexole by 20%.
 Two different types of isoenzymes of MAO are found (MAO –A and
MAO-B).
 MAO-B is responsible for most of the oxidative metabolism of
dopamine in the brain.
 MAO-A is responsible for metabolism of NA,5-HT,tyramine
 Selective irreversible inhibitors of MAO-B
Advantage:-
Prolonging T1/2 of Endogenously produce dopamine
↑Anti-parkinsonism effect of dopamine
↓‘On-off’,’wearing off’ phenomena
MAO-B inhibitors
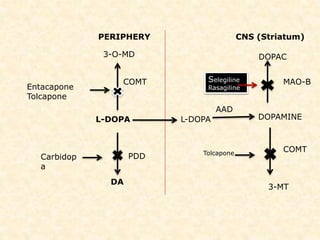
Selegiline
PERIPHERY CNS (Striatum)
3-O-MD
L-DOPA
DA
DOPAC
DOPAMINE
3-MT
L-DOPA
Entacapone
Tolcapone
Carbidop
a
Selegiline
Rasagiline
Tolcapone
AAD
COMT
PDD
MAO-B
COMT
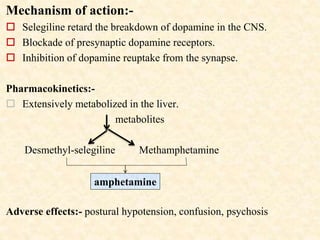
Mechanism of action:-
 Selegiline retard the breakdown of dopamine in the CNS.
 Blockade of presynaptic dopamine receptors.
 Inhibition of dopamine reuptake from the synapse.
Pharmacokinetics:-
 Extensively metabolized in the liver.
metabolites
Desmethyl-selegiline Methamphetamine
Adverse effects:- postural hypotension, confusion, psychosis
amphetamine
Interaction:- Seligiline Tricyclic antidepressant
Seligiline Pethidine (excitement,rigidity)
Seligiline SSRI
 Contraindication:- Contraindicated in patients with convulsive
disorder.
Newer selective MAO-B inhibitor.
Advantage:-
 5 time more potent than seligiline
 Longer acting
 Not metabolized to amphetamine
 Doesn’t produce excitatory side effects
Rasagiline
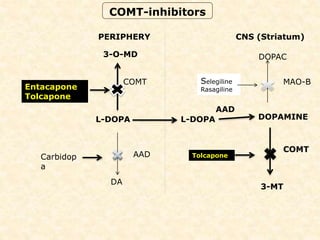
PERIPHERY CNS (Striatum)
3-O-MD
L-DOPA
DA
DOPAC
DOPAMINE
3-MT
L-DOPA
Entacapone
Tolcapone
Carbidop
a
Selegiline
Rasagiline
Tolcapone
AAD
COMT
AAD
MAO-B
COMT
COMT-inhibitors
Reversible COMT-inhibitors
Only periphery action
Shorter acting drug
Mechanism of action:-
 Entacapone is a selective and reversible inhibitor of COMT .
Adverse effects :-
 Dyskinesia, nausea, diarrhoea, abdominal pain, and urinary
discoloration.
 It increases the side effects of levodopa.
Entacapone
 selective and reversible inhibitor of COMT
 Both action- Peripheral + Central action
 Longer acting drug
SE:- occasionally associated with hepatotoxicity
Amantadine:-
Introduced as an antiviral agent
Effective against influenza A2 virus.
Mechanism of action:
It acts presynaptically and postsynaptically
Presynaptically:-
1. release of stored catecholamine from intact dopaminergic terminals
2. Inhibits catecholamine reuptake process at the presynaptic
terminal.
Dopamine facilitator
Postsynaptically:-
 Activation of DA receptors directly.
 Anticholinergic action.
 NMDA receptor blocking effect.
USES:-
Only in milder cases as monotherapy.
Supplement to levodopa for advanced cases.
It serves to suppress motor fluctuations and abnormal movements.
Side effect:- Insomnia, dizziness, confusion, nightmares
 These are the only drugs effective in drug induced
parkinsonism.
 Antimuscarinic agents improve tremor and rigidity but
have little effect on bradykinesia.
USES:-
 Iatrogenic Parkinsonism:- anti dopaminergic drug
induced
 Idiopathic parkinsonism: useful in the management of
mild-to-moderate symptoms of the PD.
Advantage:-
 Main action –centrally so minimal peripheral action
 cheaper and better tolerated then L-dopa
Adverse effect:- Dry mouth,constipation,drowsiness
Central anticholinergic
Drugs:-
Orphenadrine
promethazine
 H1 blockers-addition anti-muscarinic action of
acetylcholine
 Promethazine- tremors,rigidity,sialorrhoea
Anti-histaminic
 Blocked of Dopamine receptor in striatum
 No deficiency of Dopamine
Eg.-
1. Antipsychotic Drugs-e.g.-haloperidol,phenothiazines
High potent D2 blockers
Drugs induce parkinsonism
2.Reserpine-dopamine depleting agent
3.Metoclopramide- cross BBB-block D2 receptor
Drug Induced Parkinsonism
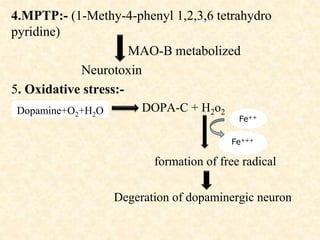
4.MPTP:- (1-Methy-4-phenyl 1,2,3,6 tetrahydro
pyridine)
MAO-B metabolized
Neurotoxin
5. Oxidative stress:-
DOPA-C + H2o2
formation of free radical
Degeration of dopaminergic neuron
Fe++
Fe+++
Dopamine+O2+H2O
1.Classify anti-parkinsonian drugs. Write pharmacological
action, AE and therapeutic uses of levodopa.
(2)Write Short Notes on:-
Levodopa
Cheese reaction
Dopaminergic agonist
MAO-B inhibitors
Explain why:-
1.Levodopa is combined with carbidopa
2. Promethazine used in drugs induce parkinsonism
 The most prevalent cause of dementia with Ageing
 Atrophy of cortical & sub-cortical areas is associated
with deposition of -amyloid protein in a form of
plaques
 Accumulation of Aβ initiate inflammation
 Inflammatory mediators like IL-1,IL-6
 Ultimately leads to apoptosis
 Pharmacotherapy:-
 These drugs provide symptomatic relief but poorly
affect the progression of the disease
 Advantage of drug treatment:-
  β amyloid (Aβ) production
 drugs to prevent Aβ aggregation
 drugs to promote Aβ clearance
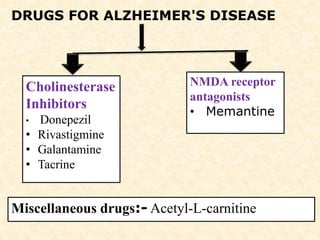
DRUGS FOR ALZHEIMER'S DISEASE
Cholinesterase
Inhibitors
• Donepezil
• Rivastigmine
• Galantamine
• Tacrine
NMDA receptor
antagonists
• Memantine
Miscellaneous drugs:- Acetyl-L-carnitine
 N-methyl-D-aspartate (NMDA) receptor antagonist
 Used as monotherapy and also in combination with
Donepezil
Mechanism of action:-
exert therapeutic effect by blocking NMDA receptors &
preventing exitotoxicity
Pharmacokinetic:-
 Well absorbed after oral admistration.
 Absolute bioavailability of 90%
 t1/2 - 60-80 hours.
 Adverse effects:-Agitation, insomnia, hallucination,
bronchitis, depression.
Memantine
Therapeutic uses: Mild to moderate dementia
Acetyl-L-cartinine:-
 Intracellular carrier of acetyl groups - mitochondrial
membranes - promotes acetylcholine release,  choline
acetyltransferase activity & potent antioxidant.
 Investigational product
 Not recommended - routine use in clinical practice.