ANTICONVULSANT DRUGS
Prepared by:-
SATENDRA PRADHAN
Research
Scholor
Department of Pharmacology
Rungta Institute of Pharmaceutical Science Bhilai
INTRODUCTION
 The word “epilepsy” comes from the Greek
word meaning “to seize” and is used to
describe a disorder of recurrent seizures due
to a chronic, underlying cause.
3
Definition
 A “seizure” is defined as the clinical
manifestation of excessive or hyper
synchronous activity of neurons within the
cerebral cortex.
 Epilepsy is a disorder that is viewed as a
symptom of disturbed electrical activity in the
brain caused by a wide variety of etiologies.
 It is a collection of many different types of
seizures that vary widely in severity, appearance,
cause, consequence, and management.
4
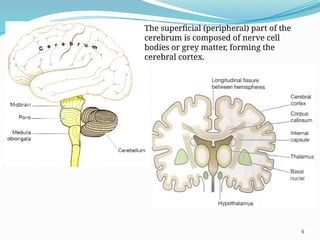
The superficial (peripheral) part of the
cerebrum is composed of nerve cell
bodies or grey matter, forming the
cerebral cortex.
5
EPIDEMIOLOGY
 The lifetime prevalence of epilepsy is approximately
3%.
 The incidence is highest in the first 10 years of life
and declines thereafter to the age of 50 when the
incidence increases again.
 Epilepsy begins before the age of 18 in more than 75%
of individuals.
 The rate of recurrence of a first unprovoked seizure
within 5 years ranges between 23% and 80%.
6
Contd……
 Epilepsy is a chronic disorder characterized by
recurrent seizures.
 The age-adjusted incidence of epilepsy is 44 per
100,000 person-years.
 Each year, about 125,000 new epilepsy cases
occur;
 Of these, 30% are in people younger than age 18
at the time of diagnosis.
 At least 10% of patients in long-term care
facilities are taking at least one antiepileptic
drug (AED).
7
CLASSIFICATION
 The International League Against Epilepsy (ILAE)
has proposed two major schemes for the
classification of seizures and epilepsies:
 International Classification of Epileptic Seizures
 International Classification of the Epilepsies and
Epilepsy Syndromes.
8
International Classification of Epileptic
Seizures
 I. Partial seizures (seizures begin locally)
A. Simple (without impairment of consciousness)
 1. With motor symptoms
 2. With special sensory or somato sensory symptoms
 3. With psychic symptoms
B. Complex (with impairment of consciousness)
 1. Simple partial onset followed by impairment of
consciousness—with or without automatisms
 2. Impaired consciousness at onset—with or without
automatisms
C. Secondarily generalized (partial onset evolving to
 generalized tonic-clonic seizures)
9
 II. Generalized seizures (bilaterally symmetrical
and without local onset)
 A. Absence
 B. Myoclonic
 C. Clonic
 D. Tonic
 E. Tonic-clonic
 F. Atonic
 G. Infantile spasms
10
 III. Unclassified seizures
 IV. Status epilepticus
11
 Generalized absence seizures are manifested:
 by a sudden onset,
 interruption of ongoing activities,
 a blank stare,
 and possibly a brief upward rotation of the
eyes.
 They generally occur in young children
through adolescence.
12
 Partial seizures with an alteration of
consciousness are de-scribed as complex partial.
 With complex partial seizures, the patient may
have automatisms, periods of memory loss, or
aberrations of behavior.
 Complex partial seizures also may progress to
GTC seizures.
 Patients with complex partial seizures typically
are amnestic to these events.
13
Generalized seizures
 Generalized seizures have clinical
manifestations that indicate involvement of
both hemispheres.
 Motor manifestations are bilateral, and there is
a loss of consciousness.
 Generalized seizures may be further
subdivided by EEG and clinical manifestations.
 A partial seizure that becomes generalized is
referred to as a secondarily generalized seizure.
14
Generalized tonic clonic seizures
 The seizure results in a sudden sharp tonic
contraction of muscles followed by a period of
rigidity and clonic movements.
 During the seizure,
 the patient may cry or moan, lose sphincter control,
bite the tongue, or develop cyanosis.
 After the seizure, the patient may have altered
consciousness, drowsiness, or confusion for a
variable period of time (postictal period) and
frequently goes into a deep sleep.
 Tonic and clonic seizures may occur separately
15
Myoclonic
 Brief shock like muscular contractions of the
face, trunk, and extremities are known as
myoclonic jerks.
 They may be isolated events or rapidly repetitive.
 A sudden loss of muscle tone is known as an
atonic seizure.
 This may be described as a head drop, the
dropping of a limb, or a slumping to the ground.
 These patients often wear protective head ware
to prevent trauma.
16
Status Epilepticus
 status epilepticus (SE) is a life-threatening
condition in which the brain is in a state of
persistent seizure.
 Traditionally it is defined as one continuous
unremitting seizure lasting longer than 5
minutes, or recurrent seizures without regaining
consciousness between seizures for greater than 5
minutes.
 It is always considered a medical emergency.
17
The International Classification of Epilepsies
and Epilepsy Syndromes
 Adds components such as age of onset,
intellectual development, findings on neurologic
examination, and results of neuro imaging
studies to define epilepsy syndromes more fully.
 Syndromes can include one or many different
seizure types (e.g., Lennox Gastaut syndrome).
 The syndromic approach includes seizure type(s)
and
possible etiologic classifications (e.g., idiopathic,
symptomatic, or unknown).
18
ETIOLOGY
 Seizures small numbers of neurons discharge
abnormally.
 Normal homeostasis of neuron
 disruption
disturbs its stability
trigger
abnormal activity and seizures.
Patients with mental retardation and cerebral palsy
are at increased risk for seizures.
19
Contd….
 In the elderly, seizures are primarily partial in
onset.
 The causes of seizures in the elderly may be
multifactorial and include cerebrovascular disease
(both ischemic and hemorrhagic stroke),
 Neurodegenerative disorders, tumor, head trauma,
metabolic disorders, and CNS infections.
 In some cases, if an etiology can be found and
corrected, the patient will not require chronic AED
treatment.
20
 Hyperventilation may precipitate absence seizures.
 Sleep, sleep deprivation, sensory stimuli, and
emotional stress may initiate seizures.
 Hormonal changes occurring around the time of
menses, puberty, or pregnancy have been
associated with the onset of or an increased
frequency of seizures.
 Children who are small for gestational age or with
neonatal seizures are also at increased risk for
developing epilepsy.
21
 In many cases, patients will present with
seizures that do not have an identifiable cause
and thus have idiopathic epilepsy.
 The incidence of idiopathic epilepsy is higher in
children.
The most clearly established risk factors for
epilepsy in all age groups are head trauma
(especially in patients in whom the dura
mater has been breached
 and in whom there is evidence of loss of
conciousness), CNS infections, and stroke.
22
 A careful history should be obtained from
patients presenting with seizures because ;
 theophylline,
 alcohol,
 high-dose phenothiazines,
 antidepressants (especially
 maprotiline or buproprion), and street drug use
have been associated with provoking seizures.
 Also, AEDs in toxic concentrations may cause
seizures in certain patients.
23
Common Causes of New-Onset Seizures
 Primary or Acquired Neurological Disorders
Alzheimer's disease or other neurodegenerative
diseases
Brain tumor
Central nervous system infection
Cerebro vascular disease
Febrile seizures of childhood
Genetic or developmental disorders
Head trauma
24
 Hepatic failure
Hypocalcemia
Hypoglycemia
Hypomagnesemia
Hyponatremia
Porphyria
Renal failure
 Alcohol abuse and withdrawal
Anoxia or ischemia
Drug overdose or toxicity
25
Drugs That Have Been Associated With Provoking or
Drugs That May Exacerbate Seizures
 Anti arrhythmic agents (class 1B)
Antimicrobials
β-Lactams and related compounds
Isoniazid
 Quinolones
 Antivirals
Acyclovir
Ganciclovir
 Drugs of abuse
Amphetamine
Cocaine
Ephedra
Methylphenidate
26
 Psychotropic agents
Antidepressants
Antipsychotics
Lithium
Sedative-hypnotic drug withdrawal
Alcohol
Barbiturates (short-acting)
Benzodiazepines (short-acting)
27
 Miscellaneous
Cyclosporine
Lindane
Flumazenil
Metoclopramide
Normeperdine (accumulation in renal failure)
Radiographic contrast agents
Theophylline
Tramadol.
28
PATHOPHYSIOLOGY
 Seizure activity is characterized by paroxysmal
discharges occurring synchronously in a large
population of cortical neurons.
 The seizure originates from the gray matter of any
cortical or perhaps subcortical area.
 Initially, a small number of neurons fire abnormally.
Normal membrane conductances and inhibitory
synaptic currents break down, and excess
excitability spreads, either locally -to produce a
focal seizure
 or more widely to produce a generalized seizure.
29
CONTD…
The clinical manifestations depend on the
 site of the focus,
 the degree of irritability of the surrounding area of
the brain,
 and the intensity of the impulse.
 An abnormality of potassium conductance,
 a defect in the voltage-sensitive ion channels,
 or a deficiency in the membrane ATPases linked to
ion transport may result in neuronal membrane
instability and a seizure.
30
 Selected neurotransmitters (e.g., glutamate,
aspartate, acetylcholine, norepinephrine, histamine,
corticotropin-releasing factor, purines, peptides,
cytokines, and steroid hormones) enhance the
excitability and propagation of neuronal activity,
 whereas γ -aminobutyric acid (GABA) and
dopamine inhibit neuronal activity and
propagation.
31
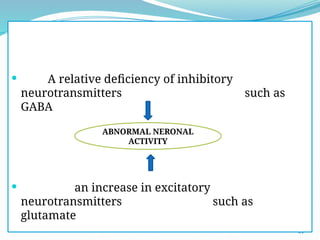
 A relative deficiency of inhibitory
neurotransmitters such as
GABA
 an increase in excitatory
neurotransmitters such as
glutamate
ABNORMAL NERONAL
ACTIVITY
32
Control of abnormal neuronal activity with AEDs is
accomplished by :
 elevating the threshold of neurons to electrical or
chemical stimuli or
 by limiting the propagation of the seizure discharge
from its origin.
 Raising the threshold stabilization of
neuronal
membranes,
 limiting the propagation depression of synaptic
transmission and
reduction of nerve
conduction.
33
 During a seizure, there is a large increase in the
demand for blood flow to the brain to carry off
CO2 and to bring substrates for neuronal
metabolic activity.
 The more prolonged the seizure, the more likely
the brain is to suffer ischemia that may result in
neuronal destruction and brain damage.
 Also, the continued exposure to glutamate, an
excitatory neurotransmitter, may contribute to
neuronal damage.
34
CLINICAL PRESENTATION
 SYMPTOMS
 Symptoms of a specific seizure will depend on seizure
type.
 While seizures can vary between patients.
 Complex partial seizures may include somatosensory or
focal motor features.
• Complex partial seizures are associated with altered
conciousness.
 Absence seizures may appear relatively bland, with
only very brief (seconds) periods of altered
conciousness.
 Generalized tonic-clonic seizures are major convulsive
episodes and are always associated with a loss of
conciousness.
35
 Idiopathic describes syndromes that are
presumably genetic but also those in which
no underlying etiology is documented or
suspected.
 A family history of seizures is commonly
present, and neurologic function is
essentially normal except for the occurrence
of seizures.
36
 Symptomatic cases involve evidence of brain
damage or a known underlying cause.
 A cryptogenic syndrome is assumed to be
symptomatic of an underlying condition that
cannot be documented.
37
 Unknown or undetermined is used when no
cause can be identified.
 This syndromic classification is more
important for prognostic determinations than
for a classification based simply on seizure
type.
38
DIAGNOSTIC TESTS
 EEG is very useful in the diagnosis of various
seizure disorders.
 The EEG may be normal in some patients
who still have the clinical diagnosis of
epilepsy.
 While MRI is very useful (especially imaging
of the temporal lobes), CT scan typically is not
helpful except in the initial evaluation for a
brain tumor or cerebral bleeding.
39
 TREATMENT
40
NONPHARMACOLOGIC THERAPY
 includes :
 diet,
 surgery,
 vagal nerve stimulation
 (VNS), which is implantation of a vagal nerve
stimulator.
 A vagal nerve stimulator is an implanted medical
device approved for use in epilepsy.
41
 most common side effect associated with
stimulation; voice alteration,
 increased cough,
 pharyngitis,
 dyspnea,
 dyspepsia,
 and nausea.
42
 Serious adverse effects reported include ;
 infection,
 nerve paralysis,
 hyesthesia,
 facial paresis,
 left vocal chord paralysis,
 left facial paralysis,
 left recurrent laryngeal nerve injury,
 urinary retention,
 low-grade fever.
43
 Surgery is the most widespread and most useful
non pharmacologic therapy.
 A focus in the temporal lobe has the best chance
for a positive outcome; however,
 extra temporal foci may be excised successfully in
more than 75% of patients.
 The procedure is not without risk.
 Learning and memory are most susceptible to
impairment postoperatively
44
Contd..
 general intellectual abilities are also affected
in a
 small number of patients.
 Surgery may be particularly useful in children
with intractable epilepsy.
 Patients may still need to receive AED therapy
for a period of time following successful
epilepsy surgery in order to prevent seizure
recurrence.
45
Diet
 Protein and calorie intake are set at levels that
will meet requirements for growth.
 Most of the calories are provided in the form of
heavy cream and butter.
 No sugar is allowed.
 Vitamins and minerals are supplemented.
 Medium-chain triglycerides may be substituted
for the dietary fats.
 Fluids are also controlled.
46
Initiating Antiepileptic Drug Therapy
 AEDs are more frequently associated with adverse
effects during initiation of therapy;
 therefore, treatment should begin with low doses
and the dose should be gradually escalated
according to the patient's clinical status.
 When therapy is initiated too aggressively,
patients may experience uncomfortable adverse
effects and are often unwilling to continue
treatment with that agent despite a reduction in
dosage
47
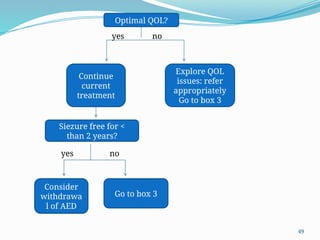
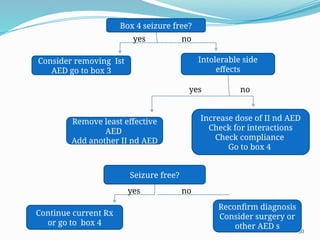
ALGORITHM FOR THE TRAETMENT OF
EPILEPSY
48
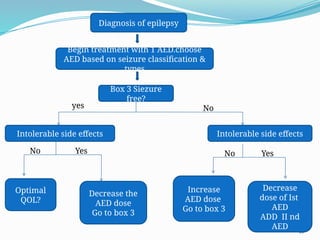
Diagnosis of epilepsy
Begin treatment with 1 AED.choose
AED based on seizure classification &
types
Box 3 Siezure
free?
Intolerable side effects Intolerable side effects
yes No
No Yes
Optimal
QOL?
Decrease the
AED dose
Go to box 3
No Yes
Increase
AED dose
Go to box 3
Decrease
dose of Ist
AED
ADD II nd
AED
49
Optimal QOL?
Continue
current
treatment
Explore QOL
issues: refer
appropriately
Go to box 3
Siezure free for <
than 2 years?
Consider
withdrawa
l of AED
Go to box 3
no
yes
yes no
50
Box 4 seizure free?
Consider removing Ist
AED go to box 3
Intolerable side
effects
Remove least effective
AED
Add another II nd AED
Increase dose of II nd AED
Check for interactions
Check compliance
Go to box 4
Seizure free?
Continue current Rx
or go to box 4
Reconfirm diagnosis
Consider surgery or
other AED s
yes no
yes no
yes no
51
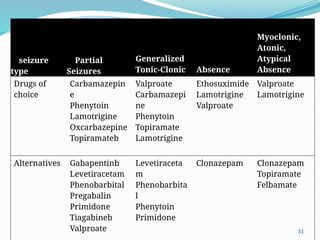
seizure
type
Partial
Seizures
Generalized
Tonic-Clonic Absence
Myoclonic,
Atonic,
Atypical
Absence
Drugs of
choice
Carbamazepin
e
Phenytoin
Lamotrigine
Oxcarbazepine
Topiramateb
Valproate
Carbamazepi
ne
Phenytoin
Topiramate
Lamotrigine
Ethosuximide
Lamotrigine
Valproate
Valproate
Lamotrigine
Alternatives Gabapentinb
Levetiracetam
Phenobarbital
Pregabalin
Primidone
Tiagabineb
Valproate
Levetiraceta
m
Phenobarbita
l
Phenytoin
Primidone
Clonazepam Clonazepam
Topiramate
Felbamate
52
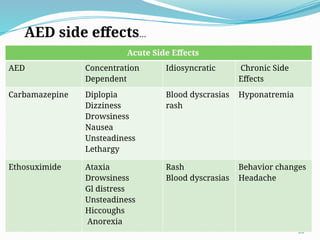
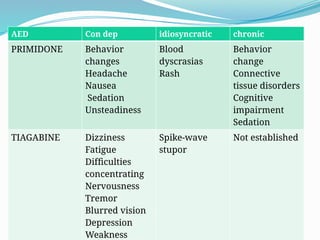
ANTI EPILEPTIC
DRUGS-
SIDE EFFECTS..
53
Acute Side Effects
AED Concentration
Dependent
Idiosyncratic Chronic Side
Effects
Carbamazepine Diplopia
Dizziness
Drowsiness
Nausea
Unsteadiness
Lethargy
Blood dyscrasias
rash
Hyponatremia
Ethosuximide Ataxia
Drowsiness
Gl distress
Unsteadiness
Hiccoughs
Anorexia
Rash
Blood dyscrasias
Behavior changes
Headache
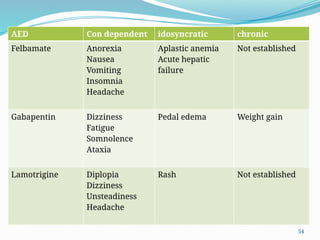
AED side effects…
54
AED Con dependent idosyncratic chronic
Felbamate Anorexia
Nausea
Vomiting
Insomnia
Headache
Aplastic anemia
Acute hepatic
failure
Not established
Gabapentin Dizziness
Fatigue
Somnolence
Ataxia
Pedal edema Weight gain
Lamotrigine Diplopia
Dizziness
Unsteadiness
Headache
Rash Not established
55
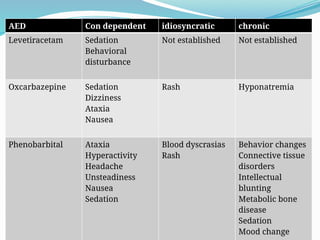
AED Con dependent idiosyncratic chronic
Levetiracetam Sedation
Behavioral
disturbance
Not established Not established
Oxcarbazepine Sedation
Dizziness
Ataxia
Nausea
Rash Hyponatremia
Phenobarbital Ataxia
Hyperactivity
Headache
Unsteadiness
Nausea
Sedation
Blood dyscrasias
Rash
Behavior changes
Connective tissue
disorders
Intellectual
blunting
Metabolic bone
disease
Sedation
Mood change
56
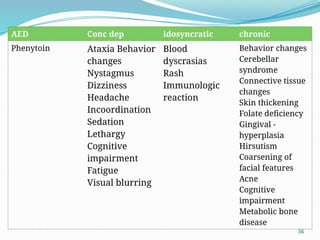
AED Conc dep idosyncratic chronic
Phenytoin Ataxia Behavior
changes
Nystagmus
Dizziness
Headache
Incoordination
Sedation
Lethargy
Cognitive
impairment
Fatigue
Visual blurring
Blood
dyscrasias
Rash
Immunologic
reaction
Behavior changes
Cerebellar
syndrome
Connective tissue
changes
Skin thickening
Folate deficiency
Gingival -
hyperplasia
Hirsutism
Coarsening of
facial features
Acne
Cognitive
impairment
Metabolic bone
disease
57
AED Con dep idiosyncratic chronic
PRIMIDONE Behavior
changes
Headache
Nausea
Sedation
Unsteadiness
Blood
dyscrasias
Rash
Behavior
change
Connective
tissue disorders
Cognitive
impairment
Sedation
TIAGABINE Dizziness
Fatigue
Difficulties
concentrating
Nervousness
Tremor
Blurred vision
Depression
Weakness
Spike-wave
stupor
Not established
58
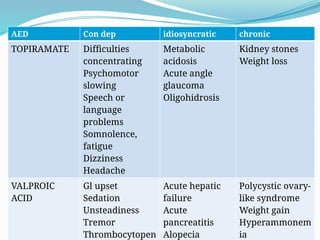
AED Con dep idiosyncratic chronic
TOPIRAMATE Difficulties
concentrating
Psychomotor
slowing
Speech or
language
problems
Somnolence,
fatigue
Dizziness
Headache
Metabolic
acidosis
Acute angle
glaucoma
Oligohidrosis
Kidney stones
Weight loss
VALPROIC
ACID
Gl upset
Sedation
Unsteadiness
Tremor
Thrombocytopen
Acute hepatic
failure
Acute
pancreatitis
Alopecia
Polycystic ovary-
like syndrome
Weight gain
Hyperammonem
ia
59
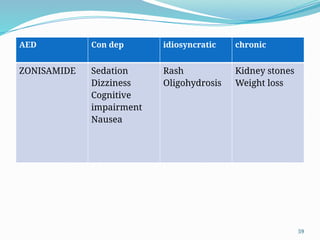
AED Con dep idiosyncratic chronic
ZONISAMIDE Sedation
Dizziness
Cognitive
impairment
Nausea
Rash
Oligohydrosis
Kidney stones
Weight loss
60
CLINICAL CONSIDERATIONS WITH SPECIFIC
DRUGS
 CARBAMAZEPINE
 The absorption of carbamazepine from immediate-release
tablets is slow and erratic because of its low water solubility.
 There is no first-pass metabolism.
 Food may enhance the bioavailability of carbamazepine.
 The suspension dosage form is absorbed faster than the tablets.
 Controlled-release (Tegretol-XR) and sustained-release
(Carbatrol) preparations are also available. These dosage forms
are bioequivalent in twice-daily (ev-ery 12 hours) dosing to
dosing four times daily (every 6 hours) with immediate-release
carbamazepine.
 Patients should be told to take Tegretol-XR with food and that the
casing will be excreted in the feces.
 Tegretol-XR cannot be broken or crushed.
61
 Carbamazepine Tegretol
 Usual initial dose: 400 mg/day
 Usual max. daily dose: 400–2400 mg
 Target serum con range :4–14 mcg/mL
 Oral immediate- and extended-release solid and
liquid dosage forms are available.
 The oral solid dosage form is available as an
immediate-release tablet and as a sustained-
release capsule and a controlled-release tablet.
 The sustained- and controlled-release dosage
forms allow for twice-daily dosing.
62
 Carbamazepine has the unique ability to induce its
own
 metabolism (autoinduction). which requires
careful dosage titration.
 Carbamazepine should be considered a first-line
therapy for patients with newly diagnosed partial
seizures,
 and for patients with primary generalized
convulsive seizures who are not in an emergent
situation.
63
 ETHOSUXIMIDE
 Metabolism occurs in the liver by hydroxy-lation,
and the metabolites are believed to be inactive.
 Ethosuximide usual initial dose:500 mg/day
 Usual max daily dose: 500–2000 mg
 Target serum con range:40–80 mcg/mL
 A loading dose of ethosuximide is not required.
 Titration over 1 to 2 weeks to maintenance doses
of 20 mg/kg per day usually results in
concentrations of approximately 50 mcg/mL.
64
 The total daily dose is usually divided into two
 equal doses.
 This drug is very effective in the treatment of
absence seizures. It is generally well tolerated and
has few pharmacokinetic interactions.
 Disadv :
 Ethosuximide has a very narrow spectrum of
activity
65
 FELBAMATE
 Felbamate is rapidly and well absorbed.
 The absorption is unaffected by food or antacids.
 About 40% to 50% of a dose of felbamate is
metabolized by hydroxylation and conjugation
pathways in the liver, with the remainder being
excreted unchanged in the urine.
 Drug Interactions: Felbamate inhibits the clearance
and increases the serum concentration of
phenytoin, valproic acid, and phenobarbital.
66
 If felbamate is used as monotherapy, the dose is
initiated at 1200 mg/day
 (15 mg/kg in children) and then is increased by
600 mg every 2 weeks up to a maximum dose of
3600 mg (45 mg/kg in children).
 Effective in treating patients with partial
seizures.
 This agent should be reserved for patients not
responding to other AEDs.
 Disadvantages. The use of felbamate is limited by
the association with aplastic anemia and
hepatotoxicity, as well as multiple drug
interactions.
67
 GABAPENTIN
 Gabapentin is eliminated exclusively by the
kidneys, dosage adjustments will be necessary in
patients with significantly impaired renal function.
 Typical starting doses of gabapentin are 300 mg at
bedtime on the first day, increasing to 900 mg/day
over
3 days.
 Faster titration rates (e.g., starting at 300 to 900 mg
three times daily) have been well tolerated.
 Gabapentin has the additional advantages of a
broad therapeutic index with minimal CNS adverse
effects and no drug interactions.
68
 Gabapentin is a second-line agent for patients with
partial seizures who have failed initial treatment.
 In addition,
 although monotherapy trials have no proven
efficacy in previously diagnosed refractory
patients, there may be a role for this drug in
patients with less severe seizure disorders, such as
new-onset partial epilepsy, particularly in the
elderly patient.
 Gabapentin also has been shown to be useful in
the treatment of chronic pain and other
nonepilepsy conditions.
69
 LAMOTRIGINE
 Lamotrigine is potentially a broad-spectrum AED,
having efficacy in partial seizures as well as
several types of generalized seizures.
 A pediatric dosage form is available. It does not
induce or inhibit the metabolism of other AEDs.
 Lamotrigine has linear pharmacokinetics and is
not highly protein bound.
 Lamotrigine appears to be generally well tolerated
in both children and elderly adult patients and
does not cause weight gain.
70
 Lamotrigine is useful as both adjunctive treat-
ment in patients with partial seizures and as
monotherapy.
 useful alternative therapy in patients with
primary generalized seizure types such as
absence.
71
 LEVETIRACETAM
 Levetiracetam, an S-enantiomer pyrolidone
derivitive, is chemically unrelated to other
available AEDs.
 Typical initial dosing of this agent is 500 mg orally
twice daily, titrating at 1000-mg/day increments
every 2 weeks to a maximum recommended dose
of 3000 mg/day (1500 mg twice daily).
 Currently, levetiracetam is indicated for pa-tients
with partial seizures who have failed initial
therapy.
72
 OXCARBAZEPINE
 Oxcarbazepine, which is structurally related to
carbamazepine, is a prodrug that is rapidly
converted to a 10-monohydrate derivative (MHD),
which is the active component
 In adults, the starting dose of oxcar-bazepine as
monotherapy is 300 mg once or twice a day.
 The dose is titrated upward at a rate of 600 mg/day
per week to a maximum dose of 2400 mg/day.
73
 For children aged 4 to 16 years, the starting dose
is 8 to 10 mg/kg given twice daily, not to exceed
600 mg/day
 The dose is titrated to the target dose over 2
weeks.
 The recommended daily dose according to weight
is 20–29 kg: 900 mg/day;
 29.1–39 kg: 1200 mg/day;
 greater than 39 kg: 1800 mg/day.
74
 Oxcarbazepine is indicated for use as
monotherapy or adjunctive therapy in the
treatment of partial seizures in adults and as
monotherapy and adjunctive therapy in the
treatment of partial seizures in patients as young
as 4 years of age with epilepsy.
 It is also a potential first-line drug for patients
with primary generalized convulsive seizures.
 Oxcarbazepine may be effective in patients not
demonstrating a response to carbamazepine.
75
 PHENOBARBITAL
 Phenobarbital penetrates the brain at a rate
comparable with that of phenytoin, and peak
concentrations are achieved 3 to 20 minutes after
an intravenous dose.
 In nonacute situations, phenobar-bital should be
started in low doses and titrated upward.
 Because the half-life of pheno-barbital is long,
doses can be given once daily.
 Bedtime dosing may minimize CNS depression.
 Because of its long half-life, phenobarbi-tal takes 3
to 4 weeks to reach steady state.
76
 Therefore, rapid dosage adjustments should be
avoided in a nonacute situation.
 Phenobarbital is the drug of choice for neonatal
seizures but in other situtations is reserved for
patients who have failed other AEDs.
 It may be useful given intravenously in refractory
status epilepticus.
77
 PHENYTOIN
 Four dosage forms are used for oral administration
of phenytoin .
 The salt content should be considered when
changing from one dosage form to another.
 Changes between dosage forms may lead to
changes in phenytoin concen-tration. Phenytoin
capsules are designated as immediate-release or
extended-release
 Only the extended-release capsules should be used
in once-a-day dosing.
78
 Phenytoin has long been a first-line AED for
primary generalized convulsive and partial
seizures.
 Its use in therapy may be reevaluated as more
experience is gained with newer AEDs.
 Phenytoin or fosphenytoin is a first-line drug for
the treatment of status epilepticus.
79
 VALPROIC ACID
 Valproic acid is available as a soft gelatin capsule, an
enteric-coated tablet, a syrup, a “sprinkle,” an extended-
release formulation designed for once-daily dosing, and
a parenteral (intravenous) for-mulation for replacement
of oral therapy or in situations where rapid loading of
valproic acid is deemed necessary.
 Valproic acid is available in multiple dosage
formulations. It has a wide therapeutic index and can be
considered a broad-spectrum AED.
 It also may be useful in other neurologic or psychiatric
disorders, including migraine headache and bipolar-
affective
 disorder.
80
 Valproic acid is first-line therapy for primary
generalized seizures such as myoclonic, atonic, and
absence seizures.
 It can be used as both monotherapy and adjunctive
therapy for partial seizures, and it can be very
useful in patients with mixed seizure disorders
81
 ZONISAMIDE
 Zonisamide is currently approved for the adjunctive
treatment of partial seizures.
 Thus far, insufficient data exist to support its use as
initial monotherapy.
 potentially effective in a variety of partial and
primary generalized seizure types,
 The dose should be titrated slowly to patient
response.
 Renal stones and oligohydrosis also have been
associated with zonisamide.
82
 TOPIRAMATE
 Topiramate is a sulfamate-substituted
monosaccharide.
 The kidney mainly eliminates it, although some liver
metabolism occurs.
 Topiramate is a second-line AED for patients with
partial seizures who have failed initial therapy.
 Its role as a primary AED and in other seizure types
is being evaluated.
 Starting doses are 12.5 to 50 mg/day, increasing by
12.5 to 50 mg/day every week or every other week.
 The minimally effective dose of topiramate is
approximately 200 mg/day.
83
EVALUATION OF THERAPEUTIC
OUTCOMES
 Patients should be chronically monitored for seizure
control, side effects, social adjustment, drug
interactions, compliance, quality of life, and toxicity.
 Screening for neuropsychiatric disorders is also
important.
 Clinical response is more important than serum
drug concentrations.
 Patients should be asked to record severity and
frequency of seizures in a seizure diary.
84
 Outcomes can be assessed by prospective clinical
monitoring, drug utilization review, and quality-of-
life assessments.
 Clinical monitoring involves identifying the
number and type of seizures.
 A therapeutic range should be established for each
patient.
 This range should define concentrations that result
in minimal side effects and optimal seizure control.
 This therapeutic plasma concentration range
should be used to identify the appropriate patient
specific dose.
85