



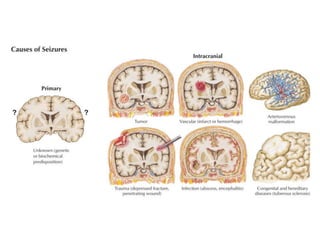






































Antiepileptic drugs
Dr. Karun Kumar
Assistant Professor
Dept. of Pharmacology
Definitions
• Seizure  (from the Latin sacire, “to take
possession of ”) is a transient occurrence of signs or
symptoms due to abnormal excessive or
synchronous neuronal activity in the brain
• Epilepsy  Condition in which a person has a risk
of recurrent seizures due to a chronic, underlying
process. Clinical phenomenon rather than a single
disease entity.
Types of seizures
• Focal seizures  Originate within networks limited
to one brain region (partial seizures NO longer
used)
• Generalized seizures  Arise within and rapidly
engage networks distributed
Classification of seizures (2017 ILAE)
1. Focal Onset (having intact or impaired awareness,
motor or nonmotor onset, or evolve from focal to
bilateral tonic clonic)
2. Generalized Onset
a. Motor  Tonic-clonic, Other motor (e.g., atonic,
myoclonic)
b. Nonmotor (absence)
3. Unknown Onset
a. Motor, nonmotor, or unclassified
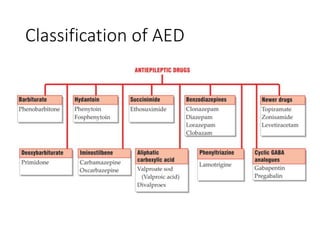
Classification of AED
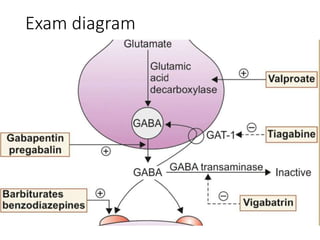
Exam diagram
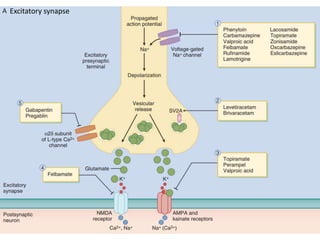
Excitatory synapse
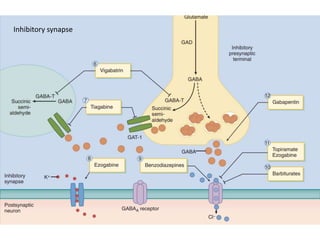
Inhibitory synapse
Approach to the patient
• History and examination
• 1st goal  Determine whether the event was truly
a seizure
• In-depth history is essential, because in many cases
the diagnosis of a seizure is based solely on clinical
grounds—the examination and laboratory studies
are often normal
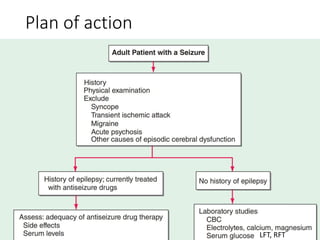
Plan of action
LFT, RFT
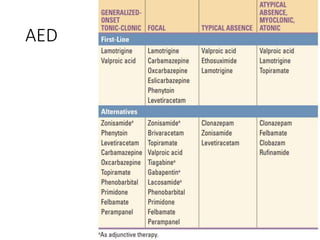
AED
PNES or PNEE
• Pseudoseizures, psychogenic seizures, and
hysterical seizures are older terms
• Clinically resemble epileptic seizures but occur
without the excessive synchronous cortical
electroencephalographic activity that defines
epileptic seizures
• These terms reinforce the idea that the events are
not epileptic seizures and are of psychiatric origin
Phenytoin
• MOA  Prevents repetitive detonation of normal
brain cells (↑ inact. state of VGSC)
• Also,
1. ↓ presynaptic release of glutamate
2. ↑ GABA release
3. ↓ Ca2+ influx
Adverse effects-PHENYTOIN
• Plasma level monitoring needed (0 order k.)
• Hypertrophy of gums
• Enzyme induction
• Neutropenia and other hypersensitivity reactions
• Young girls beware ! Causes hirsutism, coarsening
of facial features and acne
• Teratogenic
• Osteomalacia
• Interference with folate absorption leads to
megaloblastic anemia
• Neurological manifestations at higher doses 
Ataxia, vertigo, nystagmus, diplopia
Uses
• Used only when better tolerated newer drugs
cannot be used
• Trigeminal neuralgia  2nd choice drug to
Carbamazepine
Interactions
1. Phenobarbitone competitively inhibits phenytoin
metabolism, while by enzyme induction both
enhance each other’s degradation—
unpredictable overall interaction
2. Carbamazepine and phenytoin induce each
other’s metabolism
3. Valproate displaces protein bound phenytoin and
decreases its metabolism  Plasma level of
unbound phenytoin increases
4. Chloramphenicol, Isoniazid, Cimetidine and
Warfarin inhibit phenytoin metabolism  Can
precipitate its toxicity
5. Phenytoin induces microsomal enzymes and
increases degradation of steroids (failure of oral
contraceptives), Doxycycline, Theophylline
Fosphenytoin
• Water soluble prodrug of Phenytoin has been
introduced to overcome the difficulties in i.v.
administration of Phenytoin, which it has replaced
for use in status epilepticus.
• On i.v. injection it is less damaging to the intima
• While Phenytoin cannot be injected in a drip of
glucose solution (because it gets precipitated),
fosphenytoin can be injected with both saline and
glucose
Carbamazepine
• 1st line AED for focal seizures and trigeminal
neuralgia (MOA  ↑ inact. state of VGSC)
• Manic depressive illness and acute mania  As an
alternative to Lithium
• Carbamazepine produces dose-related
neurotoxicity  sedation, dizziness, vertigo,
diplopia and ataxia
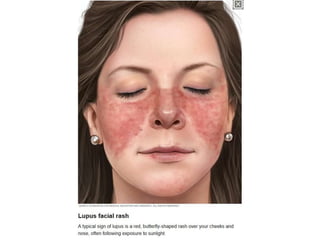
• Hypersensitivity  Rashes, photosensitivity,
hepatitis, lupus like syndrome and rarely
agranulocytosis, aplastic anemia
Lupus like syndrome
• Autoimmune disorder caused by a reaction to
certain medications
• Symptoms are muscle and joint pain sometimes
with swelling;flu-like symptoms of fatigue and fever
• SHIP drugs are responsible
1. Sulfonamides incl. dapsone and PAS
2. Hydralazine
3. Isoniazid
4. Procainamide
Interactions
• Carbamazepine is an enzyme inducer; can reduce
efficacy of Haloperidol, oral contraceptives
• Metabolism of Carbamazepine is induced by
Phenobarbitone, Phenytoin, Valproate and vice
versa
• Erythromycin, Fluoxetine, Isoniazid inhibit
metabolism of carbamazepine
Oxcarbazepine
• Newer congener of carbamazepine
• Toxic effects due to the epoxide metabolite are
avoided
• Drug interactions and auto induction of own
metabolism are less marked, because it is a weak
enzyme inducer
• Risk of hepatotoxicity is estimated to be lower than
carbamazepine; but that of hyponatremia is more
• Indications are the same as for carbamazepine, but
it may be better tolerated
• Dose to dose it is 1½ times less potent
Eslicarbazepine
• Prodrug
• Rapidly converted in liver to the same active
metabolite as is oxcarbazepine
• Same range of therapeutic and toxic effects
• Once daily dosing
• Add-on drug for focal seizure with or without
generalization only in adults
Valproic acid (Sodium valproate)
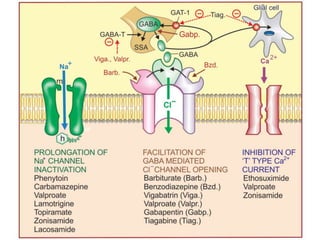
• Valproate appears to act by multiple mechanisms:
1. A phenytoin-like frequency-dependent
prolongation of Na+ channel inactivation.
2. Weak attenuation of Ca2+ mediated ‘T’ current
(Ethosuximide like)
3. Augmentation of release of inhibitory transmitter
GABA by inhibiting its degradation (by GABA-
transaminase)
4. Blockade of excitatory NMDA type of glutamate
receptor
Uses
• Drug of choice for
1. Generalised tonic clonic seizures
2. Absence seizures
3. Myoclonic seizures
4. Atonic seizures
• Alternative/adjuvant drug for focal seizures
• Mania and bipolar illness  As alternative to
Lithium
Adverse effects (VALPROATE)
• Vomiting
• Alopecia
• Liver toxicity
• Pancreatitis
• Rash
• Obesity
• Agranulocytosis
• Teratogenic (Neural tube defects in offspring)
• E (dEntist)  Dentist may face excess bleeding
while executing a dental procedure as Valproate
causes increased bleeding tendency
• E  Epigastric pain
Interactions
1. ↑ plasma levels of Phenobarbitone and Lamotrigine
2. Displaces Phenytoin from protein binding site
3. Inhibits hydrolysis of active epoxide metabolite of
Carbamazepine
4. Concurrent administration of Clonazepam and
valproate is C/I (absence status may be pptd.)
5. Foetal abnormalities are more common if Valproate
and Carbamazepine are given concurrently
Divalproex (Semisodium
valproate)
• Coordination compound of valproic acid with
sodium valproate (1:1)
• Oral absorption is slower, but bioavailability is the
same
• Gastric tolerance may be better
• Primarily used in mania and bipolar illness
• May be used like Valproate
Lamotrigine
• Blocks voltage sensitive Na+ channels
• Broad-spectrum antiepileptic
• S/E  Sleepiness, dizziness, diplopia, ataxia and
vomiting. Rash may be a severe reaction,
particularly in children, requiring withdrawal
• Dose of lamotrigine should be reduced to half in
patients taking Valproate
Uses
• Drug of choice for
1. Generalised tonic clonic seizures
2. Absence seizures
3. Myoclonic seizures
4. Atonic seizures
5. Focal seizures
Gabapentin
• Enhances GABA release, but does not act as agonist
at GABAA receptor
• Adjunctive therapy in focal seizures
• 1st line drug for neuralgic pain due to diabetic
neuropathy and postherpetic neuralgia
• Prophylactic effect in migraine
• Alternative drug for phobic states
• S/E  Sedation, tiredness, dizziness, tremors &
unsteadiness
Pregabalin
• Similar to gabapentin
• Used for
1. Neuropathic pain (diabetic neuropathy,
postherpetic neuralgia, complex regional pain
syndrome (CRPS)
2. Chronic pain
S/E  Poor concentration, rashes and allergic
reactions have been complained
Levetiracetam
• 1st line drug  Focal seizures
• 2nd line drug  GTCS and typical absence seizures
• MOA  Binds selectively to a synaptic vesicular
protein ‘SV2A’, and this may alter release of
glutamate and/or GABA across the synapse,
thereby exerting anti-seizure effect
• S/E  Sleepiness, dizziness, weakness
Topiramate
• 1st line drug in atypical absence, myoclonic and
atonic seizures
• 2nd line drug in GTCS and focal seizures
• Broad spectrum anticonvulsant drug acting by :-
1. Prolongation of Na+ channel inactivation
2. Suppression of repetitive neuronal firing
3. GABA potentiation
4. Antagonism of certain glutamate receptors
5. Neuronal hyperpolarization through K+ channels
• A/E  Impairment of attention, sedation, ataxia,
word finding difficulties, poor memory, weight loss,
paresthesias and renal stones.
• Other uses
• Approved for prophylaxis of migraine (when β
blockers/other prophylactics are C/I or ineffective)
Zonisamide
• Adjunctive therapy in GTCS and focal seizures
• MOA  Prolongation of Na+ channel inactivation
• S/E  Somnolence, dizziness, headache, irritability
and anorexia.
• Metabolic acidosis and renal stones can occur.
• C/I  In patients sensitive to Sulfonamides
Lacosamide
• Adjunctive therapy in focal seizures
• MOA  ↑ Na+ channel inactivation and suppresses
repetitive firing of neurons
• A/E  Ataxia, vertigo, diplopia, tremor, depression
and cardiac arrhythmia
Treatment of epilepsies
• Antiepileptic drugs suppress seizures, but do not
cure the disorder
• Aim  Control and prevent all seizure activity at an
acceptable level of side effects
• Cause of epilepsy should be searched; if found and
treatable, an attempt to remove it should be made
• Some general principles of symptomatic treatment
with antiepileptic drugs are 
1. Start with one 1st line drug
2. Initiate treatment early
3. Start at a low dose; gradually ↑ until
1. Effective control of seizures is achieved OR
2. Side-effects develop
4. Optimise adherence (use minimum number of
doses per day)
5. If 1st drug fails start second 1st line drug, followed
if possible by gradual withdrawal of 1st
6. If 2nd drug fails, start 2nd line drug in combination
with the preferred baseline drug at maximum
tolerated dose (beware interactions)
7. If this combination fails, replace 2nd line drug with
alternative second-line drug
8. If this combination fails, check adherence and
reconsider diagnosis (Are events seizures? Occult
lesion? Treatment adherence/alcohol/drugs
confounding response?)
9. Consider alternative, non-drug treatments (e.g.
epilepsy surgery, vagal nerve stimulation)
10. Use minimum number of drugs in combination at
any one time
Epilepsy in pregnancy
1. Pre-conception counselling  Best; start folic
acid (5 mg daily for 2 months) before conception
to reduce the risk of fetal malformations.
2. Risk of fetal malformation is minimised if a single
drug is used. Carbamazepine and Lamotrigine
have the lowest incidence of major fetal
malformations
3. Prophylactic folic acid supplementation in 2, 3 tri.
4. Vit. K in the last month of pregnancy
Dental implications
1. Dentists have to recognize and manage Phenytoin
induced gum hypertrophy
2. In an epileptic patient, dental procedure should
be carried out only after ensuring that the patient
is under adequate anticonvulsant drug cover and
has taken his/her medication
3. In the event of a patient developing an attack of
GTCS during dental procedure, the first priority is
to prevent injuries due to biting or fall. Ensure
that the patient is secure on the flat dental chair
or floor
• Any denture or instrument should be immediately
removed from the mouth
• The head should be turned to the side to prevent
the tongue from falling back and obstructing the
airway
• Give oxygen through a face mask to support
respiration if any sign of cyanosis is seen
• Do not attempt to stop convulsive movements by
restraining the patient
• In case the seizures do not stop or recur within 10-
20 minutes, management is as for status epilepticus
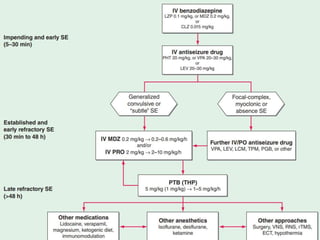
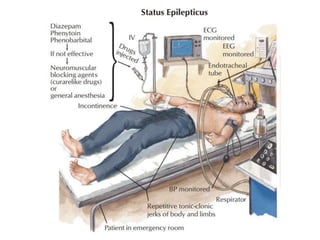
Status epilepticus
• Continuous seizures or repetitive, discrete seizures
with impaired consciousness in the interictal period
1. GCSE (e.g., persistent, generalized electrographic
seizures, coma, and tonic-clonic movements)
2. Nonconvulsive status epilepticus (e.g., persistent
absence seizures or focal seizures with confusion
or partially impaired consciousness, and minimal
motor abnormalities)
• Practical def.  Duration of seizures prompts the
acute use of anticonvulsant therapy
• In GCSE  When seizures last beyond 5 min.
Febrile convulsions
• Some children (<5 yrs.) develop convulsions during
fever
• Attempt should be made to see that they do not
develop fever, but when they do, temperature
should not be allowed to rise by using paracetamol
and external cooling
• DOC  Rectal diazepam 0.5 mg/kg
• In recurrent cases or those at particular risk of
developing epilepsy  Intermittent prophylaxis
with diazepam (oral or rectal)
Infantile spasms (hypsarrhythmia)
• Therapy of this condition is unsatisfactory
• antiepileptic drugs are generally useless
• Corticosteroids afford symptomatic relief but
cannot be used for long-term due to A/E
• Clonazepam, Valproate and Vigabatrin may afford
some relief