ANTICOAGULANTS
Drugs that preventharmful blood-clot formation
Pharmacology • Third Year B.Pharm
Focus of the session
Mechanism • Classification • Uses • Adverse effects • Monitoring • Antidotes
1
2.
Start with aclinical problem Why do we need anticoagulants?
Pharmacology • Anticoagulants
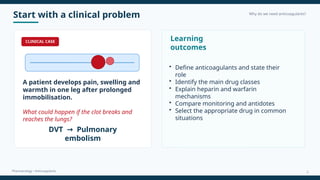
CLINICAL CASE
A patient develops pain, swelling and
warmth in one leg after prolonged
immobilisation.
What could happen if the clot breaks and
reaches the lungs?
DVT Pulmonary
→
embolism
Learning
outcomes
• Define anticoagulants and state their
role
• Identify the main drug classes
• Explain heparin and warfarin
mechanisms
• Compare monitoring and antidotes
• Select the appropriate drug in common
situations
2
3.
What are anticoagulants?Core definition
Pharmacology • Anticoagulants
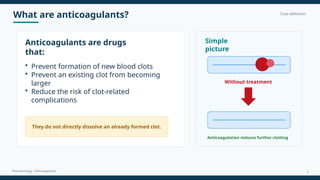
Anticoagulants are drugs
that:
• Prevent formation of new blood clots
• Prevent an existing clot from becoming
larger
• Reduce the risk of clot-related
complications
They do not directly dissolve an already formed clot.
Simple
picture
Without treatment
Anticoagulation reduces further clotting
3
4.
Do not confusethese three groups A common examination point
Pharmacology • Anticoagulants
Antiplatelets
Act mainly on platelets
Useful mainly in arterial
thrombosis
Examples: aspirin,
clopidogrel
Anticoagulants
Act mainly on coagulation
factors
Prevent formation or
extension of clots
Examples: heparin, warfarin
Fibrinolytics
Activate clot breakdown
Can dissolve a recently
formed clot
Examples: alteplase,
streptokinase
4
5.
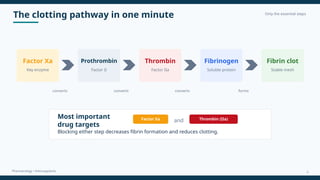
The clotting pathwayin one minute Only the essential steps
Pharmacology • Anticoagulants
Factor Xa
Key enzyme
Prothrombin
Factor II
Thrombin
Factor IIa
Fibrinogen
Soluble protein
Fibrin clot
Stable mesh
converts converts converts forms
Most important
drug targets
Factor Xa and Thrombin (IIa)
Blocking either step decreases fibrin formation and reduces clotting.
5
6.
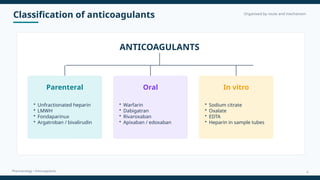
Classification of anticoagulantsOrganised by route and mechanism
Pharmacology • Anticoagulants
ANTICOAGULANTS
Parenteral
• Unfractionated heparin
• LMWH
• Fondaparinux
• Argatroban / bivalirudin
Oral
• Warfarin
• Dabigatran
• Rivaroxaban
• Apixaban / edoxaban
In vitro
• Sodium citrate
• Oxalate
• EDTA
• Heparin in sample tubes
6
7.
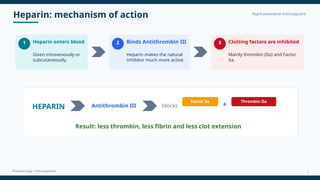
Heparin: mechanism ofaction Rapid parenteral anticoagulant
Pharmacology • Anticoagulants
1 Heparin enters blood
Given intravenously or
subcutaneously.
2 Binds Antithrombin III
Heparin makes the natural
inhibitor much more active.
3 Clotting factors are inhibited
Mainly thrombin (IIa) and Factor
Xa.
HEPARIN Antithrombin III blocks
Factor Xa
+
Thrombin IIa
Result: less thrombin, less fibrin and less clot extension
7
8.
Heparin: clinical profileUses, monitoring, adverse effects and antidote
Pharmacology • Anticoagulants
Uses
• DVT and pulmonary embolism
• Acute coronary syndromes
• Haemodialysis and cardiac procedures
Monitoring
• Unfractionated heparin: aPTT
• Platelet count is monitored
• LMWH usually needs no routine aPTT
Adverse
effects
• Bleeding
• Heparin-induced thrombocytopenia
• Osteoporosis with prolonged use
Antidote
• Protamine sulfate
• Neutralises heparin
• Dose is based on amount of heparin given
8
9.
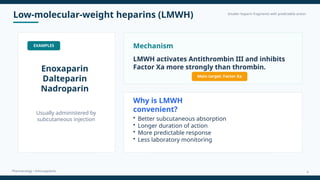
Low-molecular-weight heparins (LMWH)Smaller heparin fragments with predictable action
Pharmacology • Anticoagulants
EXAMPLES
Enoxaparin
Dalteparin
Nadroparin
Usually administered by
subcutaneous injection
Mechanism
LMWH activates Antithrombin III and inhibits
Factor Xa more strongly than thrombin.
Main target: Factor Xa
Why is LMWH
convenient?
• Better subcutaneous absorption
• Longer duration of action
• More predictable response
• Less laboratory monitoring
9
10.
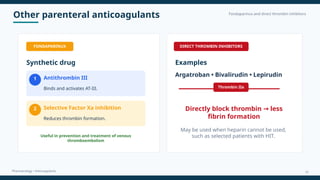
Other parenteral anticoagulantsFondaparinux and direct thrombin inhibitors
Pharmacology • Anticoagulants
FONDAPARINUX
Synthetic drug
1 Antithrombin III
Binds and activates AT-III.
2 Selective Factor Xa inhibition
Reduces thrombin formation.
Useful in prevention and treatment of venous
thromboembolism
DIRECT THROMBIN INHIBITORS
Examples
Argatroban • Bivalirudin • Lepirudin
Thrombin IIa
Directly block thrombin less
→
fibrin formation
May be used when heparin cannot be used,
such as selected patients with HIT.
10
11.
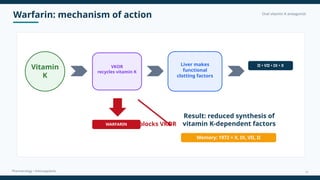
Warfarin: mechanism ofaction Oral vitamin K antagonist
Pharmacology • Anticoagulants
Vitamin
K
VKOR
recycles vitamin K
Liver makes
functional
clotting factors
II • VII • IX • X
WARFARIN blocks VKOR
Result: reduced synthesis of
vitamin K-dependent factors
Memory: 1972 = X, IX, VII, II
11
12.
Warfarin: practical pointsSlow onset, careful monitoring
Pharmacology • Anticoagulants
Route & onset
Oral drug
Slow onset of action
Used mainly for long-term
therapy
Monitoring
Prothrombin time (PT)
Reported as INR
Dose is individualised
Antidote
Vitamin K
Severe bleeding may need
additional reversal measures
Important adverse effects
and precautions
• Bleeding is the major adverse effect
• May cause skin necrosis early in therapy
• Many drug and food interactions
• Generally avoided during pregnancy
12
13.
Direct oral anticoagulants(DOACs) Fast, predictable oral anticoagulation
Pharmacology • Anticoagulants
DIRECT THROMBIN INHIBITOR
DABIGATRAN
Thrombin IIa
↓ Fibrin formation
Specific reversal agent: idarucizumab
DIRECT FACTOR Xa INHIBITORS
RIVAROXABAN
APIXABAN
EDOXABAN
“XABAN” drugs block Factor Xa
Specific reversal agent may be used for selected
Xa inhibitors where available.
13
14.
Heparin versus warfarinHigh-yield comparison
Pharmacology • Anticoagulants
Feature Heparin Warfarin
Route IV / SC Oral
Onset Rapid Slow
Mechanism Activates Antithrombin III Blocks vitamin K recycling
Main effect Inhibits Xa and IIa Reduces II, VII, IX and X
Monitoring aPTT PT / INR
Antidote Protamine sulfate Vitamin K
Pregnancy Commonly preferred when needed Generally avoided
Feature Heparin Warfarin
14
15.
Monitoring and reversal:remember the pairs Rapid recall
Pharmacology • Anticoagulants
Unfractionated
heparin
MONITOR
aPTT
REVERSAL
Protamine sulfate
Warfarin
MONITOR
PT / INR
REVERSAL
Vitamin K
Dabigatran
MONITOR
No routine test
REVERSAL
Idarucizumab
15
16.
Clinical application: choosethe drug Think before answering
Pharmacology • Anticoagulants
CASE
A patient with acute
pulmonary embolism
requires immediate
anticoagulation.
Which characteristic is most
important?
Reasoning
1 Need rapid action
An emergency requires an anticoagulant with immediate or rapid onset.
2 Choose a parenteral drug
Heparin or an appropriate LMWH may be selected depending on the
patient.
3 Plan continuation
Long-term oral therapy may follow after clinical assessment.
Key answer: rapid onset is the deciding feature.
16
17.
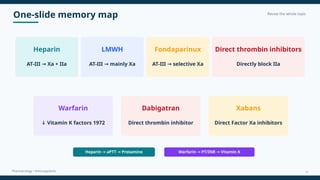
One-slide memory mapRevise the whole topic
Pharmacology • Anticoagulants
Heparin
AT-III Xa + IIa
→
LMWH
AT-III mainly Xa
→
Fondaparinux
AT-III selective Xa
→
Direct thrombin inhibitors
Directly block IIa
Warfarin
↓ Vitamin K factors 1972
Dabigatran
Direct thrombin inhibitor
Xabans
Direct Factor Xa inhibitors
Heparin aPTT Protamine
→ → Warfarin PT/INR Vitamin K
→ →
17
18.
Summary and quickviva End-of-session check
Pharmacology • Anticoagulants
Take-home
points
• Anticoagulants prevent new clot formation
and clot extension
• Factor Xa and thrombin are the main
targets
• Heparin acts rapidly through Antithrombin
III
• Warfarin reduces vitamin K-dependent
factors
• Bleeding is the major adverse effect of all
anticoagulants
Quick viva
questions
1 What is the antidote of heparin?
2 Which test monitors warfarin?
3 Name one LMWH.
4 Which factors depend on vitamin K?
5 What does a “xaban” drug inhibit?
THANK YOU
18
Editor's Notes
#1 Begin by asking: “What happens when a blood clot forms in the wrong place?” Explain that anticoagulants do not make blood watery. They reduce the ability of blood to form or extend harmful clots.
#2 Use the case to create interest. Ask students to identify DVT and pulmonary embolism. Tell them that anticoagulants prevent clot extension and new clot formation; the body’s own fibrinolytic system gradually removes the clot.
#3 Clarify the common term “blood thinner.” Anticoagulants do not literally thin the blood. Their main action is to interfere with clotting factors so the clotting process slows down.
#4 Ask students to compare the target: platelets, clotting factors, or the fibrin clot itself. This distinction makes the rest of the topic easier.
#5 Do not teach the entire cascade initially. Focus on Factor Xa and thrombin. Explain that Xa generates thrombin, and thrombin converts fibrinogen into fibrin.
#6 Tell students that parenteral drugs are injections and usually act quickly. Warfarin and DOACs are oral drugs. In-vitro anticoagulants are used outside the body, especially in blood collection and storage.
#7 Emphasise that heparin acts indirectly through Antithrombin III. It does not destroy clotting factors. It accelerates the natural inhibition of Xa and thrombin.
#8 HIT is a paradox: platelet count falls, but thrombosis may occur. If HIT is suspected, heparin should be stopped and an alternative anticoagulant is considered.
#9 Compare LMWH with unfractionated heparin. LMWH acts mainly on Factor Xa, has a longer duration and a more predictable effect, so routine aPTT monitoring is generally unnecessary.
#10 Fondaparinux acts indirectly through antithrombin but selectively inhibits Xa. Argatroban and bivalirudin act directly on thrombin and do not require antithrombin.
#11 Explain why warfarin has a slow onset: it does not remove clotting factors already circulating. The body must first use those factors, after which the anticoagulant effect becomes evident.
#12 INR allows comparison of PT results between laboratories. Mention that warfarin has many interactions and patients should maintain a consistent diet rather than suddenly changing vitamin K intake.
#13 DOACs have rapid onset and predictable effects. They usually do not require routine INR monitoring. Their use still requires attention to kidney function, bleeding risk and drug interactions.
#14 This is a key exam slide. Ask students to compare route, onset, monitoring and antidote. Repeat the memory pair: heparin–aPTT–protamine; warfarin–PT/INR–vitamin K.
#15 Explain that monitoring depends on the drug. Routine laboratory monitoring is not needed for most DOACs, but clinical monitoring and renal function assessment remain important.
#16 Use this slide as a class discussion. The goal is not to prescribe a specific regimen but to make students connect acute conditions with rapid-onset parenteral anticoagulation.
#17 Pause on each box and ask students to say the target. Finish by repeating the monitoring-antidote pairs.
#18 Use the five questions as an exit ticket. Ask students to answer aloud or write the answers in one minute.

 Most read

 Most read
 Most read