Department of Pharmacology
IGMC, Shimla
ANTI PLATELETS
WHAT ARE PLATELETS ?
White, discoid
Smallest element of flowing blood
1 - 2 microns diameter
Lipid bilayer membrane
Normal range 150000 – 450000 microlitre blood
Formed from cytoplasm of megakaryocytes
No nucleus
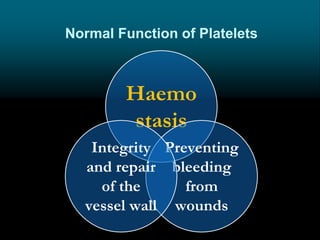
Normal Function of Platelets
Haemo
stasis
Preventing
bleeding
from
wounds
Integrity
and repair
of the
vessel wall
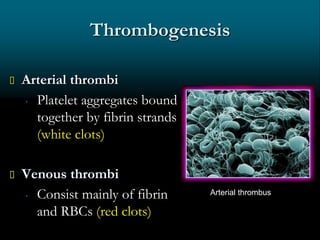
Thrombogenesis
ď‚  Platelet aggregates bound
together by fibrin strands
(white clots)
ď‚  Consist mainly of fibrin
and RBCs (red clots)
Arterial thrombus
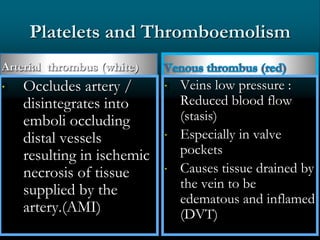
Platelets and Thromboemolism
ď‚  Occludes artery /
disintegrates into
emboli occluding
distal vessels
resulting in ischemic
necrosis of tissue
supplied by the
artery.(AMI)
ď‚  Veins low pressure :
Reduced blood flow
(stasis)
ď‚  Especially in valve
pockets
ď‚  Causes tissue drained by
the vein to be
edematous and inflamed
(DVT)
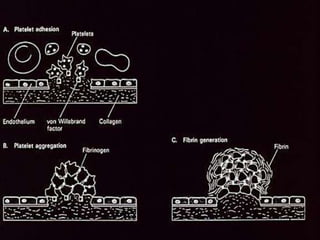
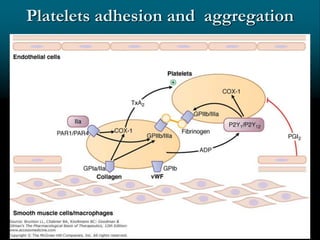
Platelets adhesion and aggregation
9
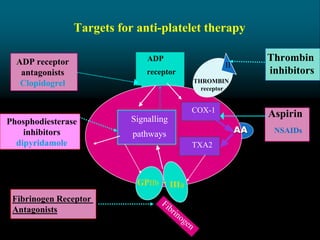
Targets for anti-platelet therapy
Aspirin
NSAIDs
ADP
receptor
COX-1
TXA2
GPIIb - IIIa
Signalling
pathways
ADP receptor
antagonists
Clopidogrel THROMBIN
receptor
Thrombin
inhibitors
II
Phosphodiesterase
inhibitors
dipyridamole
Fibrinogen Receptor
Antagonists
AA
CLASSIFICATION OF
ANTIPLATELET AGENT-
1. PGI 2
2. TXA2 inhibitors-
3. ADP antagonists-
• Ticlopidine, Clopidogrel
4. Phospodiesterase inhibitor-
• Dipyridamole, Pentoxifylline
5. Glycoprotein IIB/IIIA receptors antagonists-
Abciximab, Eptifibatide, Tirofiban
PGI 2- (Prostacyclins)
Naturally occurring potent vasodilator and inhibitor of platelet aggregation.
Produced by vessel walls, also present in brain ,gut and kidney.
Formed from PG endperoxidase by the action of COX
Inhibit platelet aggregation by stimulating adenylcyclase increasing cyclic
AMP levels in platelets.
Prostacyclins causes hypotension , tachycardia ,headache. intense facial
flushing
Very unstable ,1/2 life of 3 mins.
Prostacyclins (Epoprostananol)-used during haemodialysis.
ASPIRIN-
• MOA-
In platelets major COX product is TXA2 , a labile
inducer of platelet aggregation and potent
vasoconstrictor.
Aspirin blocks production of TXA2 by covalently
acetylating serine residue near the active site of COX, this
enzyme produces cyclic endperoxidase precursor of TXA2.
Since platelets do not synthesize new proteins hence the
action of aspirin on platelets is permanent (7-10 days).
For complete inactivation of platelet COX dose of aspirin req. is 160
mg daily.
Reason—
Higher doses decrease efficacy of aspirin as they inhibit production of
prostacyclins which is spared at low doses. (75-150mg)
Higher doses also increase toxicity esp.. Bleeding.
USES OF ASPIRIN
Prevention of AMI in pts. Of unstable angina
Prevention of reinfarction in pts. Of AMI and IHD
Prevention of stroke in pts. Of cerbrovascular accidents and h/o
TIA
For improving prognosis in patients with atherosclerotic
peripheral vascular diseases
Percutaneous angioplasty for coronary thrombosis ,
Primary prophylaxis of thromboembolism in pts with prosthetic
heart valves
ADP Antagonist: Ticlopedine
1. Ticlopidine blocks Gi coupled ADP receptors.
2. It is a prodrug requires conversion to active form by CYP450.
3. Rapid absorption, high bioavailability
4.Maximal inhibition of platelet inhibition it takes 8-11 days
after starting therapy.
5.Dose-loading 500mg for rapid onset of action. Usual dose
250mgBD
AE- Nausea ,Vomiting, Diarrhea, Neutropenia, Thrombotic
Thrombocytopenia
Uses- Prevention cerebrovascular events, in secondary
prevention of stroke angina
Combination –Aspirin + ticlopidine---angioplasty, coronary
artery stenting 16
Clopidogrel
Less toxic then ticlopedine less incidence of leucopenia,
thrombocytopenia.
Less used than Ticlopidine
MOA, PK profile same as Ticlopidine
Dose 75mg/day
Rest same as Ticlopidine.
Dipyridmole-
• MOA
Inhibition of PDE (phospodiesterase enzyme) and/ or by
blockade of adenosine which act at A2 receptor to stimulate
adenylcyclase thus increase CAMP causing platelet inhibition.
Current recommended use-
Along with Warfarin in primary prophylaxis of thromboemboli in patients
with prosthetic heart valves
Xanthine analogue
Increases deformability of RBCs thus increases microcirculation,
reduce fibrinogen levels, inhibit pl. aggregation.
Uses- CVAs esp.TIA(transient ischemic attacks) ,
Ischemic ulcers of legs
Dose 400mg tds
Pentoxifyllines
Glycoprotein IIB/IIIA receptors antagonists
Platelet surface receptor, receptor for fibrinogen and von
willebrand factor,which anchors platelets to foreign surface and
each other thereby mediating aggregation.
Receptor is activated by TXA2, Collagen, and thrombin to
developbinding sites for its ligands.
Inhibition of binding to this receptor blocks platelet aggregation
induced by the agonist.
Abciximab
Monoclonal antibody cause platelet receptor blockade.
Given IV max. effect seen with in 2hrs, DOA 10-12 hrs.
Use- percutaneous angioplasty for coronary thrombosis
Prevents restenosis, recurrent and death when used in conjugation with aspirin and heparin.
Dose-0.25mg bolus---0.125microgm/kg/min for 12hrs IV
AE-bleeding
Contraindication same as fibrinolytics
Coagulation Phase
Two major pathways
Biosynthesis of these factors are dependent on Vitamin K1 and K2
Most of these factors are proteases
Normally inactive and sequentially activated
Hereditary lack of clotting factors lead to hemophilia -A
Intrinsic pathway
Extrinsic pathway
Clotting factors
23
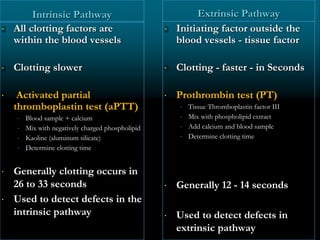
Intrinsic Pathway
ď‚  All clotting factors are
within the blood vessels
ď‚  Clotting slower
ď‚  Activated partial
thromboplastin test (aPTT)
ď‚  Blood sample + calcium
ď‚  Mix with negatively charged phospholipid
ď‚  Kaoline (aluminum silicate)
ď‚  Determine clotting time
ď‚  Generally clotting occurs in
26 to 33 seconds
ď‚  Used to detect defects in the
intrinsic pathway
Extrinsic Pathway
ď‚  Initiating factor outside the
blood vessels - tissue factor
ď‚  Clotting - faster - in Seconds
ď‚  Prothrombin test (PT)
ď‚  Tissue Thromboplastin factor III
ď‚  Mix with phospholipid extract
ď‚  Add calcium and blood sample
ď‚  Determine clotting time
ď‚  Generally 12 - 14 seconds
ď‚  Used to detect defects in
extrinsic pathway
Diagnosis of coagulation defects
Prolonged APTT
No change in PT
• Defective Intrinsic Pathway
No change in APTT
Prolonged PT
• Defective Extrinsic Pathway
Prolonged APTT
Prolonged PT
• Defective in Common pathway
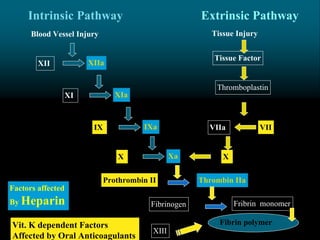
Blood Vessel Injury
IX IXa
XI XIa
X Xa
XII XIIa
Tissue Injury
Tissue Factor
Thromboplastin
VIIa VII
X
Prothrombin II Thrombin IIa
Fibrinogen Fribrin monomer
Fibrin polymer
XIII
Intrinsic Pathway Extrinsic Pathway
Factors affected
By Heparin
Vit. K dependent Factors
Affected by Oral Anticoagulants
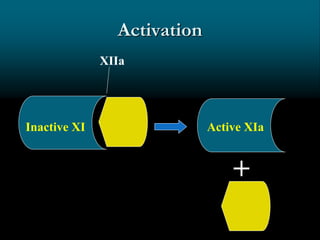
Activation
Inactive XI Active XIa
XIIa
+
ANTICOAGULANTS
ď‚  These are the drugs used to reduce coagulability of blood.
ď‚  Classification
In vitro anticoagulants In vivo anticoagulants
Heparin A) -Heparin
Sodium citrate -Low molecular weight Heparin
Sodium oxalate -Danaparoid
Sodium edetate -Lepirudin
-Heparan sulfate
B) Oral anticoagulants
ď‚  Warfarin sodium
ď‚  Bishydroxycoumarin (dicumarol)
ď‚  Acenocoumarol
ď‚  Phenindione
Chemistry & Occurence
Straight chain mucopolysaccharide,
glycosaminoglycans
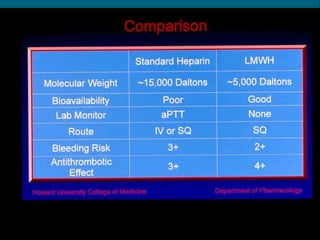
MW 10000-20000. Average=15,000 d (~45monosaccharide chains)
Strongest organic acid in the body.
Heparin is present in all tissues containing mast cells,
richest source are liver, lung (bovine) and intestinal
mucosa (porcine)
LMWH isolated from standard heparin by gel filtration
chromatography or partial depolymerization. (1000-
10000 daltons).
H
e
p
a
r
i
n
MOA
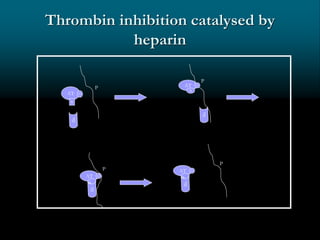
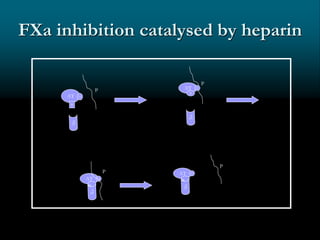
ď‚  Heparin binds to antithrombin III -----complex
 Increases thrombin –AT reaction 1000folds.
ď‚  Heparin induces conformational change in ATIII to expose
its interactive sites.
ď‚  Long heparin molecule provides scaffolding for clotting
factors ( Xa & IIa) aswellas ATIII.
ď‚  At low conc. interferes with intrinsic pathway while at high
common pathway.
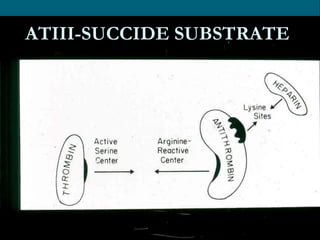
ď‚  ATIII inhibits activated clotting factors of intrinsic and
common pathway including thrombin, Xa, IXa and thus acts
as Succide substrate
ATIII-SUCCIDE SUBSTRATE
Thrombin inhibition catalysed by
heparin
AT
R
H
AT H
AT H
AT H
R
P
P
P
P
R
R
FXa inhibition catalysed by heparin
AT
R
H
AT H
AT H
AT H
R
P
P
P
P
R
R
Anticoagulant Properties of Heparin
1. Inhibits the thrombin-mediated conversion of
fibrinogen to fibrin
2. Inhibits the aggregation of platelets by
thrombin
3. Inhibits activation of fibrin stabilizing enzyme
4. Inhibits activated factors XII, XI, IX, X and II
Pharmacokinetics
ď‚  Not effective orally
ď‚  Sc/ iv administration
ď‚  Onset immediate, peak in 5-10mins
ď‚  Metabolized in liver
ď‚  Excretion through kidney.
Unfractionated Heparin
ď‚  High Dose
ď‚  Treatment of venous/arterial thrombi
ď‚  Requires monitoring
ď‚  IV- 5,000 Units bolus, then 30,000-35,000 units/24
hrs
ď‚  80 Units/kg bolus, then 18 Units/kg/hr to maintain

aPTT in therapeutic range
 therapeutic goal – 2-2.5 times normal control value (-
30 sec)
Low Dose Unfractionated Heparin
ď‚  Surgical Prophylaxis
ď‚  5,000 Units SC 2 hr preop
ď‚  5,000 Units SC every 12 hours
ď‚  Medical Prophylaxis
ď‚  5,000 Units SC every 12 hours
ď‚  No monitoring required
ADVANTAGES OF LMWH
1. Less anti IIa activity than
anti Xa activity
2. Good pk profile
3. More predictable dose
response
4. Can be given by
subcutaneous route
5. No monitoring required,
can be given OPD basis
6. Less anti-platelet effects
7. Longer t1/2’s
8. Decreased hospital stay
9. More favorable benefit –
risk ratio
LMWH
ď‚  1mg/ kg S.C BD for DVT
ď‚  30mg/ Kg S.C. for DVT
prophylaxis of Knee and hip
surgery
ď‚  1mg/ kg S.C BD for DVT
ď‚  30mg/ Kg S.C. for DVT
prophylaxis of Knee and hip
surgery
Adverse effects
ď‚  Allergic and anaphylactic manifestations
ď‚  Bleeding (1-33%)-antidote- Protamine sulphate
ď‚  Heparin induced thromocytopenia. (more than
25%)
ď‚  Alopecia
ď‚  Osteoporosis
ď‚  Hyperkalemia
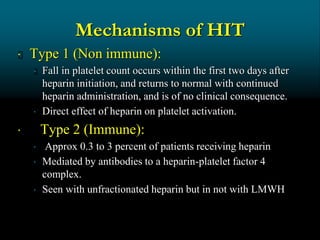
Mechanisms of HIT
ď‚  Type 1 (Non immune):
ď‚  Fall in platelet count occurs within the first two days after
heparin initiation, and returns to normal with continued
heparin administration, and is of no clinical consequence.
ď‚  Direct effect of heparin on platelet activation.
ď‚  Type 2 (Immune):
ď‚  Approx 0.3 to 3 percent of patients receiving heparin
ď‚  Mediated by antibodies to a heparin-platelet factor 4
complex.
ď‚  Seen with unfractionated heparin but in not with LMWH
Warfarin
Warfarin, a coumarin derivative, is the most commonly used
oral anticoagulant (OAC) .
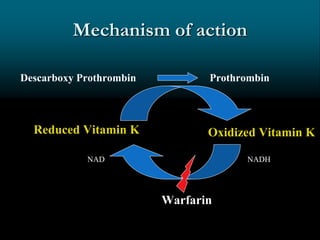
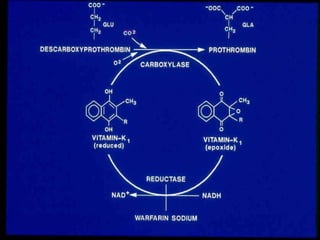
Warfarin is a vitamin K antagonist - Impairs the generation
of active vitamin K, decreasing the amounts of vitamin K
dependent coagulation factors
• (FII, FVII, FIX, FX)
Depending on factors such as age, risk factors, recurrence,
etc., warfarin may be continued for anywhere from 1 month
to lifelong
Oral anticoagulants : warfarin, dicumarol
ď‚  Coumarins - warfarin, dicumarol
ď‚  Isolated from clover leaves
ď‚  Structurally related to vitamin K
ď‚  Inhibits production of active clotting factors
 Absorption rapid –high plasma protein binding binds to
albumin
ď‚  Clearance is slow - 36 hrs
ď‚  Delayed onset 8 - 12 hrs
ď‚  Overdose - reversed by vitamin K infusion
ď‚  Can cross placenta - do not use during late pregnancies
Mechanism of action
Descarboxy Prothrombin Prothrombin
Reduced Vitamin K Oxidized Vitamin K
NADHNAD
Warfarin
Warfarin Monitoring
Warfarin Monitoring
• Why monitor? Need to balance proper
anticoagulation without bleeding risk.
• Monitored with PT, expressed as INR:
INR =
[Patient PT / Mean Normal PT]ISI
• Where ISI = International Sensitivity Index,
assigned by each thromboplastin
manufacturer
INR : International Normalized Ratio.
ď‚  Different thromboplastins vary in sensitivity
ď‚  To give PT values a consistent basis of comparison from
lab to lab, WHO instituted the INR:
ď‚  A uniform value in which the PT is expressed as a
ratio.
ď‚  Many manufacturers aim for an ISI of 1.0.
ď‚  INR is affected by diet (because of the vitamin K
dependent mechanism of action), other medications,
ď‚  Monitored routinely, every 2 to 4 weeks
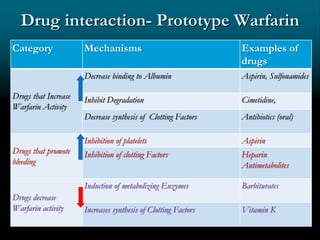
Drug interaction- Prototype Warfarin
Category Mechanisms Examples of
drugs
Drugs that Increase
Warfarin Activity
Decrease binding to Albumin Aspirin, Sulfonamides
Inhibit Degradation Cimetidine,
Decrease synthesis of Clotting Factors Antibiotics (oral)
Drugs that promote
bleeding
Inhibition of platelets Aspirin
Inhibition of clotting Factors Heparin
Antimetabolites
Drugs decrease
Warfarin activity
Induction of metabolizing Enzymes Barbiturates
Increases synthesis of Clotting Factors Vitamin K
New Anticoagulants
Limitations of
traditional
anticoagulants
, both with
Heparin and
Warfarin, have
prompted the
development
of new agents
New Anticoagulants
Parenteral FXa Inhibitors
FXa Inhibitors
Parenteral synthetic pentasaccharide analogs
Fondaparinux (Arixtra®)
• Synthetic and highly selective inhibitor
of FXa
• Acts as cofactor to AT
• Administered by subcutaneous
injection ONCE A DAY
• Absolute bioavailability of 100%
FXa Inhibitors
Parenteral synthetic pentasaccharide analogs
Danaparoid
• LMW mixture of heparinoids
(glycosaminoglycans, GAGs); acts as cofactor
to AT
• Anticoagulation effect is predominantly
mediated by inhibition of FXa
• Also has some anti-IIa effects
• Fast acting, generally predictable dose
response
Direct Thrombin Inhibitors
Lepirudin (Recombinant hirudin)
• Recombinant hirudin, a derivative of
the saliva of the medicinal leech
Hirudo medicinalis
• First direct thrombin inhibitor (DTI)
to be approved by the FDA for
anticoagulation in patients with (HIT)
• Can be monitored with APTT, TT,
Direct Thrombin Inhibitors
Argatroban
• A synthetic anticoagulant for prophylaxis or treatment of
thrombosis in patients with heparin-induced
thrombocytopenia (HIT)
• Active against both free and clot-bound thrombin
• Argatroban is typically monitored by APTT, but other
methods like the chromogenic anti-IIa assay may be more
accurate.
Direct Thrombin Inhibitors
Bivalirudin
• Synthetic polypeptide hirudin analog that
interacts with the thrombin active site to
reversibly inhibit thrombin
• Alternative to heparin
• Administered parenterally
• Short half life
• Monitored by Activated Clotting Time (ACT)
Direct Thrombin Inhibitors
Ximelagatran oral anticoagulant
• Studies have shown similar efficacy
and bleeding risk to warfarin
• Does not need monitoring
• Was not FDA approved: more
studies needed to assess liver
failure risk
USES
OF
ANTICOAGULANTS
USES
OF
ANTICOAGULANTS
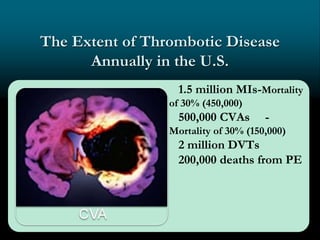
The Extent of Thrombotic Disease
Annually in the U.S.
1.5 million MIs-Mortality
of 30% (450,000)
500,000 CVAs -
Mortality of 30% (150,000)
2 million DVTs
200,000 deaths from PE
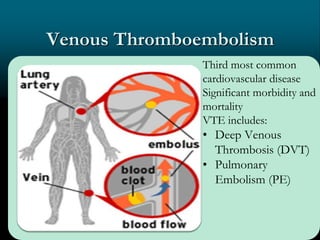
Venous Thromboembolism
Third most common
cardiovascular disease
Significant morbidity and
mortality
VTE includes:
• Deep Venous
Thrombosis (DVT)
• Pulmonary
Embolism (PE)
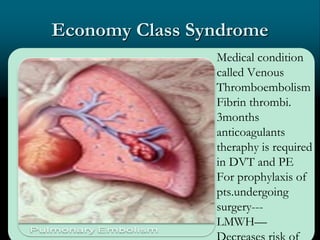
Economy Class Syndrome
Medical condition
called Venous
Thromboembolism
Fibrin thrombi.
3months
anticoagulants
theraphy is required
in DVT and PE
For prophylaxis of
pts.undergoing
surgery---
LMWH—
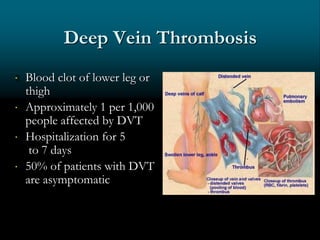
Deep Vein Thrombosis
ď‚  Blood clot of lower leg or
thigh
ď‚  Approximately 1 per 1,000
people affected by DVT
ď‚  Hospitalization for 5
to 7 days
ď‚  50% of patients with DVT
are asymptomatic
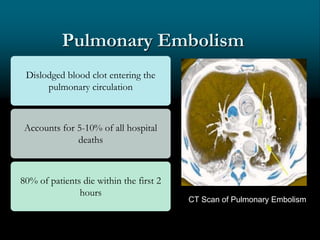
Pulmonary Embolism
Dislodged blood clot entering the
pulmonary circulation
Accounts for 5-10% of all hospital
deaths
80% of patients die within the first 2
hours
CT Scan of Pulmonary Embolism
Deep Vein ThrombosisEmbolusPulmonary Embolism
AMI AND UNSTABLE
ANGINA
Arterial thrombi-platelet thrombi
Use of anticoagulants???
Beneficial in preventing mural thrombi at infarction site
and venous thrombi in leg veins.
Can be given for short periods till the Pt. is ambulatory.
Heparin iv for 2-8 days followed by oral anticoagulant for
3 months.
Short term use in unstable angina.
RHD, AF
Warfarin / low dose aspirin
/ LMWH are effective in
preventing stroke due to
embolism from fibrillating
atria.
Warfarin the most effective.
(3-4week theraphy)
Blood Hypercoagulability
Increased procoagulants
Decrease in inhibitors
Impaired fibrinolysis
Occurs in obstretic conditions, mallignancies, infections.
FIBRINOLYTICS
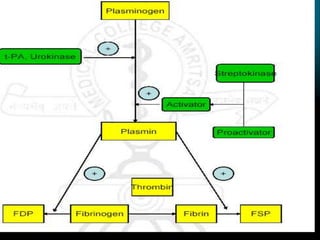
Fibrinolysis
• Enhance degradation of clots
• Activation of endogenous protease
• Plasminogen (inactive form) is converted to Plasmin
(active form)
• Plasmin breaks down fibrin clots
FIBRINOLYTICS
CONVENTIONAL
NONSELECTIVE AGENTS
Fibrin selective agents
FIBRINOLYTICS
• Streptokinase - bacterial product - continuous use - immune reaction
• Urokinase - human tissue derived - no immune response
• Tissue plasminogen activator (tPA) - genetically cloned - no immune
reaction - EXPENSIVE
Inhibitors of fibrinolysis
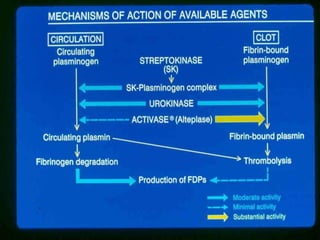
ď‚  Streptokinase is a protein (but not an
enzyme in itself) synthesized by streptococci
that combines with the pro-activator
plasminogen.
ď‚  This enzymatic complex catalyzes the
conversion of inactive plasminogen to active
plasmin
ď‚  Urokinase is a human enzyme synthesized by
the kidney that directly converts plasminogen to
active plasmin.
ď‚  Plasmin formed inside a thrombus by these
activators is protected from plasma antiplasmins,
which allows it to lyse the thrombus from within
ď‚  Plasminogen can also be activated endogenously
by tissue plasminogen activators (t-PAs).
ď‚  Activate plasminogen that is bound to fibrin,
which (in theory) confines fibrinolysis to the
formed thrombus and avoids systemic activation.
ď‚  Human t-PA is manufactured as ALTEPLASE
by means of recombinant DNA technology.
ď‚  RETEPLASE is less expensive than Alteplase.
It lacks the major fibrin-binding domain thus is
less fibrin-specific than Alteplase
ď‚  TENECTEPLASE is a mutant form of t-PA
that has a longer half-life, and it can be given as
an intravenous bolus. Tenecteplase is slightly
more fibrin-specific than Alteplase
DOSES
Streptokinase
• Dose:250000 U loading dose followed by 100000 U every hr for
24 -72 hrs
Urokinase
• Loading dose of 300000 U followed by 300000 U/hr for 12 hrs
Alteplase
(t-PA)
• 60mg iv over 1 hr followed by 40mg iv at a rate of 20mg/ hr
Contraindications to Antithrombotic
Therapy
General risk factors
• Pre-existing coagulation or platelet defect, thrombocytopenia, or other
bleeding abnormality
• Inaccessible ulcerative lesion(e.g., gastrointestinal tract lesion)
• Central nervous system lesion (e.g., caused by stroke, surgery, trauma)
• Malignant hypertension
• Advanced retinopathy
• Old age (relative)
• Aspirin or other antiplatelet drugs
• Neoplastic disease
Contraindications to Antithrombotic
Therapy
Specific to thrombolytic agents
• Recent thoracic, abdominal, or central
nervous system surgery
• Recent cerebrovascular accident, trauma,
or neoplasm
• Bleeding ulcer
• Anticipated invasive procedures (arterial
punctures, biopsies, central lines)
• Concurrent hemostatic dysfunction
Indications
• AMI
• Multiple pulmonary emboli.
• Pulmonary embolism with
hemodynamic instability
• Central DVT
• Pheripheral vascular disease
Drug preparations : to stop bleeding
Fibrinolytic Inhibitors: Aminocaproic
Acid
ď‚  Similar to the amino acid lysine, is a synthetic
inhibitor of fibrinolysis
ď‚  Competitively inhibits plasminogen activation
ď‚  Oral dosage of EACA is 6 g four times a day
ď‚  Tranexamic acid is an analog of aminocaproic
acid and has the same properties. It is
administered orally with a 15 mg/kg loading dose
followed by 30 mg/kg every 6 hours
USES
ď‚  Adjunctive therapy in hemophilia
ď‚  Bleeding from fibrinolytic therapy
ď‚  Prophylaxis for re-bleeding from intracranial aneurysms.
ď‚  Postsurgical gastrointestinal bleeding ,post
prostatectomy bleeding ,bladder hemorrhage secondary
to radiation and drug-induced cystitis.
ď‚  Adverse effects
ď‚  Intravascular thrombosis from inhibition of
plasminogen activator
ď‚  Hypotension, myopathy, abdominal discomfort,
diarrhea, and nasal stuffiness
Drug preparations: clotting deficiencies
Vitamin K
• Oral : 5 mg tablets
Plasma fractions - for hemophilia
• Antihemophilic factor ( VIII, AHF)
• Parenteral
Factor IX complex
• Parenteral : in vials