Diabetes mellitus
• DM is characterized by elevated blood
sugar levels due to absolute or relative
lack of insulin.
• Type 1 diabetes - β-cell failure at outset
– Insulin dependent
• Type 2 diabetes - Gradual β-cell
deterioration
– Early stages: Diet and Oral agents
– Late-stage: Insulin therapy
Diabetes mellitus
• Glycosylated hemoglobin Hb-A1c :
It is used to monitor the plasma glucose
concentration over prolonged periods of
time (4-6 weeks).
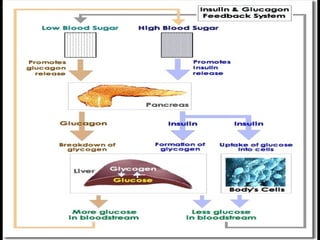
• Insulin secretion is promoted by ↑ blood
glucose levels, amino acids, GI
hormones and by β-2 agonist.
Insulin
• Proinsulin is converted to insulin and C
peptide.
• Insulin is referred as the storage hormone
as it promotes anabolism and inhibits
catabolism of carbohydrates, fatty acids
and protein.
• In the absence of insulin, most tissues
cannot use glucose and fats/proteins are
broken down to provide energy.
Insulin
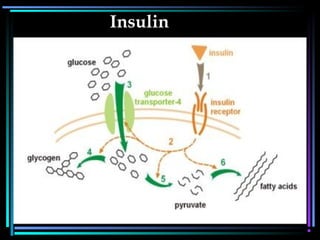
Mechanism of action :
• Insulin binds to insulin receptors on the
plasma membrane and activates
tyrosine kinase – primarily in adipose
tissue, liver and skeletal muscle.
• The Nerves, RBC’s, Kidney, and Lens of
the eye do not require insulin for
glucose transport.
Insulin
Liver :
• Insulin increase the storage of glucose as
glycogen in the liver.
• It inserts the GLUT-2 glucose transport
molecule in the cell membrane.
• It inhibits gluconeogenesis – thus
significantly ↓ glucose output by the liver.
• It decrease the protein catabolism.
Insulin
Muscle :
• Insulin stimulates the glycogen
synthesis and protein synthesis.
• Glucose transport into the cells is
facilitated by GLUT-4 into the cell
membrane.
• It inhibits the protein catabolism.
Insulin
Adipose tissue :
• Insulin facilitates the storage of
triglyceride by activating plasma
lipoprotein lipase and inhibiting
intracellular lipolysis.
• It increase the glucose uptake by
GLUT-4 insertion into the cell
membrane.
Insulin
Insulin
• Insulin is a 51 AA peptide
• Not active orally.
• Insulin is inactivated by insulinase found
mainly in liver and kidney.
• Dose reduced in renal insufficiency
• Sources of Insulin :
– Beef pancreas / Pork pancreas
– Human insulin: recombinant DNA origin
Insulin
Human Insulin :
• Do not contain measurable amounts of
proinsulin or contaminants.
• Diminished antibody
• Less allergic reactions
• Less lipodystrophy
• Preferred in gestational diabetes
Insulin
Insulin preparations :
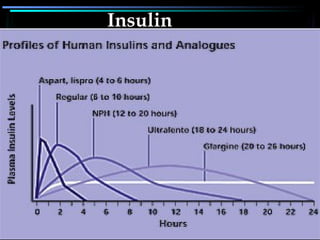
• Rapid acting insulin :
Lispro, Aspart and Glulisine
• Short acting insulin:
Regular (crystalline)
• Intermediate acting insulin:
NPH (isophane) and Lente (insulin zinc)
• Long acting insulin:
Ultralente, Detimir and Glargine
Insulin Duration Route Features
Lispro 3 – 5 hrs I.V or S.C Onset within 15
minutes
Regular
(crystalline)
7 – 10 hrs I.V or S.C common
NPH
(Neutral protamine
hagedorn)
16 – 20 hrs S.C NPH can mix
with regular
Ultralente 24 – 30 hrs S.C Basal level
Insulin
Insulin
Insulin
Adverse effects of Insulin :
• Hypoglycemia
• Allergic reactions
• Lipodystrophy
• Others includes
– Seizures
– Coma
Oral Anti-diabetic drugs
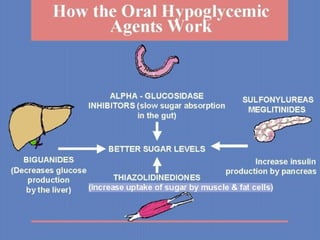
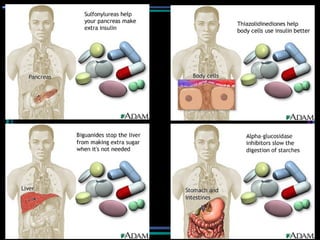
Mechanisms to reduce blood sugar :
• Stimulation of pancreatic insulin release –
Sulfonylureas, Meglitinide
• Reduce the bio-synthesis of glucose in
liver – Biguanides (Metformin)
• Increase the sensitivity of target cells to
insulin -- Thiazolidinediones
• Retard the absorption of sugars from the
GI tract – Acarbose, Miglitol
Oral Anti-diabetic drugs
Sulfonylureas :
• First generation : Acetohexamide,
Chlorpropamide, Tolbutamide,
Tolazamide
• Second generation : Glipizide, Glyburide
– more potent, more efficacious and fewer
adverse effects.
• Third generation : Glimiperide
Sulfonylureas
Sulfonylureas
Dose
(mg)
Duration
(h)
First Generation
Tolbutamide (Orinase) 1000-1500 6-8
Chlorpropamide (Diabinese) 250-375 24-60
Tolazamide (Tolinase) 250-375 12-24
Second generation
Glipizide (Glucotrol) 10 10-24
Glyburide (Micronase)
(Glibenclamide)
Third generation
5 16-24
Glimepiride (Amaryl) 1-2 24
Oral Anti-diabetic drugs
Sulfonylureas : Adverse effects :
• Hypoglycemia
• Cholestatic jaundice
• Weight gain
• Cross placenta – fetal hypoglycemia.
• Chlorpropamide : It can cause water
retention by ↑ release of ADH (SIADH)
• Disulfiram-like reaction with alcohol.
Oral Anti-diabetic drugs
Repaglinide, Nateglinide :
• More rapidly acting insulin enhancers
and shorter duration than sulfonylurea.
• Hypoglycemia is the common adverse
effect.
• Less weight gain
Oral Anti-diabetic drugs
Repaglinide, Nateglinide
• The drug has minimal renal excretion
thus useful in patients with DM and
impaired renal function. 
• It is designed to be taken with each meal
to stimulate insulin release with meal.
If a meal is skipped, so is the repaglinide.
Oral Anti-diabetic drugs
Biguanides (Metformin):
• Inhibits gluconeogenesis.
• Does not promote insulin secretion.
• It increase the sensitivity of liver and
muscle to insulin.
• It causes modest weight loss.
Oral Anti-diabetic drugs
Metformin (Glucophage) :
• It does not cause hypoglycemia.
• It produces a significant ↓ TG and LDL,
and ↑HDL.
• There is a serious concern about lactic
acidosis especially in patients with kidney
disease.
Oral Anti-diabetic drugs
Thiazolidinediones
• Enhance glucose and lipid metabolism
through action on Peroxisome Proliferator
Activated Receptor (PPAR–γ)
• Enhance sensitivity to insulin in muscle
and fat by increasing the GLUT 4 glucose
transporters.
• E.g. ; Pioglitazone Actos,
Rosiglitazone Avandia
Anti-diabetic drugs
Thiazolidinediones :
• Beneficial effects on serum lipid; ↓TG
and ↑HDL.
• Troglitazone is associated with
hepatitis.
• Edema.
Anti-diabetic drugs
Alpha-Glucosidase Inhibitors:
• It inhibits -glucosidase which converts
dietary starch and complex
carbohydrates into simple sugars
• It reduces absorption of glucose after
meals.
• The main side effects includes
flatulence and diarrhea.
• AcarboseAcarbose (Glucobay)(Glucobay) , Miglitol, Miglitol (Glyset)(Glyset)
Anti-diabetic drugs
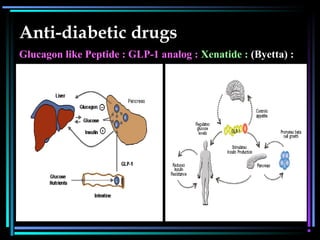
Glucagon like Peptide : GLP-1 analog :
Xenatide : (Byetta) :
• GLP is an incretin released from the small
intestine which increase the glucose
dependent insulin secretion.
• Xenatide suppress glucagon release and
reduce appetite
• It is administered by SC injection.
Anti-diabetic drugs
Glucagon like Peptide : GLP-1 analog : Xenatide : (Byetta) :
Anti-diabetic drugs
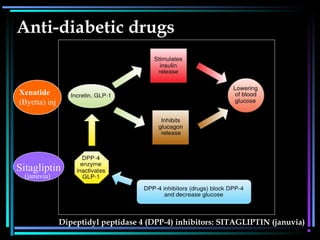
Dipeptidyl peptidase 4 (DPP-4) inhibitors: SITAGLIPTIN (januvia)
Xenatide
(Byetta) inj
Sitagliptin
(januvia)
Anti-diabetic drugs
• Sitagliptin (Januvia) is an oral anti-
diabetic drug.
• It inhibit the dipeptidyl peptidase 4 (DPP-
4), an enzyme which inactivates the
incretins GLP-1 and GIP, that are released
in response to a meal.
• It potentiates the secretion of insulin and
suppress the release of glucagon by the
pancreas.
Endocrine pancreas
Glucagon :
• It has positive inotropic action and
chronotropic action on the heart.
• It acts by stimulation of glucagon
receptors and not through beta 1
receptors.
• This is the basis for using glucagon in
beta blocker overdose.