Diabetes Mellitus
Definition:-
Heterogeneous group of common metabolic disorder
characterized by an elevation of blood glucose caused by a
relative or absolute deficiency of Insulin
 Diabetes= more urine+ mellitus= sugar
3rd leading cause of death & 2nd leading cause of blindness
and renal failure
Classical symptoms:-
Polyuria, polydipsia,Polyphagia
Cause:-
1. Insulin deficiency (↓circulating level of insulin)
2. Insulin resistance(↓ response of target tissue to insulin)
Types:- Type-1 diabetes (IDDM/juvenile onset
Type-2 diabetes (NIDDM/maturity onset
Type-3 diabetes (other types)
Type-4 diabetes (Gestational )
Cause due to absolute lack of insulin so, regular Injection of
Insulin are needed
Juvenile-onset DM- commonly develops below 20 years of age &
persist through out the life
Approximately 10% of diabetics suffer from type-1
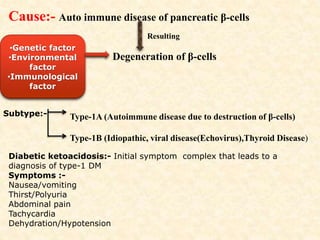
Cause:- Auto immune disease of pancreatic β-cells
Resulting
Degeneration of β-cells
•Genetic factor
•Environmental
factor
•Immunological
factor
Subtype:- Type-1A (Autoimmune disease due to destruction of β-cells)
Type-1B (Idiopathic, viral disease(Echovirus),Thyroid Disease)
Diabetic ketoacidosis:- Initial symptom complex that leads to a
diagnosis of type-1 DM
Symptoms :-
Nausea/vomiting
Thirst/Polyuria
Abdominal pain
Tachycardia
Dehydration/Hypotension
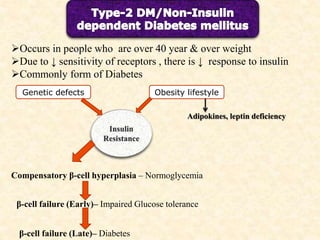
Occurs in people who are over 40 year & over weight
Due to ↓ sensitivity of receptors , there is ↓ response to insulin
Commonly form of Diabetes
Genetic defects Obesity lifestyle
Adipokines, leptin deficiency
Compensatory β-cell hyperplasia – Normoglycemia
β-cell failure (Early)– Impaired Glucose tolerance
β-cell failure (Late)– Diabetes
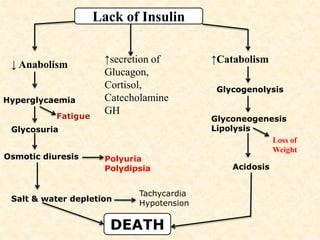
Lack of Insulin
↓ Anabolism ↑Catabolism↑secretion of
Glucagon,
Cortisol,
Catecholamine
GH
Hyperglycaemia
Glycosuria
Osmotic diuresis
Fatigue
Polyuria
Polydipsia
Salt & water depletion
Tachycardia
Hypotension
Glycogenolysis
Glyconeogenesis
Lipolysis
Loss of
Weight
Acidosis
DEATH
Insulin
 Insulin was discovered by Banting & Best.
Insulin analogs – genetic engineering by changing AA
sequence or by adding a molecule
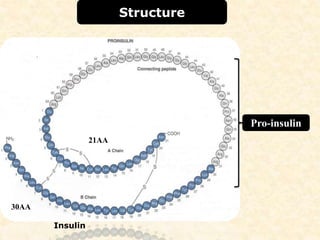
Structure:-
Polypeptide consisting of an A and B chain of 21 and 30
amino acid
Molecular weight 5800 KD
Two chains are linked by a pair of S-S bonds
An intrachain S-S bond connects 6th and 11th amino acid
within A chain
Forms a dimer with 2 Zn ions
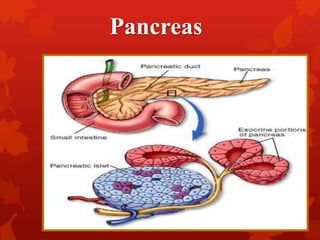
 A triangular gland, which has both exocrine and endocrine
functions
 Acinar cells produce an enzyme-rich juice used for digestion
(exocrine product)
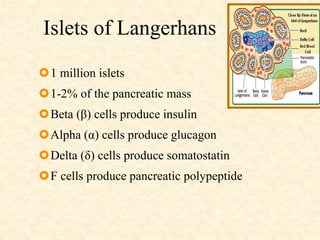
 Pancreatic islets (islets of Langerhans) produce hormones
involved in regulating blood glucose level.
Pancreas
Islets of Langerhans
1 million islets
1-2% of the pancreatic mass
Beta (β) cells produce insulin
Alpha (α) cells produce glucagon
Delta (δ) cells produce somatostatin
F cells produce pancreatic polypeptide
Structure
Pro-insulin
21AA
30AA
Insulin
Synthesis of insulin
 Insulin gene encodes a large
precursor of insulin (preproinsulin)
 During translation, the signal
peptide is cleaved (proinsulin)
 During packaging in granules by
Golgi, proinsulin is cleaved into
insulin and C peptide
PK
Degraded within the liver and kidneys
 80% metabolized in the liver
 Half-life of about 5 minutes
 Degraded by hepatic glutathione insulin
dehydrogenase
 Enzyme disrupts S-S bonds
Regulation of Insulin
secretion
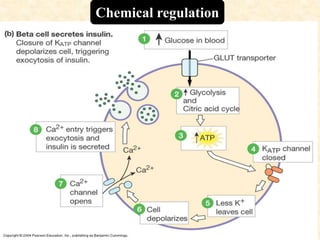
It is mainly regulated by feed back control
Three types of regulation
 Chemical regulation
 Hormonal regulation
 Neural regulation
Chemical regulation
Stimulator of insulin secretion
 Gastro Inhibitory Peptide (GIP)
 Vasoactive Intestinal Peptide (VIP)
 Cholecystokinin (CCK)
 Secretin, Gastrin, Glucagon
 Epinephrine (β-receptor)
Inhibitor of insulin secretion
 Somatostatin
 Epinephrine (α-receptor)
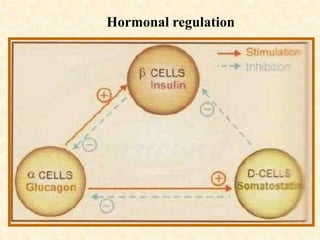
Hormonal regulation
Hormonal regulation
Neural regulation
Islet is supplied by both parasympathetic
and sympathetic nerves.
It contain both α and β adrenergic receptor.
Primary central site of regulation insulin
secretion is hypothalamus.
Ventrolateral nuclei, ventromedial nuclei.
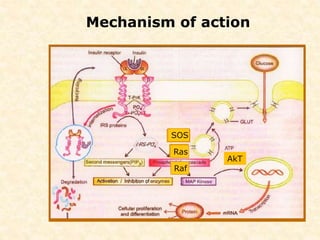
Mechanism of action
AkT
Shc
Grb2SOS
Ras
Raf
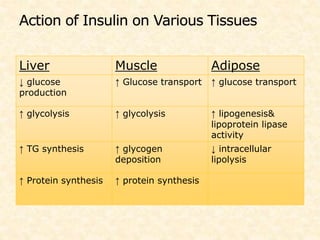
Liver Muscle Adipose
↓ glucose
production
↑ Glucose transport ↑ glucose transport
↑ glycolysis ↑ glycolysis ↑ lipogenesis&
lipoprotein lipase
activity
↑ TG synthesis ↑ glycogen
deposition
↓ intracellular
lipolysis
↑ Protein synthesis ↑ protein synthesis
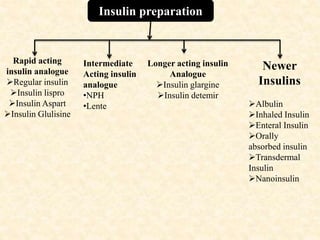
Insulin preparation
Rapid acting
insulin analogue
Regular insulin
Insulin lispro
Insulin Aspart
Insulin Glulisine
Intermediate
Acting insulin
analogue
•NPH
•Lente
Longer acting insulin
Analogue
Insulin glargine
Insulin detemir
Newer
Insulins
Albulin
Inhaled Insulin
Enteral Insulin
Orally
absorbed insulin
Transdermal
Insulin
Nanoinsulin
Rapid -Acting Analogues
Rapid onset and shorter duration of action.
Administered immediately before meals because peak of onset
corresponds more closely with the post prandial glucose peak
This avoids post prandial hypoglycaemia that occurs due to long
duration of action of soluble insulin .
The shorter duration of action of these analogues leads to lower
incidence of hypoglycaemia.
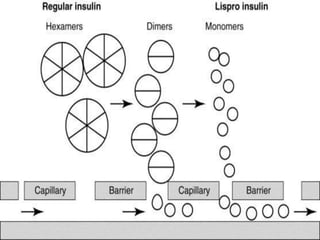
Come as a hexamer in solution
Upon Sc application –delay in action due to dissociation & resorption
 Peak plasma conc. Are reached 45-120 min after the application
 Route:- Sc,im,iv
 Preparation :- Insulin lispro & insulin aspart
Regular Human
Insulin
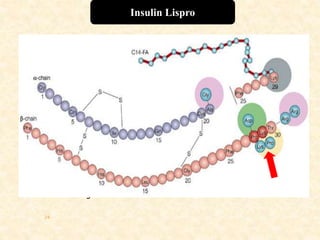
 First recommended DNA analogue,approved by FDA in 1996
 Modification – inversion of proline at position B28 with lysine at B29
Advantage –
1.Block the formation of insulin dimer and hexamer thus allows large
numbers of monomeric insulin to be available for postprandial
injection
2.More flexibility and convenience
3.Better reduction in PPG and HbA1c
4.Less chances of hypoglycemia
5.Better PK and PD properties irrespective of site of injection
6. Less immunogenic
24
Insulin Lispro
Insulin aspart
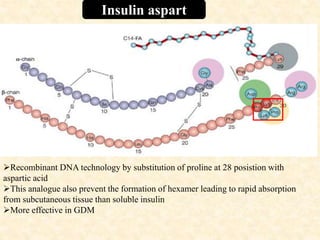
Recombinant DNA technology by substitution of proline at 28 posistion with
aspartic acid
This analogue also prevent the formation of hexamer leading to rapid absorption
from subcutaneous tissue than soluble insulin
More effective in GDM
Insulin Glulisine
Substitution Two
B3- aspargine lysine
B29- lysine glutamine
It has rapid onset and short duration of action than regular human
insulin
Antiapoptotic activity:- it counteracts autoimmune and lipotoxicity
induced beta-cell destruction
. It has advantage over regular human insulin by causing less chance
of hypoglycemia by administering just before meals
Tumerogenic potential:- as various studies have shown that by
substitution at position B28-30 causes increased binding to IGF-1
receptor and increases mitogenic activity
 Intermediate acting insulin
Insulin complex with protamine and Zn.dissociate slowly on S.C.
administration
Onset of action is delayed and duration of action is 10-20 hrs
Cloudy solution
Given once or twice daily
Both of them associate with some problems
To overcome problems two long acting insulin analogue insulin
glargine and insulin detemir developed on two approach
1.Insulin Glargine:-
First long acting basal human insulin.created by modyfying 3 aminoacid with the
aim with increase DOC and no pronounced peak activity
Substitution of asparagine residue with a glycine at position 21 of the A chain –
stabilize the hexamer
Elongating B chain at the C terminus by addition of 2 arginine residues
Insulin glargine is a clear solution with a Ph of 4.0 which stabilizes the insulin
hexamer.when injected into the neural pH of the subcutaneous space,aggregation
occur,resulting in prolonged absorption from the injection site
Due to its acidic Ph insulin glargine cannt be mixed with short acting insulin
preparation that are formulated ar neutral pH
At a more neutral pH of the tissue,micro precipitstion take place,which delays
resorption.Resorption is also additionally delayed with a small amont of Zn. Added
Glargine has the same affinity for insulin receptor as human insulin,after SC.
Application glargine reaches its maximum activity after 4-5 hrs ,which then remain
even without pronounced peaks
Pt receiving glargine had significantly less nocturnal hypoglycemia less
symptomatic hypoglycemia and less severe hypoglycemia(with blood sugar less than
2mmol/l)
Important benefits of glargine includes :-
•Because of longer duration of action that is 24 hrs, it can be administered once a day.
•Treatment with glargine is more flexible since it can be given at any time of day but
should be administered at the same time each day
•Unlike traditional insulin preparations that are absorbed more rapidly fropm abdomen
than the arm or leg, the site of administration does not influence the time action profile
of glargine.
•No higher risk of early worsening of diabetic retinopathy compared with NPH
•Treat to target study compared glargine with NPH where Less hypoglycaemic episodes
compared to NPH
•It has been demonstrated that s.c absorption of glargine is not affected by exercise
Disadvantages:-
Expensive
To maintain solubility, the formulation is unusually acidic so Cannot be mixed with
regular insulin and hence multiple injections are required
Cannot be used in children less than 6 years of age
Not yet approved in pregnancy category C by FDA
Glagine binds with a slightly greater affinity to IGF-1 receptors as compared to
human insulin which may increase chances of malignancy Mitogenic effect
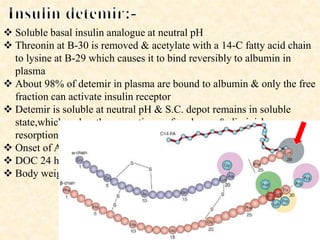
 Soluble basal insulin analogue at neutral pH
 Threonin at B-30 is removed & acetylate with a 14-C fatty acid chain
to lysine at B-29 which causes it to bind reversibly to albumin in
plasma
 About 98% of detemir in plasma are bound to albumin & only the free
fraction can activate insulin receptor
 Detemir is soluble at neutral pH & S.C. depot remains in soluble
state,which makes the resorption surface larger & diminishes
resorption variability
 Onset of Action-1-2 hrs
 DOC 24 hrs
 Body weight decrease
1.Albulin:-
Newest insulin analogues.
It is single chain analogue produced in yeast or mammalian cell
Potent longer acting
2.Inhaled Insulin:- Exubera
1st inhalational drug faster onset of action even faster than IV route
BA –just 10%
DOA:- 5-10 hrs
So high dose of insulin have to be given about 8 times
Major problems:-
Loss of drug with inhaler and mouth during inhalator
Variation in absorption due to age related differences,respiratory tract inflammation &
smoking
Mild to moderate cough
Shortness of breath
Sore throat
Dry mouth
Other Newer Insulins
Enteral insulin:- uses carrier to enable insulin resorption through
membrane
Orally absorbed insulin:- (Oralin ):-
Aerosol containing insulin for buccal absorption,using an applicator
similar to those used for asthma medications
Transdermal insulin:-
The electronic adhesion is first applied to the skin vaporizing superficial
dermal cells and forming micropores for insulin to pass through and then
the insulin patch is applied
Artificial β-cell prototype:-
It is closed loop device consisting of implantable peritoneal insulin pump
and glucose sensor implanted in superior venacava
Nanoinsulin:-
Arsenic destroys insulin molecule so diabetics living in areas with
arsenic contamination of ground water suffers arsenic poisoning &
unsucessful diabetic treatment.
To overcome this problem insulin is coated by polymer nanoparticles
called nanoinsulin
Anti diabetic drugs