Dr. Ankita Bist
Assistant Professor
Department of Pharmacology
 Normally, testes are responsible for male sexual characters
 Testes Functions:
• Production of Androgenic hormones
• Spermatogenesis occurring within the seminiferous tubules
 Androgens are the substances which cause development
of secondary sex characters in the castrated male.
Natural Androgens:
 From Testes:
• Testosterone
• Dihydrotestosterone (by 5 α-reductase)
• Androsterone – metabolite of testosterone
 From Adrenal cortex: (weak androgens)
• Dehydroepiandrosterone
• Androstenedione
 Females : 0.25 – 0.5 mg/day (ovary + adrenals)
 Synthetic androgens:
 Methyltestosterone, Fluoxymesterone–17-alkyl substituted
derivatives
 Orally effective: Testosterone undecanoate and Mesterolone
 Lipid soluble esters: Propionate, cypionate, enanthate salts etc.
Produced from cholesterol, primarily by Leydig cells in testes.
Secreted at adult levels during 1st trimester, during neonatal
life, continually after puberty.
Converted by 5 α-reductase to the more potent, 5α-dihydrotestosterone
(DHT), which is responsible for many of the responses to testosterone in
the urogenital tract (e.g. prostate gland hyperplasia)
Binds to and activates androgen receptors (AR)
Androgen receptors are present in many tissues including
reproductive tissue, skeletal muscle, brain, kidney etc.
Testosterone
17-alkyl substitution
Methyltestosterone
Fluoxymesterone
• All androgens contain a Testosterone structures
•Testosterone has 19-carbons and in general its a steroidal structure
DIhydrotestosterone
5 –α reductase
•Testosterone secretion - Leydig`s cell of testes
• Pulsatile LH – Pituitary
• FSH – only Spermatogenesis
• High testosterone – inhibits LH (atrophy)
• Oestrogen – feedback inhibition
• Inhibin – FSH inhibition
• Plasma level of Testosterone: 0.3 to 1 mcg/dl (male) 20 to 60 ng/dl
(female)
Androgenic Effects
 Foetus: promotes development of male reproductive tract (sex
differentiation).
 During puberty, testosterone promotes development of :
• primary sexual characteristics (e.g. enlargement of penis, scrotum and
testes)
• secondary sexual characteristics (e.g. male body shape, axillary/pubic
hair, deeper pitch of voice, thickening of skin – greasy, loss of
subcutaneous fat)
 Adulthood: Male pattern baldness, BHP, Prostatic cancer.
Testes: Normal spermatogenesis and maturation of sperm
• Moderately high dose : testicular atrophy by inhibiting Gn secretion.
• Higher doses: direct sustaining effect and less marked atrophy
Skeleton and muscles growthmuscle
building, estrogen from testosterone leads
to fusion of epiphysis and mineralization
Positive nitrogen, minerals and water balance
– increase in weight, edema
Increase in appetite
Acceleration of erythropoiesis
Androgen receptor:
Testosterone is converted to more active dihydrotestosterone by 5 –α
reductase. It has 2 isoforms:
•1 is present in genital skin and urogenital tract
•2 has wider distribution and is less sensitive to finestride.
 Both, testosterone and DH testosterone – act via Androgen
receptors (AR) – nuclear receptor super family
 Ligand binding and DNA binding domains
 Mutations in AR: Incomplete sexual development.
• Absorption: Inactive orally, undergoes high first pass metabolism.
Therefore IM injections or synthetic, preparations are used
• Transport: highly protein bound (98%) in plasma to albumin & sex
hormone binding globulin (SHBG)
• Metabolism:
– by liver enzymes : converted to androsterone & etiocholanolone
– excretion by urine after conjugation
– small quantity of oestrogen also produced from testosterone,
by aromatization of A ring.
– Plasma t1/2 10-20 mins
 Females: Virilization, menstrual irregularities may occur in women
receiving relatively high doses for prolonged periods, such as for
estrogen-dependent mammary carcinoma.
 Acne
 Cholestatic Jaundice: may be produced by steroids possessing a 17-
alkyl substituted group
 Priapism (sustained erection)
 Precocious puberty and stunting stature
 Oligozoospermia or testicular atrophy
 Oedema--via promotion of salt and water retention
 Hepatic carcinoma
 Gynaecomastia
1. Androgen replacement therapy (ART)
Primary Androgen deficiency: underlying testicular disorders (high LH, but
low testosterone levels), courses of 4-6 months at a time given.
Secondary Androgen deficiency: hypothalamic-pituitary disorders
(low LH and low testosterone levels)
Mimic the normal testosterone concentration as closely as possible
(serum concentration monitoring)
If untreated, does not shorten life expectancy, but is associated with
significant morbidity (ambiguous genitalia, delayed puberty & infertility)
The aim is to restore tissue androgen exposure by using the natural
androgen testosterone, rather than synthetic androgens, because they are
safe, effective and easy to monitor.
2. Hypopituitarism: Monitoring at anticipated time of puberty, as
hypogonadism is one of the factor
3. AIDS related muscle wasting
4. Hereditary angioneurotic edema (methyltestosterone)
5. Ageing
Misuse: involves prescription with no acceptable medical indication.
Examples of misuse include:
 male infertility
 male sexual dysfunction
Contraindication: CA prostate, male breast, liver kidney and during
pregnancy (virilization of female foetus)
• Synthetic androgens – higher anabolic but lower androgenic
activity (1: 3 ratio) – decreased virilizing effect
• Examples:
Nandrolone, Stanazolol, Oxymetholone, Methandione
• Similar anabolic effect, same receptors and same androgenic
effects
• Side effects and CI similar to testosterone.
1. Catabolic states: Acute illness, severe trauma, major surgery.
These may produce transient response over short periods, but
long term response is debatable.
2. Renal insufficiency
3. Osteoporosis: better drugs available
4. Suboptimal growth in boys
5. Anaemia: haemolytic and malignancy associated : better drugs
available
6. Performance enhancement as in athletes but illegal.
• Superactive GnRH agonists
• Danazol
• Cyproterone acetate
• Flutamide
• Finasteride, Bicalutamide
Ethisterone derivative effective orally
Weak androgenic, anabolic, progestational & glucocorticoid action
Also Labeled as impeded/attenuated androgen:
 Causes suppression of Gn secretion from Pituitary – FSH & LH release
in both sexes decrease – inhibition of testicular/ovarian function directly by
inhibition of steroidogenic hormones.
• Uses:
– Endometriosis : 3-6 months course
– Menorrhagia
– Fibrocystic breast disease
– Hereditary angioneurotic oedema
– Gynecomastia, Infertility
Direct antiantiandrogenic action
Progesterone like activity – inhibits LH causing antiandrogenic action
Competes with dihydroteststerone for intracellular receptor
Uses:
Precocious puberty in Boys
Virilization in women
Limited use
Non-steroidal and no other hormonal activity
Active metabolite “2-hydroxyflutamide” that competitively blocks
Androgen action on accessory sex organs as well as Pituitary.
Increased LH secretion by blocking feedback inhibition
Plasma testosterone level may increase that partially overcomes the direct
antiandrogenic effect, this limits monotherapy.
Uses: Cancer of prostate along with GnRH agonist, Female hirusitism
ADRs: Hepatotoxic potential, Gynaecomastia and breast tenderness.
Dose: 250 mg tds.
BICALUTAMIDE: more potent, longer acting (OD), less hepatotoxic
MOA: Competitive inhibitor of 5 α-reductase
Selectively inhibits 5 α-reductase type-2 isoenzyme
Uses:
 Benign prostatic hypertrophy – decrease in prostate volume,
improved urinary flow, reversion of disease progression
Withdrawal results in regrowth – prolonged therapy needed,
overcomes the static component of obstruction. (alpha 1 blockers
needed for dynamic component)
 Male pattern baldness
Pharmacokinetics: effective orally, metabolized in liver (t1/2 – 4-6 hrs)
Side effects: loss of libido, impotence, decreased ejaculation
Doses: 5 mg OD (BHP) or 1 mg OD in baldness
Dutesteride: Competitive inhibitor of both 5 α-reductases, approved for
both BPH and Baldness.
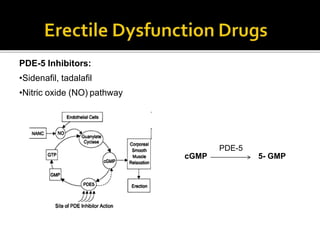
PDE-5 Inhibitors:
•Sidenafil, tadalafil
•Nitric oxide (NO) pathway
cGMP 5- GMP
PDE-5
Absorbed orally and half-life is 4 Hrs
Inhibits PDE5 in the corpus cavernosa
Potentiate nitrate’s hypotension activity
renal & hepatic disease increases its level
Drug interactions
•Ketoconazole, erythromycin, Verapamil increases its level – due
to CYP3A4 inhibition
•Fall in BP and precipitation of MI especially in patient with Nitrates
for angina
Side effects: headache, flushing, dyspepsia, myalgia, loose
motion.
Colour vision impairement and Norarteretic ischaemic optic
neuropathy (NAION) (PDE6)
Other Uses: Pulmonary hypertension
1. Testosterone – Pharmacological action, MOA,
Pharmacokinetics, Uses and its preparations
2. Anabolic steroids and uses
3. Antiandrogens
4. PDE – 5 inhibitors, MOA and Adverse effects
Androgens, anabolic steroids  and antiandrogens