Facts about amputation
Factsabout amputation
90% of all amputation are lower limb
77% are Males
50% between 21 – 65 years old
Currently number one cause is vascular
50% of vascular amputation are caused by
diabetes
80% of diabetic amputations are over 50 years
Majority of diabetic amputations are preventable
Care during amputation
Careduring amputation
To achieve a non-sensitive residual limb
To achieve weight bearing capabilities
Treatment of the distal bony end
Appropriate treatment the blood vessels
Appropriate treatment of the nerves
Appropriate suture lines
Appropriate location of scars
Amputation through themidsection of the
metatarsals. It is usually indicated for
gangrene and infections. Shoe
modifications and inserts will be required.
Weight bearing problems may surface, and
will need follow-up over time
Transmetatarsal
7.
Amputation removing theforefoot and
midfoot, leaving the talus and calcaneus.
Often a prosthesis or AFO is needed
Chopart
8.
Ankle disarticulation withattachment of
heel pad to distal end of tibia. Gait
problems minimized with prosthesis. The
prosthesis is designed to balance and relieve
weight bearing
Symes
9.
Below the kneeamputation. Amputation
through the tibia and fibula with knee left
intact. Careful consideration to weight
bearing is given.
Transtibia
Psychological / motivationaleffects
Residual limb (stump) condition
Change of center of mass support
Change from physiological weight transfer
surfaces to non-physiological ones
Loss of feedback and physiological control
loops
Loss of joint stabilization
General side effect of amputation
16.
Loss ofactive joint motion control
Need to re-learn the process of standing
and walking
Need to switch from subconscious,
automated control and motion patterns
to highly conscious and completely new
patterns of stability-control (which means
safety!) and motion.
General side effect Cont…
17.
Parameters fora healthy good stump is
considered to have the following:
A well healed stump
Of a reasonable lever arm length ( the
longer the better)
Of healthy skin condition ( minimum scarring,
Of good general soft tissue coverage
Free of soft tissue rolls or excessive tissue
Of good distal soft tissue coverage
Of good load acceptance (surface pressure
tolerance)
Good stump condition
18.
Good stump Cont….
Of good blood circulation
Free of ROM-limitations (no contractures)
Free of neuroma
Free of bone spurs
Free of phantom pain
Well capable of sensory feedback
Well under amputee’s conscious control
19.
Loss of alimb produces a permanent
disability that can impact a patient's self-
image, self-care, and mobility (movement).
Rehabilitation of the patient with an
amputation begins after surgery during the
acute treatment phase. As the patient's
condition improves, a more extensive
rehabilitation program is often begun.
Rehabilitation after
amputation
20.
The success ofrehabilitation depends on
many variables, including the following:
level and type of amputation
type and degree of any resulting
impairments and disabilities
overall health of the patient
family support
21.
The goal ofrehabilitation after an amputation
is to help the patient return to the highest
level of function and independence
possible, while improving the overall
quality of life - physically, emotionally, and
socially.
22.
In order tohelp reach these goals, amputation
rehabilitation programs may include the
following:
treatments to help improve wound healing and
stump care
activities to help improve motor skills, restore
activities of daily living (ADLs), and help the
patient reach maximum independence
exercises that promote muscle strength, and
control
23.
pain managementfor both post-operative and
phantom pain (a sensation of pain that occurs
below the level of the amputation)
emotional support to help during the grieving
period and with readjustment to a new body image
fitting and use of artificial limbs (prostheses
use of assistive devices
nutritional counseling to promote healing and
health
vocational counseling
adapting the home environment for ease of
function, safety, accessibility, and mobility
patient and family education
24.
Rehabilitation programs forpatients with
amputations can be conducted on an
inpatient or outpatient basis. Many skilled
professionals are part of the amputation
rehabilitation team, including any/all of the
following:
The Rehabilitation Team
25.
Orthopaedists/orthopaedic surgeons
Physical therapist
Occupational therapist
Orthotist
Prosthetist
Social worker
Nurse
vocational counselor
The Team
26.
The majorcomponents of a lower
extremity prosthesis are:
the socket (with or without a socket liner),
a suspension system,
Joint components (as needed)
a shank (pylon) and
a prosthetic foot
LOWER EXTREMITY PROSTHESIS
COMPONENTS
27.
Functions:
Thesocket serves as the interface between
the residual limb and the prosthesis.
protect the residual limb
appropriately transmit the forces associated
with standing and ambulation. ·
The socket
28.
The PTBwith hard socket
Adavantages
Perspiration
Lessy bulky
Easy to clean
Contours won’t compress
Relief's precisely located
Socket types
29.
Disadvantages of hardsocket
Requires more skill
Not for bony or sensitive residuum
Not easy to modify
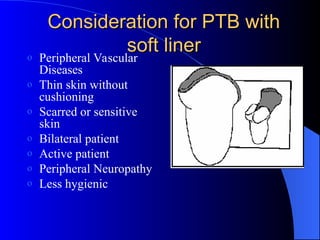
30.
Consideration for PTBwith
Consideration for PTB with
soft liner
soft liner
o Peripheral Vascular
Diseases
o Thin skin without
cushioning
o Scarred or sensitive
skin
o Bilateral patient
o Active patient
o Peripheral Neuropathy
o Less hygienic
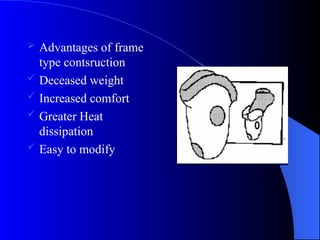
31.
Advantages offrame
type contsruction
Deceased weight
Increased comfort
Greater Heat
dissipation
Easy to modify
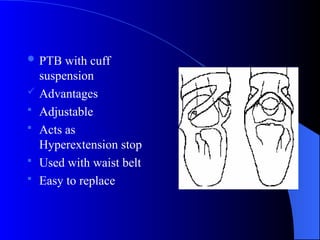
32.
PTB withcuff
suspension
Advantages
Adjustable
Acts as
Hyperextension stop
Used with waist belt
Easy to replace
33.
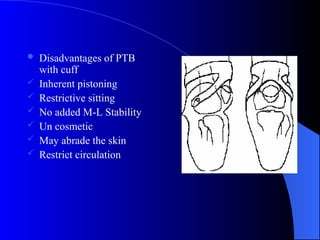
Disadvantages ofPTB
with cuff
Inherent pistoning
Restrictive sitting
No added M-L Stability
Un cosmetic
May abrade the skin
Restrict circulation
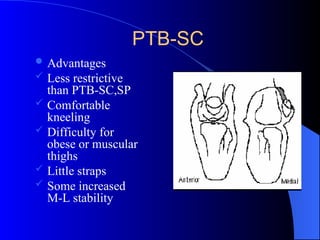
PTB-SC
Advantages
Lessrestrictive
than PTB-SC,SP
Comfortable
kneeling
Difficulty for
obese or muscular
thighs
Little straps
Some increased
M-L stability
36.
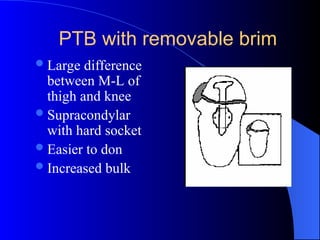
PTB with removablebrim
Large difference
between M-L of
thigh and knee
Supracondylar
with hard socket
Easier to don
Increased bulk
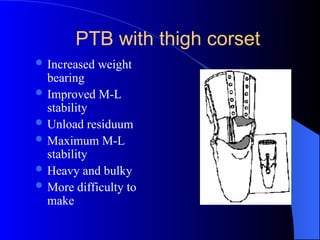
37.
PTB with thighcorset
Increased weight
bearing
Improved M-L
stability
Unload residuum
Maximum M-L
stability
Heavy and bulky
More difficulty to
make
38.
Prosthetic Knees
The prostheticknee can have a single axis
with a simple hinge and a single pivot point,
or it may have a polycentric axis with
multiple centers of rotation

 Most read



 Most read