Advanced Radiotherapy and Brachytherapy Techniques in Head and Neck Cancer Management
Comprehensive overview of radiotherapy, brachytherapy, imaging, and treatment planning for head and neck cancers, emphasizing tumor control, tissue sparing, and quality of life improvements.
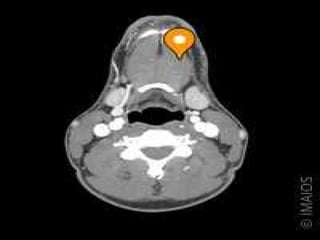
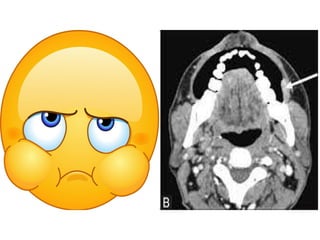
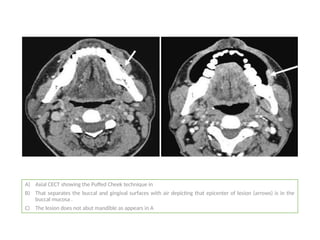
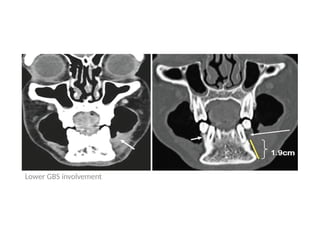
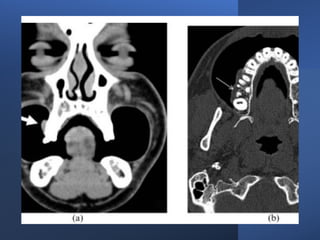
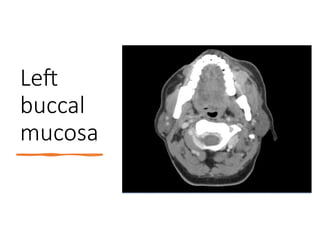
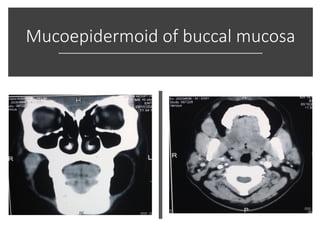
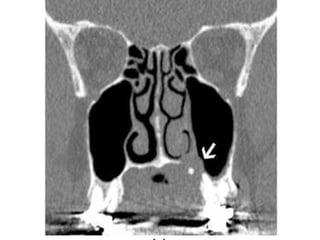
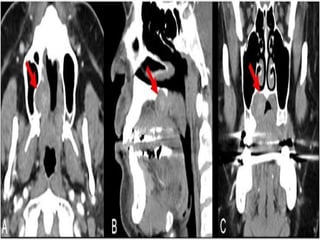
A) Axial CECTshowing the Puffed Cheek technique in
B) That separates the buccal and gingival surfaces with air depicting that epicenter of lesion (arrows) is in the
buccal mucosa .
C) The lesion does not abut mandible as appears in A
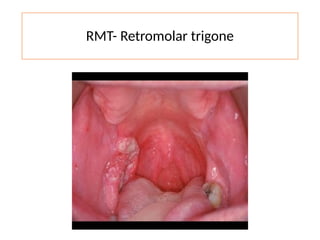
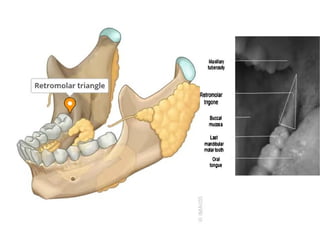
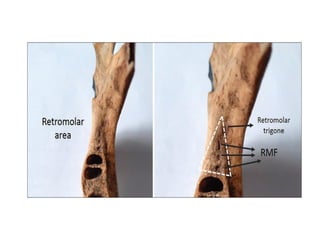
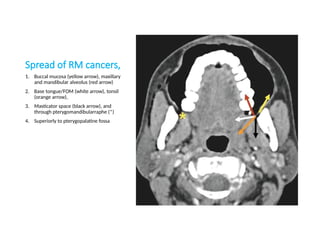
Spread of RMcancers,
1. Buccal mucosa (yellow arrow), maxillary
and mandibular alveolus (red arrow)
2. Base tongue/FOM (white arrow), tonsil
(orange arrow),
3. Masticator space (black arrow), and
through pterygomandibularraphe (*)
4. Superiorly to pterygopalatine fossa
43.
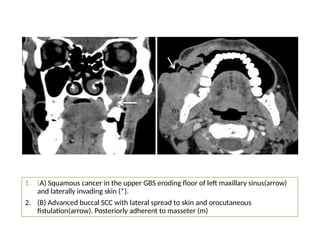
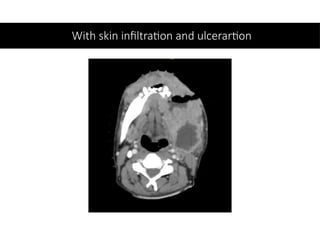
1. (A) Squamouscancer in the upper GBS eroding floor of left maxillary sinus(arrow)
and laterally invading skin (*).
2. (B) Advanced buccal SCC with lateral spread to skin and orocutaneous
fistulation(arrow). Posteriorly adherent to masseter (m)
44.
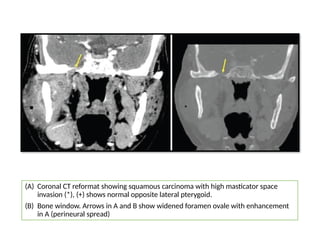
(A) Coronal CTreformat showing squamous carcinoma with high masticator space
invasion (*), (+) shows normal opposite lateral pterygoid.
(B) Bone window. Arrows in A and B show widened foramen ovale with enhancement
in A (perineural spread)
46.
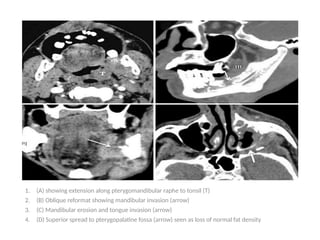
1. (A) showingextension along pterygomandibular raphe to tonsil (T)
2. (B) Oblique reformat showing mandibular invasion (arrow)
3. (C) Mandibular erosion and tongue invasion (arrow)
4. (D) Superior spread to pterygopalatine fossa (arrow) seen as loss of normal fat density
47.
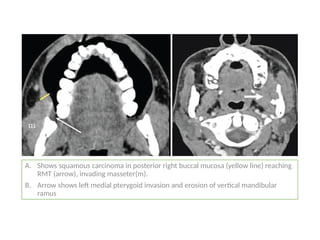
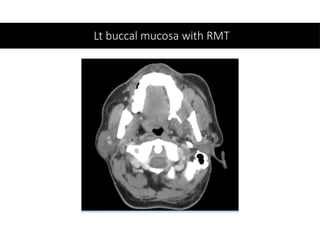
A. Shows squamouscarcinoma in posterior right buccal mucosa (yellow line) reaching
RMT (arrow), invading masseter(m).
B. Arrow shows left medial pterygoid invasion and erosion of vertical mandibular
ramus
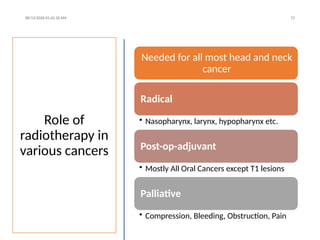
Role of
radiotherapy in
variouscancers
08/13/2026 01:42:10 AM 72

Needed for all most head and neck
cancer
Radical
• Nasopharynx, larynx, hypopharynx etc.
Post-op-adjuvant
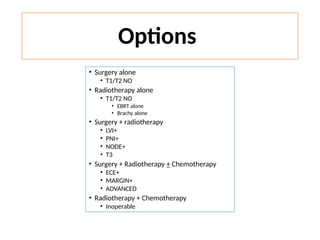
• Mostly All Oral Cancers except T1 lesions
Palliative
• Compression, Bleeding, Obstruction, Pain
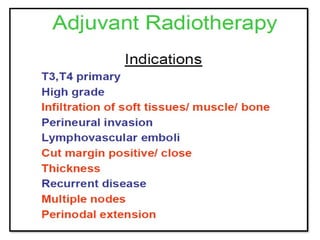
74.
Postoperative Radiation forOral Cavity
Squamous Cell Carcinoma
• Oral Cavity Cancer is a Surgical Disease
• Use Radiation Postoperatively for Appropriate Patients
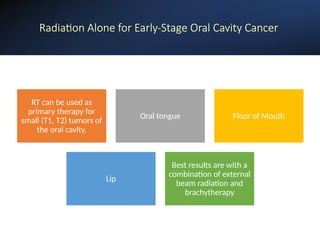
Radiation Alone forEarly-Stage Oral Cavity Cancer
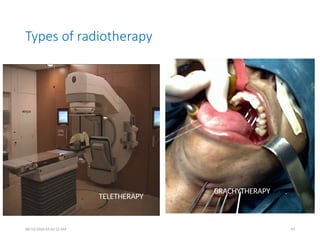
RT can be used as
primary therapy for
small (T1, T2) tumors of
the oral cavity.
Oral tongue Floor of Mouth
Lip
Best results are with a
combination of external
beam radiation and
brachytherapy
History- radiation
1896 –Becquerel - Radioactivity
1898 – Madam Curie / Pierre Curie - Radium
1903 – Nobel Prize for Curie’s & Becquerel
1903 – First successful case of malignancy basal cell carcinoma of
face
08/13/2026 01:42:12 AM 91
92.
GOALS
High doseto tumor tissue-Tumor control
Normal tissue sparing
Minimize long and short term toxicities
Better Quality of life
08/13/2026 01:42:12 AM 92
93.
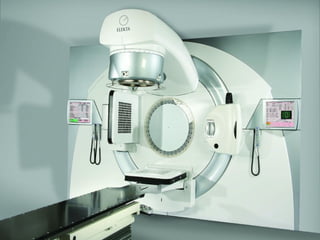
Treatment
• Delivered 5days per week over 6-8 weeks
• Typical treatment takes around 5 minutes
• Treatment is painless--like having an X-ray taken
• No radioactive substances involved; beam goes on/off
• Side effects usually temporary; controlled with medication/diet
• Covered by Medicare and many other insurance companies
08/13/2026 01:42:12 AM 93