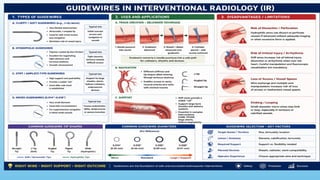
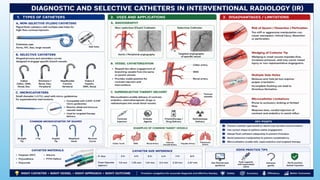
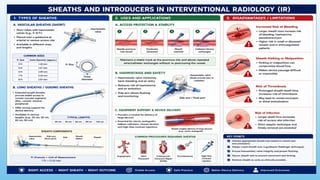
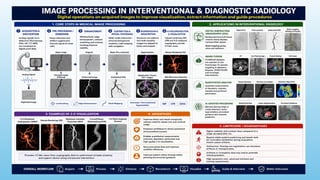
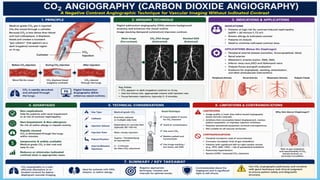
Advanced Monitoring and Cardiac Resuscitation Techniques ,Instrumentations,co2 angiography,ACT equiment, in Interventional Radiology
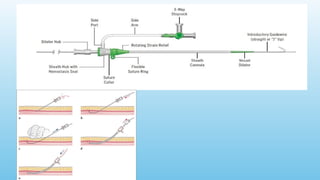
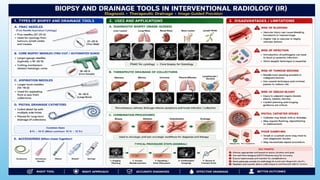
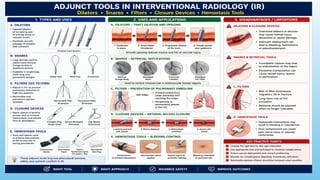
Overview of pulse oximetry, ECG in cardiac resuscitation, pressure injectors, catheters, needle, sheets, and imaging tools used in interventional radiology for patient monitoring and emergency response.co2 angiography, ACT equipment.
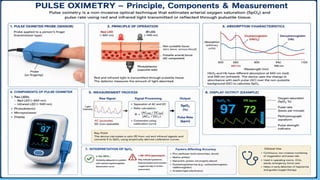
PULSE OXIMETRY
• pulseoximetry is a non‑invasive optical
technique that estimates arterial oxygen
saturation (SpO₂) and pulse rate using red
and infrared light transmitted or reflected
through pulsatile tissue, most commonly a
fingertip or earlobe.
4.
Basic principle
• Bluepulse oximeter probe applied to a person's finger.
• A pulse oximeter uses two LEDs, typically around 660 nm (red) and 940 nm (infrared), and a
photodetector positioned opposite (transmission type) or adjacent (reflectance type) to the tissue.
• Oxyhemoglobin and deoxyhemoglobin have different absorption characteristics at these
wavelengths; by measuring the change in absorbance with each arterial pulse (AC component)
over the non‑pulsatile background (venous blood, tissue; DC component), the device calculates a
ratio that is converted to SpO₂ via empirically derived calibration curves.
• Measurement and output
• Pulse oximeter diagram
• The sensor detects the pulsatile increase in arterial blood volume with each heartbeat and extracts
this signal to provide heart rate and the corresponding oxygen saturation value, usually displayed
as a percentage (e.g., SpO₂ 97%).
• In routine clinical practice, readings 94–95% in a patient with a normal oxyhemoglobin
≥
dissociation curve are generally considered adequate, while persistent values below this range
may suggest hypoxemia and trigger further assessment or oxygen therapy.
5.
Clinical uses
• Pulseoximetry is widely used as a continuous monitoring tool in anesthesia, critical care, emergency
departments, and during procedural sedation, and is often described as the “fifth vital sign.”
• It is also employed for screening and monitoring in chronic respiratory or cardiac conditions, assessing
response to supplemental oxygen, and in portable/wearable devices for home or ambulatory
monitoring.
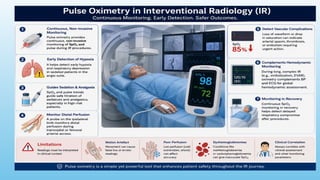
• Pulse oximetry provides continuous, non‑invasive monitoring of SpO₂ and pulse during IR procedures.
• It helps detect early hypoxia and respiratory depression in sedated patients in the angio suite.
• SpO₂ and pulse trends guide safe titration of sedatives and analgesics, especially in high‑risk patients.
• A probe on the ipsilateral limb monitors distal perfusion during transradial or femoral arterial access.
• Loss of waveform or drop in saturation can indicate arterial spasm, thrombosis, or embolism requiring
urgent action.
• During long, complex IR (e.g., embolization, EVAR), oximetry complements BP and ECG for global
hemodynamic assessment.
• Continuous SpO₂ monitoring in recovery helps detect delayed respiratory compromise after
procedures.
• Limitations include motion artefact, poor perfusion, and dyshemoglobinemias, so readings must be
interpreted in clinical context.
6.
Types of pulseoximeters
• Bedside and transport monitors use cabled sensors (finger, ear,
toe, or forehead) as part of multiparameter systems in hospitals,
while compact clip‑on fingertip devices are common for spot
checks in clinics and home use.
• Newer wearable designs integrate reflective sensors into
watches or patches, enabling long‑term trend monitoring but
often with performance characteristics that differ from
medical‑grade, regulated devices.
7.
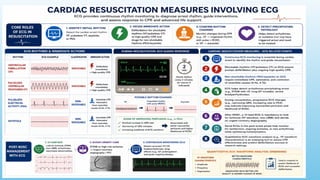
Cardiac resuscitation
• Cardiacresuscitation measures involving ECG focus on using
continuous rhythm monitoring to diagnose arrest rhythm, guide
interventions, and assess response to CPR and advanced life
support.
• Core roles of ECG in resuscitation
• Identify initial rhythm: ventricular fibrillation (VF), pulseless VT,
asystole, or pulseless electrical activity (PEA).
• Decide immediate action: defibrillation for shockable rhythms
(VF/pulseless VT) vs high‑quality CPR and drugs for non‑shockable
rhythms (PEA/asystole).
• Confirm rhythm changes during CPR (e.g., VF organized rhythm
→
with pulse = ROSC, or VF asystole).
→
8.
Cardiac resuscitation measures– ECG
• Continuous ECG monitoring is essential during cardiac arrest to identify the rhythm
and guide resuscitation.
• Shockable rhythms (VF/pulseless VT) on ECG require prompt defibrillation plus
ongoing high‑quality CPR.
• Non‑shockable rhythms (PEA/asystole) on ECG require immediate CPR, adrenaline,
and correction of reversible causes (4 Hs, 4 Ts).
• ECG helps detect arrhythmias precipitating arrest (e.g., STEMI with VF, long‑QT
torsades, severe bradyarrhythmias).
• During resuscitation, progressive ECG changes (e.g., narrowing QRS, increasing rate in
PEA) may indicate improving myocardial perfusion and likelihood of ROSC.
• After ROSC, a 12‑lead ECG is mandatory to look for ischemia (ST elevation, new LBBB)
and decide on urgent coronary angiography.
• Serial ECGs in the post‑arrest phase help monitor for reinfarction, ongoing ischemia,
or new arrhythmias while optimizing hemodynamics.
• Quantitative ECG waveform analysis (e.g., VF waveform characteristics) is an emerging
tool to assess CPR effectiveness and predict defibrillation success in research settings.
9.
Cardiac resuscitation measures- ECG
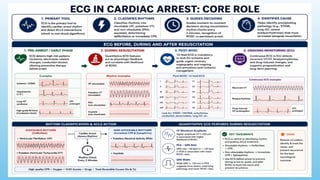
• ECG in Cardiac Arrest: Core Role
• ECG is the primary tool to identify cardiac arrest rhythm and
direct ACLS interventions (shock vs non‑shock algorithms).
• Classifies rhythms into shockable (VF, pulseless VT) and
non‑shockable (PEA, asystole), determining defibrillation or
immediate CPR
• Guides moment‑to‑moment decisions during resuscitation:
rhythm checks every 2 minutes, recognition of ROSC vs
persistent arrest.
• Helps identify precipitating pathology (e.g., STEMI, long‑QT,
severe bradyarrhythmias) that must be treated alongside
resuscitation.
10.
ECG Before, Duringand After Resuscitation
• Pre‑arrest / early phase: ECG detects high‑risk patterns
(ischemia, electrolyte‑related changes, conduction blocks)
allowing preventive therapy before arrest.
• During resuscitation: quantitative ECG features (VF
waveform, QRS rate and width in PEA) act as physiologic
feedback and correlate with likelihood of ROSC.
• Post‑ROSC: 12‑lead ECG is mandatory to look for ischemia and
guide urgent coronary angiography and ongoing
anti‑arrhythmic/anti‑ischemic management.
• Ongoing monitoring: continuous ECG in ICU detects
recurrent VT/VF, bradyarrhythmias, and drug‑induced
changes, and supports prognostication and long‑term
planning.