1
ADULT IMMUNISATION – HOW AND WHY
IT’S RELEVANT!
DR BODHISATWA CHOUDHURI
MBBS, MD(MED), MRCEM(UK), MEM(USA), MRCP ACUTE MEDICINE,
DIP RHEUMATOLOGY(UK), CCEBDM, CCIDC, FCCS
CONSULTANT & IN-CHARGE, EMERGENCY & CRITICAL CARE, RHEUMATOLOGY,
PARKVIEW SUPER-SPECIALTY HOSPITAL, SALT LAKE, KOLKATA
SECRETARY, SEMI WEST BENGAL CHAPTER
VACCINATION IN
ADULTS: AN
UNDERUTILIZED
OPPORTUNITY
2
3
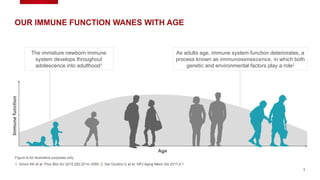
Figure is for illustrative purposes only
OUR IMMUNE FUNCTION WANES WITH AGE
1. Simon AK et al. Proc Biol Sci 2015;282:2014–3085; 2. Del Giudice G et al. NPJ Aging Mech Dis 2017;4:1
As adults age, immune system function deteriorates, a
process known as immunosenescence, in which both
genetic and environmental factors play a role2
Immune
function
Age
The immature newborn immune
system develops throughout
adolescence into adulthood1
4
T cells
B cells
NK cells
Neutrophils
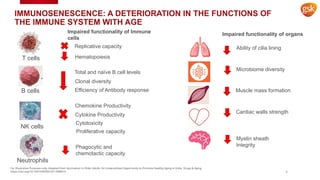
Impaired functionality of organs
Impaired functionality of Immune
cells
Hematopoiesis
Total and naïve B cell levels
Clonal diversity
Efficiency of Antibody response
Chemokine Productivity
Cytokine Productivity
Cytotoxicity
Proliferative capacity
Phagocytic and
chemotactic capacity
Replicative capacity
Myelin sheath
Integrity
Cardiac walls strength
Muscle mass formation
Microbiome diversity
Ability of cilia lining
For Illustrative Purposes only. Adapted from Vaccination in Older Adults: An Underutilized Opportunity to Promote Healthy Aging in India, Drugs & Aging
https://doi.org/10.1007/s40266-021-00864-4
IMMUNOSENESCENCE: A DETERIORATION IN THE FUNCTIONS OF
THE IMMUNE SYSTEM WITH AGE
5
MANY EXTERNAL FACTORS, INCLUDING VACCINATION, ARE
CONSIDERED IMPORTANT TO A HEALTHY LIFESTYLE
Philip RK et al. Expert Rev Vaccines 2018;17:851–864; 2. Doherty MT et al. Ann Med 2019;51:128–140
Healthy eating
Physical activity
Life-course immunisation
Smoking avoidance or
cessation
Screening for health
conditions
Hygiene
Vaccination, like other external influences
such as diet and exercise, is a key element of
maintaining health throughout life1
These factors are also under the control of the individual, requiring individual acceptance and autonomy2
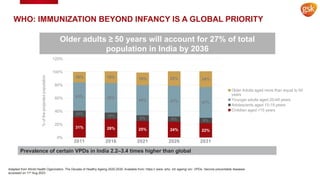
WHO: IMMUNIZATION BEYOND INFANCY IS A GLOBAL PRIORITY
Adapted from World Health Oganization. The Decade of Healthy Ageing 2020-2030. Available from: https:// www. who. int/ ageing/ en/. VPDs: Vaccine preventable diseases
accessed on 11th
Aug 2023
Older adults ≥ 50 years will account for 27% of total
population in India by 2036
Prevalence of certain VPDs in India 2.2–3.4 times higher than global
2011 2016 2021 2026 2031
0%
20%
40%
60%
80%
100%
120%
31% 28% 25% 24% 22%
10%
10%
9% 8% 8%
43% 45%
46% 47% 47%
16% 18% 19% 22% 24%
Older Adults aged more than equal to 50
years
Younger adults aged 20-49 years
Adolescents aged 15-19 years
Children aged <15 years
%
of
the
projected
population
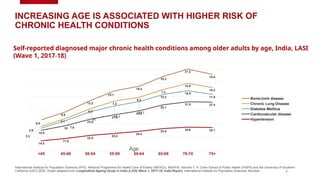
INCREASING AGE IS ASSOCIATED WITH HIGHER RISK OF
CHRONIC HEALTH CONDITIONS
7
International Institute for Population Sciences (IIPS), National Programme for Health Care of Elderly (NPHCE), MoHFW, Harvard T. H. Chan School of Public Health (HSPH) and the University of Southern
California (USC) 2020. Graph adapted from Longitudinal Ageing Study in India (LASI) Wave 1, 2017-18, India Report, International Institute for Population Sciences, Mumbai.
Self-reported diagnosed major chronic health conditions among older adults by age, India, LASI
(Wave 1, 2017-18)
<45 45-49 50-54 55-59 60-64 65-69 70-74 75+
14.5
17.9
22.5
25.4
28.4
32.6 34.6 34.1
15.5
19
23.9
27.5
30.3
35.1
37.5 37.4
3.3
7.6
11
13.1
13.7
15.3
16.4
11.5
2.6
3.1
4.3
7.2
6.2
7.3
10.8
10.2
9.5
9.8
12.2
15.1
16.4
19.3
21.2
19.4
Bone/Joint disease
Chronic Lung Disease
Diabetes Mellitus
Cardiovascular disease
Hypertension
Age
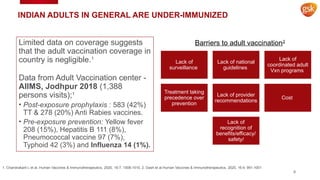
INDIAN ADULTS IN GENERAL ARE UNDER-IMMUNIZED
Limited data on coverage suggests
that the adult vaccination coverage in
country is negligible.1
Data from Adult Vaccination center -
AIIMS, Jodhpur 2018 (1,388
persons visits);1
• Post-exposure prophylaxis : 583 (42%)
TT & 278 (20%) Anti Rabies vaccines.
• Pre-exposure prevention: Yellow fever
208 (15%), Hepatitis B 111 (8%),
Pneumococcal vaccine 97 (7%),
Typhoid 42 (3%) and Influenza 14 (1%).
8
1. Chandrakant L et al. Human Vaccines & Immunotherapeutics, 2020, 16:7, 1508-1510, 2. Dash et al.Human Vaccines & Immunotherapeutics, 2020, 16:4, 991-1001
Barriers to adult vaccination2
Lack of
surveillance
Lack of national
guidelines
Lack of
coordinated adult
Vxn programs
Treatment taking
precedence over
prevention
Lack of provider
recommendations
Cost
Lack of
recognition of
benefits/efficacy/
safety/
9
IMPORTANCE OF VACCINATION
• Vaccination is one of the most cost-effective strategies available in public
health today.
• In addition to protecting the vaccinated individual from developing a
potentially serious disease, vaccines help protect the community by
reducing the spread of infectious diseases.

• It is highly fitting that one of the most dramatic successes in the history of
public health, the eradication of small pox served as a definitive
conclusion to the story of smallpox vaccination by Edward Jenner.
• A potential exists where the immunization program can expand its
immunization activities beyond infancy to accommodate newer vaccines
for adolescents and adults, depending on disease burden and cost-
effectiveness of the intervention.
10
AT RISK POPULATION
• Elderly
• Healthcare personnel
• Diabetics
• Patients with CKD, CLD
• Patients with heart or lung disease
• Immunocompromised patients – due to disease or medicines
11
GUIDELINES
Unlike the Paediatric Immunization Guidelines, given by the Indian
Academy of Pediatrics and the National Immunization Programs, the
guidelines for vaccination in healthy adults vary from region to region.
The major guidelines are:
• The Advisory Committee on Immunization Practices (ACIP) guidelines
from Centers for Disease Control and Prevention
• WHO guidelines
• Association of Physicians of India – Expert panel guidelines
12
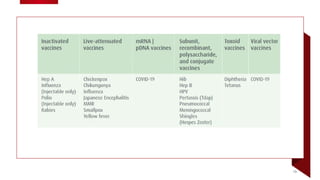
13
Tetanus, Diphtheria, Pertussis
(Tdap/Td)
Measles, Mumps, Rubella (MMR)
Varicella
Zoster recombinant *
Human Papillomavirus
Pneumococcal conjugate vaccine
Pneumococcal polysaccharide
vaccine
Hepatitis A/B vaccine
Meningococcal A,C,W,Y
Meningococcal B
Influenza Inactivated
VACCINE 19-26 yrs 27-49 yrs 50-64 yrs ≥65 yrs
1 dose annually
1 dose Tdap in each pregnancy, 1 dose Tdap & then Td/Tdap booster every 10 years
1 or 2 doses depending on indication ( if born 1957 or later)
2 doses (if born 1980 or later) 2 doses
2 doses
2/3 doses 27 -45 years
1 dose
1 or 2 dose depending on indication
2 or 3 dose depending on vaccine
1 or 2 dose depending on indication
2 or 3 dose depending on indication & vaccine
ADULT IMMUNIZATION SCHEDULE
Ref: Adapted from https://www.cdc.gov/vaccines/schedules/hcp/imz/adult.html accessed on: 17/07/2023
*RZV recommendation is adapted as per the approved indication in India, Indication : SHINGRIX is approved in India as a 2-dose
vaccine for the Prevention of herpes zoster and PHN in adults aged 50 years and above
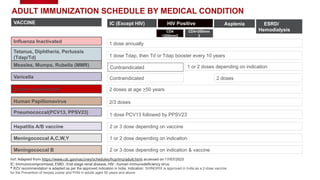
Tetanus, Diphtheria, Pertussis
(Tdap/Td)
Measles, Mumps, Rubella (MMR)
Varicella
Zoster recombinant*
Human Papillomavirus
Pneumococcal(PCV13, PPSV23)
Hepatitis A/B vaccine
Meningococcal A,C,W,Y
Meningococcal B
Influenza Inactivated
VACCINE IC (Except HIV) HIV Positive Asplenia ESRD/
Hemodialysis
1 dose annually
1 dose Tdap, then Td or Tdap booster every 10 years
1 or 2 doses depending on indication
Contraindicated 2 doses
2 doses at age >50 years
2/3 doses
1 dose PCV13 followed by PPSV23
2 or 3 dose depending on vaccine
1 or 2 dose depending on indication
2 or 3 dose depending on indication & vaccine
Ref: Adapted from https://www.cdc.gov/vaccines/schedules/hcp/imz/adult.html accessed on 17/07/2023
IC: Immunocompromised, ESRD : End-stage renal disease, HIV : human immunodeficiency virus
* RZV recommendation is adapted as per the approved indication in India, Indication: SHINGRIX is approved in India as a 2-dose vaccine
for the Prevention of herpes zoster and PHN in adults aged 50 years and above
Contraindicated
CD4
<200mm3
CD4>200mm
3
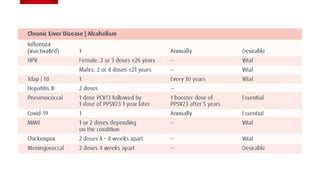
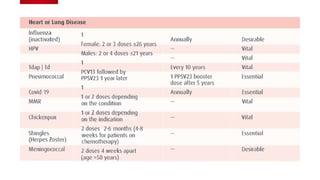
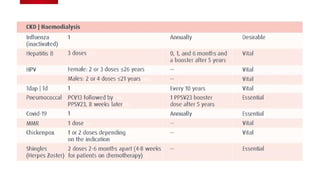
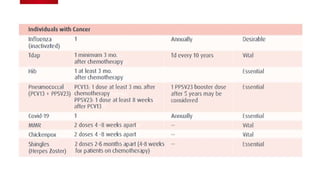
ADULT IMMUNIZATION SCHEDULE BY MEDICAL CONDITION
INFLUENZA
VACCINATION :
FOR HEALTHY
AGEING
16
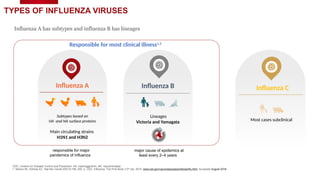
Influenza A has subtypes and influenza B has lineages
TYPES OF INFLUENZA VIRUSES
CDC, Centers for Disease Control and Prevention; HA, haemagglutinin; NA, neuraminidase.
1. Nelson MI, Holmes EC. Nat Rev Genet 2007;8:196–205; 2. CDC. Influenza. The Pink Book (13th
ed), 2015. www.cdc.gov/vaccines/pubs/pinkbook/flu.html. Accessed August 2018.
Most cases subclinical
Influenza C
Lineages
Victoria and Yamagata
Influenza B
Influenza A
Subtypes based on
HA and NA surface proteins
Main circulating strains
H1N1 and H3N2
Responsible for most clinical illness1,2
responsible for major
pandemics of influenza
major cause of epidemics at
least every 2–4 years
CLINICAL SYMPTOMS AND COMPLICATIONS OF INFLUENZA
1. CDC. Influenza. The Pink Book. 2015. www.cdc.gov/vaccines/pubs/pinkbook/flu.html. Accessed August 2018; 2. Hite LK et al. Medically attended pediatric influenza during the resurgence of the Victoria lineage of influenza B virus. Int J Infect Dis
2007;11:40–7; 3. WHO. Influenza (Seasonal). 2018. http://www.who.int/en/news-room/fact-sheets/detail/influenza-(seasonal) Accessed August 2018; 4. CDC. Flu Symptoms & Complications. 2018.
https://www.cdc.gov/flu/about/disease/complications.htm. Accessed August 2018.
Myalgia, especially
of back muscles
Runny nose Gastrointestinal: abdominal
pain, diarrhoea and vomiting
Sudden onset of fever,
extreme fatigue
Headache
Non-productive cough,
sore throat
Complications of influenza can include:4
• Sinus and ear infections • Pneumonia • Myocarditis • Encephalitis • Myositis • Rhabdomyolysis
• Multi organ failure (eg respiratory and kidney failure)
‑ • Extreme inflammatory response and sepsis
• Exacerbation of pre-existing asthma • Exacerbation of pre-existing chronic heart disease
Symptoms are similar for influenza A and B1–3
Influenza symptoms are easily recognisable but complications can be diverse
PEOPLE WITH DIABETES EXPERIENCE MORE SERIOUS OUTCOMES
FOLLOWING INFLUENZA INFECTION
.
ICU, intensive care unit
.1. Allard R, et al. Diabetes Care. 2010; 33:1491–3. 2 Valdez R, et al. Am J Public Health. 1999; 89: 1715–21. 3. Bouter KP, Diabetes Res Clin Pract 1991;12:61-8. 4. https
https://www.gov.uk/government/publications/influenza-the-green-book-chapter-19, Accessed Oct 2021
Influenza infection in people with
diabetes leads to:
risk of hospitalization1,3
3-6x
4x risk of ICU admission1*
risk of death from pneumonia2*
risk of death4*
4x
6x
*versus people without diabetes #-During Influenza season
(95% CI 1.29-1.43) (95% CI 3.8-8.9)
(95% CI 2.3-7.7)
(n=10,000)
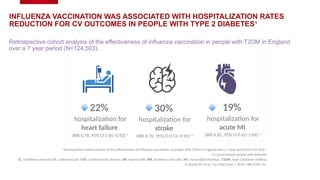
INFLUENZA VACCINATION WAS ASSOCIATED WITH HOSPITALIZATION RATES
REDUCTION FOR CV OUTCOMES IN PEOPLE WITH TYPE 2 DIABETES1
VA C C I N AT I O N &
C V D
†
Retrospective cohort analysis of the effectiveness of influenza vaccination in people with T2DM in England over a 7 year period (N=124,503).1
*vs unvaccinated people with diabetes.
CI, confidence interval; CV, cardiovascular; CVD, cardiovascular disease; HR, hazard ratio; IRR, incidence rate ratio; MI, myocardial infarction; T2DM, type 2 diabetes mellitus.
1. Vamos EP, et al. Can Med Assoc J. 2016; 188: E342–51.
22%
hospitalization for
heart failure
(IRR 0.78, 95% CI 0.65–0.92)*1
30%
hospitalization for
stroke
(IRR 0.70, 95% CI 0.53–0.91)*1
19%
hospitalization for
acute MI
(IRR 0.81, 95% CI 0.62–1.04)*1
Retrospective cohort analysis of the effectiveness of influenza vaccination in people with T2DM in England
over a 7 year period (N=124,503).
RECOMMENDATIONS : INFLUENZA VACCINATION IN AT RISK INDIVIDUALS
21
AUS, Department of Health of the Australian Government; CDC, US Centers for Disease Control; ECDC, European Centre for Disease
Prevention and Control; NHS, UK National Health Service; STIKO, Standing Committee on Vaccination at the Robert Koch Institute (Germany)
CDC. Recommended Adult Immunization Schedule. https://www.cdc.gov/vaccines/schedules/downloads/adult/adult-combined-schedule.pdf 2. WHO. Vaccines against influenza. WHO position paper. 2012. https://www.who.int/immunization/position_papers/PP_influenza_november2012_summary.pdf?ua=1 3. ECDC. GUIDANCE PRIORITY RISK GROUPS
FOR INFLUENZA VACCINATION https://www.ecdc.europa.eu/sites/portal/files/media/en/publications/Publications/0808_GUI_Priority_Risk_Groups_for_Influenza_Vaccination.pdf4. NHS. Who should have the flu vaccine? https://www.nhs.uk/conditions/vaccinations/who-should-have-flu-vaccine/ 5. STIKO. Epidemiologisches Bulletin. 2017.
https://www.rki.de/EN/Content/infections/Vaccination/recommandations/34_2017_engl.pdf?__blob=publicationFile 6. Australian Government Department of Health. List. Specified medical conditions associated with increased risk of influenza disease and severe outcomes.
https://immunisationhandbook.health.gov.au/resources/handbook-tables/list-specified-medical-conditions-associated-with-increased-risk-of-0 7. ICS:NCCP Influenza guidelines. Lung India 37(7):S4-18 DOI:10.4103/lungindia.lungindia_270_20 8. Geriatric society of India vaccination recommendation.
http://www.geriatricindia.com/indian_vaccination_guidelines.html. Accessed in May 2021 9. https://www.japi.org/v2c494b4/api-guidelines-on-immunizations-during-covid-19-pandemic, Accessed in May 2021. 10.http://www.who.int/wer/2012/wer8747.pdf?ua=1 Accessed Oct 2021 11.
https://www.ecdc.europa.eu/sites/default/files/documents/seasonal-influenza-antiviral-use-2018.pdf , accessed Oct 2021 12.
10. RSSDI guidelines for management of Diabetes https://www.ncbi.nlm.nih.gov/pmc/articles/PMC7328526/
• Global Recommendations
– CDC,1
WHO,2
ECDC,3
NHS,4
STIKO,5
AUS6
• India Recommendations
– Indian Chest Society & National College of Chest
Physicians, 20197
– Geriatric Society of India (GSI), 20158
– Association of Physicians of India (API), 2016 & 20209
Annual influenza vaccination is recommended for
people with diabetes1
• WHO10
• ECDC11
• International Diabetes Federation
• American Diabetes Association
• CDC
• RSSDI
PERTUSSIS: NOT JUST A
CHILDHOOD DISEASE
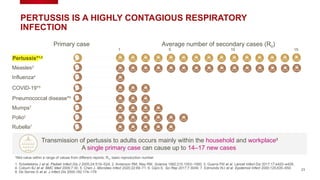
PERTUSSIS IS A HIGHLY CONTAGIOUS RESPIRATORY
INFECTION
23
1. Schellekens J et al. Pediatr Infect Dis J 2005;24:S19–S24; 2. Anderson RM, May RM. Science 1982;215:1053–1060; 3. Guerra FM et al. Lancet Infect Dis 2017;17:e420–e428;
4. Coburn BJ et al. BMC Med 2009;7:30; 5. Chen J. Microbes Infect 2020;22:69–71; 6. Gijini E. Sci Rep 2017;7:3049; 7. Edmunds WJ et al. Epidemiol Infect 2000;125;635–650;
8. De Serres G et al. J Infect Dis 2000;182:174–179
1
Average number of secondary cases (R0)
Primary case
Transmission of pertussis to adults occurs mainly within the household and workplace8
A single primary case can cause up to 14–17 new cases
Pertussis*1,2
Measles3
Influenza4
Mumps7
Polio2
Rubella7
Pneumococcal disease*6
*Mid-value within a range of values from different reports; R0, basic reproduction number
COVID-19*5
5 10 15
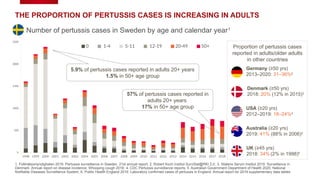
Number of pertussis cases in Sweden by age and calendar year1
THE PROPORTION OF PERTUSSIS CASES IS INCREASING IN ADULTS
1. Folkhälsomyndigheten 2019. Pertussis surveillance in Sweden. 21st annual report; 2. Robert Koch Institut SurvStat@RKI 2.0; 3. Statens Serum Institut 2019. Surveillance in
Denmark. Annual report on disease incidence: Whooping cough 2018; 4. CDC Pertussis surveillance reports; 5. Australian Government Department of Health 2020. National
Notifiable Diseases Surveillance System; 6. Public Health England 2019. Laboratory confirmed cases of pertussis in England. Annual report for 2019 supplementary data tables
1998 1999 2000 2001 2002 2003 2004 2005 2006 2007 2008 2009 2010 2011 2012 2013 2014 2015 2016 2017 2018
0
500
1000
1500
2000
2500
0 1-4 5-11 12-19 20-49 50+
57% of pertussis cases reported in
adults 20+ years
17% in 50+ age group
5.9% of pertussis cases reported in adults 20+ years
1.5% in 50+ age group
Germany (≥50 yrs)
2013–2020: 31–36%2
Denmark (≥50 yrs)
2018: 20% (12% in 2015)3
USA (≥20 yrs)
2012–2019: 18–24%4
Australia (≥20 yrs)
2019: 41% (88% in 2006)5
Proportion of pertussis cases
reported in adults/older adults
in other countries
UK (≥45 yrs)
2018: 34% (2% in 1998)6
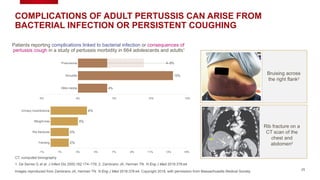
COMPLICATIONS OF ADULT PERTUSSIS CAN ARISE FROM
BACTERIAL INFECTION OR PERSISTENT COUGHING
Urinary incontinence
Weight loss
Rib fractures
Fainting
-1% 1% 3% 5% 7% 9% 11% 13% 15%
4%
3%
2%
2%
CT, computed tomography
25
1. De Serres G et al. J Infect Dis 2000;182:174–179; 2. Zambrano JA, Herman TN. N Eng J Med 2018;378:e4
Images reproduced from Zambrano JA, Herman TN. N Eng J Med 2018;378:e4. Copyright 2018, with permission from Massachusetts Medical Society.
Pneumonia
Sinusitis
Otitis media
-5% 0% 5% 10% 15%
4–9%
13%
4%
Rib fracture on a
CT scan of the
chest and
abdomen2
Bruising across
the right flank2
Patients reporting complications linked to bacterial infection or consequences of
pertussis cough in a study of pertussis morbidity in 664 adolescents and adults1
INCREASINGLY, GLOBAL AND NATIONAL BODIES RECOMMEND
PERTUSSIS BOOSTERS THROUGHOUT LIFE
26
1. World Health Organization (WHO), Regional Office for the Western Pacific. Guidance on COVID-19 for the care of older people and people living in long-term care facilities, other non-acute care facilities and home care facilities, other non-acute care facilities
and home care. 23 March 2020. Manila: WHO Regional Office for the Western Pacific. https://iris.wpro.who.int/handle/10665.1/14500 2. Nationale Lenkungsgruppe Impfen (NALI), 2020. Corona-Pandemie: Wichtiger Schutz vor zusätzlichen Infektionen durch
Impfschutz gemäß STIKO-Empfehlungen. https://www.nali-impfen.de/impfempfehlungen/covid-19-und-impfempfehlungen/ 3. Robert Koch Institute (RKI) COVD FAQ. https://www.rki.de/SharedDocs/FAQ/NCOV2019/gesamt.html 4. SIP 2020. Mantenere ed
incrementare le coperture vaccinali nei bambini e negli anziani: evitiamo di aggiungere epidemie alla pandemia. https://www.sip.it/wp-content/uploads/2020/04/CS-CALENDARIO-PER-LA-VITA-24042020.pdf (all URLs accessed August 2021) 5. GOLD
recommendation 2020, https://goldcopd.org/wp-content/uploads/2019/11/GOLD-2020-REPORT-ver1.0wms.pdf. Accessed in May 2021 6. CDC;2020;1-2;Pertussis: Summary of Vaccine Recommendations 7. Association of Physicians of India guidelines 2009
Countries recommending pertussis booster vaccination
Age group Patient profile Recommendation
GOLD
(2021)5
Adults COPD patients 1 Tdap if not vaccinated
in adolescence
CDC6 >19 years All adults 1 Tdap dose, then
Decennial Tdap booster
API7 18-64 years History of complete primary vaccinations
*- references included in slide notes Tdap- Tetanus Diphtheria Pertussis (Acellular component) vaccine, COPD - Chronic Obstructive Pulmonary Disease, GOLD- Global Initiative for Chronic obstructive Lung disease, CDC- Centres for Disease
controland Prevention API- Association of Physicians of India. CDC recommends decennial Td/Tdap booster
Adults: 23 countries
Includes Australia, Canada, France,
Germany, Belgium, USA*
Older adults: 16 countries
Includes Italy, Greece, Australia,
Canada, France, Germany, Belgium,
USA*
High-risk adults: 10 countries
Includes Australia, Canada, Iceland,
Ireland, Israel, Portugal, USA*
PNEUMOCOCCAL DISEASES:
Confidential. For internal use only. 27
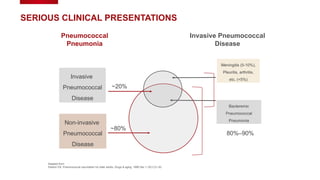
~80%
~20%
Meningitis (5-10%),
Pleuritis, arthritis,
etc. (<5%)
Bacteremic
Pneumococcal
Pneumonia
Invasive
Pneumococcal
Disease
Non-invasive
Pneumococcal
Disease
Invasive Pneumococcal
Disease
Pneumococcal
Pneumonia
SERIOUS CLINICAL PRESENTATIONS
Adapted from:
Fedson DS. Pneumococcal vaccination for older adults. Drugs & aging. 1999 Dec 1;15(1):21-30.
80%–90%
PREDISPOSING RISK FACTORS FOR PNEUMOCOCCAL DISEASE IN
ADULTS
Pneumococcal
Disease
Decreased immune
function from aging,
disease or drugs
Functional or
anatomic asplenia
Chronic heart, lung
(including asthma),
liver, or renal disease
Cigarette smoking
Cerebrospinal fluid
leak or cochlear
implant
Adapted from:
Pneumococcal Disease | Clinical | Risk Factors | CDC. 2017 [cited 13 January 2021]. Available from: https://www.cdc.gov/pneumococcal/clinicians/risk-factors.html
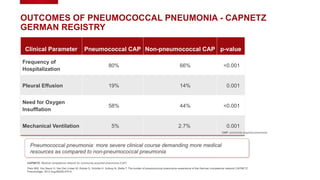
OUTCOMES OF PNEUMOCOCCAL PNEUMONIA - CAPNETZ
GERMAN REGISTRY
Pletz MW, Von Baum H, Van Der Linden M, Rohde G, Schütte H, Suttorp N, Welte T. The burden of pneumococcal pneumonia–experience of the German competence network CAPNETZ.
Pneumologie. 2012 Aug;66(08):470-5.
Clinical Parameter Pneumococcal CAP Non-pneumococcal CAP p-value
Frequency of
Hospitalization
80% 66% <0.001
Pleural Effusion 19% 14% 0.001
Need for Oxygen
Insufflation
58% 44% <0.001
Mechanical Ventilation 5% 2.7% 0.001
Pneumococcal pneumonia: more severe clinical course demanding more medical
resources as compared to non-pneumococcal pneumonia
CAPNETZ- Medical competence network for community-acquired pneumonia (CAP)
CAP: community acquired pneumonia
31
VACCINES
• Conjugate Vaccines: PCV13, PCV15, PCV20
• Polysaccharide Vaccines: PPSV23
• Acc to research by Greenberg et al,
• In pneumococcal vaccine-naïve adults, an initial PCV13 augmented the
anti-pneumococcal response to subsequent administration of PPSV23
for many of the serotypes in common to both vaccines.
• In contrast, an initial PPSV23 resulted in a diminished response to
subsequent administration of PCV13 for all serotypes.
Greenberg RN, Gurtman A, Frenck RW, Strout C, Jansen KU, Trammel J, Scott DA, Emini EA, Gruber WC, Schmoele-Thoma B. Sequential administration of 13-valent pneumococcal conjugate vaccine and 23-
valent pneumococcal polysaccharide vaccine in pneumococcal vaccine-naïve adults 60-64 years of age. Vaccine. 2014 Apr 25;32(20):2364-74. doi: 10.1016/j.vaccine.2014.02.002. Epub 2014 Mar 5. PMID:
24606865.
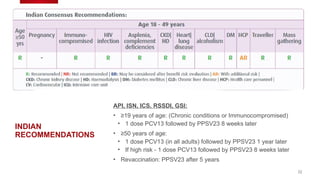
INDIAN
RECOMMENDATIONS
API, ISN, ICS, RSSDI, GSI:
• ≥19 years of age: (Chronic conditions or Immunocompromised)
• 1 dose PCV13 followed by PPSV23 8 weeks later
• ≥50 years of age:
• 1 dose PCV13 (in all adults) followed by PPSV23 1 year later
• If high risk - 1 dose PCV13 followed by PPSV23 8 weeks later
• Revaccination: PPSV23 after 5 years
32
CLINICAL PRACTICE
GUIDELINES
(ICS / NCCP)
INDIAN CONSENSUS-BASED
RECOMMENDATIONS ON
PNEUMOCOCCAL VACCINATION
FOR ADULTS
Indian guidelines on pneumococcal vaccination with PCV13 and PPSV23
* such as chronic heart disease, chronic liver disease, poorly controlled diabetes mellitus, chronic lung disease, and in current smokers and those with alcohol abuse
# such as those with HIV infection, iatrogenic immunosuppression, chronic kidney disease, hematologic malignancy, other solid tumor malignancies with or without metastasis,
hematopoietic stem cell transplantation, and solid-organ transplantation
1. Dhar, Raja, et al. "Clinical practice guidelines 2019: Indian consensus-based recommendations on pneumococcal vaccination for adults." Lung India 37.7 (2020): 19.
PCV: Pneumococcal conjugate vaccine; PPSV: Pneumococcal polysaccharide vaccine
• The Indian guidelines are different from the ACIP guidelines, in terms of recommendation
regarding vaccination with PCV13 vaccine.
• The ACIP guidelines are based on the fact that in the United States, PCV13 is being
administered to all children since the year 2010, and therefore, there is herd immunity,
which prevents adults from being affected by the 13 serotypes covered in PCV13
• In India, pneumococcal vaccination in the pediatric immunization schedule has only been
incorporated recently. Thus, the concept of herd immunity is not applicable.
HEPATITIS
34
35
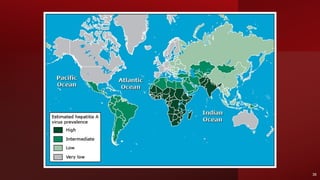
HEPATITIS A
Among the most common preventable infections acquired by travelers
Humans are the only known reservoir for HAV; therefore, the virus could be
eradicated with successful employment of widespread prevention strategies.

Vaccine Schedule: Two doses of 1ml at 6 months interval
Adult Indication: Only for Individuals at increased risk for HAV infection or
at increased risk for severe disease from HAV infection
36
37
RECOMMENDATION FOR HEPATITIS A VACCINATION
Individuals with chronic liver disease, hepatitis B virus infection, hepatitis C virus infection, fatty
liver disease, alcoholic liver disease, autoimmune hepatitis
Individuals ≥1 year with HIV infection
Drug abusers
Male homosexuals
People who work with Hepatitis A virus
Individuals traveling to or working in countries with high or intermediate rates of HAV
HEPATITIS B
38
There are more than 2 billion individuals with serologic evidence of
hepatitis B virus (HBV) infection worldwide
In 2015, 887,000 died due to chronic hepatitis B-associated cirrhosis and
hepatocellular carcinoma
Only 10.5 percent of patients with chronic hepatitis B were aware of their
infection, and less than 2 percent were on treatment
Primary prevention by vaccination to increase herd immunity remains the
main focus of controlling HBV infection
HBV infection can potentially be eradicated through global vaccination
39
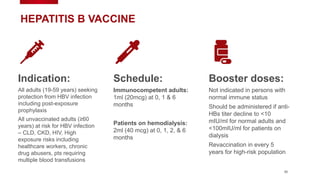
HEPATITIS B VACCINE
Indication:
All adults (19-59 years) seeking
protection from HBV infection
including post-exposure
prophylaxis
All unvaccinated adults (≥60
years) at risk for HBV infection
– CLD, CKD, HIV, High
exposure risks including
healthcare workers, chronic
drug abusers, pts requiring
multiple blood transfusions
Schedule:
Immunocompetent adults:
1ml (20mcg) at 0, 1 & 6
months
Patients on hemodialysis:
2ml (40 mcg) at 0, 1, 2, & 6
months
Booster doses:
Not indicated in persons with
normal immune status
Should be administered if anti-
HBs titer decline to <10
mIU/ml for normal adults and
<100mIU/ml for patients on
dialysis
Revaccination in every 5
years for high-risk population
SHINGLES :
AN ADULT
MENACE
40
HZ, herpes zoster; VZV, varicella zoster virus * US Data
1. Kimberlin DW et al. New Engl J Med 2007;356:1338 1343; 2. Harpaz R
‒ et al. MMWR Recomm Rep 2008;57:1 30
‒
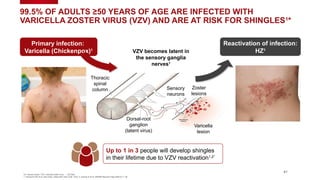
41
Primary infection:
Varicella (Chickenpox)1
VZV becomes latent in
the sensory ganglia
nerves1
Varicella
lesion
Sensory
neurons
Zoster
lesions
Dorsal-root
ganglion
(latent virus)
Reactivation of infection:
HZ1
Thoracic
spinal
column
99.5% OF ADULTS ≥50 YEARS OF AGE ARE INFECTED WITH
VARICELLA ZOSTER VIRUS (VZV) AND ARE AT RISK FOR SHINGLES1
*
Up to 1 in 3 people will develop shingles
in their lifetime due to VZV reactivation1,2*
PRESENTATION & RISK FACTORS OF HERPES ZOSTER (HZ)
HZ incidence is predicted to increase, presenting a growing burden in patients with comorbidities 3,4
42
HZ, herpes zoster; PHN, post-herpetic neuralgia; VZV, varicella zoster virus
1. Mueller NH et al. Neurol Clin 2008;26:675–697; 2. Katz J et al. Clin Infect Dis 2004;39:342–348; 3. Kawai K et al. BMJ Open 2014;4:e004833 4. Centers for Disease Control and Prevention. MMWR. 2008 May;57(RR-5):1-30
Age and immunocompromising conditions are well-recognised risk factors1
Decreased VZV-specific cell-mediated immunity in these groups leads to VZV reactivation
HZ is characterised by acute pain and reduction in quality of life2
HZ incidence has increased in several countries in recent decades3
• Predicted to continue increasing with an ageing population
• May also reflect an increase in other risk factors, use of immunosuppressive agents
or awareness and diagnosis
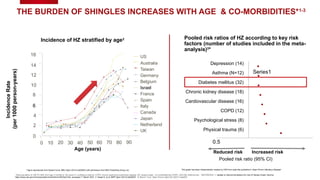
THE BURDEN OF SHINGLES INCREASES WITH AGE & CO-MORBIDITIES*1-3
0
Age (years)
Incidence
Rate
(per
1000
person-years)
10 20 30 40 50 60 70 80 90
0
2
4
6
8
10
12
14
16
Spain
Netherland
Canada
Italy
Japan
Israel
France
Australia
Taiwan
Germany
Belgium
UK
US
Figure reproduced from Kawai K et al. BMJ Open 2014;4:e004833 with permission from BMJ Publishing Group Ltd.
*Total population of 198,751,846, from age 3 months to 104 years CI, confidence interval; COPD, chronic obstructive pulmonary disease; HZ, herpes zoster , Co-morbidities like COPD, CKD,DM, Ashthma etc. REFERENCE: 1. Update on Recommendations for Use of Herpes Zoster Vaccine:
https://www.cdc.gov/mmwr/preview/mmwrhtml/mm6333a3.htm; accessed 11 March 2021. 2. Kawai K, et al. BMP Open 2014;4:e004833 3. Marra F et al. Open Forum Infect Dis 2020;7:ofaa005
Incidence of HZ stratified by age2
0.5
Series1
Depression (14)
Asthma (N=12)
Diabetes mellitus (32)
Chronic kidney disease (18)
Cardiovascular disease (16)
COPD (12)
Psychological stress (8)
Physical trauma (6)
Pooled risk ratios of HZ according to key risk
factors (number of studies included in the meta-
analysis)3
*
Pooled risk ratio (95% CI)
Increased risk
Reduced risk
This graph has been independently created by GSK from data first published in Open Forum Infectious Disease1
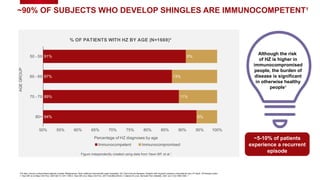
~90% OF SUBJECTS WHO DEVELOP SHINGLES ARE IMMUNOCOMPETENT1
80+
70 - 79
60 - 69
50 - 59
50% 55% 60% 65% 70% 75% 80% 85% 90% 95% 100%
94%
89%
87%
91%
6%
11%
13%
9%
% OF PATIENTS WITH HZ BY AGE (N=1669)*
Immunocompetent Immunocompromised
Percentage of HZ diagnoses by age
AGE
GROUP
Figure independently created using data from Yawn BP, et al.1
Although the risk
of HZ is higher in
immunocompromised
people, the burden of
disease is significant
in otherwise healthy
people1
~5-10% of patients
experience a recurrent
episode
*US data. Immuno compromised patients included: Malignancies, Stem cell/bone marrow/solid organ transplant, HIV, Auto-immune diseases, Subjects with long-term systemic corticosteroid use (>5 mg/d). HZ=herpes zoster.
1. Yawn BP, et al. Mayo Clin Proc. 2007;82(11):1341-1349 2. Yawn BP, et al. Mayo Clin Proc. 2011 Feb;86(2):88-93. 3. Batram M, et al. Dermatol Ther (Heidelb). 2021 Jun;11(3):1009-1026. 1
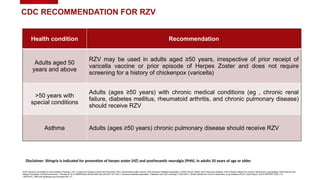
CDC RECOMMENDATION FOR RZV
Health condition Recommendation
Adults aged 50
years and above
RZV may be used in adults aged ≥50 years, irrespective of prior receipt of
varicella vaccine or prior episode of Herpes Zoster and does not require
screening for a history of chickenpox (varicella)
>50 years with
special conditions
Adults (ages ≥50 years) with chronic medical conditions (eg , chronic renal
failure, diabetes mellitus, rheumatoid arthritis, and chronic pulmonary disease)
should receive RZV
Asthma Adults (ages ≥50 years) chronic pulmonary disease should receive RZV
Disclaimer: Shingrix is indicated for prevention of herpes zoster (HZ) and postherpetic neuralgia (PHN), in adults 50 years of age or older.
ACIP, Advisory Committee on Immunization Practices; CDC, Centers for Disease Control and Prevention; RZV, recombinant zoster vaccine, ADA American Diabetes Association, COPD Chronic Obstru ctive Pulmonary Disease, GOLD Global Initiative for Chronic Obstructive Lung Disease, AAFA Asthma and
Allergy Foundation of America Sources: 1.Dooling KL et al. MMWR Morb Mortal Wkly Rep 2018;67:103 108; 2. American Diabetes Association. Diabetes Care 2021;44(Suppl 1):S40 S52 3..Global Initiative for Chronic Obstructive Lung Disease (GOLD). 2022 Report. GOLD REPORT 2022 v1.0
12Nov2021_WMV.pdf (goldcopd.org) Accessed Nov ‘21.
SHINGRIX IS INDICATED FOR PREVENTION OF HERPES ZOSTER (HZ) &
POST-HERPETIC NEURALGIA (PHN), IN ADULTS AGED 50+ YEARS
SHINGRIX is supplied in 2 vials for reconstitution: 1 vial of antigen should be reconstituted
with 1 accompanying vial of adjuvant suspension.1
SHINGRIX is for intramuscular injection only.1
SHINGRIX is given as a 2-dose series: Primary vaccination Schedule consists of initial dose
followed by a second dose 2 months later. If flexibility in the vaccination schedule is necessary,
second dose can be administered between 2 and 6 months after the first dose1
Note: The vial stoppers are not made with natural rubber latex. Reference: 1 GSK India Shingrix PI SNX/PI/IN/2022/03 dated 04-Jul-2022
SHINGRIX is not indicated for the prevention of primary
varicella infection (chickenpox)1
MENINGOCOCCAL DISEASE
Meningococcal disease is a devastating infection, an important cause of
meningitis, sepsis, and, less often, pneumonia, pericarditis, and septic arthritis
Neisseria meningitidis tends to strike young, previously well individuals and
can progress to death in a matter of hours
Survivors may have serious long-term sequelae (eg, loss of limbs, hearing
loss, neurocognitive dysfunction)
Polysaccharide vaccine: Quadrivalent (Men A, C, Y, W-135)
The vaccine does not induce herd immunity and has no effect on
nasopharyngeal carriage
INDICATION
• Anatomical or functional asplenia (including sickle cell disease), HIV
infection, persistent complement deficiency or on complement inhibitors –
2 doses at minimum 8 weeks apart, then booster every 5 years
• Travelers to endemic area, Hajj pilgrims – 1 dose
• Drug abusers, Male homosexuals, CLD – 1 dose
• Lab workers, Microbiologists – 1 dose, then booster every 5 years, if risk
remains
Recommended up to the age of 55 years
HAEMOPHILUS
INFLUENZAE
INFECTION
INDICATION
Prevention of invasive disease caused by Haemophilus influenzae type
b (Hib):
• Anatomical or Functional asplenia (including sickle cell disease) – 1 dose
• If elective splenectomy, preferably at least 14 days before splenectomy
• Adults at high risk – Immunocompromised, CSF Leak, Diabetics,
pregnancy, cancer, chemotherapy, Alcoholism – 1 dose
• Hematopoietic stem cell transplant (HSCT) – 3 dose series 4 weeks part,
starting 6-12 months after successful transplant
HUMAN PAPILLOMA VIRUS
INFECTION
HUMAN PAPILLOMA VIRUS
• The high-risk HPV genotypes 16 and 18 cause approximately 70 percent
of all cervical cancers worldwide
• Types 31, 33, 45, 52, and 58 cause an additional 20 percent
• HPV types 16 and 18 also cause nearly 90 percent of anal cancers and a
significant proportion of oropharyngeal cancer, vulvar and vaginal cancer,
and penile cancer
• HPV types 6 and 11 cause approximately 90 percent of anogenital wart
• Recombinant vaccine –
• Bivalent (Cervarix) - containing HPV strains 16 & 18
• Quadrivalent (Gardasil, Cervavac) – containing HPV strains 6, 11, 16, 18
INDICATION
Recommended for Females <26 years of age and before first sexual
encounter –
• Age 15 years or older at initial vaccination: 3-dose series at 0, 1–2
months, 6 months
• Age 9–14 years at initial vaccination and received 1 dose or 2 doses
less than 5 months apart: 1 additional dose
• Age 9–14 years at initial vaccination and received 2 doses at least 5
months apart: HPV vaccination series complete, no additional dose
needed
• Adults aged 27-45 years: Based on shared clinical decision, 2-3 doses
• Immunocompromising conditions, including HIV infection: 3-dose
series, even for those who initiate vaccination at age 9-14 years
VARICELLA
AICOG 2023 Koushik Lahiri
VARICELLA VACCINE
• Contains live attenuated VZV (Oka strain)
• Dose: 2 doses of 0.5ml in deltoid area subcutaneously at 4-8 weeks
interval
• Indication:
• All adults who have never had chickenpox

• Especially important to susceptible persons like – healthcare workers,
family contacts of immunocompromised persons, high risk of exposure

(e.g. teachers, daycare employees, military personnel and international
travelers)
• At risk population – DM, CLD, CKD, Heart or Lung disease, Asplenia
AICOG 2023 Koushik Lahiri
CONTRAINDICATION
•Pregnancy
•Pts on high dose systemic immunosuppressive therapy
including oral corticosteroids >2 mg/kg of body weight or a total
of more than 20 mg/day of prednisone or its equivalent for >2
weeks
•HIV+ adult with CD4+ count <200 cells/μL
•Persons with a family history of congenital or hereditary
immunodeficiency in first-degree relatives
OTHER VACCINES
AICOG 2023 Koushik Lahiri
CHOLERA VACCINE
• Routine administration not recommended
• Indication:
• Travellers
• Potential exposure to cholera patients or contaminated water/food
• During natural calamity
• During outbreak
• 2 doses – at least 2 weeks apart
AICOG 2023 Koushik Lahiri
TYPHOID VACCINE
• Typhoid conjugated vaccine is preferred
• Indication:
• Professional food handlers
• Travelers to endemic areas
• Unvaccinated adults 18-45 years in endemic areas
• During outbreaks
• Dose: TCV 1 dose – may be given a booster after 3 years in high-risk
cases
INDIAN CONSENSUS
RECOMMENDATIONS
AICOG 2023 Koushik Lahiri
UPCOMING VACCINES
• Dengue Vaccine: Phase I-II (Serum Institute of India) & Phase III (Panacea)
• HIV Vaccine: Phase I (Moderna, HOOKIPA Pharma, AELIX Therapeutics)
• Malaria Vaccine: S|AS01 – completed phase 3 trial – ongoing pilot
administration
• Tuberculosis Vaccine: M72|AS01E – Phase 2b
• Leprosy Vaccine: MiP vaccine
• Others:
• Zika virus
• Noro virus
• Gr B Streptococcus
• Staph Aureus
• Bacterial Lysate
• Personalized Vaccine for cancer: Pancreatic Ductal Adenocarcinoma
AICOG 2023 Koushik Lahiri
THANK YOU
Any Questions?
 bodhi.doc@gmail.com
 9830636315