ADULT HEALTH NURSING I
UNIT I
Topics 1 – 7
© 2026 Dr. Sudhadevi Sadanandan
Question 1
Evolution and Trends of Adult Health Nursing
(Medical-Surgical Nursing)
Introduction
• Adult Health Nursing, also known as Medical-Surgical Nursing, is
the largest specialty in nursing practice.
• It provides comprehensive care to adult patients with acute and
chronic medical and surgical disorders.
• It focuses on health promotion, disease prevention, diagnosis,
treatment, rehabilitation, and palliative care.
• It is practiced in medical wards, surgical wards, intensive care units,
emergency departments, operation theatres, rehabilitation centres,
and community settings.
Definition
Adult Health Nursing (Medical-Surgical Nursing) is a specialized
branch of nursing that provides preventive, promotive, curative,
rehabilitative, and palliative care to adult patients with medical and
surgical disorders through evidence-based nursing practice.
Evolution of Adult Health Nursing (Medical-Surgical Nursing)
1. Ancient Era
• In the ancient era, diseases were believed to be caused by evil spirits
and supernatural powers.
• Family members, priests, and traditional healers cared for sick
people.
• Herbal medicines, prayers, and rituals were commonly used for
treatment.
• Scientific knowledge regarding diseases was very limited.
© 2026 Dr. Sudhadevi Sadanandan
2. Medieval Era
• During the medieval era, religious institutions and monasteries cared
for sick people.
• Nursing care was mainly provided by nuns and volunteers.
• Hospitals gradually developed as centres for patient care.
• Nursing was considered a charitable service rather than a profession.
• There was no formal nursing education during this period.
3. Modern Era
• The modern era of nursing began with Florence Nightingale (1820–
1910), who is known as the Founder of Modern Nursing.
• During the Crimean War (1854–1856), she introduced scientific
nursing principles through her Environmental Theory.
• She emphasized pure air, pure water, efficient drainage, cleanliness,
adequate light, proper ventilation, hand hygiene, nutrition,
observation, and documentation.
• She used statistical methods to improve the quality of patient care.
• In 1860, she established the Nightingale Training School at St.
Thomas' Hospital, London, the first professional nursing school.
• She established nursing as a scientific profession and improved
hospital administration and patient safety.
Development of Nursing in India
Pre-Independence
• In 1871, the first formal nursing school was started at Government
General Hospital, Madras (Chennai).
• In 1888, Military Nursing Service was started at Secunderabad.
Post-Independence
• In 1946, Christian Medical College, Vellore, started India's first
degree programme in nursing.
© 2026 Dr. Sudhadevi Sadanandan
• Rajkumari Amrit Kaur (RAK) College of Nursing, New Delhi, was
also established in 1946 and introduced the B.Sc. (Hons.) Nursing
programme.
• The Indian Nursing Council Act, 1947, provided for the constitution
of the Indian Nursing Council and uniform standards of nursing
education.
• In 1949, the Indian Nursing Council (INC) was constituted to
regulate nursing education and practice in India.
4. Contemporary Era
• Adult Health Nursing has become a highly specialized field of
nursing.
• Nurses provide care in medical wards, surgical wards, intensive care
units, emergency departments, operation theatres, dialysis units,
oncology units, burns units, rehabilitation centres, and home
healthcare.
• Adult Health Nursing emphasizes multidisciplinary teamwork,
patient safety, and evidence-based clinical decision-making.
• The nursing process (Assessment, Diagnosis, Planning,
Implementation, and Evaluation) became firmly established as the
foundation of professional nursing practice in the contemporary era.
• Modern nursing combines scientific knowledge, advanced
technology, research, critical thinking, communication skills, and
compassionate patient care.
Current Trends in Adult Health Nursing
1. Evidence-Based Practice (EBP)
• Evidence-based practice integrates the best research evidence,
clinical expertise, and patient preferences.
• It improves patient outcomes and enhances the quality of nursing
care.
© 2026 Dr. Sudhadevi Sadanandan
2. Technological Advancement
• Modern nurses use advanced equipment such as ventilators, cardiac
monitors, infusion pumps, dialysis machines, and Electronic Health
Records (EHR).
• Technology has improved patient monitoring, diagnosis, and
treatment.
3. Patient and Family-Centred Care
• Patients and family members actively participate in planning and
decision-making regarding healthcare.
• Individualized care improves patient satisfaction and treatment
outcomes.
4. Specialized Nursing
• Nursing has developed into specialties such as Critical Care Nursing,
Cardiac Nursing, Oncology Nursing, Emergency Nursing,
Nephrology Nursing, Neuroscience Nursing, and Infection Control
Nursing.
• Specialized nurses receive advanced education and training in their
respective fields.
5. Quality Assurance and Accreditation
• Hospitals maintain quality standards through nursing audits and
quality assurance programmes.
• Many hospitals follow NABH and JCI accreditation standards to
improve patient safety and quality of healthcare.
6. Infection Prevention and Patient Safety
• Nurses follow standard precautions, hand hygiene, sterile
techniques, biomedical waste management, and patient safety
protocols to prevent hospital-acquired infections.
7. Tele-nursing and Digital Health
• Tele-nursing and telemedicine enable nurses to provide healthcare
services through digital technology.
© 2026 Dr. Sudhadevi Sadanandan
• Remote patient monitoring and online consultations improve
healthcare accessibility, especially in rural and remote areas.
8. Artificial Intelligence (AI) and Digital Documentation
• Artificial Intelligence assists nurses in clinical decision-making,
patient monitoring, and documentation.
• Electronic Health Records (EHR) improve communication,
accuracy, and continuity of patient care.
9. Holistic and Palliative Care
• Holistic nursing addresses the physical, psychological, social,
cultural, and spiritual needs of patients.
• Palliative care focuses on pain relief, symptom management,
emotional support, and improving the quality of life of patients with
life-limiting illnesses.
Conclusion
• Adult Health Nursing has evolved from simple home-based
caregiving to a highly specialized scientific profession.
• Modern nurses integrate evidence-based practice, advanced
technology, research, and compassionate care to provide safe,
holistic, and patient-centred healthcare.
• Nurses play a vital role in promoting health, preventing disease,
restoring health, and providing compassionate end-of-life care.
• Continuous professional development and adherence to national and
international standards help improve patient outcomes and the
quality of healthcare.
Question 2
International Classification of Diseases (ICD)
© 2026 Dr. Sudhadevi Sadanandan
1. Introduction
• Diseases, injuries, and causes of death differ across countries and
populations.
• A standardized system is required to record and classify these health
conditions accurately.
• The World Health Organization (WHO) developed the International
Classification of Diseases (ICD) for this purpose.
• ICD assigns alphanumeric codes to classified diseases and related
health conditions.
• It enables uniform recording, reporting, and comparison of health
information worldwide.
• It ensures accurate documentation, global research, disease
surveillance, and effective healthcare planning.
2. Definition
International Classification of Diseases (ICD) is a standardized medical
classification system developed by the World Health Organization
(WHO) that assigns unique alphanumeric codes to diseases, disorders,
injuries, signs, symptoms, and causes of death worldwide.
3. History and Key Milestones
• 1893: Jacques Bertillon introduced the first International
Classification of Causes of Death.
• 1948: The World Health Organization (WHO) assumed
responsibility for revising and publishing the ICD.
• 2019: The World Health Assembly (WHA) adopted ICD-11.
• 1 January 2022: ICD-11 is the latest revision and came into effect
for international health reporting on this date.
4. Objectives of ICD
• To provide a uniform system for classifying diseases and health
conditions.
© 2026 Dr. Sudhadevi Sadanandan
• To maintain accurate national and international health records.
• To collect morbidity (illness) and mortality (death) statistics.
• To compare disease patterns among different countries.
• To support disease surveillance, outbreak control, and public health
programmes.
• To assist in healthcare planning and policy development.
• To promote medical education and research.
• To facilitate health insurance claims and reimbursement.
5. Key Features of ICD
• ICD assigns alphanumeric codes to classified diseases and health
conditions.
• ICD provides a common language for healthcare professionals
worldwide.
• ICD follows internationally accepted classification standards.
• ICD is revised periodically by WHO to include advances in medical
science and newly emerging diseases.
• ICD improves the accuracy and consistency of health records.
• ICD facilitates electronic health records (EHR) and digital health
information systems.
6. Applications and Uses of ICD
A. In Hospitals
• ICD improves clinical documentation and medical record
management.
• ICD is used for disease coding and discharge summaries.
• ICD supports hospital statistics and medical audits.
B. In Public Health
• ICD helps monitor disease outbreaks and epidemics.
© 2026 Dr. Sudhadevi Sadanandan
• ICD assists in planning national immunization and public health
programmes.
• ICD supports disease surveillance and control measures.
C. In Medical Research
• ICD provides reliable epidemiological data for research.
• ICD helps compare disease trends at national and international
levels.
• ICD supports evidence-based healthcare planning.
D. In Health Insurance
• ICD standardizes disease coding for insurance claims.
• ICD facilitates accurate medical billing and reimbursement.
E. In Health Policy
• ICD helps governments measure disease burden.
• ICD assists in allocating healthcare resources effectively.
• ICD supports the development of national health policies.
7. Role of the Nurse in ICD
• The nurse documents patient symptoms, diagnoses, and nursing care
accurately and completely.
• The nurse maintains clear nursing records and discharge summaries
to support correct ICD coding.
• The nurse promptly reports notifiable diseases according to hospital
policy.
• The nurse maintains confidentiality of patient records according to
hospital policy and legal guidelines.
• The nurse assists the healthcare team by ensuring accurate and
complete clinical documentation.
• The nurse ensures timely and accurate recording of patient
information to improve the quality of health records.
© 2026 Dr. Sudhadevi Sadanandan
• The nurse collaborates with the healthcare team to ensure accurate
disease coding and quality patient care.
8. Advantages of ICD
• ICD ensures consistent and standardized disease documentation
worldwide.
• ICD strengthens disease surveillance and public health programmes.
• ICD improves the accuracy of health statistics.
• ICD promotes evidence-based medical research.
• ICD supports healthcare planning and resource allocation.
• ICD improves communication among healthcare professionals.
9. Limitations of ICD
• Accurate coding requires proper training.
• Incomplete or incorrect clinical documentation may result in coding
errors.
• Regular WHO updates require continuous learning by healthcare
professionals.
• Some complex diseases require detailed classification.
• ICD coding may be time-consuming for complex clinical conditions.
Conclusion
• The International Classification of Diseases (ICD) is the global
standard for disease classification developed by the World Health
Organization (WHO).
• It provides standardized coding for diseases, injuries, and causes of
death.
• ICD plays an important role in hospital documentation, research,
disease surveillance, health insurance, and healthcare planning.
• ICD improves communication among healthcare professionals and
supports quality healthcare delivery worldwide.
© 2026 Dr. Sudhadevi Sadanandan
• Accurate clinical documentation by nurses is essential for correct
ICD coding and contributes to safe, effective, and quality patient
care.
Question 3
Roles and Responsibilities of the Nurse in
Medical and Surgical Settings (OPD, IPD & ICU)
1. Introduction
• Medical-Surgical Nurses provide comprehensive nursing care to
adult patients suffering from medical and surgical illnesses.
• They work in various hospital units, including the Outpatient
Department (OPD), Inpatient Department (IPD), and Intensive Care
Unit (ICU).
• Their roles include health promotion, disease prevention, nursing
assessment, nursing diagnosis, implementation of prescribed
treatment, rehabilitation, and palliative care.
• They deliver patient-centred, evidence-based, and safe nursing care.
2. Definition
A Medical-Surgical Nurse is a registered nurse who provides preventive,
promotive, curative, rehabilitative, and palliative care to adult patients
with medical and surgical conditions across different healthcare settings.
3. Difference Between Roles and Responsibilities
• Roles: General professional functions and titles a nurse performs in
every healthcare setting (e.g., Care Provider, Educator).
• Responsibilities: Specific daily tasks and duties a nurse carries out
based on their work unit—OPD, IPD, or ICU.
© 2026 Dr. Sudhadevi Sadanandan
4. General Roles of a Medical-Surgical Nurse
1. Care Provider
• Provides comprehensive physical and emotional care.
• Assesses, plans, implements, and evaluates nursing care.
• Provides holistic, individualized, and evidence-based nursing care.
2. Educator
• Educates patients and families about disease, treatment, diet,
exercise, and home care.
• Promotes healthy lifestyle practices.
3. Advocate
• Protects patients' rights, dignity, privacy, and confidentiality.
• The nurse verifies that informed consent has been obtained before
the procedure and witnesses the patient's signature according to
hospital policy.
4. Communicator
• Communicates effectively with patients, relatives, and the healthcare
team.
• Maintains accurate documentation and reports.
5. Collaborator
• Coordinates care with doctors, physiotherapists, dietitians,
pharmacists, and other healthcare professionals.
6. Leader and Manager
• Supervises nursing staff and students.
• Manages ward activities, equipment, and supplies.
7. Researcher
• Applies evidence-based nursing practice.
• Participates in research and continuing professional education.
© 2026 Dr. Sudhadevi Sadanandan
5. Responsibilities of the Nurse in OPD (Outpatient Department)
A. Before Patient Care
• Maintains a clean and organized OPD.
• Prepares equipment, instruments, and emergency trolley.
• Checks medicines and dressing supplies.
• Ensures all equipment is functioning properly.
B. During Patient Care
Assessment
• Receives and registers patients.
• Collects medical history.
• Assesses and records vital signs.
• Assesses pain and chief complaints of the patient.
Procedures
• Assists the doctor during examinations and minor procedures.
• Performs wound dressing, suture removal, and catheter care.
• Maintains medical and surgical asepsis.
Medication Administration
• Administers prescribed medications, injections, and vaccines safely.
• Observes for adverse reactions.
C. After Patient Care
• Documents all procedures accurately.
• Provides health education regarding medicines, diet, exercise, and
follow-up.
• Schedules follow-up appointments and referrals when required.
• Disposes biomedical waste according to hospital policy.
6. Responsibilities of the Nurse in IPD (Inpatient Department)
A. Admission and Assessment
• Receives and admits patients.
© 2026 Dr. Sudhadevi Sadanandan
• Verifies admission records.
• Performs complete nursing assessment.
• Orients patients to the ward.
B. During Hospital Stay
• Assists with hygiene and comfort.
• Administers medications and IV fluids.
• Monitors vital signs regularly.
• Maintains intake and output records.
• Maintains fluid and electrolyte balance.
• Performs wound care, drain care, and catheter care.
• Provides preoperative and postoperative nursing care.
• Prevents falls and other patient safety incidents.
• Identifies complications and reports immediately.
C. Patient Education and Support
• Educates patients regarding disease management, diet, medication,
and home care.
• Provides emotional support.
D. Discharge Care
• Completes discharge documentation.
• Explains medications, diet, follow-up, and home care.
• Arranges referrals when required.
E. Administrative Responsibilities
• Maintains nursing records.
• Supervises junior staff and students.
• Manages ward inventory and equipment.
• Maintains ethics, privacy, and confidentiality.
© 2026 Dr. Sudhadevi Sadanandan
7. Responsibilities of the Nurse in ICU (Intensive Care Unit)
A. Admission
• Receives critically ill patients safely.
• Assesses ABC (Airway, Breathing, Circulation) immediately.
• Assists in establishing and maintaining monitors, oxygen therapy,
and intravenous access.
B. Continuous Monitoring
• Continuously monitors vital signs.
• Monitors ECG, SpO₂ (Peripheral Oxygen Saturation), CVP (Central
Venous Pressure), ABG (Arterial Blood Gas Analysis), urine output,
and neurological status.
• Maintains hourly intake and output records and closely monitors
fluid balance.
• Detects emergencies and initiates prompt nursing interventions.
C. Therapeutic Care
• Administers emergency medications and IV infusions accurately.
• Operates ventilators and infusion pumps.
• Performs airway suctioning, tracheostomy care, and sterile wound
care.
• Assists in emergency procedures such as CPR when required.
• Follows strict infection prevention and control measures.
D. Patient Safety and Hygiene
• The nurse repositions the patient at regular intervals according to the
patient's condition, pressure-injury risk, and hospital protocol.
• Provides oral care, eye care, and bed bath.
• Prevents pressure ulcers and hospital-acquired infections.
E. Family Support
• Provides regular updates to the family as per hospital policy and the
treating physician's instructions.
© 2026 Dr. Sudhadevi Sadanandan
• Offers emotional support and counselling.
• Coordinates communication with the healthcare team.
F. Administrative Responsibilities and Transfer
• Maintains ICU records and flow charts.
• Ensures proper documentation of all nursing interventions and
medications administered.
• Checks emergency crash cart and defibrillator daily.
• Stabilizes the patient before transfer.
• Gives complete bedside handover to the receiving nurse.
8. Conclusion
• Medical-Surgical Nurses play an essential role in providing safe,
holistic, evidence-based, and patient-centred care in OPD, IPD, and
ICU settings.
• Their responsibilities include assessment, treatment, medication
administration, patient education, infection prevention,
documentation, communication, and coordination with the
healthcare team.
• Effective nursing care improves patient recovery, prevents
complications, enhances patient safety, and promotes quality
healthcare outcomes.
• Medical-Surgical Nurses contribute significantly to patient safety,
quality improvement, and multidisciplinary healthcare delivery.
Question 4
Medical and Surgical Asepsis
© 2026 Dr. Sudhadevi Sadanandan
1. Introduction
• Infection is one of the major causes of illness and death among
hospitalized patients.
• Medical and Surgical Asepsis are important measures used to
prevent the spread of infection.
• Nurses play a vital role in maintaining aseptic techniques during
patient care and invasive procedures.
• Proper aseptic practices protect patients, healthcare workers, and the
hospital environment.
2. Definition
• Asepsis refers to practices that prevent contact with or
contamination by microorganisms.
• Medical Asepsis is the practice of reducing the number and spread
of microorganisms by using clean techniques.
• Surgical Asepsis is the use of sterile techniques to prevent
contamination and maintain an area or object free from all
microorganisms, including bacterial spores.
3. Objectives of Asepsis
• To prevent hospital-acquired (nosocomial) infections.
• To prevent the spread of microorganisms.
• To protect patients and healthcare workers from infection.
• To promote wound healing.
• To maintain a safe and clean healthcare environment.
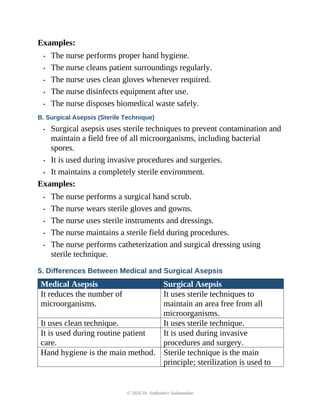
4. Types of Asepsis
A. Medical Asepsis (Clean Technique)
• Medical asepsis reduces the number and spread of microorganisms.
• It is used during routine nursing care.
• It does not destroy all microorganisms.
© 2026 Dr. Sudhadevi Sadanandan
Examples:
• The nurse performs proper hand hygiene.
• The nurse cleans patient surroundings regularly.
• The nurse uses clean gloves whenever required.
• The nurse disinfects equipment after use.
• The nurse disposes biomedical waste safely.
B. Surgical Asepsis (Sterile Technique)
• Surgical asepsis uses sterile techniques to prevent contamination and
maintain a field free of all microorganisms, including bacterial
spores.
• It is used during invasive procedures and surgeries.
• It maintains a completely sterile environment.
Examples:
• The nurse performs a surgical hand scrub.
• The nurse wears sterile gloves and gowns.
• The nurse uses sterile instruments and dressings.
• The nurse maintains a sterile field during procedures.
• The nurse performs catheterization and surgical dressing using
sterile technique.
5. Differences Between Medical and Surgical Asepsis
Medical Asepsis Surgical Asepsis
It reduces the number of
microorganisms.
It uses sterile techniques to
maintain an area free from all
microorganisms.
It uses clean technique. It uses sterile technique.
It is used during routine patient
care.
It is used during invasive
procedures and surgery.
Hand hygiene is the main method. Sterile technique is the main
principle; sterilization is used to
© 2026 Dr. Sudhadevi Sadanandan
prepare sterile articles.
It is used for routine and lower-
risk patient-care activities.
It is required for high-risk
procedures.
6. Principles of Medical and Surgical Asepsis
• The nurse performs hand hygiene before and after every procedure.
• The nurse wears appropriate Personal Protective Equipment (PPE).
• Sterile items should touch only other sterile items.
• The nurse never touches a sterile field with unsterile hands.
• The sterile field should always remain above waist level and within
the nurse's vision.
• Wet, torn, or expired sterile packs should not be used.
• The nurse avoids talking, coughing, or sneezing over the sterile
field.
• Contaminated materials should be discarded immediately.
• Biomedical waste should be disposed of according to hospital
policy.
7. Methods of Maintaining Asepsis
Hand Hygiene
• Hand washing with soap and water removes dirt and
microorganisms.
• Alcohol-based hand rub is used when hands are not visibly soiled.
Personal Protective Equipment (PPE)
• Gloves protect the hands from contamination.
• Masks protect the nose and mouth from microorganisms.
• Gowns protect clothing and skin.
• Goggles and face shields protect the eyes and face from splashes.
© 2026 Dr. Sudhadevi Sadanandan
Sterilization
• Sterilization destroys all microorganisms, including spores.
• Common methods include autoclaving, dry heat, gas sterilization,
and radiation.
Disinfection
• Disinfection destroys most disease-causing microorganisms but may
not destroy bacterial spores.
• Common disinfectants include alcohol, sodium hypochlorite, and
glutaraldehyde.
Cleaning
• Cleaning removes dirt, blood, and organic matter from equipment
and surfaces.
• Cleaning should always be done before disinfection or sterilization.
8. Nursing Responsibilities
• The nurse performs proper hand hygiene before and after patient
care.
• The nurse follows standard precautions during all procedures.
• The nurse maintains sterile technique during invasive procedures.
• The nurse uses sterile equipment and sterile dressings whenever
required.
• The nurse observes patients for signs of infection.
• The nurse educates patients and relatives about infection prevention.
• The nurse disposes biomedical waste according to hospital
guidelines.
• The nurse reports hospital-acquired infections promptly.
• The nurse maintains accurate documentation of nursing procedures.
9. Advantages of Aseptic Technique
• Aseptic technique prevents infection.
© 2026 Dr. Sudhadevi Sadanandan
• Aseptic technique promotes faster wound healing.
• Aseptic technique reduces hospital-acquired infections.
• Aseptic technique protects patients and healthcare workers.
• Aseptic technique improves patient safety.
• Aseptic technique improves the quality of healthcare services.
Conclusion
• Medical and Surgical Asepsis are essential components of nursing
practice.
• Medical asepsis reduces the spread of microorganisms, whereas
surgical asepsis uses sterile techniques to maintain a sterile
environment during invasive procedures.
• Proper aseptic techniques help prevent infection, promote wound
healing, protect patients and healthcare workers, and improve the
quality of nursing care.
Question 5
INFLAMMATION
1. Introduction
• Inflammation is the body's natural protective response to injury,
infection, or tissue damage.
• It helps remove harmful microorganisms and damaged tissue.
• It initiates the healing process and restores normal tissue function.
• Although inflammation is beneficial, excessive or prolonged
inflammation can damage healthy tissues.
© 2026 Dr. Sudhadevi Sadanandan
2. Definition
Inflammation is the protective response of vascular tissues to injury,
infection, or irritation that aims to destroy harmful agents, remove
damaged tissue, and promote healing.
3. Protective Functions of Inflammation
• Inflammation destroys harmful microorganisms.
• Inflammation prevents the spread of infection.
• Inflammation removes dead and damaged tissue.
• Inflammation initiates tissue repair.
• Inflammation may help restore tissue function, although severe or
prolonged inflammation can result in fibrosis or permanent loss of
function.
4. Causes (Etiology)
A. Physical Causes
• Trauma causes injury to body tissues.
• Burns damage the skin and underlying tissues.
• Excessive heat can injure body tissues.
• Extreme cold can damage tissues.
• Radiation can cause tissue injury and inflammation.
B. Chemical Causes
• Acids can damage body tissues.
• Alkalis can cause tissue destruction.
• Toxic chemicals can produce inflammatory reactions.
C. Biological Causes
• Bacteria can cause infection and inflammation.
• Viruses can trigger inflammatory responses.
• Fungi can produce inflammatory diseases.
• Parasites can invade tissues and cause inflammation.
© 2026 Dr. Sudhadevi Sadanandan
D. Mechanical Causes
• Cuts can injure tissues and initiate inflammation.
• Fractures can produce inflammation at the injury site.
• Pressure injuries can damage tissues and initiate inflammation.
E. Allergic Causes
• Drugs may produce allergic inflammatory reactions.
• Food allergens may trigger inflammation.
• Insect bites may cause localized inflammation.
F. Autoimmune Diseases
• Rheumatoid arthritis causes chronic inflammation of joints.
• Systemic lupus erythematosus (SLE) causes inflammation in
multiple organs.
5. Types of Inflammation
A. Acute Inflammation
• Acute inflammation develops rapidly after tissue injury.
• Acute inflammation usually lasts for a few hours or days.
• Acute inflammation is characterized by redness, heat, swelling, pain,
and loss of function.
• Acute inflammation usually resolves completely after healing.
Examples: Appendicitis, Cellulitis.
B. Chronic Inflammation
• Chronic inflammation develops gradually.
• Chronic inflammation usually lasts for months or years.
• Chronic inflammation causes continuous tissue destruction and
fibrosis.
• Healing and inflammation occur simultaneously during chronic
inflammation.
Examples: Tuberculosis, Rheumatoid arthritis.
© 2026 Dr. Sudhadevi Sadanandan
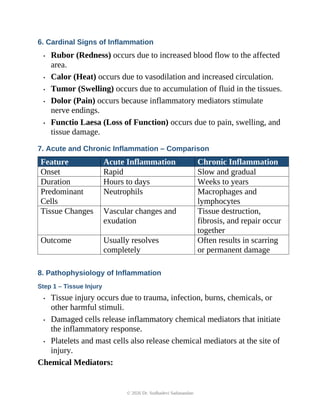
6. Cardinal Signs of Inflammation
• Rubor (Redness) occurs due to increased blood flow to the affected
area.
• Calor (Heat) occurs due to vasodilation and increased circulation.
• Tumor (Swelling) occurs due to accumulation of fluid in the tissues.
• Dolor (Pain) occurs because inflammatory mediators stimulate
nerve endings.
• Functio Laesa (Loss of Function) occurs due to pain, swelling, and
tissue damage.
7. Acute and Chronic Inflammation – Comparison
Feature Acute Inflammation Chronic Inflammation
Onset Rapid Slow and gradual
Duration Hours to days Weeks to years
Predominant
Cells
Neutrophils Macrophages and
lymphocytes
Tissue Changes Vascular changes and
exudation
Tissue destruction,
fibrosis, and repair occur
together
Outcome Usually resolves
completely
Often results in scarring
or permanent damage
8. Pathophysiology of Inflammation
Step 1 – Tissue Injury
• Tissue injury occurs due to trauma, infection, burns, chemicals, or
other harmful stimuli.
• Damaged cells release inflammatory chemical mediators that initiate
the inflammatory response.
• Platelets and mast cells also release chemical mediators at the site of
injury.
Chemical Mediators:
© 2026 Dr. Sudhadevi Sadanandan
• Histamine is released from mast cells and causes vasodilation and
increased capillary permeability.
• Serotonin is a vasoactive mediator released from platelets and
contributes to vascular changes during inflammation.
• Prostaglandins increase pain and vasodilation.
• Bradykinin increases pain and capillary permeability.
Step 2 – Vasodilation
• Blood vessels dilate immediately after tissue injury.
• Vasodilation increases blood flow to the affected area.
• Increased blood flow produces Rubor (Redness) and Calor (Heat).
Chemical Mediators:
• Histamine causes vasodilation.
• Nitric oxide relaxes blood vessels and increases blood flow.
• Prostaglandins enhance vasodilation.
Step 3 – Increased Capillary Permeability
• Capillary walls become more permeable due to the action of
inflammatory mediators.
• Plasma proteins and fluid leak into the surrounding tissues.
• White blood cells migrate towards the injured tissue.
• The accumulation of fluid produces Tumor (Swelling).
Chemical Mediators:
• Histamine increases capillary permeability.
• Bradykinin increases vascular permeability and causes pain.
• Leukotrienes increase vascular permeability and attract leukocytes.
Step 4 – Leukocyte Migration and Phagocytosis
• Neutrophils are the first white blood cells to reach the site of injury.
• Monocytes migrate into the tissues and differentiate into
macrophages.
© 2026 Dr. Sudhadevi Sadanandan
• Neutrophils and macrophages destroy microorganisms by
phagocytosis.
• Dead cells and microorganisms are removed from the injured tissue.
Chemical Mediators:
• Interleukin-1 (IL-1) stimulates the inflammatory response.
• Interleukin-6 (IL-6) promotes the acute-phase response.
• Tumor Necrosis Factor-alpha (TNF-α) activates inflammatory cells.
• Complement proteins (C3a and C5a) attract leukocytes and enhance
inflammation.
Step 5 – Resolution and Tissue Repair
• After the harmful agent is removed, inflammation gradually
subsides.
• Fibroblasts synthesize collagen and extracellular matrix to repair the
damaged tissue.
• New blood vessels are formed by angiogenesis.
• Granulation tissue develops at the site of injury.
• Tissue remodeling restores normal tissue structure and function.
Growth Factors:
• Platelet-Derived Growth Factor (PDGF) stimulates fibroblast
proliferation and tissue repair.
• Transforming Growth Factor-beta (TGF-β) promotes collagen
synthesis and wound healing.
• Vascular Endothelial Growth Factor (VEGF) stimulates the
formation of new blood vessels.
Flow Chart
Tissue Injury → Release of Chemical Mediators → Vasodilation → Increased Capillary Permeability → Leukocyte
Migration → Phagocytosis → Resolution of Inflammation → Tissue Repair and Healing
9. Clinical Manifestations
• Redness occurs due to increased blood flow to the affected area.
© 2026 Dr. Sudhadevi Sadanandan
• Heat occurs because of vasodilation and increased circulation.
• Swelling occurs due to accumulation of fluid in the tissues.
• Pain occurs because inflammatory mediators stimulate nerve
endings.
• Loss of function occurs due to pain, swelling, and tissue damage.
• Fever may occur in severe inflammation or infection.
• Tenderness is present over the inflamed area.
10. Systemic Manifestations
• Leukocytosis causes an increase in the white blood cell count.
• Acute-phase proteins such as C-Reactive Protein (CRP) and
fibrinogen become elevated.
• Malaise and generalized weakness may occur.
• Loss of appetite may develop.
• Tachycardia may occur in severe inflammation.
11. Diagnosis
• A complete health history should be collected.
• A thorough physical examination should be performed.
• Laboratory investigations help identify the cause and severity of
inflammation.
• Complete Blood Count (CBC) may show leukocytosis and helps
assess possible infection or systemic inflammation.
• Erythrocyte Sedimentation Rate (ESR) is measured to assess
inflammation.
• C-Reactive Protein (CRP) is estimated to determine the severity of
inflammation.
• Culture and sensitivity tests are performed when infection is
suspected.
• X-ray, CT scan, MRI, or Ultrasound may be performed when
indicated.
© 2026 Dr. Sudhadevi Sadanandan
12. Management
A. Medical Management
• Antibiotics are administered for bacterial infections.
• Anti-inflammatory drugs are used to reduce inflammation.
• Analgesics are administered to relieve pain.
• Corticosteroids are administered when indicated.
• Surgical drainage is performed if an abscess or pus is present.
B. General Management
• The affected part should be given adequate rest.
• Cold compresses may be applied during the early stage of
inflammation.
• The affected limb should be elevated to reduce swelling.
• Adequate nutrition and fluid intake should be maintained to promote
healing.
13. Nursing Management
• The nurse assesses redness, swelling, pain, heat, and loss of
function.
• The nurse monitors vital signs regularly.
• The nurse observes the patient for signs of infection.
• The nurse administers prescribed medications safely.
• The nurse maintains aseptic technique during wound care.
• The nurse provides adequate nutrition and hydration.
• The nurse promotes comfort and adequate rest.
• The nurse educates the patient regarding medications, wound care,
and follow-up.
• The nurse documents all nursing findings accurately.
14. Complications
• Inflammation may lead to abscess formation.
© 2026 Dr. Sudhadevi Sadanandan
• Inflammation may spread and cause cellulitis.
• Delayed wound healing may occur.
• Persistent inflammation may result in tissue destruction.
• Severe infection may lead to sepsis.
• Acute inflammation may progress to chronic inflammation.
• Permanent loss of function may occur in severe cases.
15. Prevention
• Personal hygiene should be maintained.
• Aseptic techniques should be followed during all procedures.
• Infections should be treated promptly.
• A balanced diet should be consumed to improve immunity.
• Injuries should be prevented whenever possible.
• Recommended vaccinations should be taken.
Conclusion
• Inflammation is a protective response that helps eliminate harmful
agents and initiate tissue repair.
• It is characterized by the five cardinal signs: Rubor (Redness), Calor
(Heat), Tumor (Swelling), Dolor (Pain), and Functio Laesa (Loss of
Function).
• Early assessment, appropriate treatment, and effective nursing care
help prevent complications and promote healing.
Question 6
INFECTION
© 2026 Dr. Sudhadevi Sadanandan
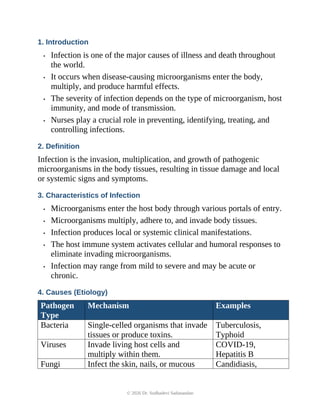
1. Introduction
• Infection is one of the major causes of illness and death throughout
the world.
• It occurs when disease-causing microorganisms enter the body,
multiply, and produce harmful effects.
• The severity of infection depends on the type of microorganism, host
immunity, and mode of transmission.
• Nurses play a crucial role in preventing, identifying, treating, and
controlling infections.
2. Definition
Infection is the invasion, multiplication, and growth of pathogenic
microorganisms in the body tissues, resulting in tissue damage and local
or systemic signs and symptoms.
3. Characteristics of Infection
• Microorganisms enter the host body through various portals of entry.
• Microorganisms multiply, adhere to, and invade body tissues.
• Infection produces local or systemic clinical manifestations.
• The host immune system activates cellular and humoral responses to
eliminate invading microorganisms.
• Infection may range from mild to severe and may be acute or
chronic.
4. Causes (Etiology)
Pathogen
Type
Mechanism Examples
Bacteria Single-celled organisms that invade
tissues or produce toxins.
Tuberculosis,
Typhoid
Viruses Invade living host cells and
multiply within them.
COVID-19,
Hepatitis B
Fungi Infect the skin, nails, or mucous Candidiasis,
© 2026 Dr. Sudhadevi Sadanandan
membranes. Ringworm
Parasites Live on or inside the human body
and obtain nourishment from the
host.
Malaria, Amoebiasis
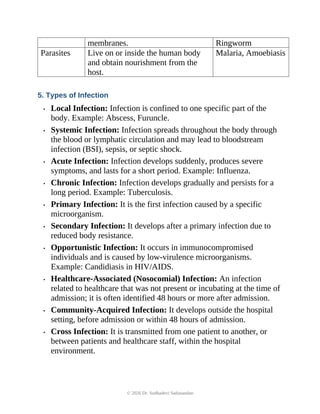
5. Types of Infection
• Local Infection: Infection is confined to one specific part of the
body. Example: Abscess, Furuncle.
• Systemic Infection: Infection spreads throughout the body through
the blood or lymphatic circulation and may lead to bloodstream
infection (BSI), sepsis, or septic shock.
• Acute Infection: Infection develops suddenly, produces severe
symptoms, and lasts for a short period. Example: Influenza.
• Chronic Infection: Infection develops gradually and persists for a
long period. Example: Tuberculosis.
• Primary Infection: It is the first infection caused by a specific
microorganism.
• Secondary Infection: It develops after a primary infection due to
reduced body resistance.
• Opportunistic Infection: It occurs in immunocompromised
individuals and is caused by low-virulence microorganisms.
Example: Candidiasis in HIV/AIDS.
• Healthcare-Associated (Nosocomial) Infection: An infection
related to healthcare that was not present or incubating at the time of
admission; it is often identified 48 hours or more after admission.
• Community-Acquired Infection: It develops outside the hospital
setting, before admission or within 48 hours of admission.
• Cross Infection: It is transmitted from one patient to another, or
between patients and healthcare staff, within the hospital
environment.
© 2026 Dr. Sudhadevi Sadanandan
• Iatrogenic Infection: It results directly from a medical or diagnostic
procedure, such as catheterization or surgery.
• Latent Infection: The microorganism remains dormant in the body
without producing active symptoms and may reactivate later.
Examples include tuberculosis and herpes-virus infections.
6. Chain of Infection
The chain of infection consists of six links:
• 1. Infectious Agent – The microorganism that causes disease.
• 2. Reservoir – The place where the microorganism lives and
multiplies.
• 3. Portal of Exit – The route through which the microorganism
leaves the reservoir.
• 4. Mode of Transmission – The method by which the microorganism
spreads.
• 5. Portal of Entry – The route through which the microorganism
enters the new host.
• 6. Susceptible Host – A person who is vulnerable to infection.
Breaking any one link in the chain helps prevent the spread of infection.
6A. Factors Affecting Host Susceptibility
• Extremes of age (infants and elderly) increase susceptibility to
infection.
• Poor nutritional status weakens the immune response.
• Immunocompromised states (HIV/AIDS, chemotherapy,
corticosteroid therapy) reduce resistance to infection.
• Chronic illnesses such as diabetes mellitus and renal disease increase
vulnerability.
• Stress and fatigue can lower immune function.
• Break in skin or mucous membrane integrity provides a portal of
entry for microorganisms.
© 2026 Dr. Sudhadevi Sadanandan
• Invasive devices such as catheters, IV lines, and ventilators increase
the risk of infection.
7. Modes of Transmission
• Direct Contact: Infection spreads through direct physical contact
with an infected person.
• Indirect Contact: Infection spreads through contaminated objects
(fomites), instruments, or equipment.
• Droplet Transmission: Infection spreads through respiratory
droplets produced during coughing, sneezing, or talking.
• Airborne Transmission: Infection spreads through tiny droplet
nuclei that remain suspended in the air.
• Vehicle Transmission: Infection spreads through contaminated
food, water, blood, or medications.
• Vector-Borne Transmission: Infection spreads through insects
such as mosquitoes, ticks, or fleas.
8. Pathophysiology of Infection
Step 1 – Entry of Microorganisms
Pathogenic microorganisms enter the body through the skin, respiratory
tract, gastrointestinal tract, genitourinary tract, or mucous membranes.
Step 2 – Colonization
Microorganisms adhere to body tissues and begin to multiply without
causing significant tissue damage initially.
Step 3 – Invasion and Multiplication
Microorganisms invade body tissues and release toxins or enzymes that
damage host cells.
Step 4 – Tissue Damage and Inflammatory Response
• Tissue injury stimulates the inflammatory response.
• Vasodilation and increased capillary permeability produce redness,
heat, swelling, and pain.
© 2026 Dr. Sudhadevi Sadanandan
• Chemical mediators such as histamine, prostaglandins, cytokines,
and complement proteins help produce inflammation and activate
the immune response.
Step 5 – Immune Response
• Neutrophils, macrophages, and lymphocytes migrate to the site of
infection.
• White blood cells destroy microorganisms through phagocytosis.
• Antibodies and cytokines help eliminate the infection.
• Inflammatory cytokines such as Interleukin-1 (IL-1), Interleukin-6
(IL-6), and Tumor Necrosis Factor-alpha (TNF-α) coordinate the
immune response and help eliminate microorganisms.
Step 6 – Outcome
• Effective immune response and treatment result in recovery and
tissue repair.
• Uncontrolled infection may lead to abscess formation, bloodstream
infection, septic shock, or multiple organ dysfunction.
Flow Chart
Entry of Microorganisms → Colonization → Invasion and Multiplication → Tissue Damage and Inflammatory
Response → Immune Response → Recovery or Complications
9. Clinical Manifestations
Local Manifestations
• Redness (Erythema) occurs due to vasodilation.
• Swelling (Edema) occurs due to increased capillary permeability.
• Heat (Warmth) occurs because of increased blood flow.
• Pain or tenderness occurs due to inflammatory mediators and
pressure on nerve endings.
• Pus or purulent discharge may be present at the site of infection.
Systemic Manifestations
• Fever (Pyrexia) and chills may occur.
© 2026 Dr. Sudhadevi Sadanandan
• Fatigue, malaise, and generalized weakness may develop.
• Loss of appetite (Anorexia) may occur.
• Leukocytosis (increased white blood cell count) may be present.
10. Diagnostic Evaluation
• A complete health history should be obtained.
• A thorough physical examination should be performed.
• Complete Blood Count (CBC) helps detect infection.
• Culture and Sensitivity (C&S) testing identifies the causative
microorganism and helps select an effective antimicrobial drug.
• Blood, urine, sputum, stool, or wound cultures may be collected as
indicated.
• Chest X-ray, Ultrasound, CT scan, or MRI may be performed to
identify the site of infection.
11. Treatment and Management
A. Medical Management
• Appropriate antibiotics, antivirals, antifungals, or antiparasitic drugs
are administered according to the causative organism.
• Intravenous fluids, antipyretics, and analgesics are provided as
supportive therapy.
B. General Management
• Adequate bed rest should be provided.
• A balanced diet rich in protein and vitamins and adequate fluid
intake should be maintained.
• Isolation precautions should be followed according to the mode of
transmission.
11A. Standard and Transmission-Based Precautions
Standard Precautions
• Hand hygiene is performed before and after every patient contact.
© 2026 Dr. Sudhadevi Sadanandan
• Personal protective equipment (gloves, gown, mask, eyewear) is
used based on anticipated exposure.
• Safe injection practices and safe handling of sharps are followed.
• Respiratory hygiene and cough etiquette are practiced.
• Contaminated equipment and surfaces are cleaned and disinfected
appropriately.
Transmission-Based Precautions
• Contact Precautions: Gloves and gown are worn; patient is placed
in a single room or cohorted; dedicated equipment is used. Examples
include uncontrolled draining wounds and certain multidrug-
resistant organisms when contact transmission is likely.
• Droplet Precautions: A surgical mask is worn within close range of
the patient; patient placed in a single room or maintained at a safe
distance. Example: Influenza, Pertussis.
• Airborne Precautions: An N95 respirator is worn; patient is placed
in a negative-pressure isolation room with the door closed. Example:
Tuberculosis, Measles, Chickenpox.
12. Nursing Management
• The nurse assesses local and systemic signs of infection.
• The nurse monitors vital signs regularly.
• The nurse administers prescribed antimicrobial drugs safely and on
time.
• The nurse collects specimens using aseptic technique before starting
antibiotics whenever possible.
• The nurse performs proper hand hygiene before and after patient
care.
• The nurse follows standard and transmission-based precautions.
• The nurse provides adequate nutrition, hydration, and rest.
© 2026 Dr. Sudhadevi Sadanandan
• The nurse educates the patient and family regarding personal
hygiene, cough etiquette, hand hygiene, and completion of the
prescribed antibiotic course.
• The nurse documents all nursing observations and the patient's
response to treatment accurately.
13. Complications
• Infection may cause localized tissue necrosis and abscess formation.
• Infection may spread into the bloodstream and cause bacteremia,
bloodstream infection, or sepsis.
• Severe infection may lead to septic shock.
• Multiple Organ Dysfunction Syndrome (MODS) may develop in
severe cases.
• Untreated infection may result in death.
14. Prevention
• Hand hygiene should be performed regularly.
• Standard precautions should be followed during all patient care.
• Sterile techniques should be maintained during invasive procedures.
• Immunization should be taken according to the recommended
schedule.
• Biomedical waste should be segregated and disposed of safely.
• Safe food, clean drinking water, and proper sanitation should be
maintained.
• Early diagnosis and prompt treatment help prevent the spread of
infection and its complications.
Conclusion
• Infection occurs when pathogenic microorganisms invade and
multiply within the body.
© 2026 Dr. Sudhadevi Sadanandan
• Early diagnosis, appropriate treatment, effective infection control
measures, and proper nursing care help prevent complications and
promote recovery.
• Nurses play a vital role in preventing the spread of infection and
ensuring safe, quality patient care.
Question 7
WOUND HEALING
1. Introduction
• Wound healing is a natural biological process that restores the
structure and function of damaged tissues.
• It begins immediately after tissue injury and continues until
complete healing or scar formation occurs.
• Successful wound healing depends on proper blood supply,
nutrition, infection control, and appropriate wound care.
• Nurses play an important role in promoting wound healing and
preventing complications.
2. Definition
Wound healing is the physiological process by which damaged tissues
are repaired through regeneration or replacement with scar tissue,
restoring tissue integrity and function.
3. Functions of Wound Healing
• Wound healing stops bleeding and prevents excessive blood loss.
• Wound healing protects the body from infection.
• Wound healing removes dead and damaged tissue.
• Wound healing restores the continuity and integrity of damaged
tissue.
© 2026 Dr. Sudhadevi Sadanandan
• Wound healing helps regain the normal structure and function of the
affected part.
4. Types of Wound Healing
A. Primary Intention (Primary Union)
• The wound edges are clean and closely approximated.
• There is minimal tissue loss.
• Healing occurs rapidly with minimal scar formation.
Examples: Surgical incision, clean sutured wound.
B. Secondary Intention (Secondary Union)
• The wound edges are not approximated.
• There is significant tissue loss.
• Healing occurs by granulation tissue formation, wound contraction,
and epithelialization.
• Scar formation is more extensive.
Examples: Pressure ulcer, infected wound, burn wound.
C. Tertiary Intention (Delayed Primary Closure)
• The wound is initially left open because of contamination or
infection.
• The wound is closed surgically after infection is controlled.
• Healing occurs with moderate scar formation.
Example: Contaminated traumatic wound.
5. Pathophysiology of Wound Healing
Step 1 – Tissue Injury
• Tissue injury occurs due to trauma, surgery, burns, pressure, or other
harmful causes.
• Blood vessels and surrounding tissues are damaged.
• Bleeding begins immediately after injury.
© 2026 Dr. Sudhadevi Sadanandan
Step 2 – Hemostasis (Hemostatic Phase)
• Immediate vasoconstriction occurs to reduce blood loss.
• Platelets adhere to the damaged blood vessel and form a platelet
plug.
• The coagulation cascade is activated.
• Fibrin is formed and stabilizes the blood clot.
• The blood clot seals the wound and provides a temporary framework
for healing.
Important Factors:
• Platelets gather at the site of injury and form a plug that helps stop
bleeding.
• Thrombin converts fibrinogen into fibrin, which helps stabilize the
clot.
• Fibrin forms a mesh-like network that strengthens and holds the
blood clot together.
• Clotting factors work together to activate the coagulation cascade
and promote clot formation.
Step 3 – Inflammation (Inflammatory Phase)
• Blood vessels dilate and increase blood flow to the injured tissue.
• Capillary permeability increases, allowing plasma proteins and white
blood cells to enter the wound.
• Neutrophils migrate first and destroy microorganisms by
phagocytosis.
• Monocytes migrate into the tissue and differentiate into
macrophages.
• Macrophages remove dead tissue and microorganisms.
• Macrophages release cytokines and growth factors that initiate tissue
repair.
Important Chemical Mediators:
© 2026 Dr. Sudhadevi Sadanandan
• Histamine increases vasodilation and capillary permeability at the
wound site.
• Prostaglandins contribute to pain and inflammation during the
healing process.
• Interleukin-1 (IL-1) stimulates the inflammatory response and
activates immune cells.
• Interleukin-6 (IL-6) promotes the acute-phase response and supports
tissue repair.
• Tumor Necrosis Factor-alpha (TNF-α) activates inflammatory cells
and strengthens the immune response.
Step 4 – Tissue Repair (Proliferative Phase)
• Fibroblasts migrate into the wound and synthesize collagen.
• Fibroblasts produce extracellular matrix to support tissue repair.
• New blood vessels develop through angiogenesis.
• Granulation tissue fills the wound defect.
• Epithelial cells migrate across the wound surface and cover the
wound (epithelialization).
• Oxygen and nutrients supplied by new blood vessels support
collagen synthesis and tissue repair.
• Myofibroblasts contract the wound and reduce its size.
Important Growth Factors:
• Platelet-Derived Growth Factor (PDGF) stimulates fibroblast growth
and collagen production.
• Transforming Growth Factor-beta (TGF-β) promotes collagen
synthesis and supports wound contraction.
• Vascular Endothelial Growth Factor (VEGF) stimulates the
formation of new blood vessels through angiogenesis.
Step 5 – Remodeling (Maturation Phase)
• Type III collagen is gradually replaced by stronger Type I collagen.
• Collagen fibers become reorganized and cross-linked.
© 2026 Dr. Sudhadevi Sadanandan
• Scar tissue gradually becomes stronger and more stable.
• The number of blood vessels decreases as healing progresses.
• The tensile strength of the wound progressively increases.
• The healed wound gradually gains strength but usually reaches only
about 80% of the original tissue strength and does not regain 100%
strength.
• Complete remodeling may continue for several months to one year.
Flow Chart
Tissue Injury
↓ Hemostasis: Vasoconstriction → Platelet Aggregation → Coagulation Cascade → Fibrin Clot Formation
↓ Inflammation: Vasodilation → Neutrophils → Macrophages → Phagocytosis
↓ Proliferation: Fibroblast Proliferation → Collagen Synthesis → Angiogenesis → Granulation Tissue Formation
→ Epithelialization → Wound Contraction
↓ Remodeling: Collagen Remodeling → Scar Formation → Increased Tensile Strength → Complete Wound
Healing
6. Factors Affecting Wound Healing
A. Local Factors
• Infection delays wound healing by destroying healthy tissue.
• Poor blood supply reduces oxygen and nutrient delivery to the
wound.
• Foreign bodies interfere with normal tissue repair.
• Excessive pressure causes tissue damage and delays healing.
• Edema reduces oxygen supply and slows tissue repair.
• Repeated trauma to the wound delays healing.
B. Systemic Factors
• Increasing age slows the wound healing process.
• Malnutrition reduces collagen synthesis and tissue repair.
• Protein deficiency reduces collagen formation and delays healing.
• Vitamin C deficiency delays collagen synthesis and wound healing.
• Zinc deficiency interferes with cell growth and tissue repair.
© 2026 Dr. Sudhadevi Sadanandan
• Diabetes mellitus delays healing due to poor circulation and
increased risk of infection.
• Anemia reduces oxygen supply to the tissues.
• Poor oxygenation and vascular disease delay healing.
• Smoking decreases blood flow and oxygen delivery.
• Obesity increases the risk of wound complications.
• Corticosteroid therapy suppresses inflammation and delays healing.
• Immunodeficiency reduces the body's ability to fight infection.
• Dehydration delays tissue repair.
7. Complications of Wound Healing
• Wound infection may occur.
• Hemorrhage may develop.
• Hematoma may form beneath the wound.
• Wound dehiscence (separation of wound edges) may occur.
• Evisceration (protrusion of internal organs through the wound) may
occur.
• Delayed wound healing may develop.
• Hypertrophic scar formation may occur.
• Keloid formation may develop.
• Contracture formation may limit joint movement.
8. Clinical Manifestations of Delayed Wound Healing
• Persistent pain may be present.
• Redness and swelling may persist.
• Fever may indicate infection.
• Purulent or foul-smelling discharge may be present.
• Delayed granulation tissue formation may occur.
• Wound edges may separate.
© 2026 Dr. Sudhadevi Sadanandan
• Delayed epithelialization may occur.
• The wound may fail to heal completely.
9. Diagnosis
• A complete health history should be obtained.
• A thorough physical examination should be performed.
• The wound should be assessed for size, depth, color, drainage, odor,
and signs of infection.
• Complete Blood Count (CBC) helps detect infection.
• Blood glucose estimation helps identify diabetes mellitus.
• Wound culture and sensitivity identify the causative microorganism.
• X-ray, Ultrasound, or CT scan may be performed when indicated.
10. Management
A. Medical Management
• Appropriate antibiotics are administered for infected wounds.
• Surgical debridement is performed to remove necrotic tissue.
• Analgesics are administered to relieve pain.
• Appropriate wound dressing and regular wound care promote
healing.
• Skin grafting may be performed when indicated, such as for
extensive burns, large wounds, or chronic non-healing wounds with
major tissue loss.
B. General Management
• Adequate nutrition rich in protein, vitamins, and minerals should be
maintained.
• Adequate hydration should be ensured.
• Pressure on the wound should be avoided.
• Appropriate wound care and dressing should be maintained
according to the wound condition.
© 2026 Dr. Sudhadevi Sadanandan
11. Nursing Management
• The nurse assesses the wound regularly for size, color, drainage,
odor, and signs of infection.
• The nurse monitors vital signs regularly.
• The nurse performs wound dressing using strict aseptic technique to
prevent infection.
• The nurse administers prescribed medications safely.
• The nurse maintains adequate nutrition and hydration.
• The nurse repositions immobile patients regularly to prevent
pressure injuries.
• The nurse encourages early mobilization when appropriate.
• The nurse teaches the patient proper wound care, personal hygiene,
and the importance of follow-up.
• The nurse encourages smoking cessation.
• The nurse documents wound healing progress accurately.
12. Prevention
• Proper hand hygiene should be maintained.
• Aseptic technique should be followed during wound care.
• Diabetes mellitus should be well controlled.
• A balanced diet rich in protein, Vitamin A, Vitamin C, and Zinc
should be consumed.
• Pressure injuries should be prevented by regular repositioning.
• Smoking and alcohol should be avoided.
• The wound should be kept clean and maintained at an appropriate
moisture level according to the prescribed dressing plan.
• Infections should be identified and treated promptly.
© 2026 Dr. Sudhadevi Sadanandan
Conclusion
• Wound healing is a complex physiological process involving
hemostasis, inflammation, proliferation, and remodeling.
• Successful wound healing depends on adequate blood supply, proper
nutrition, infection control, and effective nursing care.
• Early assessment, timely treatment, and appropriate nursing
interventions help prevent complications and promote complete
wound healing.
© 2026 Dr. Sudhadevi Sadanandan