DEFINITION OF DRUGABSORPTION
• Drug absorption define as the process of movement of unchanged drug from
the site of administration to systemic circulation.
• After reaching the blood, it is distributed to the site of action where it produce
its therapeutic effect.
• However, measuring the drug concentration directly at the site of action is
difficult.
• Therefore, plasma drug concentration used to estimate the therapeutic response.
3.
RELATIONSHIP BETWEEN PLASMADRUG
CONCENTRATION & THERAPEUTIC RESPONSE
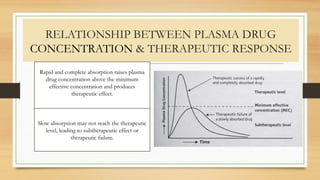
Rapid and complete absorption raises plasma
drug concentration above the minimum
effective concentration and produces
therapeutic effect.
Slow absorption may not reach the therapeutic
level, leading to subtherapeutic effect or
therapeutic failure.
4.
GASTROINTESTINAL ABSORPTION OF
DRUGS
•The oral route is the most common way to give drug.
• So, most drugs are absorbed through the GI tract.
• Many factors can affect how much drug is absorbed.
• Before understanding absorption, we must first understand the cell membrane
structure, because drugs must cross it.
• For a drug to be absorbed, distributed, or eliminated, it must cross biology membrane.
• The movement of a drug across a membrane is called drug transport.
5.
CELL MEMBRANE: STRUCTURE&
PHYSIOLOGY
• STRUCTURE:
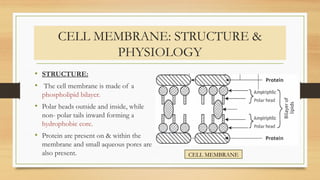
• The cell membrane is made of a
phospholipid bilayer.
• Polar heads outside and inside, while
non- polar tails inward forming a
hydrophobic core.
• Protein are present on & within the
membrane and small aqueous pores are
also present. CELL MEMBRANE
6.
CELL MEMBRANE: STRUCTURE&
PHYSIOLOGY
• FUNCTION:
• It acts as a selectively permeable barrier.
• Lipid- soluble drugs pass easily through the lipid layer, while small water- soluble molecules pass
through pores.
• Membrane protein help in transport and receptor action.
• BIOAVAILABILITY:
• The rate & extent (amount) of drug absorption is known as bioavailability.
• It is denoted as (f).
• f= Bioavailability dose administered dose
• Where= f is Bioavailable Fraction
7.
MECHANISM OF DRUGABSORPTION
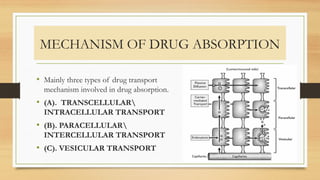
• Mainly three types of drug transport
mechanism involved in drug absorption.
• (A). TRANSCELLULAR
INTRACELLULAR TRANSPORT
• (B). PARACELLULAR
INTERCELLULAR TRANSPORT
• (C). VESICULAR TRANSPORT
8.
(A). TRANSCELLULAR INTRACELLULAR
TRANSPORT
•It is most common pathway for drug transport.
• It is defined as the passage of drug across GI epithelium.
• The various transcellular transport processes involved in drug absorption are:
1. PASSIVE TRANSPORT PROCESSES
PASSIVE DIFFUSION
PORE TRANSPORT
ION-PAIR TRANSPORT
FACILLITATED DIFFUSION
2. ACTIVE TRANSPORT PROCESSES
PRIMARY ACTIVE TRANSPORT
SECONDARY ACTIVE TRANSPORT
( Symport & Antiport)
9.
1. PASSIVE TRANSPORTPROCESSES
• (a). PASSIVE DIFFUSION:
• In this type of diffusion drug molecules diffuse from higher concentration to lower concentration until equilibrium is attained.
• Passive diffusion is expressed by Fick’s first law of diffusion.
• dQdt = DAKh [ Cgit- C ]
• dQdt = rate of drug diffusion.
• D = diffusion coefficient of the drug through membrane.
• A= surface area of absorbing membrane.
• Kmw = partition coefficient of the drug between the lipoidal membrane & the aqueous GI fluids.
• [ Cgit – C] = difference in the concentration of drug.
• H= thickness of the membrane.
10.
1. PASSIVE TRANSPORTPROCESSES
• (b). PORE TRANSPORT:
• It is also called as filtration.
• In this transport drug
molecule move through
aqueous pores or protein
channel present in the cell
membrane.
11.
1. PASSIVE TRANSPORTPROCESSES
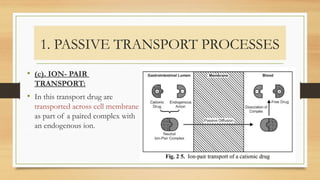
• (c). ION- PAIR
TRANSPORT:
• In this transport drug are
transported across cell membrane
as part of a paired complex with
an endogenous ion.
12.
1. PASSIVE TRANSPORTPROCESSES
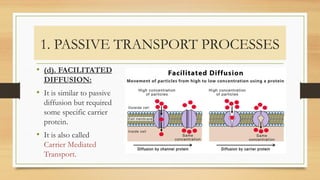
• (d). FACILITATED
DIFFUSION:
• It is similar to passive
diffusion but required
some specific carrier
protein.
• It is also called
Carrier Mediated
Transport.
13.
2. ACTIVE TRANSPORTPROCESSES
• In Active Transport drug moves against the concentration gradient (i.e: from
low concentration to high concentration).
• In this transport mechanism requires energy in the form of ATP, these are
further subdivided into:
• (a). PRIMARY ACTIVE TRANSPORT: It required direct ATP.
• (b). SECONDARY ACTIVE TRANSPORT: It is not required direct
ATP.
14.
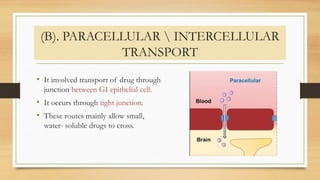
(B). PARACELLULAR INTERCELLULAR
TRANSPORT
• It involved transport of drug through
junction between GI epithelial cell.
• It occurs through tight junction.
• These routes mainly allow small,
water- soluble drugs to cross.
15.
(C). VESICULAR CARPUSCULAR
•It is also energy dependent process but involved transport of substance
within vesicle into a cell.
• Vesicular transport of drug can classified into two categories:
• 1). ENDOCYTOSIS: It is a process in which cell absorbs by engulfing
them.
• (a). Phagocytosis: Cell Eating
• (b). Pinocytosis: Cell Drinking
• (c). Transcytosis: Macromolecules are transferred across the cell
membrane.
16.
FACTORS INFLUENCING GI
ABSORPTIONOF A DRUG
• (A). PHARMACEUTICAL FACTORS: Include factors relating to the physicochemical properties of the
drug, dosage form characteristics & pharmaceutical ingredient.
• 1). Physicochemical Properties Of Drug
1. Drug solubility & dissolution rate
2. Particle size & effective surface area
3. Polymorphism & amorphism
4. Salt form & lipophilicity of the drug
5. pKa of the drug & GI
6. Drug stability
17.
(B). DOSAGE FORMCHARACTERISTICS &
PHARM. INGREDIENT
1. Disintegration time
2. Dissolution time
3. Manufacturing variable
4. Pharmaceutical ingredients
5. Nature & Type of dosage form
6. Product age & Storage condition
18.
(C). PATIENT –RELATED FACTORS
1. Age
2. Gastric emptying time
3. Intestinal transit time
4. Disease states
5. Blood flow through the GI
6. Contact time with GI mucosa
7. Presystemic metabolism
19.
ABSORPTION OF DRUGFROM NON PER
ORAL EXTRA- VASCULAR ROUTES
• NON PER OS means other than oral routes which by passes the GIT and reaches to systemic circulation.
• It involves:
1. BUCCAL SUBLINGUAL
2. RECTAL
3. TOPICAL
4. INTRAMUUSCULAR
5. SUBCUTANEOUS
6. PULMONARY
7. INTRANASAL
8. INTRAOCCULAR
9. VAGINAL
20.
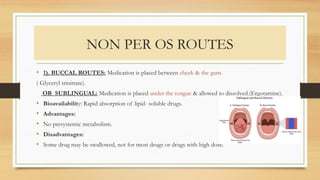
• 1). BUCCALROUTES: Medication is placed between cheek & the gum.
( Glyceryl trinitrate).
OR SUBLINGUAL: Medication is placed under the tongue & allowed to dissolved.(Ergotamine).
• Bioavailability: Rapid absorption of lipid- soluble drugs.
• Advantages:
• No presystemic metabolism.
• Disadvantages:
• Some drug may be swallowed, not for most drugs or drugs with high dose.
NON PER OS ROUTES
21.
NON PER OSROUTES
• 2.RECTAL: The rectal route of administration is still an important route for children &
old patient.
• Bioavailability: Absorption may vary from suppository.
• Advantages:
• Useful when patient cannot swallow medication.
• Disadvantages:
• Absorption may be erratic.
• Suppository may migrate to different position.
22.
NON PER OSROUTES
• 3). TOPICAL: Skin is largest organ of the body, and is commonly employed as a site of drug
administration for local as well as systemic effect.
• Bioavailability: bioavailability depends on lipid solubility of drug, molecular size, skin.
• Advantages:
• Avoid first pass metabolism.
• Reduced systemic side effect.
• Disadvantages:
• Low systemic bioavailability.
• Limited drug absorption.
23.
NON PER OSROUTES
• 4. INTRAMUSCULAR INJECTION: The drug is injected directly into the muscle for systemic
effect.
• Bioavailability: Rapid absorption from aqueous solution and slow absorption from non- aqueous
solutions.
• Advantages:
• Easier to inject than IV injection.
• Laeger volume may be used compared to subcutaneous solution.
• Disadvantages:
• Irritating drug may be very painful.
• Variable rates of absorption depending upon muscle group injected and blood flow.
24.
NON PER OSROUTES
• 5. SUBCUTANEOUS ROUTES: The drug is injected under the skin into the
subcutaneous tissue.
• Bioavailability: Rapid absorption from aqueous solution and slow absorption
from depot formulations.
• Advantages:
• Generally, used for vaccines and drug not absorbed orally like insulin.
• Disadvantages:
• Rate of drug absorption depends upon blood flow and injection volume.5.
25.
NON PER OSROUTES
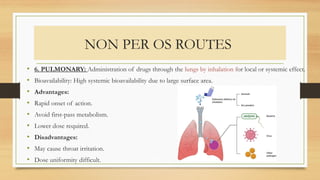
• 6. PULMONARY: Administration of drugs through the lungs by inhalation for local or systemic effect.
• Bioavailability: High systemic bioavailability due to large surface area.
• Advantages:
• Rapid onset of action.
• Avoid first-pass metabolism.
• Lower dose required.
• Disadvantages:
• May cause throat irritation.
• Dose uniformity difficult.
26.
NON PER OSROUTES
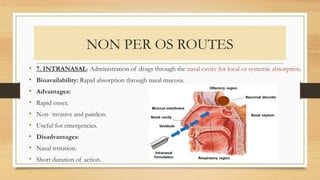
• 7. INTRANASAL: Administration of drugs through the nasal cavity for local or systemic absorption.
• Bioavailability: Rapid absorption through nasal mucosa.
• Advantages:
• Rapid onset.
• Non- invasive and painless.
• Useful for emergencies.
• Disadvantages:
• Nasal irritation.
• Short duration of action.
.
27.
NON PER OSROUTES
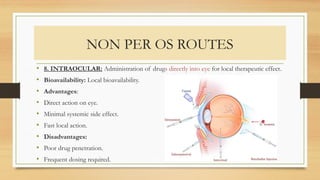
• 8. INTRAOCULAR: Administration of drugs directly into eye for local therapeutic effect.
• Bioavailability: Local bioavailability.
• Advantages:
• Direct action on eye.
• Minimal systemic side effect.
• Fast local action.
• Disadvantages:
• Poor drug penetration.
• Frequent dosing required.
28.
NON PER OSROUTES
• 9. VAGINAL: The drug is administered into the vagina to produce mainly local therapeutic effect.
• Bioavailability: Variable systemic absorption.
• Advantages:
• Good for local infection.
• Avoid gastric irritation.
• Disadvantages:
• Local irritation or discharge.
• Patient discomfort.
• Social acceptability issues.


 Most read






 Most read

 Most read