Average, Individual and Population
Bioequivalence – Understanding the
True Variability of a Generic Product

  1st Annual Generic Medicine Middle East Conference
    April 14-15th, Crown Plaza, Yas Island, Abu Dhabi


         Dr. Bhaswat S. Chakraborty
 Sr. Vice President, R&D, Cadila Pharmaceuticals
Outline
•   Bioequivalence and Average Bioequivalence (ABE)
•   Main concerns with ABE
•   Design and limitations of ABE studies
•   Individual and Population Bioequivalence (IBE and PBE)
•   Metrics
•   Design and sample size of replicate studies for IBE and PBE
•   Conduct and analysis
•   Example
•   Issues
•   Conclusion
Bioequivalent Drug Products
• Pharmaceutical Equivalent
   – Same dose and dosage form, ideally same assay and
     content uniformity
   – Could be pharmaceutical alternative dose or form

• Bioequivalent
   – Statistical and pharmacokinetic equivalent
   – Equivalent rate and extent of absorption
      • 90% CI of relative mean Cmax and AUC: 80-125%

• Interpretation: Therapeutic equivalence
Currently Practiced Bioequivalence
• For almost all generic drus today, the regulatory standard is
  “average bioequivalence (IBE)”
• Concluded from 2-product, 2-period, crossover studies with
  fixed effects
• That means
   –   An average patient (volunteer) will have
   –   An average Cmax and AUC
   –   From an average reference and test product
   –   That are not significantly different

• Problem: cannot individualize or generalize for population
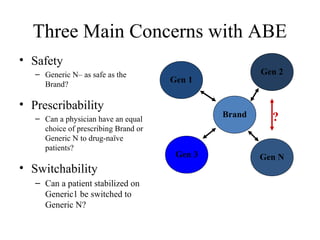
Three Main Concerns with ABE
• Safety
   – Generic N– as safe as the                         Gen 2
     Brand?
                                      Gen 1

• Prescribability
   – Can a physician have an equal             Brand     ?
     choice of prescribing Brand or
     Generic N to drug-naïve
     patients?
                                       Gen 3           Gen N
• Switchability
   – Can a patient stabilized on
     Generic1 be switched to
     Generic N?
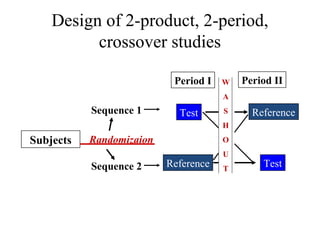
Design of 2-product, 2-period,
          crossover studies

                           Period I   W   Period II
                                      A
           Sequence 1       Test      S     Reference
                                      H
Subjects   Randomizaion               O
                                      U
           Sequence 2     Reference   T
                                              Test
Limitations of ABE
• Produces medical dilemma
• Ignores distribution of Cmax and AUC
• Within subject variation is not accurate
• Ignores correlated variances and subject-by-formulation
  interaction
• One criteria irrespective of inherent patterns of product, drug
  or patient variations
• Although rare, but may not be therapeutic equivalent
Other Choices in BE
                and their Conditions
• Individual Bioequivalence (IBE)
   – Addresses switchability
• Population Bioequivalence (PBE)
   – Addresses prescribability
• Design and statistics of IBE & PBE
   – Take into account both population mean
     and variance
   – Address switchability and thereby subject-fomulation interaction
   – Provide same level of confidence (consumer’s risk of 5%) and power
   – Accept formulations with reduced within subject variability
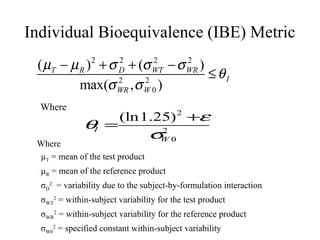
Individual Bioequivalence (IBE) Metric
 ( µT − µ R ) 2 + σ D + (σ WT − σ WR )
                    2      2      2
                                       ≤ θI
          max(σ WR , σ W 0 )
                    2    2


  Where
                         (ln1.25) 2 +ε
              θI =
                                 σ2 0
                                  W
 Where
 µT = mean of the test product
  µR = mean of the reference product
  σD2 = variability due to the subject-by-formulation interaction
  σWT2 = within-subject variability for the test product
  σWR2 = within-subject variability for the reference product
  σW02 = specified constant within-subject variability
Population Bioequivalence (PBE) Metric


                                                     ≤θP

  Where
  µT = mean of the test product
   µR = mean of the reference product
   σTT2 = total variability (within- and between-subject) of the test product
   σTR2 = total variability (within- and between-subject) of the reference
       product
   σ02 = specified constant total variance
FDA Recommended Designs of
      IBE/PBE studies
• 2-product, 2-period, crossover studies with fixed
  effects are not recommended
• 3- or 4-period, replicate designs with restricted sequences
  are recommended
  TRTR                        or              TRT
  RTRT                                        RTR
• Estimation of sWR2, sWT2, and sD2 are required along with
  response means
• One can use either reference or constant scaling (without
  much concern about increased Type I error due to multiple
  testing)
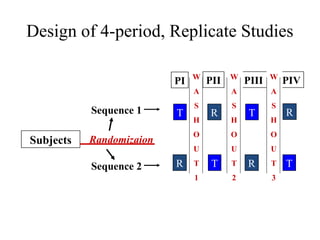
Design of 4-period, Replicate Studies

                               W         W          W
                          PI       PII       PIII       PIV
                               A         A          A
                               S         S          S
           Sequence 1     T        R         T          R
                               H         H          H
                               O         O          O
Subjects   Randomizaion
                               U         U          U

           Sequence 2     R    T    T    T   R      T   T
                               1         2          3
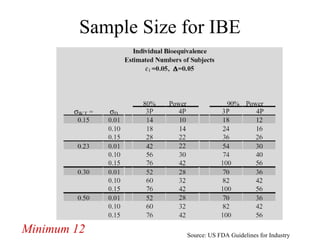
Sample Size for IBE


Minimum 12           Source: US FDA Guidelines for Industry
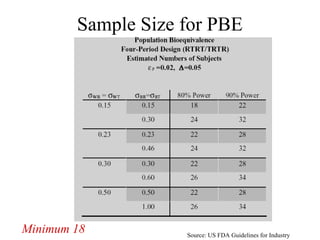
Sample Size for PBE


Minimum 18          Source: US FDA Guidelines for Industry
Conduct of Replicate Studies
• Generally dosing, environmental control, blood sampling
  scheme and duration, diet, rest and sample preparation for
  bioanalysis are all the same as those for 2-period, crossover
  studies
• Avoid first-order carryover (from preceding formulation) &
  direct-by-carryover (from current and preceding formulation)
  effects
   – Unlikely when the study is single dose, drug is not endogenous,
     washout is adequate, and the results meet all the criteria

• If conducted in groups, for logistical reasons, ANOVA model
  should take the period effect of multiple groups into account
• Use all data; if outliers are detected, make sure that they don’t
  indicate product failure or strong subject-formulation
  interaction
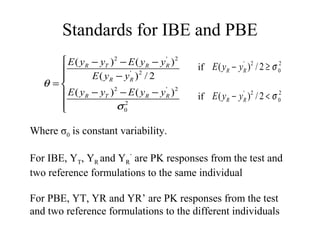
Standards for IBE and PBE
       E ( yR − yT ) 2 − E ( yR − y R ) 2
                                     '

                                            if E ( yR − yR )2 / 2 ≥ σ 02
                                                          '

              E ( yR − yR ) 2 / 2
                           '

   θ =
       E ( yR − yT ) − E ( yR − y R )
                      2              ' 2
                                             if E ( yR − yR )2 / 2 < σ 02
                                                          '

      
                      σ02


Where σ0 is constant variability.

For IBE, YT, YR and YR’ are PK responses from the test and
two reference formulations to the same individual

For PBE, YT, YR and YR’ are PK responses from the test
and two reference formulations to the different individuals
Declaring IBE and PBE

     H0: θ ≥ θI or θP; HA: < θI or θP

IBE or PBE is claimed when 95% confidence upper bound of
of θ is less than θI or θP and the observed ratio of geometric
means is within bioequivalence limits of 80 – 125%.
Analysis by SAS Proc Mixed
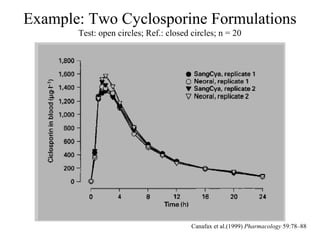
Example: Two Cyclosporine Formulations
       Test: open circles; Ref.: closed circles; n = 20


                                        Canafax et al.(1999) Pharmacology 59:78–88
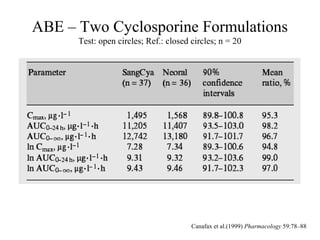
ABE – Two Cyclosporine Formulations
      Test: open circles; Ref.: closed circles; n = 20


                                       Canafax et al.(1999) Pharmacology 59:78–88
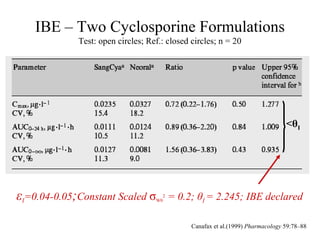
IBE – Two Cyclosporine Formulations
             Test: open circles; Ref.: closed circles; n = 20


                                                                                   <θI


εI=0.04-0.05;Constant Scaled σ     W0
                                        2
                                            = 0.2; θI = 2.245; IBE declared

                                                 Canafax et al.(1999) Pharmacology 59:78–88
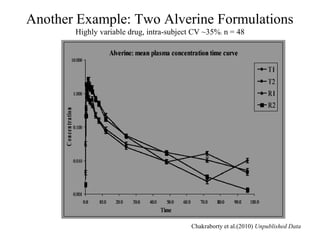
Another Example: Two Alverine Formulations
       Highly variable drug, intra-subject CV ~35%; n = 48


                                         Chakraborty et al.(2010) Unpublished Data
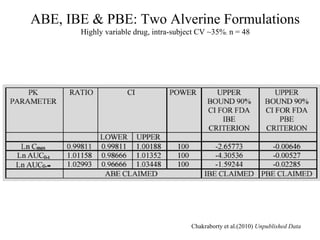
ABE, IBE & PBE: Two Alverine Formulations
       Highly variable drug, intra-subject CV ~35%; n = 48


                                        Chakraborty et al.(2010) Unpublished Data
Issues
• Primary
   – Justification and need for an IBE criterion
   – Financial and human resource burden of conducting replicate study
     design
   – appropriateness of the statistical methodology

• Advanced
   – Mean-variance trade-off (if the term σWT2 – σWR2 ) is sufficiently negative,
     the test product could be deemed BE with a large difference in the
     averages of a BE metric; resolved difference cannot exceed 80-125%)
   – Extra-reference 2x3 designs (TRR,RTR)
       • Advantages, disadvantages
   – ABE from replicate studies
       • CR products, highly variable drugs
Conclusions
• ABE serves well for wide therapeutic index and
  uncomplicated PK drugs
• ABE has limitations
    – Ignores switchability and prescribability; ignores distributions of C max and AUC;
      estimate of within subject variation is not accurate; ignores correlated
      variances and subject-by-formulation interaction….
• IBE provides for switchability and PBE for prescribability
• Replicate studies are required for IBE and PBE
• Analysis of variability is done by a mixed effects model
• NTR, HVDP, CR formulations can be assured for IBE and
  PBE
• There are methodological issues for IBE and PBE which must
  be discussed and resolved
References
• US FDA (1999). In Vivo Bioequivalence Studies
  Based on Population and Individual Bioequivalence
  Approaches. Food and Drug Administration,
  Rockville, Maryland, August, 1999.

• US FDA (2001). Guidance for Industry: Statistical
  Approaches to Establishing Bioequivalence. Food
  and Drug Administration, Rockville, Maryland,
  January, 2001.
Acknowledgements:
             Priyanka Kocheta
             Somnath Sakore


                    Thank you very much