DEFINITION
- It isthe use of proper body
mechanics in repositioning,
lifting, and transferring patients
safely.
4.
PURPOSE
- Positions andprepares client
for a variety of clinical
procedures.
- The movement maintains and
restores muscle tone.
5.
TRANSFERRING CLIENTS
Many clientsrequire some assistance in
transferring between bed and chair or wheelchair,
between wheelchair and toilet, and between bed
and stretcher. Before transferring any client, nurse
must determine the client’s physical and mental
capabilities to participate in the transfer
technique. In addition, the nurse must analyze and
organize the activity.
6.
- Plan whatto do and how to do it. Determine the space in which
the transfer will take place, the number of assistants needed to
accomplish the transfer safely, and the client’s capabilities.
- Obtain essential equipment before starting and that all
equipment is functioning correctly. The gait transfer belt is meant
only to increase control of the clients’ movements, if the client
requires lifting, a mechanical lifting device should be used.
- Make a written plan of the transfer including the client’s
tolerance.
GUIDELINES
7.
- Remove obstaclesfrom the area used for the transfer.
-Explain the transfer to the client, including what the
client should do.
- Explain the transfer to the nursing personnel who are
helping; specify who will give directions.
- Always support or hold the client rather than the
equipment and ensure the client’s safety and dignity.
- During the transfer, explain step-by-step what the
client should do.
GUIDELINES
- A clientmay need to be transferred
between the bed and a wheelchair or
chair, the bed and the commode, or
a wheelchair and the toilet. There are
numerous variations in the technique.
PURPOSE
12.
Which variation thenurse selects
depends on factors related to
the client and the environment that
are assessed prior to beginning the
transfer.
PURPOSE
13.
Before transferring aclient, assess the following:
• The client’s body size
• Ability to follow instructions
• Ability to bear weight
• Ability to position/reposition feet on floor
• Ability to push down with arms and lean
forward
• Ability to achieve independent sitting balance
ASSESSMENT
14.
• Activity tolerance
•Muscle strength
• Joint mobility
• Presence of paralysis
• Level of comfort
• Presence of orthostatic hypotension
ASSESSMENT
15.
• The techniquewith which the client is familiar
• The space in which the transfer will need to
be maneuvered
(bathrooms, for example, are usually cramped)
• The number of assistants (one or two) needed
to accomplish the transfer safely
ASSESSMENT
16.
PLANNING
- Review theclient record to determine if
previous nurses have recorded information
about the client’s ability to transfer.
Implement pain relief measures so that they
are effective when the transfer begins.
17.
The decision mustbe made at this time
regarding the client’s ability to participate.
If the client can safely participate in the
transfer, a gait/transfer belt or sliding board
can be used; if not, a powered standing
assist lift or full-body lift would be safer for
the client and nurse.
PLANNING
IMPLEMENTATION
Preparation:
• Plan whatto do and how to do it.
• Obtain essential equipment before starting
(e.g., gait/transfer belt, wheelchair), and check
that all equipment is functioning correctly.
• Remove obstacles from the area so clients do
not trip. Make sure there are no spills or liquids
on the floor on which clients could slip.
V
1. Check the
doctor’sorder
and client’s
diagnosis and
restrictions.
* To determine
any contraindica-
tions/limitations on
the client’s
physical activity
PROCEDURE RATIONALE
24.
V
2. Assess theclient’s
ability, level of
comfort, muscle
strength presence of
paralysis and ability
to follow instructions.
* To provide
information about
the client’s
physical abilities to
ensure safe
transferring.
PROCEDURE RATIONALE
25.
V
3. Wash hands.* To prevent the
transfer of
microorganisms.
PROCEDURE RATIONALE
V
5. Identify the
client.Inform
client about
desired purpose
and destination.
* To reduce
client’s anxiety
and increase
cooperation.
PROCEDURE RATIONALE
28.
V
6. Adjust the
heightof the bed
to lowest possible
position.
* To reduce
distance that the
client has to step
down thus
decreasing risk of
injury.
PROCEDURE RATIONALE
29.
* Minimize lifting
therebyminimizing
discomfort both
for client and the
health care
provider.
PROCEDURE RATIONALE
7. Slowly raise the
head of the bed if
notcontraindicate
d by client’s
condition.
30.
V
8. Place onearm under
the client’s leg and one
arm behind the client’s
back. Slowly, pivot the
client so the client’s leg
are dangling over the
edge of the bed.
* To support the
client while sitting
him/her on the
edge of the bed.
PROCEDURE RATIONALE
31.
V
9. Allow theclient
to dangle for 2 to 5
minutes. Support
client if necessary.
* To allow time for
assessing client’s
response to sitting
reduces possibility
of orthostatic
hypotension.
PROCEDURE RATIONALE
32.
V
10. Bring thechair or
wheelchair close to the
side of the bed. Place it at
a 45 degree angle of the
bed. If the client has a
weaker side, place the
chair/ wheelchair on the
client’s strong side.
* To allow client
to bear weight
on strong leg.
PROCEDURE RATIONALE
V
12. Put transferbelt
or other transfer
aid if needed, and
secure.
* Provides safe,
balance hold on
patient without
stressing joints or
limbs
PROCEDURE RATIONALE
35.
V
13. Lifter’s knees
arewell flexed
with back straight,
hands gripping
each side of the
transfer belt.
* Transfer belt is
grasped at each
side to provide
movement.
PROCEDURE RATIONALE
36.
V
14. Rock client’s
bodyup to standing
position on the count
of three while
straightening hips
and legs, keeping
knees slightly flexed.
* Rocking motion
gives a client
body movement
and requires less
muscular effort to
lift the client.
PROCEDURE RATIONALE
37.
V
15. Lifter andclient
pivot turn so lifter is
facing chair and
client’s back is
toward chair lifter still
holding the transfer
belt.
* Less effort for
lifter and client.
PROCEDURE RATIONALE
38.
V
16. Instruct clientto
use arm to rest on
chair.
* To increase
client’s stability.
PROCEDURE RATIONALE
39.
V
17. Flex hipsand
knees while lowering
client into
chair/wheelchair.
* Presents injury to
clients from poor
body alignment.
PROCEDURE RATIONALE
40.
V
18. Assess clientfor
proper alignment for
sitting position.
Support weak side
with pillow if needed.
PROCEDURE RATIONALE
* To make client
comfortable.
41.
V
19. Secure thesafety belt,
place client’s feet on foot
pedals and release brakes
if you will be moving
the client immediately. If
the client is sitting on a
chair, offer a foot stool, if
available.
PROCEDURE RATIONALE
* To ensure client’s
safety; to prepare
client for
movement.
42.
* To reducethe
transmission of
microorganism.
PROCEDURE RATIONALE
20. Wash hands.
43.
* To provide
accuratedata in
the care of client.
PROCEDURE RATIONALE
21. Record effect
of the transfer.
44.
Variation: Transferring witha Belt
and Two Nurses
• Even if a client is able to partially
bear weight and is cooperative, it still
may be safer to transfer a client with
the assistance of two nurses. If so, you
should position yourselves on both sides
of the client, facing the same direction
as the client. Flex your hips, knees, and
ankles. Grasp the client’s transfer belt
with the hand closest to the client, and
with the other hand support the client’s
elbows.
45.
Variation: Transferring witha Belt
and Two Nurses
• Coordinating your efforts,
all three of you stand
simultaneously, pivot, and
move to the wheelchair.
Reverse the process to
lower the client onto the
wheelchair seat.
46.
Variation: Transferring aClient with
an Injured Lower Extremity
- When the client has an injured
lower extremity, movement should
always occur toward the client’s
unaffected (strong) side. For
example, if the client’s right leg is
injured and the client is sitting on
the edge of the bed preparing to
transfer to a wheelchair, position
the wheelchair on the client’s left
side.
47.
Variation: Transferring aClient with
an Injured Lower Extremity
Rationale: In this way, the client
can use the unaffected leg
most effectively and safely
48.
Variation: Variation: Usinga Slide
Board
For clients who cannot stand but are
able to cooperate and posess
sufficient upper body strength, use a
slide board to help them move
without nursing assistance. Rationale:
This method not only promotes client’s
sense of independence but also
preserves your energy.
PURPOSE
• The stretcher,or gurney, is used to transfer
supine clients from one location to another.
Whenever the client is capable of
accomplishing the transfer from bed to
stretcher independently, either by lifting onto it
or by rolling onto it, the client should be
encouraged to do so.
53.
ASSESSMENT
Before transferring aclient, assess the following:
• The client’s body size and weight
• Ability to follow instructions
• Activity tolerance
• Level of comfort
• The space in which the transfer is maneuvered
• The number of assistants (one to four) needed to
accomplish the transfer safely
54.
PLANNING
- Review theclient record to determine if
previous nurses have recorded information
about how the client tolerated similar transfers.
If indicated, implement pain-relief measures so
that they are effective when the transfer
begins.
V
1. Assess the
amountof
assistance required
for transfer.
PROCEDURE RATIONALE
* To Promote clients
independence; to
ensure that enough
staff are present
before beginning
transfer.
V
3. Obtain equipment
neededand make
sure each is
functional.
PROCEDURE RATIONALE
* To avoid
accident while
moving the client.
63.
V
4. Inform client
aboutdesired
purpose and
destination.
PROCEDURE RATIONALE
* To reduce
client’s anxiety
and increase
cooperation.
64.
V
5. Raise thebed to
an inch higher than
stretcher and lock
brakes of the bed.
PROCEDURE RATIONALE
* Reduces the
distance lifter must
bend, preventing
back strain and bed
from moving.
65.
V
6. Three liftersstand side
by side, facing side of the
client’s bed. The tallest
person places one arm
under client’s head and
shoulder. Second lifter
places arm under waist
and thighs. Third and
shortest lifter places arm
under legs.
PROCEDURE RATIONALE
* To permit the
distribution of
load among
lifters.
66.
V
7. Lifters rollclient
toward their chest on
count of three; client
is lifted and held
against the lifter’s
chest.
PROCEDURE RATIONALE
* To move workload
over lifters’ base of
support, enable
lifters to work
together and safely
lift client.
67.
V
8. On countof
three, lifters step
back and pivot
toward the
stretcher.
PROCEDURE RATIONALE
* To transfer
weight toward
the stretcher.
68.
V
9. Lifters gentlylower
the client onto center
of the stretcher by
flexing knees, and hips
until elbows are
levelled with edge of
the stretcher.
PROCEDURE RATIONALE
* To coordinate
activity; use of
clients’ body
weight reduces
load on lifters.
69.
V
10. Position clienton
stretcher, place
pillows under head
and cover with sheet
or blanket.
PROCEDURE RATIONALE
* To provide
comfort and
privacy.
70.
V
11. Assess client’s
bodyalignment,
place safety strap
across body and
raise side rails.
PROCEDURE RATIONALE
* To reduce risk
of injury from
falling.
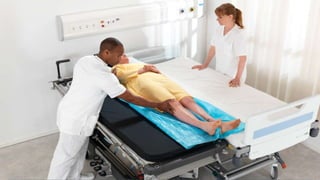
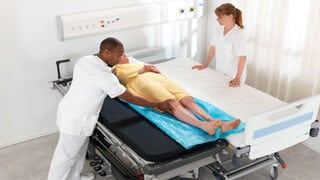
Variation: Using aTransfer Board
The transfer board is a lacquered
or smooth polyethylene board
measuring 45 to 55 cm (18 to 22 in.) by
182 cm (72 in.) with handholds along its
edges.Transfer mattresses are also
available, as are mechanical assistive
devices. It is imperative to have enough
people assisting with the transfer to
prevent injury to staff as well as clients.
74.
Variation: Using aTransfer Board
Turn the client to a lateral
position away from you, position
the board close to the client’s
back, and roll the client onto the
board. Pull the client and board
across the bed to the stretcher.
Safety belts may be placed over
the chest, abdomen, and legs.
76.
vV
- The skillof transferring a client can be
delegated to Unlicensed Assistive Personnel
(UAP) who have demonstrated safe transfer
technique for the involved client. It is important
for the nurse to assess the client’s capabilities
and communicate specific information about
what the UAP should report back to the nurse.
DELEGATION
V
EVALUATION
• Compare clientcapabilities such as weight bearing,
pivoting ability, and strength and control during
previous transfers.
• Report any significant deviations from normal to the
primary care practitioner.
• Note use of appropriate safety measures (e.g.,
transfer belt, locking wheels of bed and stretcher) by
UAP during transfer process.
INFANTS
-The infant whois lying down,
on the side or supine, can be
placed in either a bassinet or
crib for transport. If the
bassinet has a bottom shelf, it
can be used for carrying the
IV pump or monitor.
82.
CHILDREN
- The toddlershould be
transported in a high-top crib
with the side rails up and the
protective top in place.
Stretchers should not be used
because the mobile toddler
may roll or fall off.
83.
OLDER ADULTS
• Becauseconditions of older
adults can change from day to
day, always assess the situation
to ensure that you have the right
equipment and enough people
to assist when transferring a
client.
• Use special caution with older
clients to prevent skin tears or
bruising during a transfer or when
using a hydraulic lift.
84.
OLDER ADULTS
• Writethe method used to transfer each
client—equipment used, best position,
and number of people needed to assist in
transfer. This can be part of the care plan
and also be available in the client’s room
as a guide to all personnel caring for the
client.
• Avoid sudden position changes. They
can cause orthostatic hypotension and
increase the risk of fainting and falls.
V
• The caregiverand client should
practice transfer technique(s), using
appropriate equipment as needed, in
the hospital or long-term care setting
before being discharged.
• Assess furniture in the home. Does the
client’s favorite chair have arms for
ease of using and sitting? Examine the
fabric—is it rough? Will it cause skin
abrasions? If the client will be using a
wheelchair, is there enough space in
the bedroom and bathroom for a safe
transfer?
Home Care Considerations: Transferring from Bed to
a Chair
88.
V
• Observe clientand
caregiver transfer technique
in the home setting to
reinforce prior teaching.
Home Care Considerations: Transferring from Bed to
a Chair
V
The nurse whowill assist with patient transfers
ought to be knowledgeable, skilled, and trained.
Transferring a patient causes a lot of physiologic
changes that could put the patient at risk. Adverse
events are also expected if you're not following the
proper techniques which include: losing the patient
wristband/identification, disconnected/obstructed
lines, decreased/increased systolic blood pressure,
loosened/kinked tubes, fractures, and change in
mental status.
CONCLUSION
93.
V
Unexpected events duringtransfers of critically ill
intensive care unit patients can be reduced when an
intensivist or medically qualified personnel
accompanies the patient. The use of standardization
of procedures, checklists, and good team training
reduces the risk of unexpected events, improving the
patient’s safety, and lowering the complications.
CONCLUSION
V
Presented by:
ALEXA VERAE. CASTILO
ANA MELRINE S. COLINDON
RECHMON F. COMPAYAN
GABRIEL L. DALIDA
BSN 1-3
96.
V
REFERENCES
-Adion, D., &Dizon, E. (2009). Manual and Checklists on
Health Care Procedures.
-Berman, A, & Kozier, B. (2008). Kozier & Erb's
fundamentals of nursing: Concepts , process, and
practice (8th ed.). Upper Saddle River, N.J.: Pearson
Prentice Hall.pdf. Retrieved from rn.com
-Image(s) used under license from Shutterstock.com
V
QUIZ
1. It includesthe client's activity tolerance.
A. Evaluation
B. Assessment
C. Independent Nursing Intervention
D. Planning
99.
V
QUIZ
2. Obtaining theneeded equipment and
makes sure everything's functional.
A. Rationale
B. Equipment
C. Evaluation
D. Procedure
100.
V
QUIZ
3. What isthe rationale behind the procedure "checking the
doctor's order and client's diagnoses and restrictions".
A. To prevent the transfer of microorganisms
B. To provide information about the client's physical abilities to
ensure safe transferring.
C. To support the client while sitting him/her on the edge of
the bed.
D. To determine any contraindications/limitations on the
client's physical activity.