POST MARKETING SURVEILLANCE
PRESENTED BY ,
KRISHNAPRIYA V H
1ST SEMESTER M PHARM
CONTENTS
 Introduction
 Definitions
 Needs of Post Marketing Surveillance
 Sources of information
 Steps in PMS
 Methods of surveillance
 PMS procedure
 PMS oppourtunity
 Applications of PMS
 Pharmacovigilance
INTRODUCTION
 To market a drug the manufacturer must provide evidence of it’s efficacy and safety to USFDA.
 Once these premarketing requirements are met and the drug has been released.
 In premarketing testing ,the number and type of patent used to demonstrate a drugs safety
and efficacy are limited as compared with the number and type of patient who will eventually
be prescribed the drugs after it is marketed
 Post marketing surveillance of drug therefore play an important role to discover an
undesirable effect that might present at risk
 It provide additional information on the benefit and risk of the drugs .
 The principle focus of post marketing surveillance proposals has been on the safe use of
prescription drugs, even through the range of issues has encompassed both efficacy and
safety considerations.
DEFINITIONS
 Post marketing surveillance
it refers to the monitoring of drugs once they reach the market after clinical trail through a
process which evaluates drugs taken by individuals under a wide range of circumstances over an
extended period.
Post marketing surveillance is the practice of monitoring safety of pharmaceutical drugs or
medical devices after it has been released on the market and is an important part of the science
of pharmacovigilance.
 Pharmacovigilance
It is the science and activities relating to the detection ,assessment ,understanding ,and
prevention of adverse events or any other drug related problem.
NEEDS OF POST MARKETING SURVEILLANCE
 To assess a known serious risk related to the use of drug.
 To assess signals of serious risk related to the use of the drug.
 To identify an unexpected serious risk when available.
 To assess the drug-drug / food interaction .
 Find out long-term effects .
 Comply with regulatory requirements
 Compare new products or treatments with existing options and standard of care.
.
SOURCES OF INFORMATION
 Expert user groups
Health care professionals like doctors, pharmacists ,nurses can report ADRs to the connected authority
 Customer surveys
surveys can be done among the customer to find feed back, any side effects, or ADRs
these are usually done by the manufacturing companies through medical representatives
 Customer complaints
customers can complaint about a drug regarding its ADRs and other problems. These complaints are
reviewed and considered as information for further action.
 Other sources
literature review
device tracking /implant registries
user reaction during training programmers
STEPS IN PMS
Data collection
• Efficiently ,securely acquire, validate and transform real world data from various sources
Data analysis
• Transforming it in to the real world evidence
• It involves combining, blending , validating, analysing various data.
Data interpretation
• Once you finished collecting and analysing data, you need a way to interpret the data easily
and readily.
METHODS OF SURVEILLANCE
A. Controlled clinical trails
B. Spontaneous/voluntary reporting
C. Cohort studies
D. Case control studies
A. CONTROLLED CLINICAL TRAIL
 Controlled clinical trials allow the researchers to control who will receive an exposure.
 The trials may be randomized or non-randomized control trials.
 randomized control trials are considered being the gold standard, non-randomized control trials do have a
place in research. One benefit is the ability to compare a group receiving a current intervention with a
historically controlled group- a similar group in the past that did not receive the treatment/exposure.
B. SPONTANEOUS /VOLUNTARY REPORTING
 It is a communication from an individual (health care professionals , consumers)to a company or a regulatory
authority.
 This describes a suspected AE
 But the actual incidence of ADR can not be determined through spontaneous reporting
 By physicians and other HCP and hospital may alert FDA and pharmaceutical firms to possible AE of Drugs
 In India
ICSR (individual case safety reports ) are used to report the ADR, which is approved by the CDSCO
 In UK
“ Yellow card "systems are used
 In US
“Med Watch” forms are used
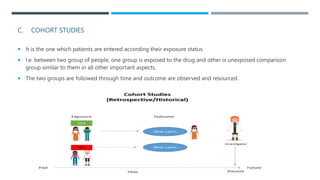
C. COHORT STUDIES
 It is the one which patients are entered according their exposure status.
 I.e. between two group of people, one group is exposed to the drug and other is unexposed comparison
group similar to them in all other important aspects.
 The two groups are followed through time and outcome are observed and resourced.
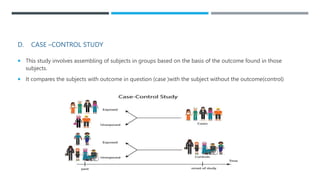
D. CASE –CONTROL STUDY
 This study involves assembling of subjects in groups based on the basis of the outcome found in those
subjects.
 It compares the subjects with outcome in question (case )with the subject without the outcome(control)
PMS PROCEDURE
 It should assign departments or position responsible for performing a function.
 Manufacturer may find it helpful to have a report at the end of year, as well as PMS tracking schedule.
 This information could constitute feed back receiver from user.
 Information obtained from PMS system should be communicated at a minimum, annually during a
management review meeting- which is top managements examination of the organizations quality
management system.
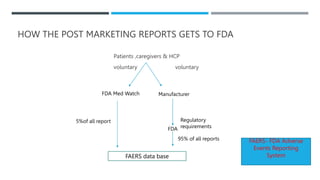
HOW THE POST MARKETING REPORTS GETS TO FDA
Patients ,caregivers & HCP
voluntary voluntary
Manufacturer
FDA Med Watch
Regulatory
requirements
FDA
FAERS data base
95% of all reports
5%of all report
FAERS- FDA Adverse
Events Reporting
System
APPLICATION OF PMS
 Access to additional health system data.
 Access to global data , regulatory, inspectional, health system, international surveillance and
pharmacovigilance
 Better analytical tool and methods.
 To establish incidence of ADR, detect previously unknown or inadequately quantified adverse reactions, and
define risk factors.
 Drug interactions (with other drugs ,food, environmental factors ,other treatments ).
 Identification of new medications
 Evaluation in different age groups and other type of patients like pregnant women.
 Big numbers and rare events.
 Dosage regimens .
PHARMACOVIGILANCE
 The term pharmacovigilance can be defined as “the science and activities relating to the
detection, assessment,understanding,and prevention of adverse events or any other drug
related problems”.
 Pharmacovigilance heavily focuses on ADRs,which are defined as any response to a drug
which is noxious and unintended ,including lack of efficacy ,medication errors such as over
dose and misuse , abuse of drug.
 Information received from patients and health care providers via pharmacovigilance
agreements (PVAs),as well as other sources such as the medical literature ,plays a critical role
in providing the data necessary for Pharmacovigilance to take place.
 In order to market or to test a pharmaceutical product in most countries , Adverse event data
received by the licence holder must be submitted to the local drug regulatory authority.
AIM & OBJECTIVE
 To improve the patient care and safety.
 To improve the public health and safety.
 To contribute to the assessment of benefit , harm, effectiveness, and risk of medicines.
 To promote education and clinical training.
 To promote rational and safe use of medicines.
 To support regulatory agency in the decision making process on use of medications
 To generate evidence based information on safety of medicines.
PHARMACOVIGILANCE IN INDIA
 The first recognised attempt to start PV activities in India, in 1986.
 In 1997, India joined the WHO’s ADR monitoring programme based in Uppsala Monitoring
Centre(UMC), Sweden.
 It considered of three centres in India for ADR monitoring .
 All India Institute of Medical Science (AIIMS),King Edward Memorial Hospital (KEM),Aligarh Muslim
University (AMU).
National pharmacovigilance programme
 The ministry of family welfare in India initiated the NPP (2005)
 It is coordinated by the central drug standard control organization (CDSCO)
 Programme was started with 2 zonal and 5 regional and 24 peripheral centres.
Pharmacovigilance Programme of India(PvPI)
 The programme NPP was renamed as PvPI ,it was initiated with AIIMS, New Delhi as National
coordination center (NCC) for monitoring ADR in the country.
 The PVPI is under the control of
 CDSCO
 Directorate general of health services
 Indian Pharmacopeia Commission (IPC), Ghaziabad as NCC
CDSCO Headquarter
the CDSCO HQ is responsible for;
 Taking appropriate regulatory decisions and action regarding drug safety.
 Propagating medicine safety related decisions to stakeholders
 Provide administrative and technical support to run PVPI.
How to report
 All HCPs can report the ADR by using the “suspected Adverse Drug Reaction Reporting form
"to report any ADR.
 Forms are available in all AMC( Adverse drug reaction Monitoring Centres).or download from
www.ipc.gov.in or www.cdsco.nic.in
 The filled reporting forms can be submitted to the AMC or directly to the NCC.
 A reporter can also mail the form at pvpi.ipcindia@gmail.com
CONCLUSIONS
 Post marketing surveillance is defined broadly as any information-gathering activity that is
performed after product approval.
 Post marketing surveillance is the practice of monitoring the safety of pharmaceutical drug
which is on the market.
 Post marketing surveillance uses a number of approaches to monitor the safety of licenced
drugs, including spontaneous reporting, controlled clinical trial, cohort studies, case control
studies.
 Pharmacovigilance is the science and activities relating to the detection, assessment ,
understanding , and prevention of adverse effects or any other drug related problems .
 UMC( Uppsala monitoring centre )is known as the global Pharmacovigilance centre .
REFERENCE
1. FDA post marketing drug safety surveillance
2. Gelenberg A.J ..post marketing surveillance –prospective of journal editor, National Centre for Biotechnology
information, National medicine library 10-32
3. Generic drug product development by Leon Shargel and Isadore Kanfer
4. Brian L strom,G.Pvelo-Drug Epidemiology and post marketing surveillance , second edition , page number 198-205
5. www.who.umc.org
6. www.ipc.gov.in
7. www.Chemtech-online.com
8. www.fda.gov.in
9. www.google.com
Thankyou!