ANTIDIABETIC
DRUGS
ANTIDIABETIC DRUGS
Classification and the nomenclature of diabetes mellitus (DM):
DM is a chronic metabolic disorder characterised by a high blood
glucose concentration-hyperglycemia (fasting plasma glucose > 7.0
mmol//L, or plasma glucose > 11.1 mmol/L 2hr after a meal) -
caused by insulin deficiency, often combined with insulin resistance.
ANTIDIABETIC DRUGS
Hyperglycemia occurs because of uncontrolled hepatic glucose output and
reduced uptake of glucose by skeletal muscle with reduced glycogen
synthesis. When the renal threshold for glucose reabsorption is exceeded,
glucose spills over into the urine -glycosuria and causes an osmotic diuresis -
polyuria, which in turn, results in dehydration, thirst and increased drinking
– polydipsia.
Diabetic ketoacidosis is an acute emergency- it develops because of
accelerated fat breakdown to acetyl-CoA, which, in the absence of aerobic
carbohydrate metabolism, is converted to acetoacetate and beta-
hydroxybutyrate (which cause acidosis) and acetone (a ketone)
Various complications develop as a consequence of the metabolic derangements in
DM, often over many years
Many of these are the results of disease of blood vessels, either large (macrovascular
disease) of small (microangiopathy).
Macrovascular disease consists of acclerated atheroma, which is much more common
and severe in diabetic patients.
Microangiopathy particularly affects the retina (blindness), kidney (chronic renal
failure) and peripheral nerves (diabetic neuropathy,which is associated with
accumulation of osmotically active metabolites of glucose.
Coexisting hypertension promotes progressive renal damage.
ANTIDIABETIC DRUGS
Classification and the nomenclature of diabetes mellitus (DM):
Type 1 diabetes encompasses cases resulting from pancreatic
B cell destruction (immune-mediated in most cases).
Type 2 diabetes consists of combined defects of insulin
secretion and action ranging from predominantly insulin
resistance with relative insulin deficiency to a predominantly
secretory defect with insulin resistance.
• Type 1 diabetes (DM1) - is a severe form associated with ketosis
in the untreated state. It occurs most commonly in juveniles
but occasionaly in adults, the nonobese. It is a catabolic
disorder form in which circulating insulin is virtually absent,
plasma glucagon elevated, and the pancreatic B cells fail to
respond to insulinogenic stimuli.
• Type 2 diabetes (DM2) - represents a heterogenous group
comprising milder forms of DM that occur predominantly in
adults. Circulating endogenous insulin is often subnormal or
relatively inadequate because of tissue insensitivity. Obesity,
which generally results in impaired insulin action, is a common
risk factor, and most patients with DM2 are obese. In addition to
tissue insensitivity to insulin, there is an accompanying
deficiency of the pancreatic B cells´s response to glucose
Oral hypoglycemic agents
Biguanides
Sulfonylureas
Meglitidines
Thiazolidinediones
Alpha-glucosidase inhibitors
Oral hypoglycemic agents
Biguanides -Metformin
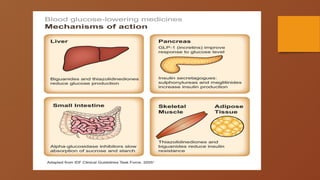
Lowers blood glucose- increases glucose uptake and utilisation in muscle + reduces hepatic
glucose production (gluconeogenesis)
Adverse effects:
- GIT disturbancies (anorexia + weight loss, diarrhea) = transient
- lactic acidosis rare but potencially fatal
Metformin should be avoided in patients who predispose to lactic acidosis (renal and
hepatic disease, heart failure…)
Use: DM2, patients obese and who fail treatment with diet alone. It does not cause
hypoglycemia
BIGUANIDES (metformin)
• MECHANISM OF ACTION
• exerts its effect by activating adenosine monophosphate (AMP)
kinase in the hepatocytes, an important enzyme in metabolic
control: hepatic glucose production (gluconeogenesis)
↓
- ↑ glucose uptake and utilization in skeletal muscles (reduce insulin
resistance)
- ↓ carbohydrate absorption
- ↑ fatty acid oxidation
- ↓ circulating LDL and VLDL
Cont.
• UNWANTED EFFECTS AND CONTRAINDICATIONS
- Gastrointestinal disturbaces most common = 30%
( anorexia, diarrhoea, nausea, Flactulence, bloating)
- Lactic acidosis is rare but fatal : should be avoided in
patients with renal / hepatic disease/ hypoxic pulmonary
disease or shock
- Long term use may interfere with absorption of vit B12
Oral hypoglycemic agents
Sulfonylureas
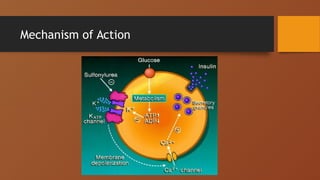
stimulate insulin secretion by B-cells (the equivalent of phase 1-
secretagogues) and thus reducing plasma glucose.
Pharmacokinetics:
. well absorbed orally,
. all bind strongly to plasma albumin and compete for these binding
sites with salicylates and sulfonamides,
. most are excreted in the urine  their action is increased in
the elderly and in patients with renal disease
. cross the placenta  severe hypoglycemia at birth
s. are generally contraindicated in pregnancy
Mechanism of Action
Cont.
ADVERSE EFFECTS
• Weight gain
• Hypoglycemia (chlorpropamide, glibenclamide)
• GI symptoms
• Skin eruptions
• Bone marrow suppression
CLINICAL USE
• Type 2 diabetes
Cont.
CONTRAINDICATIONS
• Renal impairment
• Severe liver dysfunction
• Caution in elderly
• Allergies
DRUG INTERACTIONS
• NSAIDs
• Monoamine oxidase inhibitors
• Antibacterial (trimethoprim, sulfonamides, chlorampenicol)
Doses
Glibenclamide: Starting dose 2.5 mg once daily; maximal dose 15 mg daily. Doses
exceeding 10 mg per day to be given in two divided doses.
Gliclazide: Starting dose 40 mg once daily; maximal dose 320 mg daily. Doses
exceeding 80 mg per day to be given in two divided doses.
Gliclazide modified-release: Starting dose 30 mg once daily; maximal dose 120 mg
once daily.
Glimepiride: Starting dose 1 mg daily; maximal dose 6 mg once daily.
Glipizide: Starting dose 2.5 mg once daily; maximal dose 40 mg daily. Doses
exceeding 15 mg per day to be given in two divided doses.
Oral hypoglycemic agents
First
generation:
Tolbutamide
Second
generation:
glibenclamide,
glipizide
Oral hypoglycemic agents
Meglitidines
• A new class of insulin secretagogues modulates B
cell insulin release by regulating potassium efflux
through the potassium channels
• Repaglinid has a very fast onset of action, with a
peak concentration and peak effect within
approximately 1 hour after digestion.
Oral hypoglycemic agents
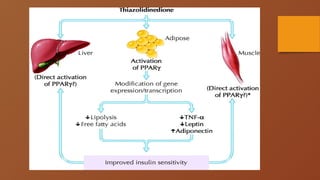
Thiazolidinediones
a recently introduced class of drugs that enhance target tissue insulin
sensitivity- rosiglitazone, pioglitazone
Their main action is to diminish insulin resistance by increasing glucose uptake
and metabolism in muscle and adipose tissues.
Alpha-glucosidase inhibitors
Acarbose and miglitol are competitive inhibitors of the
intestinal enzymes and modulate the postprandial digestion and absorption of
starch and disacharides.
ADVERSE EFFECTS AND CONTRAINDICATIONS
• Weight gain
• Fluid retention
• Increased risk of fracture with chronic use
• Headache, fatigue, GI symptoms
• Cardiovascular complications
• Contraindicated in pregnancy/ breastfeeding women,
ALPHA-GLUCOSIDASE INHIBITORS
• Acarbose
• MECHANISIM OF ACTION
- Competitively inhibits alpha glucosidase on the brush
border of the small intestine. This inhibits the conversion
of complex carbohydrates into monosaccharides, and
results in a reduction and delay in the absorption of
glucose
ADVERSE EFFECTS AND DOSING
• GI symptoms : Flactulence, diarrhoea, bloating, abd pain
• may aggravate hypoglycaemia caused by sulphonylureas and
insulin.
• Start with 50 mg once daily with meals, and increase by 50
mg every two weeks if tolerated. The maximum dose is 100
mg three times daily,
Oral hypoglycemic agents
Clinical uses of oral hypoglycemic drugs:
• DM2 as a supplement to diet and excercise to reduce
symptoms from hyperglycemia
• Metformin is preferred for obese patients unless
contraindicated by factors that predispose to lactic
acidosis
• Drugs that act on the sulfonylurea receptors are well
tolerated but often promote weight gain.